
Karteikarten
Opthamology: Conditions Causing Acute Loss Of Vision (Stroke, GCA, Central Retinal Artery and Vein Occlusion, Vitreous Haemorrhage, Retinal Detachment)
Karten in diesem Stapel (13)
- 1Stroke, causing acute loss of vision, is usually an occlusion of which arteries?Vertebral, basilar, posterior cerebral, occipital cortex.
From lecture notes: https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 2What patterns of visual loss are typically seen in stroke?Bilateral, hemianopic, +/- macular sparing.
K & C p1099 & https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 3GCA - what is it? S & Sx?* Inflammatory arteritis of large cerebral arteries (occurs in association with PMR - 50%)
* Occular emergency as can affect opthalmic artery leading to sudden loss of vision
* Usually affects >50 YO
* Sx:
> +++ Headache
> Scalp/temple tenderness
> Jaw claudication
* OE there may be RAPD, pale swollen disc, pale ischaemic retina
K & C p543 & https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 4Ix & Rx of GCA.* Start Rx before Ix - remember possibility of vision loss!
* Prednisolone PO 60-80 mg or methylprednisolone IV 0.5-1.0 g
* BD's - ^CRP & ESR (ESR may be normal in 20%), platelets often^
* Temporal artery biopsy - definitive Ix but time consuming & can get false -ve
* Long term - prednisolone needs to be tapered over 12-18/12. Beware SE's - osteoporosis, DM, HT, infxn (co-prescribe bone & gastric protection).
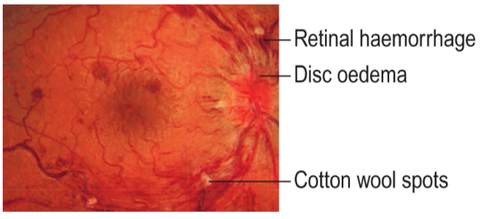
K & C p543 & https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 5Central retinal vein occlusion - who gets it, S & Sx, & Rx.* Thrombus of central retinal vein obstructs outflow of BD -> ^intravascular pressure.
* Dilated veins, retinal haemorrhage, cotton wool spots, retinal oedema (see following slide).
* Sudden, painless, monocular vision loss ('like a curtain closing' - occuring in seconds).
* Risk factors - age (>60 YO), HT, CVD, DM, glaucoma, hypercoagulability.
* Rx - anti-VEGF, retinal laser.
From lecture: https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 6—Central retinal vein occlusion.
K & C p1063 - 7Central retinal artery occlusion (CRAO) - who gets it, S & Sx, & Rx.* CRAO -> arteries narrowed, retina becomes opaque & oedematous, cherry red spot seen over fovea, usually RAPD (see following card).
* Arteriosclerotic emboli (HT/carotids) most common cause.
* Sudden, painless, monocular vision loss ('like a curtain closing' - occuring in seconds).
* Temporary CRAO = retinal TIA (aka amaurosis fugax).
* Need to rule out GCA - esp in >60 YO.
* No proven Rx.
* Stroke/TIA work-up.
K & C p1063 & https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 8—Central retinal artery occlusion.
K & C p1063.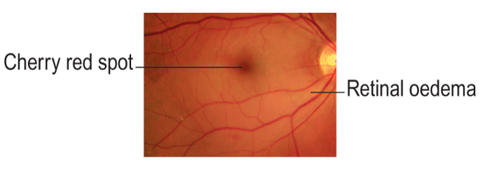
- 9What are some causes of vitreous haemorrhage? S & Sx?May be secondary to:
* Trauma
* Proliferative retinopathy - esp diabetic, also other causes of neovascularisation - eg occlusions.
* Retinal tear/detachment - may rupture BD vessels.
S & Sx:
* Painless monocular loss of vision - 'all blurry/hazy'.
* Often starts as floaters/blobs.
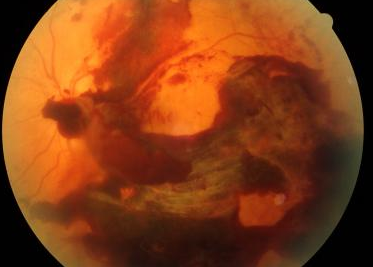
* Absent red reflex, poor/no fundal view, no RAPD.
From lecture: https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 10Ix & Rx of vitreous haemorrhage.* USS of eye to check retina flat/without tears
* Usually self-resolving in 6-8/52
* If non-resolving then virectomy
* If recurrent in proliferative diabetic retinopathy then retina may need fully lasering
From lecture: https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 11—Vitreous haemorrhage.
- 12What is the most common cause of retinal detachment? S & Sx & Rx?Posterior vitreous detachment (PVD)- with age the vitreous becomes liquified, lacunae appear which reduce shock absorption. Vitreous collapses.
* PVD Sx:
* Floaters & flashes (retinal stimulation from traction)
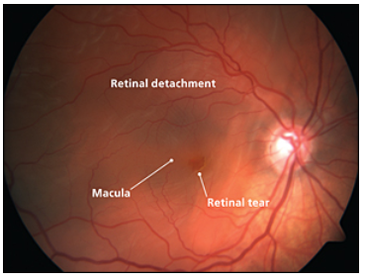
10% develop a tear which can then allow fluid behind the retina causing detachment (RD).
RD Sx:
* Black curtain/loss of vision progressing across visual field over hours to days. Blindness if not Rx.
Risk factors:
* Myopia
* Trauma
* Inflammation
* Connective tissue disorders
OE:
* Field loss
* RAPD
* Visible detachment on fundoscopy
Rx:
* Retinal surgery - vitrectomy/cryotherapy/gas
From lecture: https://www.dropbox.com/home/P-Year%20Surgical%20Lectures?preview=Ophthalmology+notes.pdf - 13—Retinal tear.
Informationen
- Beschreibung
- SGUL LOB's for Opthamology: Conditions Causing Acute Loss Of Vision (Stroke, GCA, Central Retinal Artery and Vein Occlusion, Vitreous Haemorrhage, Retinal Detachment).
- Erstellt von
- Andrew Street
- Aufrufe
- 65
- Tags
- Bewertung