
Mindmap
Septic Shock
Inhalt der Mindmap
Septic Shock
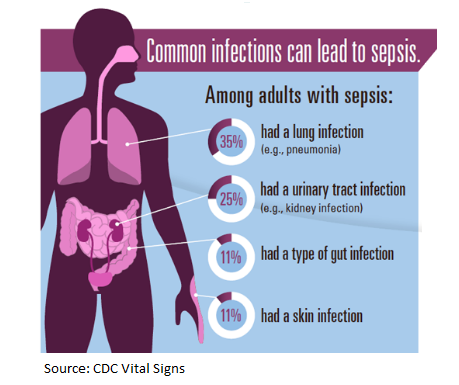
Sepsis is the simultaneous activation of systemic inflammation and coagulation due to microbial invasion
- Septic Shock
- Characterized by maldistribution of blood flow and arterial hypotension (systemic arterial pressure <90mmHg), leading to respiratory, heart and failure of other organs, and death
- Septic Shock
Diagnosis
- Pathophysiology
- Invading microorganisms
- Activation of CNS and endocrine systems
- Hypermetabolic state
- Decreased tissue perfusion
- Cellular oxygen demand
- Release of pro-inflammatory cytokines (TNF, IL-1, etc.)
- Myocardial depression, peripheral vasodilation, increased capillary permeability, microemboli, selective vasoconstriction
- Impaired cellular metabolism
- Maldistribution of circulating blood volume
- Decreased cellular oxygen supply
- Decreased tissue perfusion
- Myocardial depression, peripheral vasodilation, increased capillary permeability, microemboli, selective vasoconstriction
- Endothelial damage
- Increased membrane permeability
- Microemboli
- Activation of CNS and endocrine systems
- Invading microorganisms
- Diagnostic Studies
- Blood
- Low Hgb
- Anemia
- Abnormal glucose levels
- ↑ WBC Count
- Prolonged PT and PTT
- ↑BUN/Cr
- (+) blood cultures
- Low Hgb
- Urine
- ↑ Specific gravity
- ↑ Osmolarity
- Serum Electrolytes
- ↑ Serum Lactate Levels
- ↑ Liver Enzymes (ALT, AST, GGT)
- K+ imbalances
- Na imbalances
- Blood
- Etiology
- Risk Factors
- Major surgery, chronic disease, long-term hospital stay, predisposition to infections, poor nutrition
- Immunosuppressed
- Clients on immunosuppressive agents, males, infants, pregnant women, older adults
- Risk Factors
- Pathophysiology
Nursing Care
- Assessment
- 1) Initial Stage
- Metabolism changes at cellular level
- Aerobic to anaerobic
- Lactic acid buildup
- Aerobic to anaerobic
- Not clinically apparent
- Metabolism changes at cellular level
- 2) Compensatory Stage
- SNS:↑HR, ↓BP due to ↓CO and narrowing pulse pressure
- ↑ pro-inflammatory mediators
- Epinephrine/norepinephrine to increase BP
- Massive vasoconstriction (↑SVR)
- Epinephrine/norepinephrine to increase BP
- Blood flow maintained to vital organs, e.g. heart and brain
- Shunting of blood flow
- Skin is cool and clammy, ↓peristalsis, causing paralytic ileus, ↓gas exchange., ↑dead space l/t VQ mismatch
- Arterial O2↓ and RR/depth↑
- Skin is cool and clammy, ↓peristalsis, causing paralytic ileus, ↓gas exchange., ↑dead space l/t VQ mismatch
- Shunting of blood flow
- ↑ pro-inflammatory mediators
- Neurological status
- Agitation, Restlessness
- RAAS activation
- ↑CO, ↑BP, ↑venous return, ↑Na/H2O reabsorption and secretion of K+
- Attempts to maintain homeostasis and tissue perfusion and overcome anaerobic metabolism
- SNS:↑HR, ↓BP due to ↓CO and narrowing pulse pressure
- 3) Progressive Stage
- ↓ cellular perfusion and altered capillary permeability
- Leaking of fluids and proteins into interstitial space
- Interstitial edema
- Leaking of fluids and proteins into interstitial space
- Prevent organ failure
- Pulmonary initially affected
- Systemic edema, bronchoconstriction and decreased surfactant production
- Increased PA pressure d/t decreased blood flow and SNS stimulation
- Blood flow to pulmonary capillaries decreases and V/Q mismatch increases
- Cardiovascular
- Ischemia in distal extremities, Increased risk of MI/dysrhythmia, weak PP, Decreasing BP
- Gastrointestinal
- Decreased blood flow increases risk for ulcers and bleeding, and decreases absorption
- Other Systems
- Decreased mental functioning Confusion, altered LOC, restlessnessLiver failure l/t decreased metabolism and excretion of waste products and drugs; increased ALT/AST
- ↓ cellular perfusion and altered capillary permeability
- 4) Refractory Stage
- ↑Peripheral vasoconstriction and ↓CO
- Exacerbated anaerobic metabolism
- Lactic acidosis
- Increased permeability
- Leaking of fluids and proteins into interstitial space
- Increased permeability
- Lactic acidosis
- Exacerbated anaerobic metabolism
- Decreased cerebral blood flow
- Cerebral ischemia
- Decreased coronary blood flow
- Myocardial depression
- ↑Peripheral vasoconstriction and ↓CO
- 1) Initial Stage
- Planning
- Adequate tissue perfusion
- Restoring normal or baseline BP
- Recovery of organ function
- Avoiding prolonged states of hypoperfusion
- Implementation
- Acute
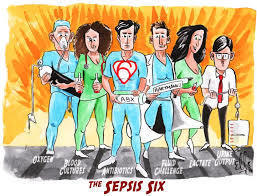
- The Sepsis Six
- 1. Give 02 to keep sats above 94%
- 2. Take blood cultures
- 3. Give antibiotics
- 4. Give a fluid challenge
- 5. Measure lactate
- 6. Measure urine output
- ROS
- Neurological
- Monitor physical and emotional status and assess for orientation and LOC q1hr
- Cardiological
- Vascular IV access, assess VS (BP, HR, CVP) frequently, ECG monitoring, capillary refill, monitor hemodynamic status, auscultate S3/S4, palpate peripheral pulses
- Respiratory
- HOB 30-45°, chest radiography, maintain clear airway, frequent suctioning, mechanical ventilation, assess ABGs levels, LS/VS (RR, depth, rhythm, SaO2 q1hr), monitor oxygenation,
- GI/GU
- Assess: BS q1hr, abdominal distention, renal output (>0.5ml/kg/hr), BUN/Cr levels and check for occult blood in NG/stool
- Integumentary:
- Assess for. diaphoresis, cyanosis, pallor, edema, T° q1hr
- Neurological
- Personal Hygiene
- Prevent skin breakdown and infection, assess swallowing and gag reflex Frequent oral care
- The Sepsis Six
- Health Promotion
- Prevention
- Prevent Complications
- LMW heparin & VTE prophylaxis
- Identify patient at risk
- Decrease risk of infections
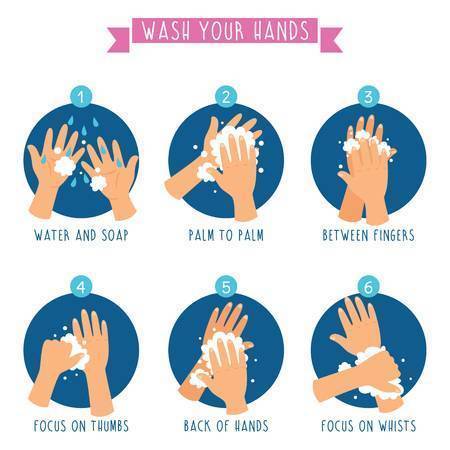
- Effective hand hygiene
- Aseptic technique during invasive procdures
- Equipment change as per institutional policies
- Prevent Complications
- Monitor fluid balance, pain management, adequate rest, reposition q2hr, encourage family members in pt care
- Therapeutic Communication
- Non-verbal
- Prevention
- Acute
- Evaluation
- Systemic Inflammatory Response Syndrome (SIRS)
- Characterized by ↑inflammation/coagulation not always related to infection
- Multiple Organ Dysfunction Syndrome (MODS)
- Physiological deterioration of individual organs
- Systemic Inflammatory Response Syndrome (SIRS)
- Assessment
Complications
- GI bleeding
- Pressure/Stress Ulcer
- Electrolyte Imbalance
- ARDS
- Anemia
- Pneumonia
- AKI
- Hyperglycemia
- Bacteremia
- DIC
- DVT
Treatment
- Fluid Therapy
- Volume management-maintain BP and stabilize blood circulation
- Crystalloids
- Isotonic Solutions (0.9% NaCl, LR)
- Monitor for circulatory overload, Increases intravascular volume, NS only for pts with liver failure
- Hypertonic Solutions (1.8%, 3%. or 5% NaCl).
- Leads to rapid volume expansion. Monitor for hypernatremia.
- Isotonic Solutions (0.9% NaCl, LR)
- Colloids e.g. albumin, dextran
- Monitor for circulatory overload in albumin & monitor for bleeding and hypersensitivity wth dextran
- Blood Products (e.g. packed RBC, whole blood, plasma/ FFP)
- Increase O2-carrying capacity
- Crystalloids
- IV bolus of NS
- If pt remains hypotensive, insert CVAD
- Volume management-maintain BP and stabilize blood circulation
- Oxygen
- Mechanical ventilation
- PaO2 between 80-100mmHg
- PEEP
- increases CO by increasing heart contractility and reducing afterload
- Nutrition and Metabolic Management
- Monitor plasma transferrin and prealbumin levels to monitor hepatic protein synthesis
- Enteral nutrition should be initiated
- If cannot be used then initiate parenteral
- Monitor glucose levels, should be less than 8.33 mmol/L
- Protein-calorie malnutrition is one of the primary manifestations of hypermetabolism and MODS
- Encourage high protein diet
- Pharmacotherapy
- Antibiotic Therapy
- Asses blood/urine/sputum cultures to help treat infections
- Broad spectrum, followed by specific antibiotics
- Administer within the first 6hrs for best possible outcome
- E.g. azithromycin, ciprofloxacin, pipercillin, etc.
- Vasopressors
- Norepinephrine
- Increases BP and MAP for hypotensive pts.
- Administer via CVAD
- Monitor dysrhythmias
- Dobutamine
- Increases contractility and decreases diastolic volume
- Corrects hypovolemia
- Administer via CVAD
- Monitor HR, BP and for tachydysrhythmias
- Norepinephrine
- Patient comfort
- Address pain, e.g. fentanyl
- Address anxiety and fear
- Encourage family to be involve in pt care
- Antibiotic Therapy
- Fluid Therapy
Client Centred Care
- Open and therapeutic communication between patient and healthcare team
- Treatment, care and care information should be culturally appropriate
- Patient, family/caregivers should be given the opportunity to make informed decisions about healthcare
- Patient and family goals should be established early in treatment
- If patient recovers from sepsis....
- Healthcare team should educate and provide patient with resources for good mental health post-sepsis
- Healthcare team should explain post-sepsis issues to family members/care givers, e.g. cognitive, physiological changes, etc.
- Educate patient on how to prevent infections
Bilder und Dateien der Mindmap










Informationen
- Beschreibung
- Mindmap am Septic Shock, erstellt von Savvy Modgil am 06/03/2019.
- Erstellt von
- Savvy Modgil
- Aufrufe
- 11
- Bewertung