
Quiz
Abdominal Pathologies :)
Dieses Quiz enthält Fragetypen, die sich im gewohnten Player öffnen.
Fragen in diesem Quiz (55)
1BG:
48 year old female with 2 children
Hypertension- well controlled with Amlodipine
-Irritable bowel syndrome (15 year history) on Mebeverine
-Menorrhagia- vaginal hysterectomy 2 years ago
2 month Hx worsening bowels-
Alternating diarrhoea/constipation
Associated lower abdominal pain
Exam:
alert, afebrile, BP 132/70, HR 70, reg
Abdomen: mildly distended but soft non-tender (SNT), no masses, bowel sounds present
FHx: Sister- breast cancer aged 48
Aunt- breast cancer aged 61
What is the next management step would you advise for this patient?- AAdmit urgently
- BPelvic Exam
- CRefer urgently
- DReassure probably just IBS
- ERefer routinely and keep a close eye
- FCardiorespiratory exame
- GUrine anaylsis
- HFBC
2BG: 53 year old male, Vetenarian,
MHx – hypertension
PC: Agreed routine review to discuss blood results
Notable results:
Bili 131 (15-73)
GGT 432 (15-73)
ALP 505 (30-130)
ALT 3017 (21-72)
Eventually got hold of him 10 days later- he was on holiday!
Whilst away admitted to a couple days when urine slightly darker and stools paler but since resolved
Approx 5 units/week alcohol
Reviewed in clinic:
No abdo pain, no stigmata liver disease
Exam: obs stable, sclera slightly jaundiced, abdomen soft, nontender, no hepatosplenomegaly
What is(are) the most appropriate next step(s)?- ARefer routinely
- BRefer urgently
- CAdmit urgently
- DFull Liver Screen
- ERepeat LFTS
- FCaeruloplasmin Serum levels
- GAutoimmune profile
- HHepatitis Screen
- IRepeat Blood tests
- JGallbladder ultrasound
3Same Patient:
blood tests repeated: Improving LFTs-except ALT still elevated
Liver Screen: all negative but Hepatits Screen:
Hep A: IgG + and IgM -
Hep E: IgG + and IgM +
What is a correct interpretation of these results?- AIgM + means that newly exposed to the pathogen
- BIgG+ means that newly exposed to the pathogen
- CIgM- that newly exposed to the pathogen
4What are possible differential diagnoses of raised ALT?
- AAlcoholic liver disease
- BWilsons
- CViral hepatitis
- DCeliac
- EAlpha 1 Antitrypsin deficiency
- FHemochromatosis
- GCertain drugs
- HNonalcoholic fatty liver disease
- INelson's disease
- JRenal Failure
5Abdominal Examination findings:
Pain in the foregut ( [blank_start]esophagus[blank_end] to mid-duodenum, liver, [blank_start]gallbladder[blank_end], spleen, 1/2 [blank_start]pancreas[blank_end]) can be felt in the [blank_start]epigastric[blank_end] region.
Pain in the midgut (mid-duodenum to [blank_start]proximal[blank_end] 2/3 transverse colon and 1/2 [blank_start]pancreas[blank_end]) can be felt in the [blank_start]umbilical[blank_end] region.
Pain in the hindgut ([blank_start]distal[blank_end] 2/3 of transverse colon to 1/2 of [blank_start]anal[blank_end] [blank_start]canal[blank_end]) is usually in the [blank_start]pubic[blank_end] region.- Aesophagus
- Bgallbladder
- Cpancreas
- Dpancreas
- Eproximal
- Fdistal
- Ganal
- Hcanal
- Iumbilical
- Jepigastric
- Kpubic
6Any gynae problem, always do a pregnancy test first.
- ARichtig
- BFalsch
724 year old presents complaining of a 2 day history of abdominal pain, vomiting and diarrhoea. He had made some stir fried rice for dinner 3 days ago and forgot to put it in the fridge. He has had no recent travel and is otherwise fit and well. A diagnosis of gastroenteritis is made.
What is your most likely causative organism?- ACampylobacter
- BCholera
- CE. Coli
- DBacillus Cereus
8Always seek urgent specialist advice whenever a child or elderly are reported to have has a single episode of bloody diarrhoea
- ARichtig
- BFalsch
9Management of acute diarrhea and gastroenteritis:
Conservative: Fluids and [blank_start]electrolytes[blank_end]
Medical: [blank_start]Antibiotics[blank_end] (if [blank_start]systematically[blank_end] unwell) and whould be based off of [blank_start]stool[blank_end] culture results- Aelectrolytes
- BAntibiotics
- Csystematically
- Dstool
10A 27 year old lady presents to you with a 6 month history of abdominal pain and bloating after meals. Her pain is relieved after defecation. She is also suffering from alternating diarrhoea and constipation and feels like she hasn’t emptied her bowels properly. She is very distressed about her symptoms as it is affecting her personal and work life.
What is your main differential?- AHyperthyroidism
- BIrritable Bowel Syndrome
- CEndometriosis
- DInflammatory Bowel Disease
11[blank_start]Irritable[blank_end] [blank_start]bowel[blank_end] [blank_start]syndrome[blank_end] is a common chronic functional disorder of the bowel causing abdominal cramps, bloating, constipation and/or diarrhea. Most common is [blank_start]women[blank_end] in their 20-30s.
- Awomen
- BIrritable
- Cbowel
- Dsyndrome
12What is NOT a potential reason for irritable bowel syndrome?
- Aoveractive bowel
- Bincreased visceral hypersensitivity
- Cshort chain carbohydrates in diet
- Dpost-parturition incontinecne
13Irritable bowel syndrome is diagnosed if there is at least a [blank_start]6[blank_end] month history of abdomen pain, [blank_start]altered[blank_end] bowel habit, and [blank_start]bloating[blank_end]. The diagnosis is official if the abdominal pain is relieved by [blank_start]defecation[blank_end] or linked to altered bowel habit and AT LEAST 2 OF:
passage of [blank_start]mucus[blank_end]
altered stool passage (urgency, frequency, [blank_start]tenesmus[blank_end])
abdominal bloating
symptoms worsened by [blank_start]eating[blank_end]
On examination, the abdomen is usually normal with some generalized [blank_start]tenderness[blank_end]- Atenderness
- B6
- Caltered
- Dbloating
- Edefecation
- Fmucus
- Gtenesmus
- Heating
14What are ways to generally investigate for irritable bowel syndrome?
- AFull blood count
- BESR (erythrocyte sedimentation rate)
- CC reactive protein
- DTTGA
- Efecal calprotetectin
- FCA125
- GCA173
- Himaging
- IHepatitis C
- Jhcg
15Main managements of IBS is dietary changes, peppermint old, and (if needed) loperamide
- ARichtig
- BFalsch
16Buscapan can be given for irritable bowel syndrome.
- ARichtig
- BFalsch
17A 45 year old gentleman presents with 7 month history of abdominal pain and unintentional weight loss. He has been feeling more tired lately and has noticed he has become increasingly paler. He has a PMH of asthma and coeliac disease. He explains that his father and his brother also experienced similar symptoms and were subsequently diagnosed with colorectal cancer.
What is your main differential?- AIrritable bowel syndrome
- BColorectal cancer
- CCrohn's disease
- DUlcerative Colitis
18IBD and HNPCC put you at increased risk for colorectal cancer
- ARichtig
- BFalsch
19What are these symptomatic of?
Often colicky pain
Rectal bleeding
Bowel obstruction
Tenesmus
Mass in LIF
Early changes in bowel habit- Aleft colon cancers
- Bright colon cancers
- CHPNCC
- Dsmall cell colon cancers
- Efamilial colon cancers
20What are these symptomatic of:
Weight loss
Anemia
Occult bleeding
Mass in RIF- Aright colon cancers
- Bleft colon cancers
- CIBS
- Dsmall cell colon cancer
- Efamilial colon cancers
21Most common presentation of colorectal cancer:
[blank_start]rectal[blank_end] [blank_start]bleeding[blank_end]
[blank_start]persisting[blank_end] change in bowel habit
[blank_start]anemia[blank_end]- Aanemia
- Bpersisting
- Crectal
- Dbleeding
22Urgent referral for cancer pathway if the patient is aged 40 and over with unexplained weight loss and abdominal pain.
- ARichtig
- BFalsch
23How can you NOT investigate colorectal cancer?
- ABedside tests
- BLiver function test
- CUrea and Electrolytes test
- DThyroid function tests
- ECEA blood test
- FColonoscopy
- GBiopsy
- HFlexible sigmoidoscopy and barium enema
- IMRI
- JUltrasound
24The earlier the Duke stage (for ex: stage A vs stage B), the lower 5-year survival likelihood.
- ARichtig
- BFalsch
25How can you manage colorectal cancer?
- Achemotherapy
- Bpalliative therapy
- Cradiotherapy
- Dsurgery
- Emultidisciplinary team approach
- Fscreening
- Gdrugs
- Hbedside monitoring
26Bowel Cancer Screening Program:
In England, men and women between the ages of [blank_start]60[blank_end]-74 years take part
A bowel cancer testing kit is sent every [blank_start]2[blank_end] years
2 bowel cancer screening tests:
[blank_start]Fecal[blank_end] [blank_start]occult[blank_end] blood testing – home testing kit
Flexi-[blank_start]sigmoidoscopy[blank_end] – looking for polyps – one at age 55 years- A2
- B60
- CFecal
- Doccult
- Esigmoidoscopy
27Fill in the chart:
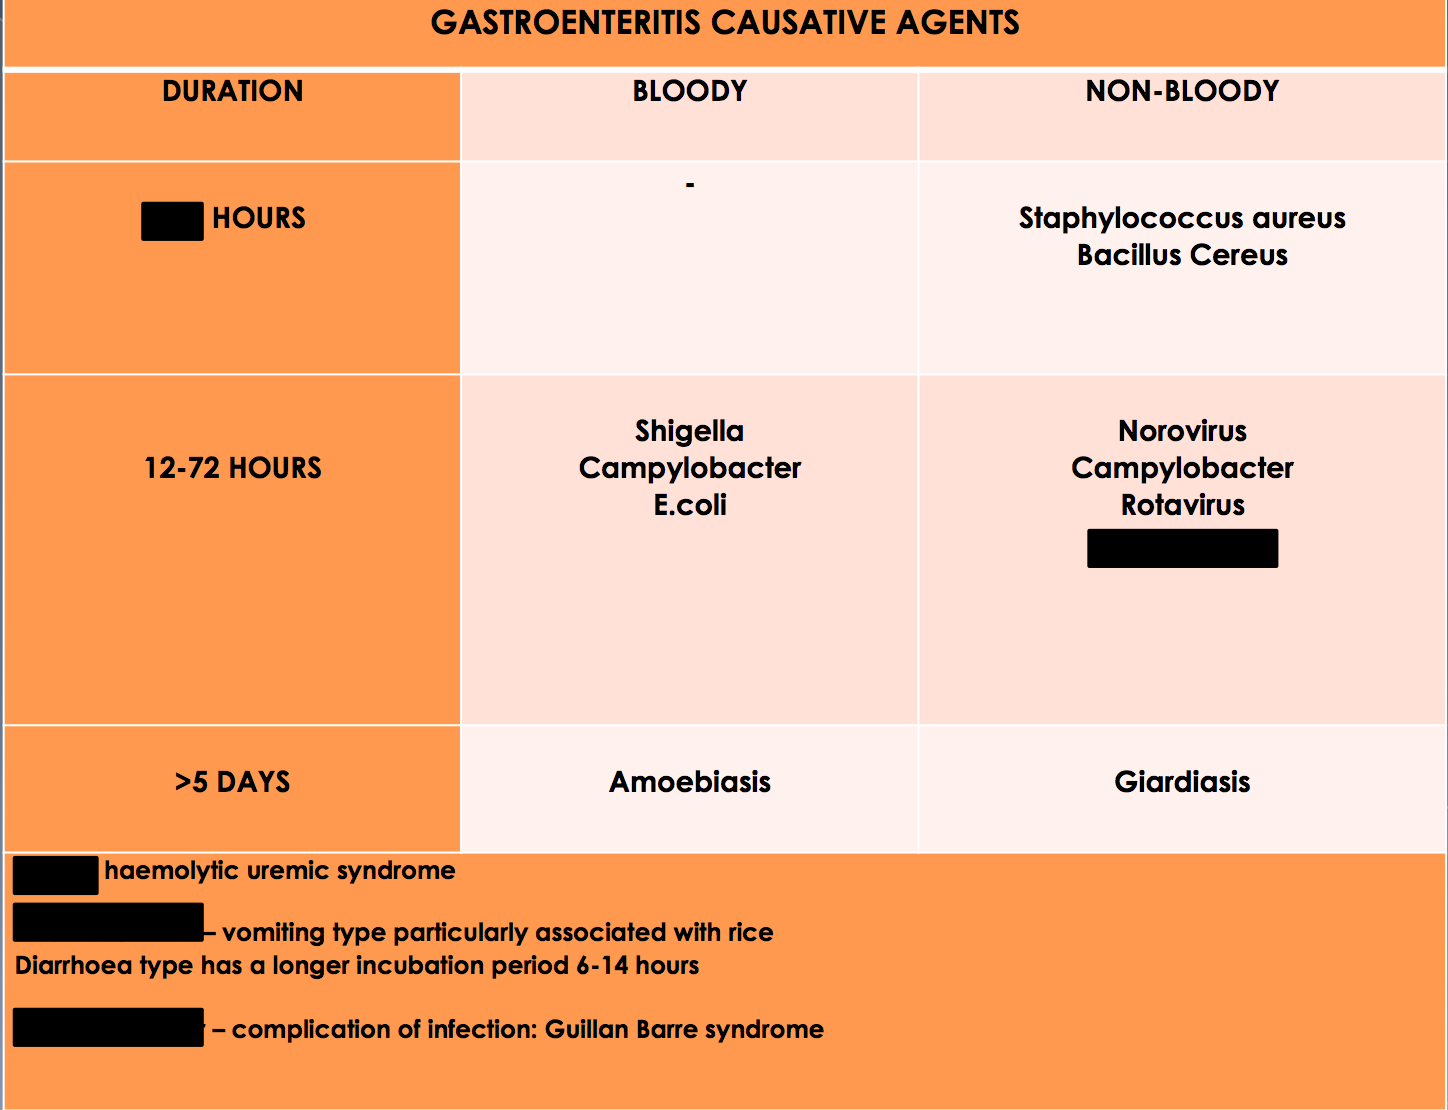
- A4-6
- Bsalmonella
- CE. coli
- DBacillus Cereus
- ECampylobacter
28Which is pelvic pain associated with?
- Agastrointestinal problems
- Bgynecological problems
- Cmusculoskeletal problems
- Durological problems
- Ecardiovascular problems
29What is true regarding Chlamydia trachomatis?
- Asmall gram negative
- Binfect columnar and transitional epithelium
- Csexually transmitted infection
- Dcauses infertility
- Emore common in younger adults
- Fasymptomatic
- Gsmall gram positive
- Hfebrile
- Iaffects cognitive functionality
- Jlies dormant before manifesting later in life
30Women with chlamydia present with dysuria and yellowish discharge and irregular bleeding
- ARichtig
- BFalsch
31Males with chlamydia present with epididymitis, hematuria, dysuria, discharge, and sudden bursts of weakness
- ARichtig
- BFalsch
32Investigations for chlamydia:
Male: [blank_start]first[blank_end]-catch [blank_start]urine[blank_end]
Female: [blank_start]vulvovaginal[blank_end] swab
Both samples are sent for NAATs ([blank_start]nucleic[blank_end] [blank_start]acid[blank_end] [blank_start]amplification[blank_end] test)- Afirst
- Burine
- Cvulvovaginal
- Dnucleic
- Eacid
- Famplification
33Chlamydia complications:
[blank_start]pelvic[blank_end] inflammatory disease, infertility, [blank_start]ectopic[blank_end] pregnancy
Treatments:
100mg [blank_start]Doxycycline[blank_end] (danger: [blank_start]teratogenic[blank_end]) or 1 gram stat [blank_start]Azithromycin[blank_end]- Ateratogenic
- BAzithromycin
- CDoxycycline
- Dectopic
- Epelvic
34Neisseria Gonnorhea is
Gram-[blank_start]negative[blank_end] diplococcus
Infects mucous membranes of the urethra, [blank_start]endocervix[blank_end], rectum, [blank_start]pharynx[blank_end] and conjunctiva
transmitted sexually or [blank_start]perinatally[blank_end]
Presentation:
Women:
[blank_start]Urinary[blank_end] [blank_start]Tract[blank_end] Infection
Discharge
[blank_start]Dysuria[blank_end]
Men:
Discharge: [blank_start]green[blank_end] and thick
[blank_start]dysuria[blank_end]- Anegative
- Bpharynx
- Cendocervix
- Dperinatally
- EUrinary
- FTract
- GDysuria
- Hgreen
- Idysuria
35Investigation for Gonnorhea:
Women: [blank_start]Pharynx[blank_end], vaginal, rectal swab
Men: Pharynx, [blank_start]urethral[blank_end], rectal swab- APharynx
- Burethral
36Ceftriaxone 500mg IM and Azithromycin 3G stat is how to treat gonnorhea.
- ARichtig
- BFalsch
37Which of these are complications of gonnorhea?
- Aurethral scarring
- Bpenile lymphangitis
- Cepididymitis
- Dprostatis
- Emiscarriage
- Fpre mature labor
- Ginfertility
- Hperlvic inflammatory disease
- Imeningtis
- Jischemic bladder
38What is the differential diagnosis for these symptoms?
lower abdominal pain
Deep dyspareunia
Abnormal vaginal bleeding and/or discharge
Right upper quadrant pain
Lower abdominal tenderness
Adnexal tenderness, cervical motion tenderness, or uterine tenderness
Abnormal cervical or vaginal mucopurulent discharge
Fever greater than 38°C- Agonnorhea
- Bchlaymdia
- Csyphilis
- Dinflammatory pelvic disease
- Edysmennorhea
- Finflammatory bowel disease
39[blank_start]Peri[blank_end]-[blank_start]hepatitis[blank_end] is the development of adhesions between the liver and the peritoneum, causing right [blank_start]upper[blank_end] quadrant pa
- Ahepatitis
- BPeri
- Cupper
40How do you manage pelvic inflammatory disease?
- Ascreen for STIs
- Bparacetamol
- Cibuprofen
- DOral ofloxacin/levofloxacin + oral metronidazole for 14 days
- ECeftriaxone as a single IM dose, followed by oral doxycycline + oral metronidazole for 14 days
- FOral cefixime as a single dose (off-label use), followed by oral doxycycline + oral metronidazole for 14 days.
- GAspirin
- HOral ofloxacin/levofloxacin or 14 days
- ICeftriaxone as a single IV dose, followed by oral doxycycline + oral metronidazole for 14 days
- JCeftriaxone as a single IM dose, followed by oral doxycycline for 14 days
41The most common cause of a UTI is E colli
- ARichtig
- BFalsch
42Obesity, poor bladder emptying, diabetes, kidney stones, and Vitamin E deficiency all put you at increased risk of a UTI.
- ARichtig
- BFalsch
43In a UTI, there will be increased urgency and frequency of urination despite it being painful due to the feeling of incomplete urination.
- ARichtig
- BFalsch
44What do you pay special notice for in a urinalysis of a UTI?
- Aleukocytes
- Bnitrates
- Cblood
- DpH
- Econcentration
- Fglucose
- Gammonia
45Which of these is not a possible complication of a UTI?
- ARenal abscess
- BSepsis
- CAcute kidney injury
- DPyelonephritis
- EFungal Vaginal infections
46Management of UTI:
[blank_start]Fluids[blank_end] (supportive)
Analgesia
1. [blank_start]Trimethoprim[blank_end]
2. [blank_start]Nitrofurantoin[blank_end]
for:
Women - [blank_start]3[blank_end] days
Men - [blank_start]7[blank_end] days- A3
- B7
- CFluids
- DTrimethoprim
- ENitrofurantoin
47While both occur shortly after menarche, there is no underlying pelvic pathology in primary dysmennorea like there is in secondary dysmenorrhea.
- ARichtig
- BFalsch
48Which of these may NOT be the reason for secondary dysmenorrhea?
- APelvic inflammatory disease
- BFibroids
- CAdhesions
- DEndometriosis
- EMeniere's disease
49[blank_start]Primary[blank_end] dysmennorhea is pain which begins just before menstruation and lasts up to [blank_start]72[blank_end] hours, progressively improving
- APrimary
- B72
50NSAIDS, analgesia and contraceptive pill is how to manage dysmenorrhea.
- ARichtig
- BFalsch
51You use ultrasounds and PAP smear tests to investigate for dysmenorrhea.
- ARichtig
- BFalsch
52Which of these are emergency findings related to dysmenorrhea?
- AAbnormal cervix
- Bpersistent bleeding
- Cpelvic mass
- Dabdominal mass
- Eultrasound suggesting cancer
- Fpositive pregnancy test
- Gdistended abdomen
53Contraception:
Starting the pill on day [blank_start]5[blank_end] or before protects from pregnancy straight away. Otherwise, patients will need additional contraception until taken for [blank_start]7[blank_end] days.- A5
- B7
54What is NOT true regarding the pill?
- Anot taking it at the same time everyday makes it less effective
- Bmissing a dose makes it less effective
- CVomiting makes it less effective
- DSevere diarrhea makes it less effective
- EIt is taken every day for 21 days, then stopped for 7 days
- FIt is not prescribed for those over the age 40
55If you forgot to take the pill yesterday, the missed pill should still be taken, even if it means taking two pills in today.
- ARichtig
- BFalsch
Informationen
- Beschreibung
- Content credits: GP soc presentations Charlotte Bennett Tabitha and Sandra Pippa Le Page
- Autor
- Gelöschter Nutzer
- Sprache
- English
- Aufrufe
- 17
- Verlauf
- Erstellt am 11 Mär 2018 · aktualisiert am 13 Mär 2018
- Schlagwörter
- Bewertung
- Noch keine Bewertungen Bewerte dieses Quiz