
Karteikarten
Diseases of Gnathic bones and TMJ
Karten in diesem Stapel (107)
- 1Idiopathic Osteosclerosis (Enostosis, dense bone island)-Asymptomatic focus of increased bone production
-Considered a variation of normal
-Tend to arise in 1st-2nd decade
-May remain static or enlarge until skeletal maturity
-Seen in tooth, or non-tooth bearing areas of the jaws
-Associated dentition vital
-Diagnosed clinically/radiographically w/ sequential radiographs as needed
-Root resorption seen rarely - 2Reported prevelance of idiopathic osteosclerosis5-10%
- 3Condensing/sclerosing osteitis-Identical radiographic appearance to idiopathic osteosclerosis
-Seen exclusively at apex of non-vital tooth
-represents reactive bone formation in response to pulpal/periapical inflammation - 4Cherubismpainless, self-limiting disorder characterized by:
-symmetric, bilateral expansion of the mandible (& maxilla)
-bone is replaced by fibro-osseous tissue w/ giant cells
-swollen, rounded cheeks
-interference of normal tooth eruption; impacted teeth
-gnathic expansion causes downward stretching of the skin, exposing the white sclera beneath the iris
-jaw enlargement continues throughout childhood; stabilizes during puberty and changes regress by early adulthood as normal bone remodeling occurs - 5Hypophosphatasia-rare metabolic bone disease characterized by ALPL mutations
-alkaline phosphatase levels in serum and bone low
-low enzyme levels results in impaired bone mineralization
-variable disease severity
>>perinatal lethal
>>infantile (50% die)
>>adult (mild phenotype)
>>odontophosphatasia - 6Odontophosphatasia-premature exfoliation of incisors only sign of disease
-most mild presentation of disease - 7Clinical features of hypophosphatasia-osteomalacia (bone pain/tenderness; fractures)
-Periodontal disease
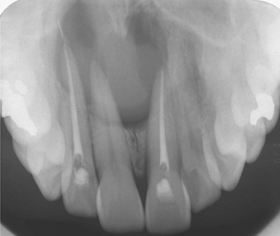
-Premature exfoliation of dentition (cementum does not form, PDL non-functional) - 8Nasopalatine duct cyst (incisive canal cyst)-Most common non-odontogenic cyst of the gnathic bones
-most common in 4th-5th decade
-Symmetric radiolucency between vital maxillary central incisors
>>may appear heart-shaped due to superimposition of the Ant. nasal spine
>>may cause root divergence - 9Paired incisive canals open into a single incisive foramen & transmit...-nasopalatine nerve (innervates palatal mucosa of incisors)
-terminal end of greater palatine artery (supplies nasal cavity)
-degenerated remnants of nasopalatine duct - 10Nasopalatine duct cyst arieses from...-epithelial rests of degenerated nasopalatine duct
- 11Nasaopalatine duct cyst differential diagnosis-radicular cyst/granuloma
-keratocystic odontogenic tumor
-large incisive foramen - 12Nasopalatine duct cyst management-conservative surgical removal
-recurrence rare - 13Cyst of the incisive papilla-soft tissue counterpart of nasopalatine duct cyst (very rare, no radiograph abnormalities)
-Arises from remnants of nasopalatine duct located within the incisive papilla
-conservative removal, recurrence rare - 14Surgical ciliated cyst-uncommon consequence of surgical entry into maxillary sinus
-sinus epithelium iatrogenically implanted in bone by surgeon (pseudostratified ciliated respiratory epithelium)
-posterior maxilla most common site
-conservative removal (recurrence rare) - 15Simple bone cyst (traumatic bone cyst, idiopathic bone cavity)-Hollow cavity within bone
-Etiology unknown
-Treated by vigorous curettage of cavity walls (induces bleeding, wound healing)
-20% recurrence rate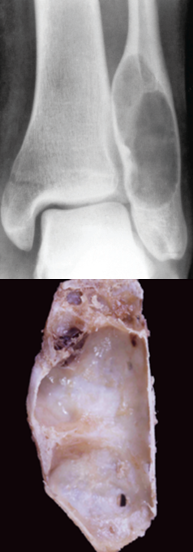
- 16Epidemiology of Simple bone cysts-Metaphysis of humerus or femur most common location
-2:1 male predilection
-Most common in 1st-2nd decade - 17Gnathic Simple Bone Cyst-75% occur in posterior mandible, typically unilocular
-asymptomatic, associated teeth are vital
-Scalloping between roots characteristic but not universal
-Rarely bilateral - 18Differential diagnosis of Gnathic simple bone cyst-Keratocystic odontogenic tumor (both have tendency to scallop around roots of teeth)
- 19Central Giant Cell Granuloma (CGCG)-Likely neoplastic lesion exclusive to gnathic bones
-associated w/ PDL of teeth
-75% of cases are unilocular/multilocular radiolucency of the mandible (anterior or body most common)
-Most common in 1st-3rd decades
-Female predilection - 20Aggressive CGCGs characterized by...-pain
-paresthesia
-size >5cm
-root resorption
-rapid growth
-cortical perforation
-recurrence - 21Management & Prognosis of CGCG-surgical excision w/ vigorous curettage
-variable recurrence rate (depending on biologic potential of lesion) - 22Recurrent CGCG lesions-En bloc resection
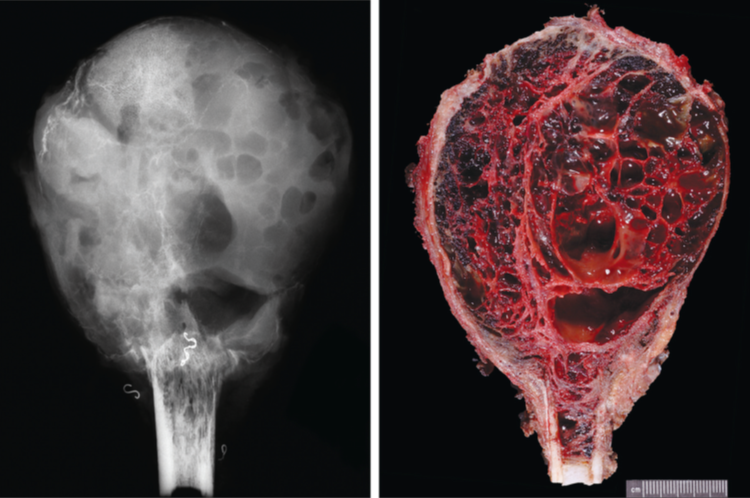
-intralesional injection (steroid, denosumab, IFN-alpha) - 23Aneurysmal bone cyst-benign neoplasm characterized by recurrent USP6 abnormalities
-Aneurysmal= referring to blowout distension of contour of affected bone
-Cyst= consists primarily of blood-filled (cyst-like) cavities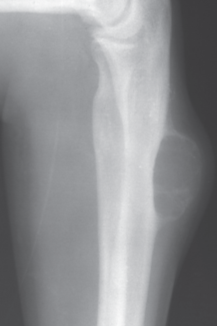
- 24Epidemiology of Aneurysmal Bone Cyst (ABC)-80% occur in 1st-2nd decade
-20% occur in craniofacial bones
-Approx. 50% of ABCs occur secondary to a pre-existing lesion (osteoblatoma, CGCGs, fibrous dysplasia, osteosarcoma in craniofacial bones) - 25Gnathic ABC-most commonly occur in posterior mandible
-multilocular, eccentric radiolucency with paper-thin shell of subperiostea bone
-rapid growth, tooth displacement, root resorption common
-patient may complain of pain, tenderness
-finger in balloon sign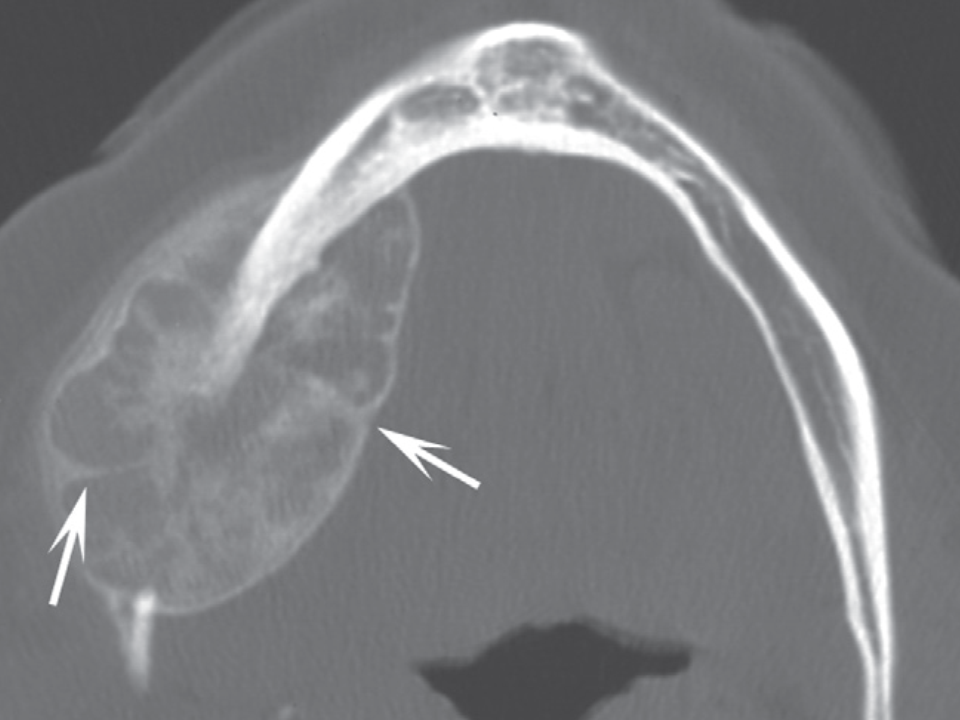
- 26ABC clinical differential diagnosis Management & Prognosis-CGCG
-Aggressive curettage w/ bone grafting (high recurrence rate (20-70%))
-En bloc resection (most effective treatment; may require significant reconstruction) - 27Hematopoietic bone marrow defect-focus of hyperplastic hematopoietic marrow
-considered a variation of normal
-no reported cases outside of gnathic bones
-no treatment required
-biopsy usually necessary for diagnosis
-Post. mandible most common site
-well-demarcated or diffuse radiolucency
-may or may not be corticated
-asymptomatic - 28Myospherulosis-increasingly uncommon iatrogenically caused condition
-gauze impregnated w/ petrolatum/antibiotics placed following:
>>dental extractions
>>surgical procedures involving paranasal sinuses
>>subcutaneous intramuscular injections - 29Cause of Myospherulosis Presentation Treatment-lipids in petrolatum or linolatum based antibiotic ointments undergo non-degradable emulsification w/ RBCs
-Non-descript radiolucency; usually in the area of a previously extracted tooth
-Curettage curative - 30Osteonecrosis (avascular necrosis)-infarction of bone & marrow
-associated w/ a variety of conditions:
>>fracture
>>corticosteroid administration (femoral head common site)
>>antiresorptive therapy (bisphosphonates, denosumab; jawbones common site)
>>infection, radiation
>>sickle cell crisis - 31Medication related osteonecrosis of teh jaws (MRONJ)-uncommon but serious side effect of certain medications
>>bisphosphonates (majority of cases)
>>denosumab
>>antiangiogenic cancer therapies (rarely)
-rarely extragnathic bones involved
-mechanism of action incompletely understood - 32What are bisphosphonates?Inhibitors of osteoclastic bone resorption
-attach to hydroxyapatite crystals in bone
-ingested by osteoclasts during bone resorption
-osteoclasts rendered non-functional
-half-life in bone ~10yr - 33When are bisphosphonates administered?-Cancer therapy (multiple myeloma, metastatic cancer to bone [breast, prostate, lung]; inc. quality of life by decreasing skeletal events)
-Osteoporosis/osteopenia (reduced risk of osteoporotic bone fracture)
-Any condition w/ excessive bone resorption (osteogenesis imperfecta, Paget disease) - 34IV bisphosphonates every 3-4 weeks for bone metastases (zoledronate/zometa; pamidronate/aredia)0.5-1% develop osteonecrosis
- 35IV bisphosphonates once yearly for osteoporosis (zoledronate/reclast)0.02-0.04% develop osteonecrosis
- 36Oral bisphosphonates taken daily/weekly/monthly for osteoporosis (alendronate/fosamax; risedronate/actonel; ibandronate/bonvia)0.1-0.2% develop osteonecrosis
- 37What is denosumab?inhibitor of osteoclastic bone resorption
-binds RANK ligand so it cannot bind RANK (binding is necessary to continue maturation)
-osteoclasts cannot develop from precursor cells
-does not bind bone
-half-life ~6months - 38When is denosumab administered?-Osteoporosis/osteopenia (reduce risk of osteoporotic bone fracture)
-Cancer therapy (metastatic cancer to bone; increase quality of life by decreasing skeletal-related events) - 39Subcutaneous administration of denosumab every 6months for osteoporosis (Prolia)0.5-1% develop osteonecrosis
- 40Subcutaneous administration of denosumab every 4 weeks for bone metastases (Xgeva)0.02-0.04% develop osteonecrosis
- 41MRONJ Risk Factors: site73% Mandible
22.5% Maxilla
4.5% Both jaws - 42MRONJ Risk Factors: Duration of dose-IV= 9-30 months median onset
-PO= 4yr median onset - 43MRONJ Risk Factors: Age-no children have developed ONJ
- 44MRONJ: Other risk factors-Dentoalveolar surgery?
-Pre-existing inflammatory dental disease? - 45Diagnosis of MRONJ3 diagnostic criteria must be met:
1) Current or previous treatment with anti-resorptive/anti-angiogenic agents
2) Exposed bone or bone that can be probed (intraorally or extraorally) through a fistula
(Present for at least 8 weeks)
3No history of radiation therapy to jaws or metastatic disease to jaws - 46Stage 0 MRONJNo clinical evidence of necrotic bone
Non-specific clinical/radiographic symptoms:
-Dull/aching bone or sinus pain
-Odontalgia, loosening of teeth
-Alveolar bone loss, changes in trabecular pattern of bone
-Intraoral fistula (does not probe to bone) - 47S-Exposed necrotic bone or fistula that probes to bone
-No evidence of infection
-Asymptomatic - 48Stage 2 MRONJ-Exposed necrotic bone or fistula that probes to bone
-Evidence of infection (swelling, erythema)
-Typically symptomatic - 49Stage 3 MRONJ-Exposed necrotic bone or fistula that probes to bone
-Evidence of infection (swelling, erythema)
-One of the following:
>>Extensive exposed bone
>>Pathologic fracture
>>Extra-oral fistula
>>Oro-antral/oro-nasal communication - 50Treatment of MRONJ-Conservative management of caries, periodontal disease
-Close monitoring for progression to higher stage
-Mobile bony sequestra should always be removed to facilitate soft tissue healing, when possible
-Chlorhexidine 0.12% (antimicrobial mouth rinse)
-Oral antibiotics (penicillin best) and/or pain control
-Surgical resection, debridement - 51MRONJ & dental considerationsPrior to beginning therapy with anti-resorptives
-Optimize dental health
If dental work needed during therapy
-Wait until 2 months after bisphosphonate administration (lowest levels in serum)
-Bisphosphonate ‘drug holiday’ suggested but efficacy unproven
If patient has exposed bone
-Instruct to gently brush area with toothbrush (so plaque doesn’t build up) - 52Osteoradionecrosis-Exposed, irradiated bone in the absence of residual or recurrent tumor
-Complication of radiotherapy= vascular obliteration leads to tissue hypoxia - 53Osteoradionecrosis of the jaws-Occurs in 5-7% of locally radiated patients
-Mandible involved in >90% of cases
(Exposed to high doses of radiation in majority of radiated patients (oropharyngeal cancer, oral cancer)
Maxillary osteoradionecrosis rare) - 54Majority of Osteoradionecrosis of the Jaws occur...-At radiation doses >60Gy
-Following dentoalveolar surgery
-4-36months after completion of radiation therapy - 55Management of Osteoradionecrosis of the jawsComplex
-Conservative debridement, antibiotics
-Resection
-Hyperbaric oxygen - 56Prevention represents best course of action (Osteoradionecrosis)-Extraction of unrestorable teeth
-Extraction of teeth w/ advanced periodontitis
-Elimination of oral foci of infection
-Excellent oral hygiene - 57Spontaneous sequestration (osteonecrosis)-Occurs nearly exclusively along the mylohyoid ridge (<1cm in diameter)
-Etiology unknown
-Patient management:
>>gently brush area (avoids plaque build-up)
>>once mobile, can be removed - 58Other causes of osteonecrosis-Mechanical trauma
-Chemical trauma
-Infection
-Secondary to disease states causing hypovascular bone - 59Fibrous dysplasia-anomaly of bone-forming mesenchymal tissue
-characterized by inability of bone-forming tissue to produce mature lamellar bone
>>Maturation arrested at level of woven bone
>>abnormal bone produced in increased amounts - 60Fibrous dysplasia manifestation-usually during 1st-3rd decades
-asymptomatic bony swelling or deformity
-mild/moderate pain occasionally
-growth typically arrests by early 20s (foci go away entirely on their own once growth is arrested due to normal remodeling) - 61Fibrous dysplasia variable phenotypic expressions Monostotic FD (85-90%)-one bone involved
-craniofacial bones, ribs, femur commonly involved - 62Fibrous dysplasia variable phenotypic expressions Polyostotic FD (10-15%)-Multiple bones affected
-craniofacial involvement in ~50% of cases
-Mazabraud syndrome: polyostotic FD w/ soft tissue myxomas - 63Fibrous dysplasia variable phenotypic expressions McCune-Albright Syndrome (<5%)-Polyostotic FD
-Irregular Cafe-au-lait skin pigmentation (coast of Maine borders)
-precocious puberty - 64Extent of disease (FD) correlates wonset of disease-causing GNAS mutation
-always post-zygotic (never inherited)
-Earlier occuring mutations in osteoblast precursors during embryologic development results in greater proportion of functional osteoblasts w/ GNAS mutation (greater amounts of abnormal bone production) - 65Radiographic appearance of FD-normal bone trabeculation characteristically replaced by 'ground glass' appearing bone
-borders often poorly discernable and blend into normal bone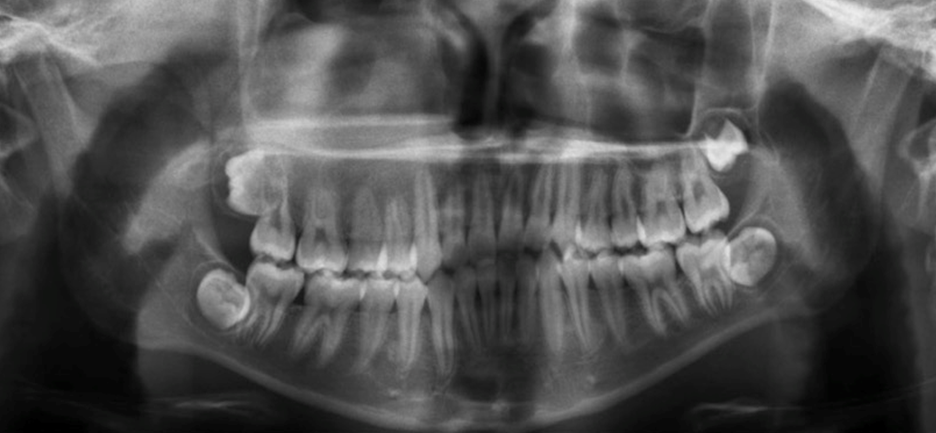
- 66Craniofacial fibrous dysplasiarefers to a solitary lesion affecting multiple contiguous craniofacial bones
- 67Fibrous dysplasia Diagnosis & Management-Diagnosed based on clinico-radiologic features (biopsy usually unnecessary)
-Management depends on the presence of symptoms:
>>Asymptomatic= observation w/ periodic radiographs
>>Symptomatic= surgical recontouring (high rate of recurrence until natural cessation of growth of lesion) - 68Cemento-ossifying fibroma-benign odontogenic neoplasm exclusive to tooth-bearing regions of gnathic bones
-most common in 3rd-4th decades
-60-70% occur in body of mandible
-Typically treated by conservative removal
-Rare patients may have hyperparathyroidism-jaw tumor syndrome - 69Cemento-ossifying fibroma Radiographic appearance-well-demarcated radiolucency w/ variable radiopacitites
-expansion, root resorption occasionally noted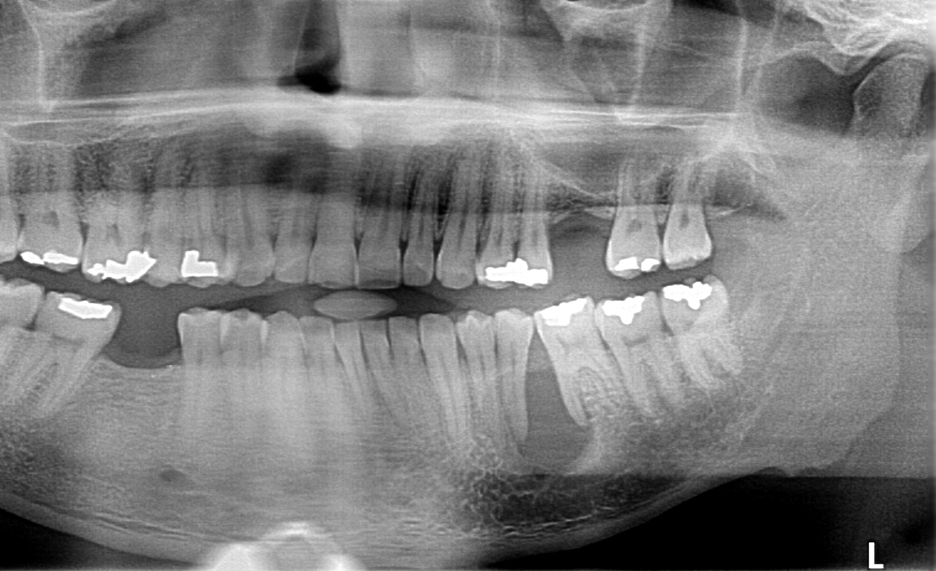
- 70Aggressive (juvenile) ossifying fibromas -Trabecular ossifying fibroma-mean age range 8.5-12yr
-Maxilla/mandible most common sites of occurence (rarely extragnathic craniofacial sites)
-Progressive/rapid expansion of affected area - 71Aggressive (juvenile) ossifying fibromas -Psammomatoid ossifying fibroma-Most common in 2nd-3rd decades
-Extragnathic craniofacial sites most commonly involved (rarely gnathic bones)
-Progressive/rapid expansion of affected area - 72Gigantiform cementoma-very rare
-multifocal development of ossifying fibroma-like lesions
-arises in childhood & progressively expand to cause facial deformity
-familial inheritance in some cases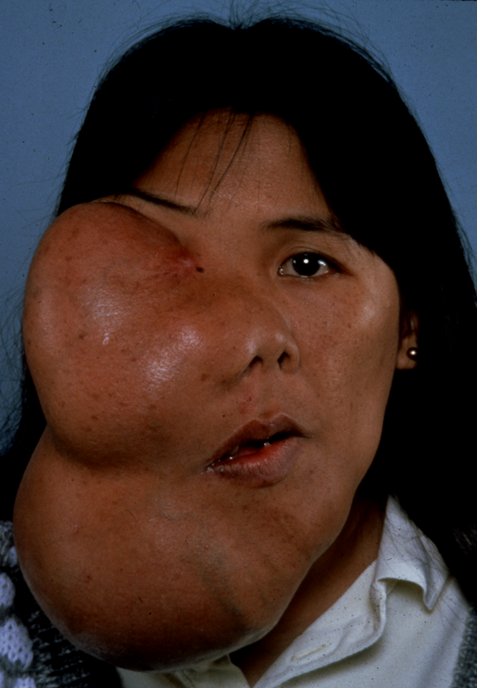
- 73Cemento-osseous dysplasia-idiopathic bone condition in which bone is replaced by varying amounts of fibrous tissue and cemento-osseous tissue
-unique to tooth-bearing regions of gnathic bones
-Most common fibro-osseous lesion encountered
-May persist following or develop in response to dental extraction - 74Cemento-osseous dysplasia Takes months/years to develop & radiographic appearance depends on maturity of lesion-Early= radiolucent (fibrous tissue)
-Intermediate= mixed radiolucent/radiopaque
-Late= radiopaque (cemnto-osseous tissue)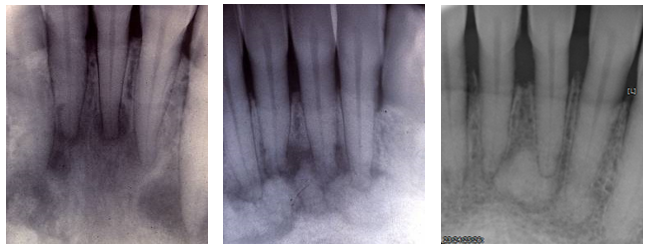
- 75Cemento-osseous dysplasia most frequently occurs in...African American females in 4th-5th decades
-asymptomatic & discovered on routine radiographs
-no bony expansion
-associated dentition vital - 76Periapical COD-(most?) common presentation of COD
-affects apices of one or more vital mandibular anterior teeth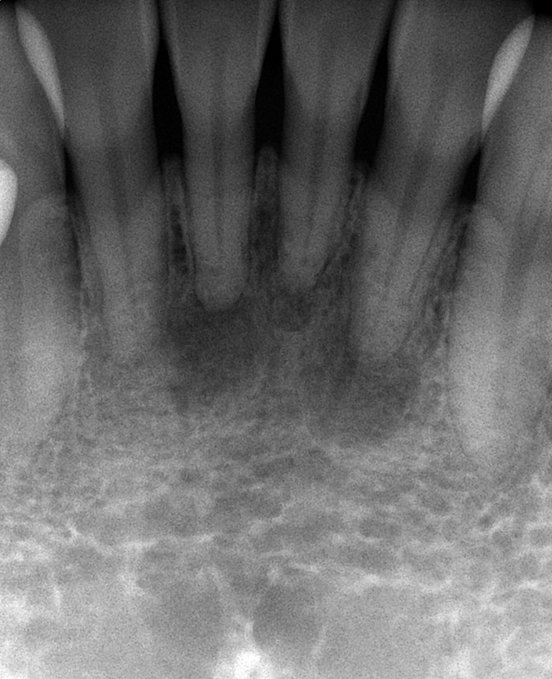
- 77Focal CODCOD also known to present unifocally in posterior jaws
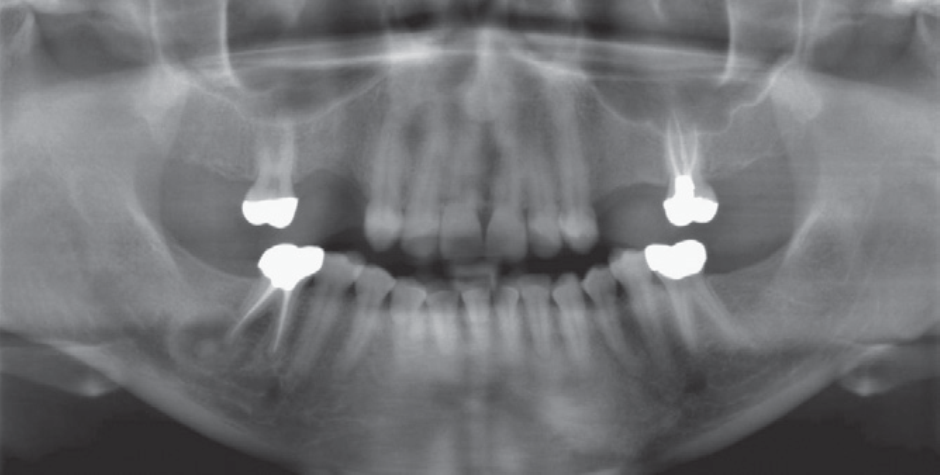
- 78Multifocal CODinvolving more than one site
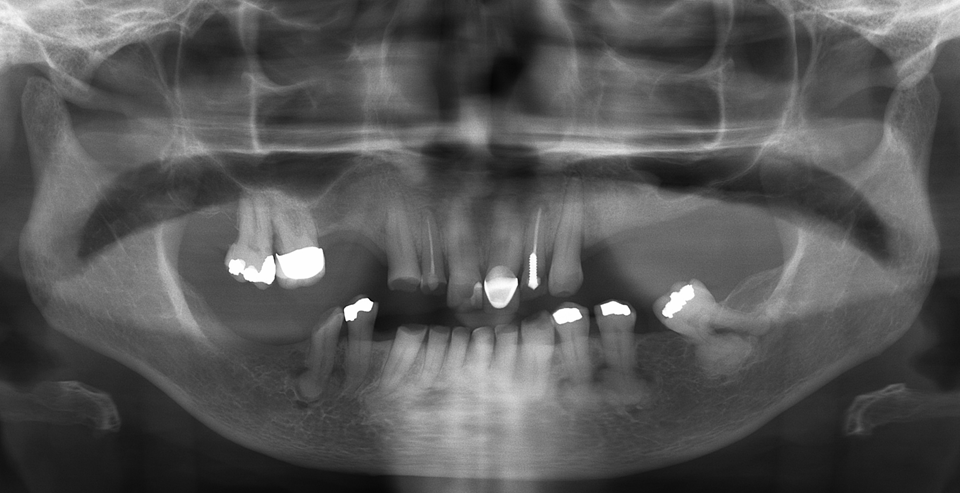
- 79Florid COD
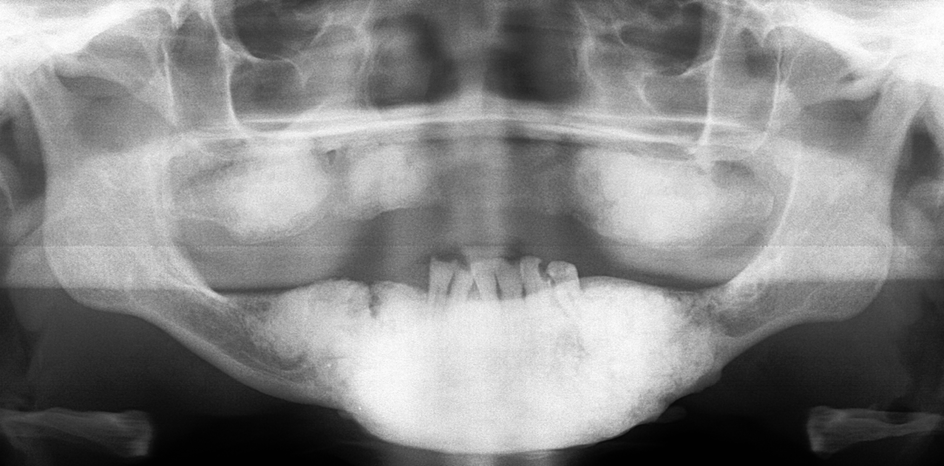
- 80Management of COD-Can be diagnosed confidently on panoramic or periapical films
(Biopsy not needed; Should be avoided because hypovascular bone prone to infection (osteomyetlitis))
-Do not do a root canal if the teeth are vital!!
-Patient can be followed with serial imaging
-Osteomyelitis may rarely develop - 81Osteoma-benign, slow-growing, bone-forming tumor
-Limited almost exclusively to craniofacial bones (gnathic bones less commonly)
-Most commonly diagnosed in 4th-5th decades
-Asymptomatic
-Firm, painless expansion - 82Osteoma Diagnosis-radiographic imaging or biopsy
-radiographic appearance of gnathic osteomas resembles that of parosteal osteosarcoma and typically requires biopsy - 83Bones/areas affected by Osteoma-Paranasal sinuses, cranial vault, nasal cavity, orbit
-Inferior or lingual border of mandible
-Condylar or coronoid regions - 84Osteoid osteoma & osteoblastoma-Microscopically identical neoplasms with predilection for 1st-3rd decades
-May appear radiolucent, radiopaque, or mixed depending on amount of osteoid is produced - 85Osteoid Osteoma-Less than 1.5-2 cm in diameter
-50% of cases involve femur or tibia
-Presents with tenderness, severe nocturnal pain relieved by aspirin
-10-12% of all bone tumors
(Uncommon in gnathic bones)
-Treated by surgical resection
-Recurrences uncommon - 86Osteoblastoma-Larger than 1.5-2 cm in diameter
-Frequently involves vertebral column
-Pain not distinctly nocturnal and unresponsive to aspirin
-Less than 1% of bone tumors
-Common in craniofacial bones
-Treated by surgical resection
-25% recurrence rate - 87Osteosarcoma-malignant neoplasm of bone
-most common primary bone malignancy
-second most common malignancy to metastases
-75% occur in 1st-2nd decades of life
-Usually arises in long bones of extremities (50% in area of knee; 6-10% occur in craniofacial bones)
-Typically presents as painful, progressively enlarging masses; pathologic fracture may be first symptom - 88Osteosarcoma survival-Historically 85-90% of patients developed metastases and died of disease
-Most patients have subclinical metastatic disease at time of surgery
-Introduction of neoadjuvant chemotherapy has markedly improved & predicted survival
>>Responders (>90% tumor necrosis)= long-term survival in 90% of cases
>>Non-responders= 5yr survival rate of <15% - 89Osteosarcoma of Gnathic bones-tends to affect skeletally mature patients (3rd-5th decades most common)
-local pain/paresthesia & swelling most consistent complaints
-Local recurrence most important reason for therapeutic failure
-metastases occur in 30% of patients (average survival rate <1yr) - 90What percent of mandibular and maxillary osteosarcomas recur-50% of mandibular osteosarcomas
-80% of maxillary osteosarcomas - 91Radiographic appearance of Gnathic Osteosarcoma-radiolucent, radiopaque, or mixed depending on ratio of bone destruction/formation
-widening of PDL, loosening of teeth, and supracrestal bone formation may all be seen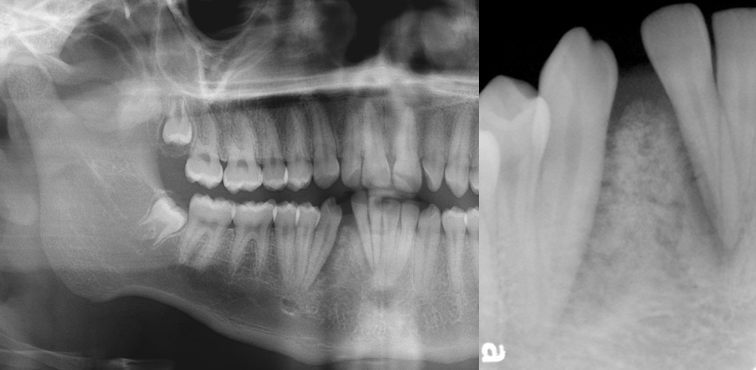
- 92Osteosarcoma, Codman triangle, & 'sunburst' appearance-when breaking through the cortex, lifts off normal periosteum, inducing reactive bone formation
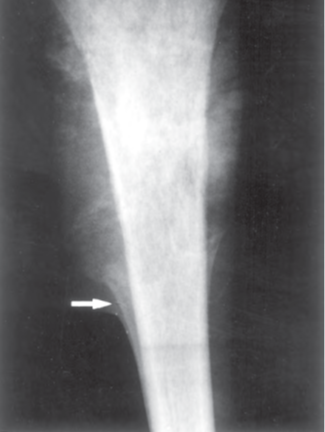
- 93Surface osteosarcomas-most osteosarcomas arise within medullary cavity of bone; some originate in periosteal or cortical region w/ little to no medullary involvement
- 94Periosteal osteosarcoma-better prognosis than conventional osteosarcoma
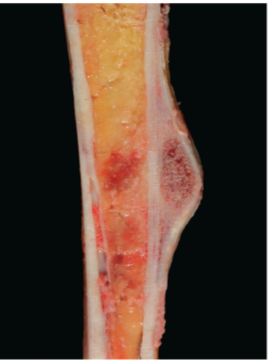
- 95Parosteal osteosarcoma-excellent prognosis
- 96Chondrosarcoma-Malignant neoplasm of cartilage
-Peak incidence after 5th decade of life
-<10% occur in craniofacial bones
-local pain/paresthesia & swelling most consistent complaints - 97Chondrosarcoma statistics-3rd most common primary bone malignancy following osteosarcoma & multiple myeloma
-Approx. 1/2 as common as osteosarcoma
-90% are low/intermediate grade tumors (grade I & II)
-10% are high-grade (grade III, other rare variants) - 98Chondrosarcoma Precursor lesions-Osteochondroma, enchondroma (<1%)
-Ollier disease, Mafucci syndrome - 99Low/intermediate grade Chondrosarcoma-Slow growing w/ low metastatic potential
-Relatively refractory to chemotherapy, radiation
-Treated by surgical resection - 100High-grade chondrosarcoma-high metastatic potential
-surgical resection remains best chance for cure but some indications for chemotherapy, radiation - 101Mesenchymal chondrosarcoma-<5% of all chondrosarcomas
-gnathic bones most common site of involvement
-significant minority occur extraskeletally
-Most common in 2nd-3rd decades
-Aggressive= 10yr overall survival ranges from 10-54% - 102Metastases to gnathic bones-comprise 1% of all oral/maxillofacial malignancies
-gnathic bones & mouth uncommon sites
-Gnathic bones 2x as commonly involved as oral soft tissues
-Typically evidence of widespread disease
-Average survival rate 7months
-First evidence of disease in up to 25% of patients
-Local pain/paresthesia & swelling most consistent complaints
-Bon preferred site of metastasis of several neoplasms (breast, prostate, thyroid, kidney, lungs) - 103Radiographic appearance of metastatic disease-poorly circumscribed radiolucency most common appearance
-breast and prostate cancer may appear radiopaque - 104Synovial Chondromatosis-benign disorder (likely neoplastic) or synovium
-Nodules of cartilage produced from synovial membrane
>>become detached from synovial membrane, float in the joint; may ossify
-Self-limiting or indolent course
-Rarely may transform to synovial chondrosarcoma - 105Synoviuimspecialized connective tissue which maintains synovial fluid within synovial cavity of synovial joints
- 106Treatment of Synovial chondromatosis-surgical removal of loose bodies & synovial membrane as needed
- 107Synovial Chondromatosis characteristics-typically monoarticular
-affects majority weight-bearing joints
-TMJ uncommonly affected
-Pain, swelling, or limitation of function
-Male predilection
-TMJ involvement present with non-specific signs and symptoms (pain, swelling, restricted movement, clicking/popping, crepitus, malocclusion)
Informationen
- Beschreibung
- NDBE Oral Path Karteikarten am Diseases of Gnathic bones and TMJ, erstellt von Laura Gennaro am 21/01/2018.
- Erstellt von
- Laura Gennaro
- Aufrufe
- 49
- Tags
- Bewertung