
Karteikarten
Alimentary System: Acute and Chronic Pancreatitis (see note Anatomy of the Pancreas)
Karten in diesem Stapel (14)
- 1Inflammatory process with cascade of release of inflammatory cytokines (TNFA, IL2, IL6, platelet-activating factor (PAF)) & pancreatic enzymes (trypsin, lipases, co-lipases) initiated by pancreatic injury, but which may develop into full blown MODS or SIRS. OHOCSInflammatory process with cascade of release of inflammatory cytokines (TNFA, IL2, IL6, platelet-activating factor (PAF)) and pancreatic enzymes (trypsin, lipases, co-lipases) initiated by pancreatic injury, but which may develop into full blown MODS or SIRS
OHOCS - 2Causes of acute pancreatitis.* Gallstones (60%)
* Alcohol (30%)
* Hyperlipidaemia
* Hypercalcaemia (hyperparathyroidism, multiple myeloma)
* Direct damage (trauma, ERCP, post-SX, cardiopulmonary bypass)
* Toxins:
> Drugs eg azathioprine, oestrogens, thiazides, isoniazid, steroids, NSAID's
* Infxn eg viral (mumps, CMV, HBV), mycoplasma
* Venom (scorpion, snake bites)
* Idiopathic - 3Clinical features of acute pancreatitis.* Severe epigastric P radiating to the back
* Severe N & V
* Fever, dehydration, hypotension, tachycardia (may be frankly shocked)
* Epigastric tenderness associated with guarding & in severe cases, rigidity which may be generalized
* L flank ecchymosis (Grey–Turner's sign) & periumbilical ecchymosis (Cullen's sign), 1–3% of cases haemorrhagic pancreatitis
OHOCS - 4Classification/complications of acute pancreatitis.* Oedematous (70%). May be simple or associated with phlegmon ('noninfected solid mass of inflamed pancreatic & retroperitoneal tissues') formation; transient fluid collections common.
* Severe/necrotizing (25%). Necrosis may be sterile or infected. Persistent large peripancreatic fluid collections may form (‘pseudocyst’), which may become infected.
* Haemorrhagic (5%)
OHOCS - 5Emergency Mx/resuscitation of suspected acute pancreatitis.* Large calibre IV access. Give crystalloid fluid up to 1000mL if tachycardic or hypotensive; may require ongoing fluids IV.
* Catheterize & place on a fluid balance chart
* BD's - FBC (Hb, WCC), U&E (Na, K), LFT's (bilirubin, albumin), amylase, group & save, clotting
* Monitor HR, BP, & urine output (urinary catheter)
• Consider central line & Mx pt in HDU if haemodynamically unstable or fails to respond to early resuscitation
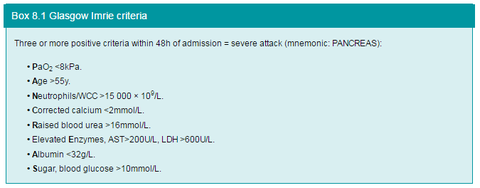
* Assess the severity of the attack by Glasgow Imrie criteria
Box 8.1 Glasgow Imrie criteria - 6Glasgow Imrie criteria. Box from OHOCS.
- 7Ix/Dx of acute pancreatitis.* Serum amylase >1000U. Diagnostic, but may be normal even in severe cases; ^amylase may occur in a wide range of other acute abdo events (intestinal ischaemia, leaking aneurysm, perforated ulcer, cholecystitis).
* Serum lipase. Remains ^longer than serum amylase; more specific, but less sensitive.
* AXR (non-specific findings). Absent psoas shadows, ‘sentinel loop sign’ (dilated proximal jejunal loop adjacent to pancreas because of local ileus’), ‘colon cut-off sign’ (distended colon to mid-transverse colon with no air distally); may show gallstone, pancreatic calcification.
* CT may be required. Shows pancreatic oedema, swelling, loss of fat planes; may show haemorrhagic or necrotic complications.
* US scan. Must be done within 48h of ADx to identify gallstones in bile duct.
OHOCS - 8Rx of acute pancreatitis.* Urgent ERCP & stone extraction for bile duct stones causing obstruction pancreatitis
Identify/prevent complications:
* IV ABx (eg IV imipenem TDS), sometimes started in moderate-severe cases without evidence of infected necrosis
* CT scan identifies development of pancreatic phlegmon, early fluid collections, necrosis, or haemorrhage
* CT-guided pancreatic aspiration to identify infected necrosis
* Early low volume enteral feeding increasingly used to reduce risk of stress ulceration & bacterial translocation causing sepsis
Rx of early complications:
* Consider Rx'ing severe cases on HDU/ITU for optimized fluid balance, respiratory, cardiovascular, & renal support
* Proven infected necrosis. SX debridement may be required, but is associated with a poor prognosis.
* Acute pseudocysts rarely need drainage unless very large
OHOCS - 9Chronic pancreatitis - key facts: * Characterized by recurrent or persistent abdo P arising from the pancreas * Often associated with exocrine or endocrine pancreatic insufficiency * Characterized by irreversible destruction & fibrosis of pancreatic parenchyma * May arise following one or more episodes of acute pancreatitis or may be a chronic progressive process de novo OHOCSChronic pancreatitis - key facts:
* Characterized by recurrent or persistent abdo P arising from the pancreas.
* Often associated with exocrine or endocrine pancreatic insufficiency
* Characterized by irreversible destruction & fibrosis of pancreatic parenchyma
* May arise following one or more episodes of acute pancreatitis or may be a chronic progressive process de novo
OHOCS - 10Pathological features of chronic pancreatitis: * May affect all or part of gland (focal) * Head tends to most severely involved part in chronic alcohol DS * Features of acute pancreatitis may occur—oedema, acute inflammatory infiltrate, focal necrosis, intraparenchymal haemorrhage * Chronic inflammatory changes cause progressive disorganization of the pancreas: > Glandular atrophy & duct ectasia > Microcalcification & intraductal stone formation with cystic changes secondary to duct occlusion OHOCSPathological features of chronic pancreatitis:
* May affect all or part of gland (focal)
* Head tends to most severely involved part in chronic alcohol DS
* Features of acute pancreatitis may occur—oedema, acute inflammatory infiltrate, focal necrosis, intraparenchymal haemorrhage
* Chronic inflammatory changes cause progressive disorganization of the pancreas:
> Glandular atrophy & duct ectasia
> Microcalcification & intraductal stone formation with cystic changes secondary to duct occlusion
OHOCS - 11Causes of chronic pancreatitis.* Recurrent acute pancreatitis of any cause, especially alcohol
* Secondary to pancreatic ductal obstruction:
> Pancreatic head cysts, tumours
> Pancreatic duct strictures—post-SX, ERCP, parasitic infestation
> Congenital pancreatic abnormalities (pancreas divisum, annular pancreas)
> Cystic fibrosis
* Associated with AI DS's (primary biliary cirrhosis, primary sclerosing cholangitis)
* Congenital idiopathic chronic pancreatitis
OHOCS - 12Features of chronic inflammation, exocrine, & endocrine failure in chronic pancreatitis.Chronic inflammation:
* Recurrent or chronic abdo P:
> Typically epigastric, radiating to back & requiring opiates
> ^With food, alcohol
Features of exocrine failure:
* Anorexia & weight loss (due to protein malabsorption)
* Steatorrhoea (due to fat malabsorption)
Features of endocrine failure:
* Insulin-dependent DM (due to loss of beta islet cells)
OHOCS - 13Rx of chronic pancreatitis.* Prevention of cause/progressive damage:
> Stop alcohol, deal with gallstones, Rx AI DS
> Encourage a diet rich in antioxidants (vitamins A, C, E, selenium)
* Control Sx/complications:
> Dietary modifications. Adequate carbohydrates & protein, reduced fat.
> Pancreatic exocrine enzyme supplements (e.g. Creon®)
> Analgesia
> Control of DM often requires insulin
Indications for SX Rx:
* Rx of reversible cause (anatomical abnormalities, tumours, cysts, ductal strictures & stones). Ops used include those to remove causes & those to drain obstructed duct:
> Pancreaticoduodenectomy (Whipple procedure)
> Partial pancreatectomy of the head (Frey procedure) or tail (distal pancreatectomy)
> Pancreaticojejunostomy (Peustow or Duval procedure)
* Rx of severe intractable P or multiple relapses. Ops are usually to resect affected portion:
> Partial pancreatectomy of head (Frey procedure) or tail (distal pancreatectomy)
> Total pancreatectomy
* Complications (pseudocyst, obstruction, fistula, infxn, portal hypertension)
OHOCS - 14What risks are associated with resectional SX?* ^Risk of exocrine & endocrine pancreatic failure
* All surgery is associated with a risk of symptom recurrence due to recurrent or progressive DS
OHOCS
Informationen
- Beschreibung
- SGUL LOB's for Alimentary System: Acute and Chronic Pancreatitis.
- Erstellt von
- Andrew Street
- Aufrufe
- 70
- Bewertung