
Fichas
Unit 3 Week 6 & 7
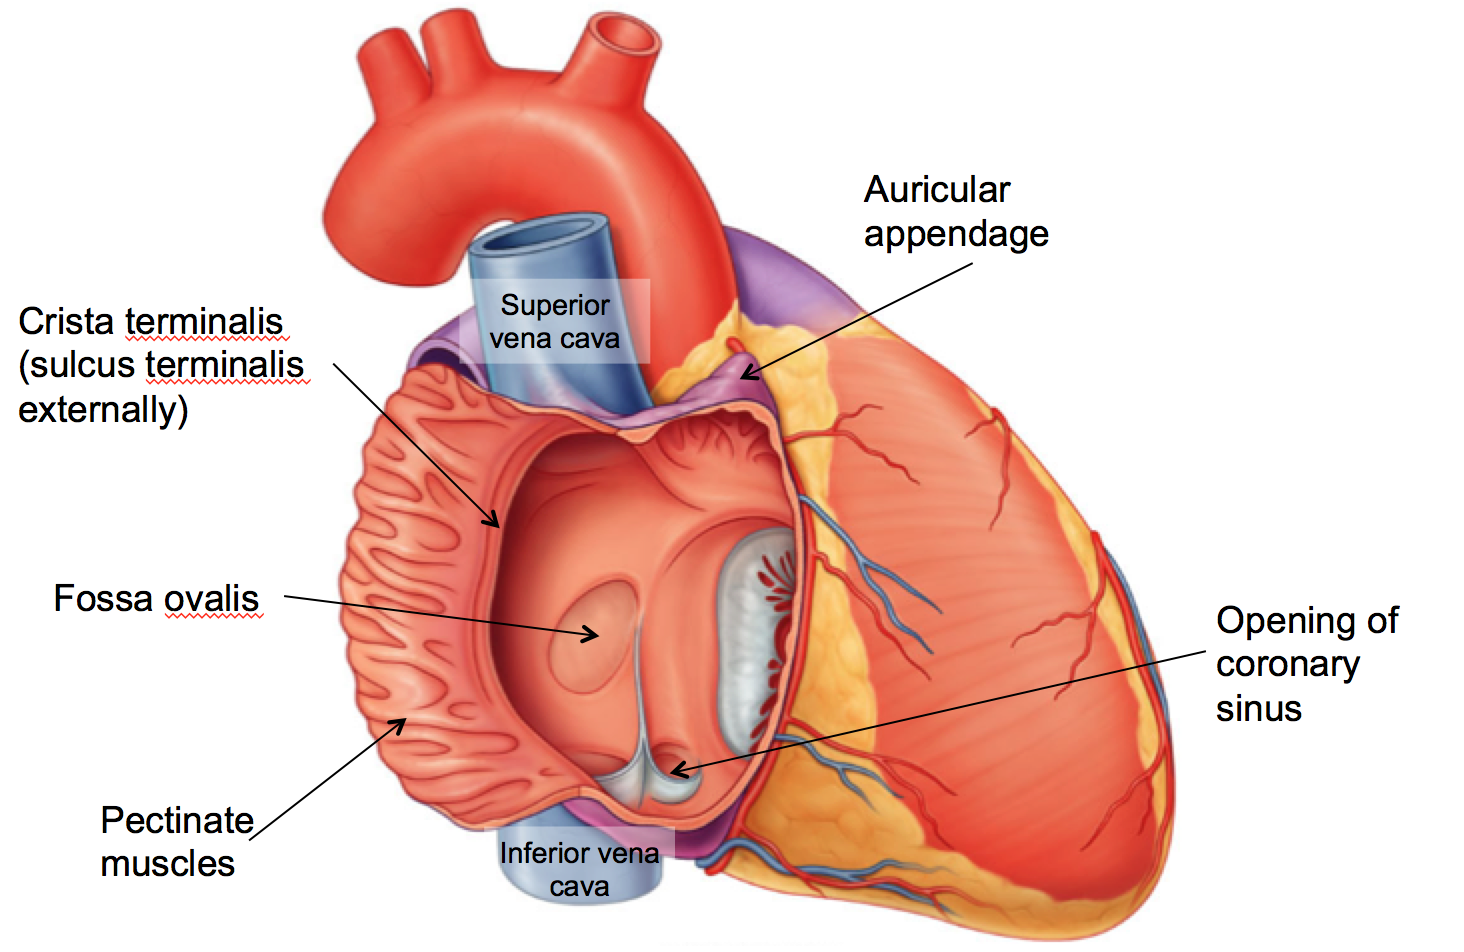
Fichas del conjunto (56)
- 1Name 4 Risk factors of CVD (2 Constitutional & 2 non-constitutional)Constitutional
Genetics
FH
Age
Non-constitutional
Smoking
Obesity
Hypercholesterolaemia
Hypertension - 2Outline the formation of a Transitional atheromatous plaque1. Endothelial injury
2. Increased vascular permeability
3. LDL Accumulation & oxidation
4. Lipid-laiden foam cells
5. Platelet adhesion & PDGF
6. SM proliferation
7. ECM deposition
8. Further LDL deposition - 3Describe what causes TIAMini-stroke
Microemboli i.e. cardiac thrombi or artheromatous plaque embolise into cerebral circulation - MCA
Cerebral hypoxia - no infarction - 4Compare a fatty streak to an advanced plaqueFatty streak: Lipid laiden foam cells (Oxidised LDL
Flat yellow dots & lines
Mature plaque: Intimal thickening - SM proliferation & ECM deposition - 5Name & describe the 2 methods for formation of complicated plaque1. Denudation of endothelium - Exposure of subendothelial collagen
2. Endothelial fissuring - Fibrous cap tears off - blood enters - thrombus forms within plaque - 6Outline the difference between Stable & Unstable anginaStable: Only occurs on exertion (At rest blood supply meets demand - on exertion heart requires more oxygen and this demand is not met by partially occluded vessel
Unstable: Occurs even at rest - Usually due to disturbance of atheromatous plaque i.e. thrombosis, embolisation - 7Define and name 2 causes of Prinzmetal anginaAngina that occurs without provocation usually due to vasoconstrictors i.e. TxA2
- Smoking
- Cold air
- Cocaine - 8Outline the pathogenesis of MI1. Artheromatous plaque undergoes disruption
2. Thrombus formation causes complete occlusion of epicardial vessel
3. Cessation of aerobic respiration
4. Myocardial contractility reduced
5. Damage causes leakage i.e. troponin - 9What is an ST elevated MI?Transmural (Involving death of all layers of heart tissue)
- 10Which parts of the heart is supplied by Anterior interventricular artery Left Circumflex RCAAnterior interventricular artery - Anterior wall & septum
Left Circumflex - Lateral wall
RCA - Posterior wall & septum - 11Explain the following presentations in MI 1. Chest pain (Left) 2. Sweaty & Clammy 3. Shortness of breath1. Myocardial necrosis => Bradykinin & adenosine (Inflammation) stimulates sympathetic and vagal afferents (T1-T4)
2. Reduce CO & SV => Reflexive sympathetic drive => Diaphoresis & Peripheral vasoconstriction
3. Reduced EF => Reduced tissue perfusion => tissue hypoxia => Dyspnoea - 12Outline which investigations should be conducted following STEMI1. ECG
2. Trponin I & C
3. CK-MB - 13What is the most optimal management strategy for MIPrimary angioplasty (Reduced mortality, re-infarction & ischaemia)
- 14Why was atenolol prescribedTo reduce heart rate and force of contraction
- 15What is the mechanism of action of Simvastatin.HMG CoA reductase inhibitor
- Reduces liver LDL synthesis
- Increases liver LDL-R synthesis
- Increases LDL clearance from circulation - 16Mechanism of action of RamiprilACE inhibitor
Inhibits conversion of Ang I => Ang II
1. Reduced Ang II binding to AngII-R - GQ/11 - Vasodilation
2. Reduced altosterone induced Na+ retention
ANTI-HYPERTENSIVE - 172 Adverse effects of warfarin1. Haemorrhage
2. Teratogenic - 18Why is aspirin given to chew after MIAspirin is an anti-platelet drug by inhibiting the production of platelet activating TxA2
Prevents clotting of blood and thrombus formation - 19How does a AED work?- Electrodes send info to computer analysing whether the rhythm is shockable or not
- Electrical current is delivered and depolarises the myocardium allow natural pacemaker tissue to resume control - 20Give 2 examples of shockable rhythms1. Ventricular tachycardia: Re-entrant pathway looping in the ventricle
2. Ventricular fibrillation: Ventricular cells are excitable and depolarising randomly - 21What are the 4 primary criteria when analysing ECG- Rate
- Regularity
- PR interval
- QRS - 22What is the difference between systolic and diastolic HFSystolic: Inadequate myocardial contractility i.e. IHD, Hypertension
Diastolic: Inability of the myocardium to fully relax and fill i.e. Hypertrophy - 23Explain the pulmonary presentations of LHF- Blood is not effectively pumped out of left side of body thus there is a backlog through pulmonary veins into the lungs
- Pulmonary hypertension causes pulmonary oedema
- Dysponoea
- Cough Crackles & Rales - 24Outline how chronic lung disease leads to cor pulmonale (What are the clinical manifestations of this?)Chronic lung disease => hypoxaemia => Hypoxic vasoconstriction => PH => Right ventricle dilation & hypertrophy
Blood backs up into the body
- Hepatosplenomegaly
-Raised JVP
- Pitting oedema - 25Management of HF Basic management of HFAtenolol
Ramipril
Furosemide
Spironolactone - 26What is the role of a first responder?Community volunteer trained to attend emergency calls received by ambulance services. Carry AED.
- 27Outline the Self regulatory model of illness- Symptom perception
- Cognition => Coping with illness threat
- Emotion > Coping with emotion
- Appraisal - 28Describe the cognitive and emotional response of the self regulatory model of illnessCognitive: Symptom perception (Controllability, curability & consequences)
Emotional: Anxiety (Apprehension, worsened with tests
& investigations)
Depression - flattened response to all situation (Feeling low, loss of interest or pleasure) - 29Give 2 examples of positive consequences of MI- Greater appreciation of life
- Healthy lifestyle changes - 30What is the role of cardiac rehabilitationTo help recovery and reduce the risk of recurrence of cardiac illness.
Includes holistic approach: Physical fitness, education, Dietician, lifestyle advice, counselling (anxiety & depression) - 31Define global governanceActions and means adopted by society to organise itself in the promotion and protection of health
- 32Give 4 ways governance can achieve equity in health1. Redistribution of resources
2. Legislation & policy development
3. Public regulation
4. Creation of public services and organisations - 33Compare and contrast the Beveridge model of healthcare to the out of pocket model of healthcareBeveridge: Free at the point of access where its funded by the government through tax
Out of pocket: Individuals pay for their own healthcare unless they are covered by health insurance. - 34—
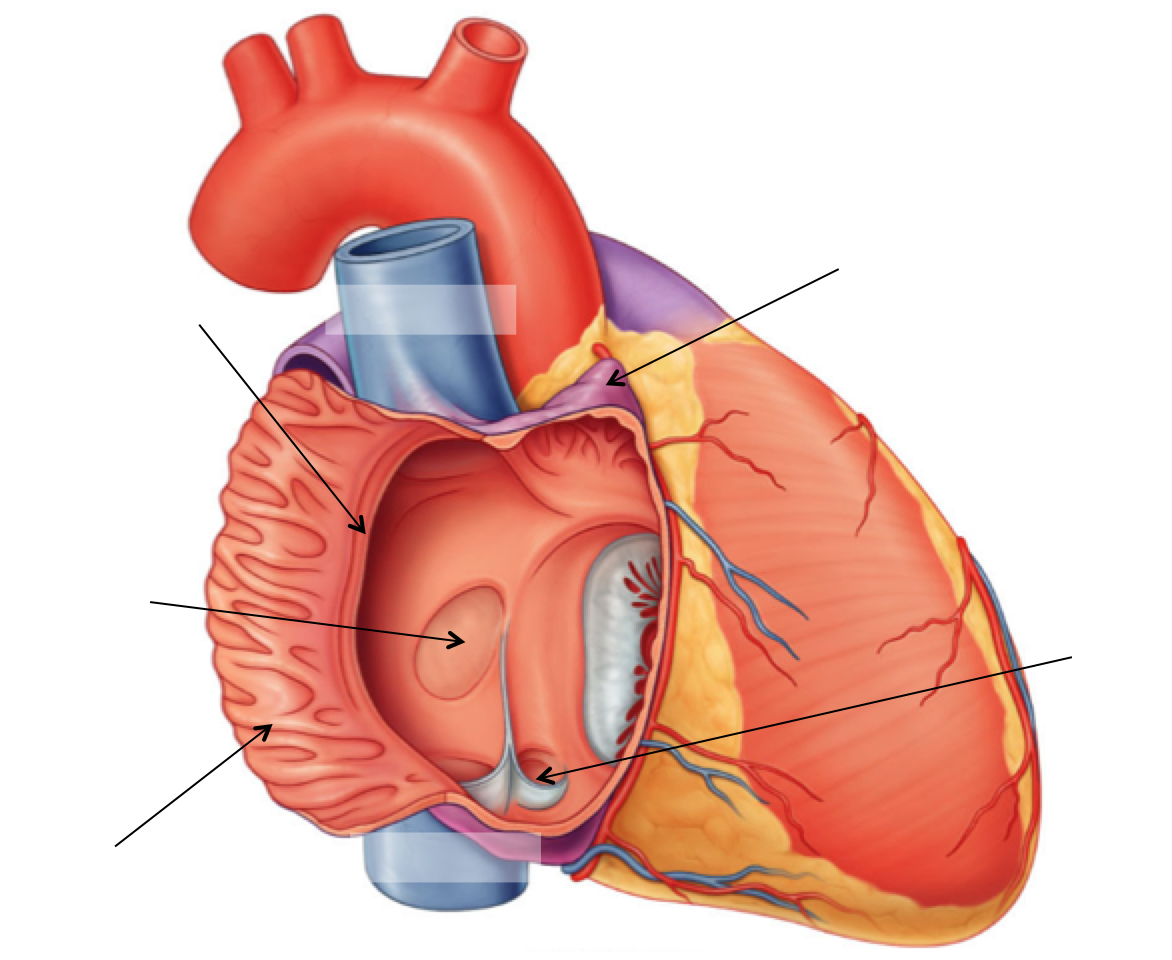
- 35—
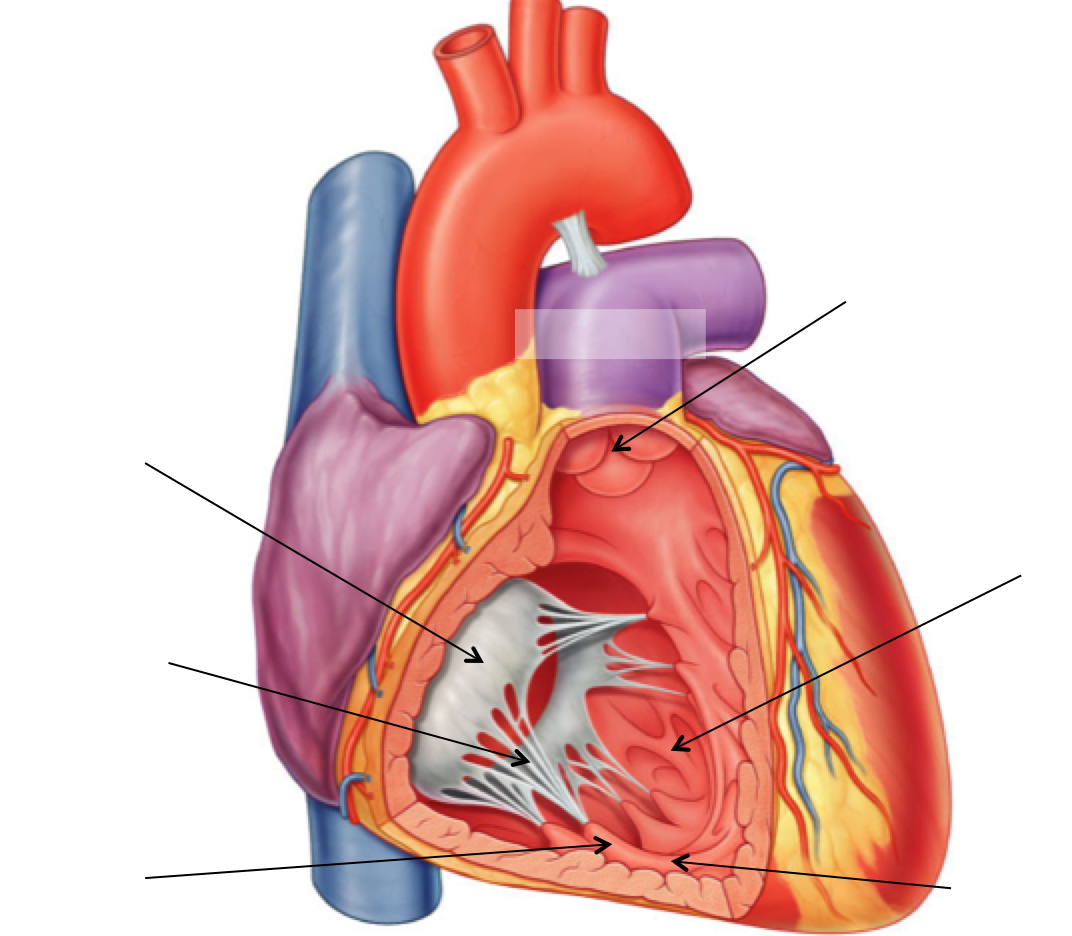
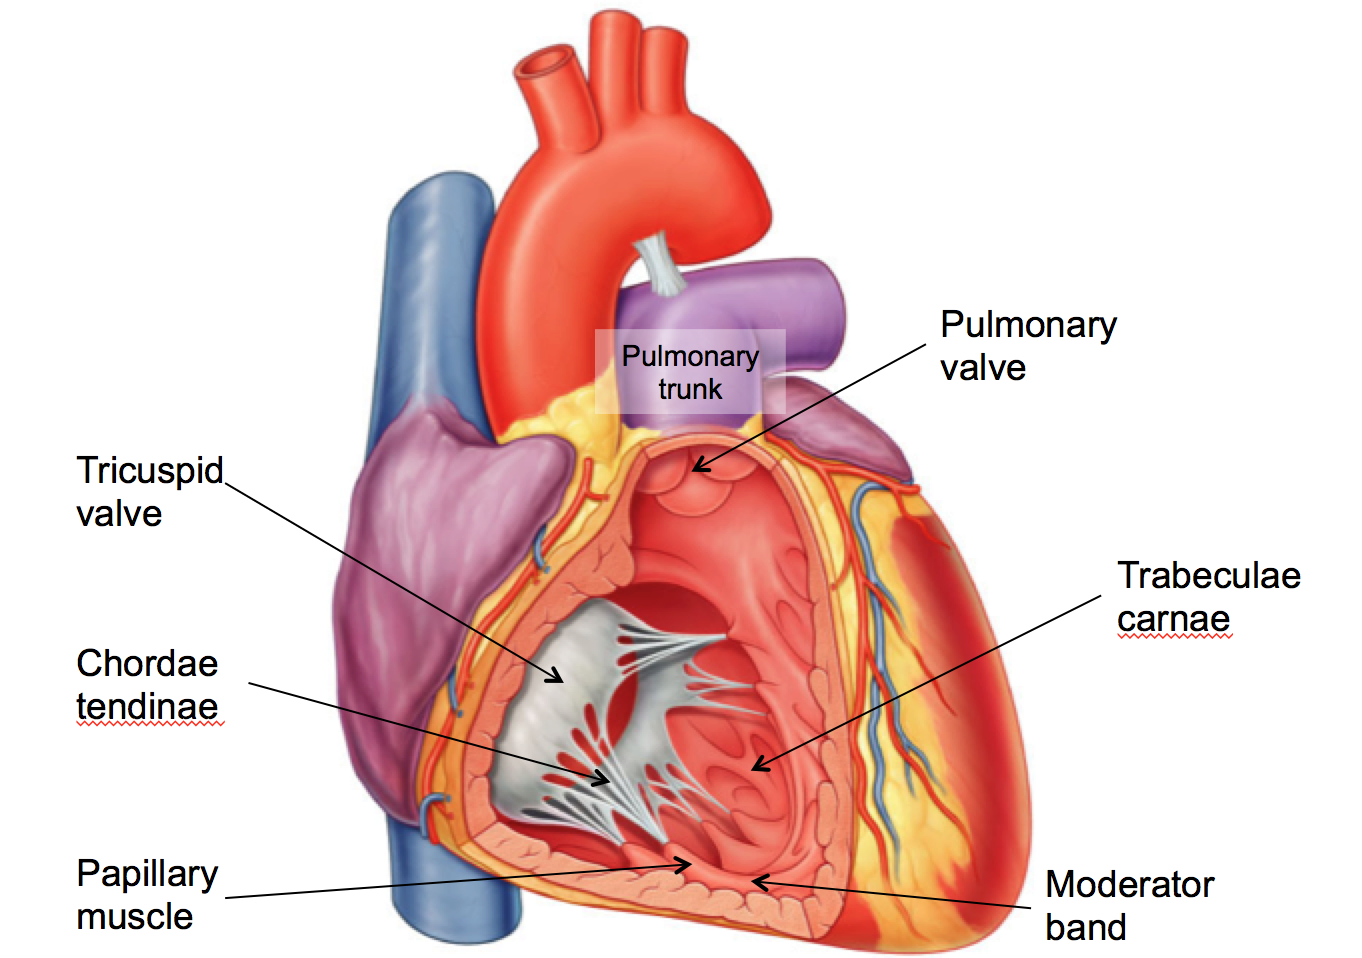
- 36—
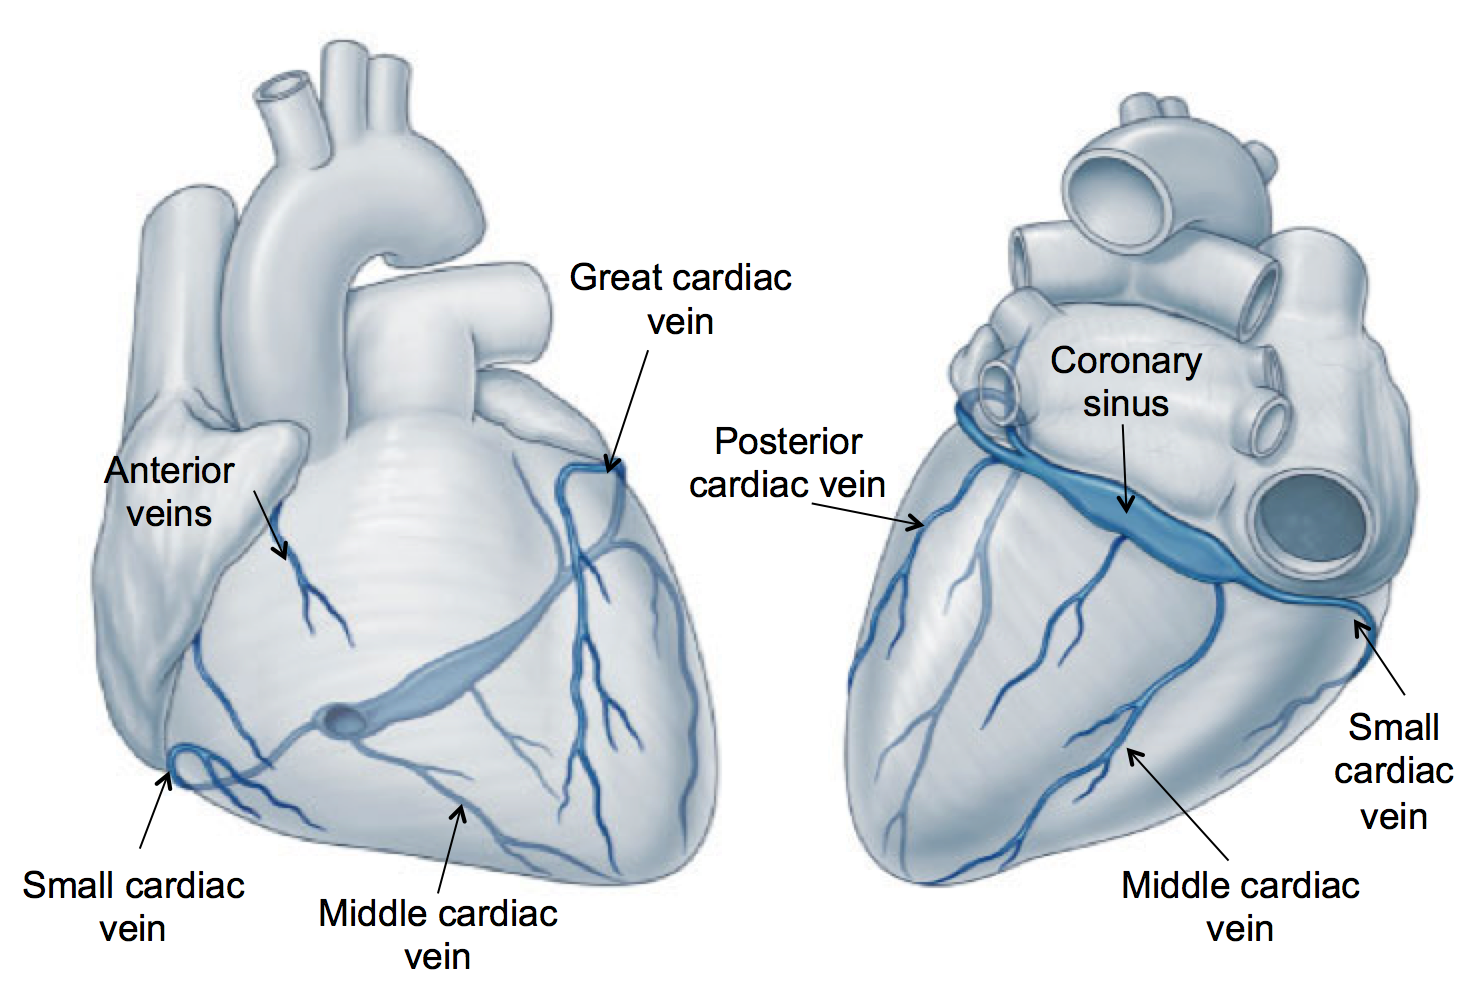
- 37Outline the classification for stage 1, & 3 of hypertensionStage 1: 140/90
Stage 2: 150/ 100
Stage 3: 160/110 - 38Name 2 constitutional and 2 non-constitutional risk factors of hypertensionConstitutional:
Age>55yrs
Black afro Caribbean
FH
Non-constitutional:
Smoking
Obesity
Physical inactivity
Heavy salt consumption
Stree - 39What is the difference between primary and secondary hypertensionPrimary: Idiopathic with no known obvious cause - linked to genetics and lifestyle (90-95%)
Secondary: A direct cause of another disease - Causes include renal artery stenosis, endocrine origin & coarctation of aorta - 40Outline how left heart failure is caused by hypertensionHypertension results in increased resistance in the aorta creating and increased afterload which the left ventricle has to work against. This results in left ventricular dilation and hypertrophy so that it is able to generate enough force to overcome the increased aortic resistance.
- 41Explain how low blood pressure is regulated by the baroreflex- Low Pa reduces arterial stretch and activation of stretch sensitive ion channels
- Reduced firing from carotid and aorta sinus to NTS and CV centre in medulla
- Increase sympathetic drive to B1 on heart => increase HR & SV
- Increased sympathetic drive to A1 on blood vessels => Vasoconstriction - 42How does the kidney normalise GFR when blood pressure is increased1. Myogenic response
2. Tubuloglomerular feedback
(Explain them!) - 43Give 5 actions of Angiotensin 21. Increased thirst and Na+ appetite
2. Na+/H+ exchanger in PCT
3. Aldosterone secretion from adrenal cortex (ZG)
4. Stimulates the release of ADH from PPG
5. Direct vasoconstriction via AT1-R - 44Explain why patients with hypertension would present with proteinuriaIncreased hydrostatic pressure leads to damage to the filtration membrane resulting in loss of the negative components of the basement membrane (glycocalyx) allowing the leakage of protein into the tubular fluid
- 45Explain the following fundoscopic findings 1. Papilloedema 2. Cotton wool spots 3. Small haemorrhages1. Increase intracranial pressure causes fluid leakage into retina
2. Damage to nerve fibres results in the accumulation of axoplasmic material in the retina - fluffy white patches
3. Increased hydrostatic pressure => endothelial cell damage => rupture - 46What would you expect to happen to serum creatinine and eGFR for a patient with hypertension?Serum creatinine: Would rise because creatinine cannot be cleared as effectively due to impaired renal function (RR: 60-120umol/l)
eGFR: would decrease due to mesangial cell expansion and ECM deposition causing occlusion of the glomerular capillaries - 47List 4 non-pharmacological interventions for hypertension1. Weight loss BMI 20-25kg/m2
2. Exercise >30 mins 3x/week at 60% max
3. Restrict alcohol <2units/week
4. Restrict salt - 48Give 2 adverse effects of phenoxymethylbenzamine1. Reflexive tachycardia
2. Postural hypotension
3. Incontinence - 49a. What class of drug is Clonidine? b. What is the mechanism of action?a. Presynaptic alpha2-R on post-synaptic sympathetic nerve endings & NTS
b. suppresses NA release & suppression of central sympathetic tone thus reducing HR, SV & causes vasodilation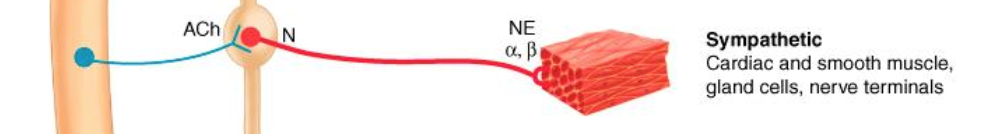
- 50Amy-lee was prescribed the beta-blocker propanolol for hypertension and now finds she often has cold hands and feet. Why might this be?- Reduced CO leads to reduced blood supply to peripheral tissues
- Blocked b2 mediated vasodilation of vessels supplying the skeletal muscles - 51Why are beta-blockers such as atenolol & bisoprolol contraindicated in diabetics?- Blockade of b2 mediated glycogoenolysis & gluconeogenesis results in hypoglycaemia.
- Blockade of sympathetic response means that the usual hypoglycaemic warnings will be absent. - 52Abbie Randall has been suffering from a persistent cough for the past 2 weeks. Upon consultation her GP finds that she has recently started taking Ramipril. Explain Abbie's coughRamipril is and ACE inhibitor which inhibits the breakdown of bradykinin in the lungs resulting in irritation and persistent cough
- 53a. What is the mechanism of action of Amlodipine? b. In what circumstance would amloppine be the first line treatment for hypertension?a. Inhibits LTCC thus reducing IC Ca2+ levels in Vascular smooth muscle cells => Vasodilation
b. Age>55 & Afro-carribbean (Most responsive to CCB rather than ACE inhibitor or ART) - 54a. what is the mechanism of action of furosemide? b. Why is the action of diuretics transient?a. Inhibits Na+/K+/Cl- co-transporter in ascending loh thus reducing Na+ & H20 reabsorption thus reducing blood volume
b. Reduction in BP stimulated by diuretics triggers renin release which in turn increases BP - 55Identify 3 possible triggers to consultation. Identify 3 possible barriers to consultation.a.
Ley referral
Sudden exacerbation of symptoms
Interference with social/working life
b.
Lack of time
Family/work responsibility
Normalisation of symptoms
Temporalisation - 56Explain the pathological basis of the following presentations in pheochromcytoma: 1. Sweating 2. Nausea & vomitting 3. Hypertension 4. Palpitations- Excess catecholamines in circulation to to presence of tumour in the adrenal medulla causes increased sympathetic drive to sweat glands => diaphoresis & Heart => Palpitations
- Stimulation of a1 receptors in area postrema causes nausea and vommiting
Información
- Descripción
- Medicine Fichas sobre Unit 3 Week 6 & 7 , creado por shirou masoodi el 06/04/2018.
- Creado por
- shirou masoodi
- Visitas
- 50
- Valoración