
Mapa mental
Pediatric head trauma and the battered child
Contenido del mapa
Pediatric head trauma and the battered child
FACTS and EPIDEMIOLOGY
- leading cause of morbidity and mortality during infancy
- vary considerably compared to adults in many aspects
- type of injury varies in relation to age and physical activity
- role of imaging is significant (CT-MRI) diagnosis, management and choice of treatment.
- 90% are mild (no hospitalisation), primary cause of death in children and adolescents
- the type and mechanics differ with age
- perinatal_period, falls(1-4y), vehicle_accidents(7-12y), abuse
Particularities
- Biomechanical properties of the child skull
- Head size
- BRAIN water content and myelination
- neonatal unmyelinated brain contains high levels of water (89%)
- More susceptible to acceleration – deceleration trauma forces the unmyelinated regions are more prone to shear injuries
- neonatal unmyelinated brain contains high levels of water (89%)
- Face to cranium ratio
- 1:8 at birth, 1:2.5 in the adult
- Increased likelihood of skull and brain injury in children // Frontal skull and lobes are more susceptible
- Neck musculature – cervical spine
- craniocervical stability depends more on ligaments than bones.
- Increased likelihood of craniocervical junction lesions
Imaging
- Plain radiographs
- limited use
- Minor injuries when CT is not required // Suspicious cases of child abuse (skeletal survey) // fracture complications such as growing fractures
- limited use
- U/S
- limited to the neonatal period for as long as the fontanels are still open // demonstrates only the peripheral lesions or the extra-axial hematomas along the convexity // Doppler technique may indicate increased intracranial pressure
- CT
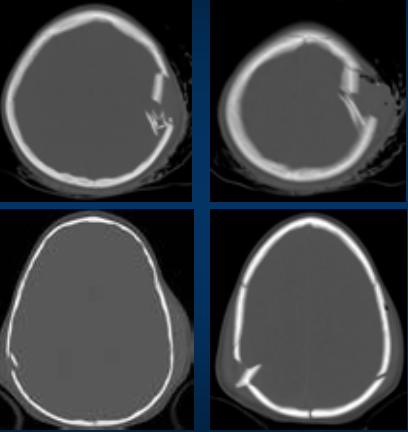
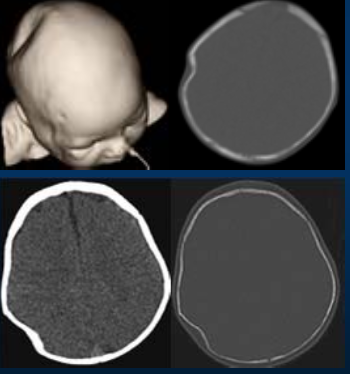
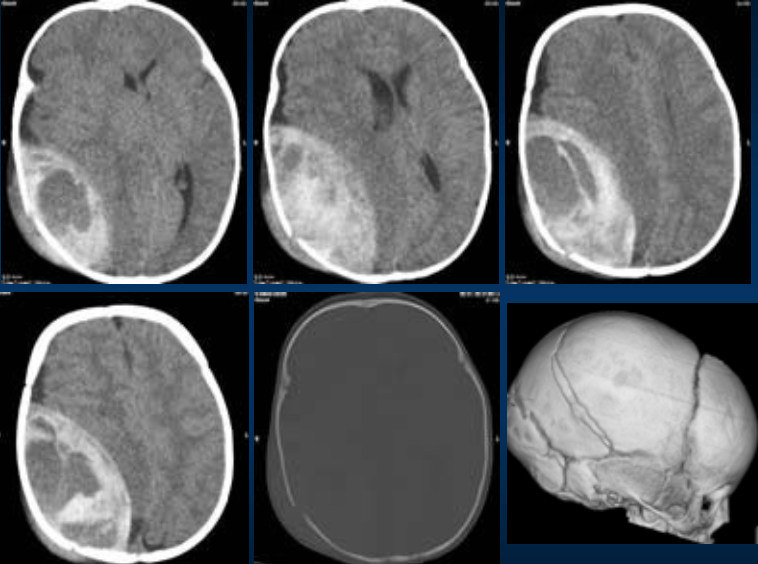
- Fractures
- linear
- 75 % of all fractures in most cases no special treatment is required the use of 3D recon often helps in their evaluation
- depressed
- associated with injury of the dura, venous epidural hematoma or contusion require surgical treatment
- Ping-pong fractures
- basilar
- 6-14% of cases of pediatric trauma patients
- complications are frequent
- CSF rhinorrhea, CSF otorrhea, ecchymosis over the mastoid bone, periorbital ecchymosis, hemotympanum, cranial nerve VII palsy
- secondary meningitis (1-5%)
- linear
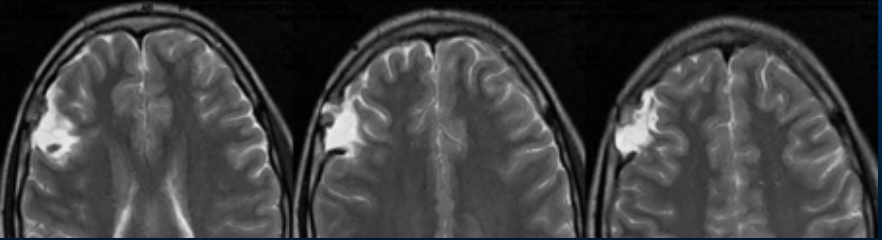
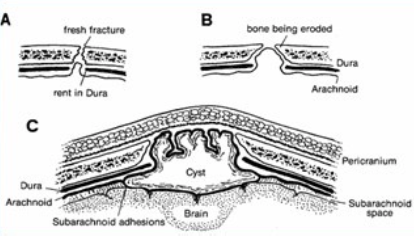
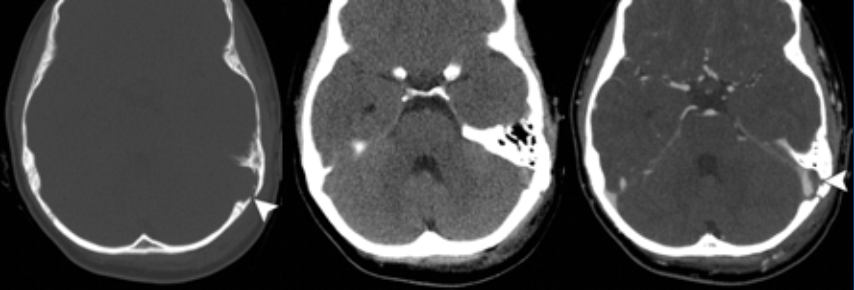
- Leptomeningeal Cyst
- growing fractures
- Tear in the underlying dura and the progressive leptomeningeal herniation through the widening of the skull defect
- Subdural hematoma
- more frequent in children than in adolescents
- not associated with a fracture
- may transverse the sutures
- nterhemispheric fissure and along the tentorium
- Subarachnoid hemorrhage
- rupture of the pial or the subarachnoid vessels
- circulation/redistribution of IVH
- rupture of an intracerebral contusion or hemorrhage into the subarachnoid space
- Intraventricular hemorrhage
- extension from intraparenchymal bleeding // deep penetrating wounds // tearing of subependymal veins // difussion from subarachnoid hemorrhage
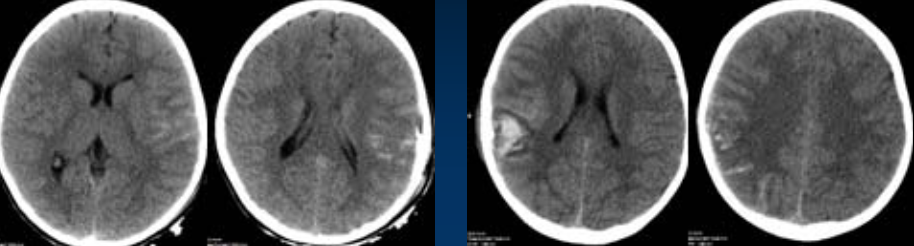
- Cortical contusions – Intracerebral hematoma
- involve superficial gray matter with sparing of the subcortical white matter
- less common in children than in adults
- mainly located in the temporal poles and frontal and occipital lobes
- shearing – straining injury due to rupture of small intraparenchymal vessels
- Diffuse Axonal Injuries (DAI)
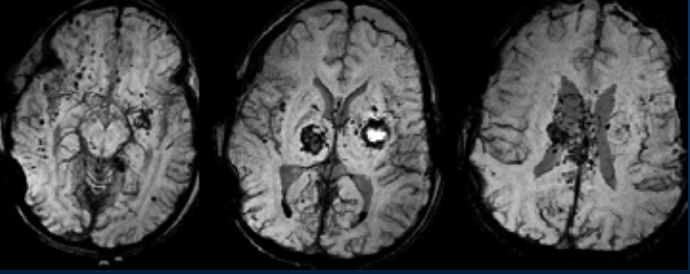
- SWI
- It has greater sensitivity than GRE in the detection of trauma related hemorrhagic lesions (esp. in DAI)
- SWI
- Vascular Injuries
- primary
- Carotid-cavernous fistulas
- communication between the internal carotid artery and one of the cavernous sinuses, due to a tear of the artery or the sinus wall
- pulsation exophthalmus, occulomotor dysfunctions dilatation and tortuosity of the superior ophthalmic vein enlargement of the cavernous sinus
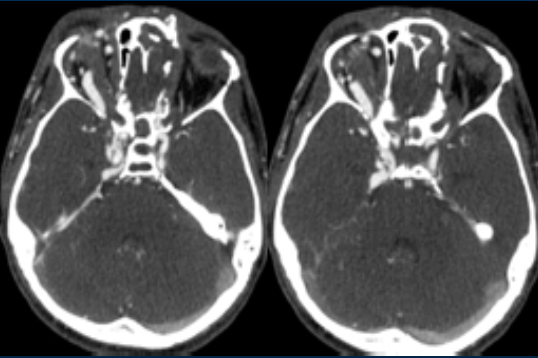
- Dissection of internal carotid / vertebral artery - thrombosis
- may be caused by a penetrating or blunt neck trauma
- Venous sinus occlusion
- direct damage or thrombosis
- Carotid-cavernous fistulas
- primary
- Hydrocephalus
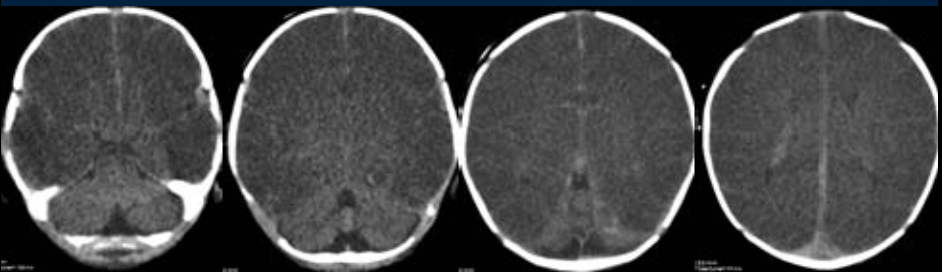
- Congestive brain / Cerebral edema
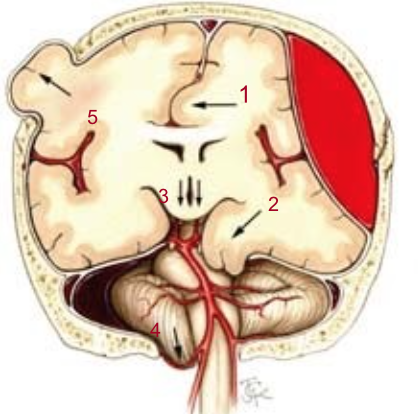
- Brain herniation
- subfalcine uncal transtentorial foramen magnum external
- expansion of brain tissue due to increased intravascular blood volume
- more frequent in children than in adults due to immature or impaired autoregulation of brain perfusion
- CT without findings during the first 12 hours
- - blurring between gray and white matter // - compression of the ventricular system // compression of the basal cisterns and the peripheral subarachnoid spaces // enhancement of subarachnoid spaces (vascular stasis) // “white cerebellum sign” // “reversal sign”
- Brain herniation
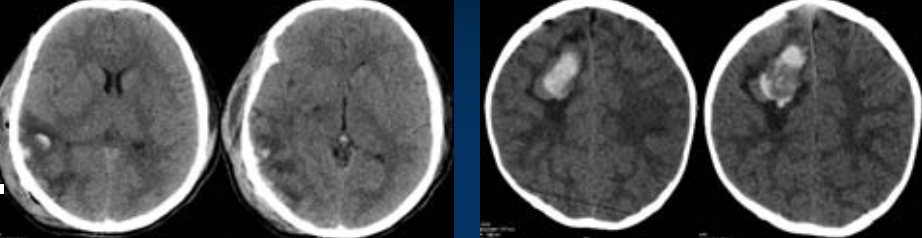
- Epidural hematoma
- less common than in adults
- better prognosis than in adults
- more frequently venous than arterial (tear of a dural sinus or diploic veins)
- Swirl sign: indicates active bleeding with risk of rapid expansion of the hematoma
- less common than in adults
- Fractures
- Perinatal injuries
- during delivery and most specifically during the stage of active pushing, due to the mechanical forces exercised on it (i.e. compression, retraction)
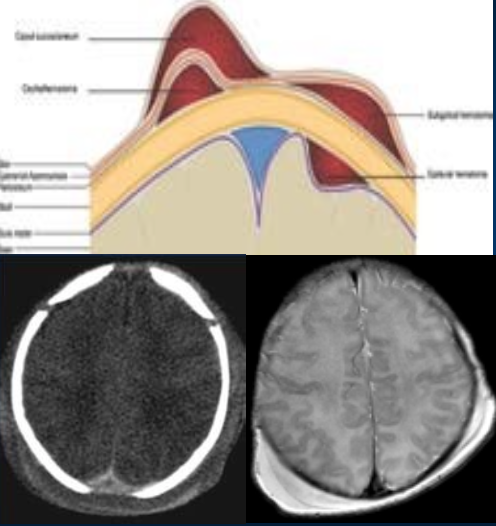
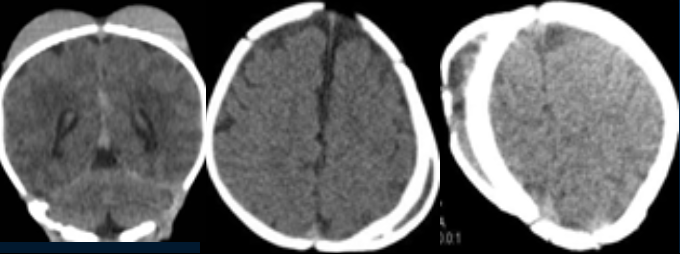
- Extracranial hemorrhage
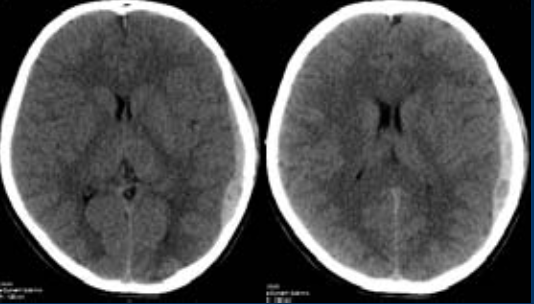
- Caput succedaneum
- serum blood collection above the periosteum
- compression of the protruding part of the fetal scalp // instrumenatal deliver
- transverses the cranial sutures
- Subgaleal hemorrhage
- between the periosteum of the skull and the galea aponeurotica
- may extend over the cranial sutures and may coexist with (40%) intracranial hemorrhage or skull fracture
- shock or hyperbilirubinaemi
- Cephalhematoma
- subperiosteal blood accumulation due to ruptured vessels
- limited by sutures especially in the parietal bone
- anaemia or blood pressure hypotension
- can calcify and form disfiguring masses visible on follow up
- Caput succedaneum
- Intracranial hemorrhage
- Subdural
- - subdural hematoma is the most common type and accounts for 73%
- Epidural
- rare in neonates
- Subarachnoid - intraventricular
- second most common type
- Parenchymal
- Subdural
- Fractures
- skull fractures are uncommon
- Plain radiographs
Abuse or Accident
- Discrepancy between trauma history and imaging findings // hemorrhage of different age // unusual findings (e.g burns or bruises) // retinal hemorrhage is present (shaken baby) // if the child has evidence of poor care
- most children deaths worldwide are due to abuse inflicted by parents. -brain injury is the most common consequence of child abuse
- Major non-traumatic brain injuries
- extraaxial lesions
- fractures (parietaloccipital or growing)
- acute with chronic subdural hematoma
- most common finding in child abuse
- parietooccipital convexity – interhemispheric fissure
- nterhemispheric subdural hematoma shaken baby
- hemorrhage of different age repetitive trauma
- interhemispheric or infratentorial subdural hematoma
- subarachnoid hemorrhage
- enlargement of the subarachnoid spaces
- intra-axial lesions
- diffuse cerebral edema
- brain contusion
- atrophy
- enchephalomalacia
- extraaxial lesions
- Major non-traumatic brain injuries
- most children deaths worldwide are due to abuse inflicted by parents. -brain injury is the most common consequence of child abuse
- Discrepancy between trauma history and imaging findings // hemorrhage of different age // unusual findings (e.g burns or bruises) // retinal hemorrhage is present (shaken baby) // if the child has evidence of poor care
Imágenes y archivos del mapa
Información
- Descripción
- RADIOLOGIA (ESNR Curso Trauma y P. Degenerativa.) CURSOS ESNR Mapa Mental sobre Pediatric head trauma and the battered child, creado por SEBASTIAN SIMONETTI el 04/04/2016.
- Creado por
- SEBASTIAN SIMONETTI
- Visitas
- 7
- Valoración