
Test
Pathology focus :)
Este test tiene tipos de pregunta que se abren en el reproductor de siempre.
Preguntas del test (81)
1Which of the following is not an example of a PAMP?
- ALipopolysaccharide
- BLipoteichoic acid
- CViral Genome (dsRNA)
- DDAMPs
- EComplement
2What do PRRs do?
- Areceptors on leukocytes that recognize PAMPS
- Breceptors on infected cells that can be activated for cell death
- Cspecified subclass of PAMPS
- DSpecial proteins displayed on bacterial surfaces
3What are some physical barriers that are part of the innate system?
- Askin
- Bmucosa
- Cstomach pH
- Dlysozomes
- Enatural body flora
- Fmacrophages
- Gbody fat
4Which cells are involved in innate immunity?
- Amacrophage
- Bneutrophil
- Cnatural killer cell
- Ddendritic cell
- EB-cell lymphocytes
- FT-cell lymphocytes
- Gbone marrow cells
- Hmast cells
- Ithymus cellls
5Which of the following isnt a granulocyte?
- Abasophils
- Bneutrophils
- Cmast cells
- Deosinophils
6Macrophages in the blood are known as monocytes.
- AVerdadero
- BFalso
7Macrophages in CNS are known as macroglia.
- AVerdadero
- BFalso
8What regarding Major Histocompability Complexes is true?
- AMHCI, MHCII, and MHCIII all serve different purposes in cell communication
- Ball nucleated cells display MHC I
- Ccytotoxic T cells interact with both MHC I and MHC II
- DMHC I recognizes antigens from the inside of the cell
- EMHC II is on all nucleated cells
- FMHC III recognizes antigens on the outside of cell
- GHelper T cells interact with MHC II
- Hsome complement proteins, cytokines, and enzymes displa MHC III
- IMHC I, MHC II, and MHC III all refer to the same receptor at different stages which is why they have very similar functions
9Which statements regarding innate immunity are false?
- AC3 convertase leads to C3 cleaving into C3a and C3b
- BC3b leads to C5 convertase activating and cleaving into C5a and C5b
- CC5b--C9 activates Membrane-Attacking Complex
- DC5a and C3a are anaphalotoxins
- EC3b is opsonin and coats bacteria as complement
- Fanaphylatoxins activate mast cell degranulation, releasing histamine and bradykinin
- Ghistamine and bradykinin lead to increased vascular permability and vasodilation
- HMembrane-Attacking Complex includes perforin and granzyme
- IMannose-Binding Lectin, Classical, and Alternative all lead to the intial step of C3 convertase
- JMannose-Binding Lectin, Classical, and Alternative all lead to the initial step of C5 convertase
10What are TCRs?
TCRs, standing for [blank_start]T-cell receptors[blank_end], are on all T-cells and allow them to interact with other [blank_start]leukocytes[blank_end] or [blank_start]other cells[blank_end]. For example, the [blank_start]cytotoxic[blank_end] TCR interacts with a host cell's MHC [blank_start]I[blank_end] in order to kill it.- AT-cell receptors
- Bleukocytes
- Cother cells
- Dcytotoxic
- EI
11There are 2 parts to adaptive immunity. The [blank_start]cell-mediated response[blank_end] occurs when an [blank_start]antigen-presenting cell[blank_end] arrives at the lymphnode and presents the antigen to the [blank_start]CD4+ T cells[blank_end] via [blank_start]MHC II[blank_end]. Specifically, [blank_start]CD4+ TH1[blank_end] will interact with the antigen-presenting cell. This interaction will lead to the chemokines [blank_start]IL-2[blank_end] and [blank_start]INF-gamma[blank_end] being releases, which activate and bring over the [blank_start]CD8+ killer[blank_end] T cells. The CD8+ killer T cell will then go off and bind to infected host cells via [blank_start]MHC I[blank_end] and initiate cell death. It does this via 2 ways: activating [blank_start]FAS ligand-receptor[blank_end] and the cytotoxic granule containing [blank_start]granzyme[blank_end] (which destroys cell inner stuff) and [blank_start]perforin[blank_end] (which punches holes.)
- Acell-mediated response
- Bhumoral response
- Cantigen-presenting cell
- Dneutrophil
- Ephagocytic cell
- FCD4+ T cells
- GTHI cells
- HTH2 cells
- ICD8+ T cells
- JMHC II
- KMHC III
- LMHC I
- MCD4+ TH1
- NCD4+ TH2
- OIL-2
- PIL-3
- QIL-4
- RIL-5
- SIL-6
- TIL-10
- UINF-gamma
- VINF-alpha
- WINF-beta
- XINF-delta
- YKiller
- ZTH II cells
- AATH I cells
- ABmhc I
- ACmhc II
- ADFAS ligand-receptor
- AEMAC
- AFcell nephrosis
- AGgranzyme
- AHlysozyme
- AIenzymes
- AJgranulozome
- AKperforin
- ALpuncturin
- AMhydrogenase
12The release of cytokines (in numerical order) [blank_start]IL-4[blank_end], [blank_start]IL-5[blank_end], and [blank_start]IL-10[blank_end] is part of the [blank_start]humoral[blank_end] response of adaptive immunity.
- Ahumoral
- BIL-4
- CIL-5
- DIL-10
13Humoral Response cannot happen without Cell-mediated BUT cell-mediated can happen without humoral having to happen
- AVerdadero
- BFalso
14Which of the following are part of the humoral response?
- Aclonal activation
- Bclonal selection
- Cclonal distribution
- Dclonal expansion
- EB plasma secretory cells
- Fclass switch
- GT memory cells
- HB memory cells
- ICD4+ TH I cells
- JCD4+ TH II cells
15Which statements regarding rolling adhesion are correct?
- Aselectins allow the phagocytic cell to roll across the epithelial walls
- Bintegrins allow the phagocytic cell to roll across the epithelial walls
- Cintegrins allow the phagocytic cell to stop at the right place in the epithelium
- Dselectins allow the phagocytic cell to stop at the right place in the epithelium
- E1L-8 enhances chemotaxis of phagocytic cells to site of injury/infection
- Fdiapedesis is transepithelial migration of the leukocyte
16Which chemokines increase the adhesiveness of epithelial cells?
- AIL-1
- BIL-2
- CIL-3
- DIL-12
- EINF-GAMMA
- FINF-ALPHA
- GINF-BETA
- HTNF-ALPHA
17Which blood results is O-?
- A

- B
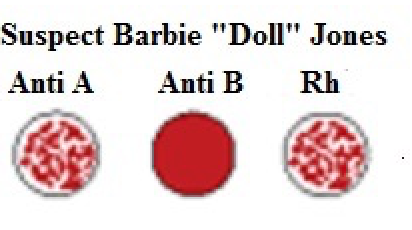
- C

- D

- E
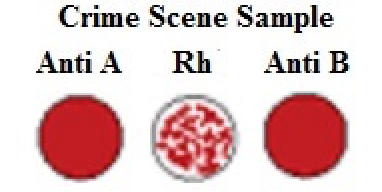
- F

- A
18Which is A-?
- A
- B
- C
- D
- E
- F
- A
19O- is universal donor for blood and universal recipient for plasma
- AVerdadero
- BFalso
20AB + is universal recipient for both plasma and blood
- AVerdadero
- BFalso
21Breast milk jaundice lasts [blank_start]longer[blank_end] than physiological jaundice. It is when certain compounds within the breast milk lead to higher [blank_start]bilirubin[blank_end] levels. It usually sorts itself out. Breast milk jaundice is quite rare.
- Alonger
- Bbilirubin
22What are the types of jaundice?
- ABreastfeeding jaundice
- BBreastmilk jaundice
- CPhysiological (Normal) Jaundice
- DJaundice of Prematurity
- EBlood Group Incompatability
- FHemolytic Disease of Newborn
- GBiliary Atresia
- HJaundicemia
23Physiological Jaundice occurs due to severe deficiency of erythrocyte decomposition and liver immaturity.
- AVerdadero
- BFalso
24How would you treat a Rhesus negative woman about to be impregnated by a Rhesus positive man due to concerns of Hemolytic Disease of the Newborn?
- ABegin Anti-D immunoglobulins now to prevent Rhesus' Disease
- BBegin Anti-D immunoglobulins once pregnant to prevent Rhesus' Disease
- CTake Anti-D immunoglobulins throughout first trimester to prevent Rhesus' Disease
- DBegin Anti-D immunoglobulins third trimester to prevent Rhesus' Disease
25Jaundice before 24 or 48 hours is [blank_start]abnormal[blank_end]. Jaundice between [blank_start]2-3 days[blank_end] to [blank_start]10-14 days[blank_end] is [blank_start]normal[blank_end]. Treatment isn't needed, but [blank_start]phototherapy[blank_end] (using UV light) can be helpful, especially for [blank_start]premature[blank_end] babies. Sometimes, a small amount of the [blank_start]matched blood[blank_end] is placed into the fetus to help speed up the process. Jaundice may last longer than that, which is [blank_start]abnormal[blank_end]. In which cases, [blank_start]surgical treatment[blank_end] and further investigation may be needed.
- Aabnormal
- Bnormal
- C2-3 days
- D1 week
- E10-14 days
- F1 month
- GNormal
- HAbnormal
- Iphototherapy
- Jx-ray fluoroscopy
- Kpremature
- Llate
- Mmatched blood
- Nmother's blood
- Oab-normal
- PnormaL
- Qsurgical treatment
- Rwide spread antibiotics
26What regarding hemolytic disease of the newborn is correct?
- Ait is due to mixing of the fetus' blood and maternal blood during the first pregnancy
- Bit is due to mixing of the fetus' blood and maternal blood during the second pregnancy
- Cleads to hyperbilirubinemia
- Dleads to anemia
- Eif severe, can lead to multi-organ failure
- Fif severe, can lead to hypoproteinemia
- Gmaternal antibodies will start attacking fetus' blood cells during first pregnancy
- Hmaternal antibodies will start attacking fetus' blood cells during second pregnancy
27If Jaundice in the first 24 hours, why might it be due to?
- ABlood group incompability
- BRed cell defects
- CRhesus disease
- Dphysiological
- EBreast milk jaundice
- Fneonatal hepatitis
28If jaundice after 14 days, what may be a cause?
- ABiliary atresia
- Bneonatal hepatitis
- Cbreast milk jaundice
- Dbreast feeding jaundice
- Ehypothyrodism
- Ferrors in new born's metabolism abilities
- Gblood group incompatability
- Hphysiological
- Ipre-eclampsia
29In gram staining, what type of microorganism stains purple?
- AGram + bacteria
- BGram - bacteria
- CGram + virus
- DGram - virus
- EGram + fungus
- FGram - fungus
30Gram negative bacteria have LPS, thin cell wall, and stain red
- AVerdadero
- BFalso
31A primary headache is a headache due to the condition itself and not another cause.
- AVerdadero
- BFalso
32What is characteristic of a cluster headache?
- Aunilateral
- Bbilateral
- Cunilateral or bilateral
- Dextremely painful--feel like banging your head or tearing out your hair
- Eperiorbital pain
- Fmild pain
- Gmedium pain
33what is NOT characteristic of migraine?
- Abilateral or unilateral
- Bpulsating or throbbing pain
- Cmedium pain
- Dperiorbital pain
34What is characteristic of tension headache?
- Amild pain
- Btight band, non-tender kind of pain
- Cbroad generalized but tender pain
- Dintense pain
- Emedium pain
- Fbilateral
- Gbilateral or unilateral
- Hunilateral
35How might you treat tension headache?
- ALifestyle changes
EX: control sleep, diet, and exercise - BParacetamol
- CNSAIDs
- DSurgical means
- Ecorticosteroids
- ALifestyle changes
36How might you treat and prevent migraines?
- ATRTMENT: NSAIDS
- BTRTMENT: paracetamol
- CTRTMENT: surgical intervention
- DTRTMENT: Triptans
ex: sumitriptan - EPRVNT: Beta-blockers
- FPRVNT: Amitriptyline
(tricyclic antidepressant) - GPRVNT: corticosteroids
37How might you treat and prevent a cluster headache?
- ATRTMENT: give oxygen for 15 minutes
- BTRTMENT: triptans
- CPRVNT: Surgical intervention--> Occipital nerve block
- DPRVNT: Verapamil (calcium channel blocker)
- ETRTMENT: Verapamil (calcium channel blocker)
- FTRTMENT: Surgical intervention--> Occipital nerve block
- GPRVNT: triptans
- HPRVNT: give oxygen for 15 minutes
38Morbillivirus is a single-stranded RNA which infects lower respiratory tract and lungs and leads to measles.
- AVerdadero
- BFalso
39What is the MMR vaccine?
- Ameasles
- Brubella
- Cmumps
- Droseola
- Erubiola
- Fmeningitis
40Which of the following is not part of the presentation of measles?
- AFever paired with a cough and coryza
- Bblotchy pink rash: beginning at the back of the ear
- CKoplik spots
- Dswelling around eyes and conjunctivitis
- Evomiting
41Measles is a notifiable disease.
- AVerdadero
- BFalso
42There is no fixxerup for measles. You can provide support via rest, drinking [blank_start]fluids[blank_end], [blank_start]antipyretics[blank_end] (reducing fever) etc. Because measles is [blank_start]contagious[blank_end], the child must stay at home until resolved illness.
- Afluids
- Bantipyretics
- Ccontagious
43If an immunosuppressed or pregnant person came into contact with an infectious measles person in the past 48 hours, what would you give?
- AMMR vaccine (or just measles vaccine)
- Bmeasles antibodies
44This type of rash is characterisitic of....?
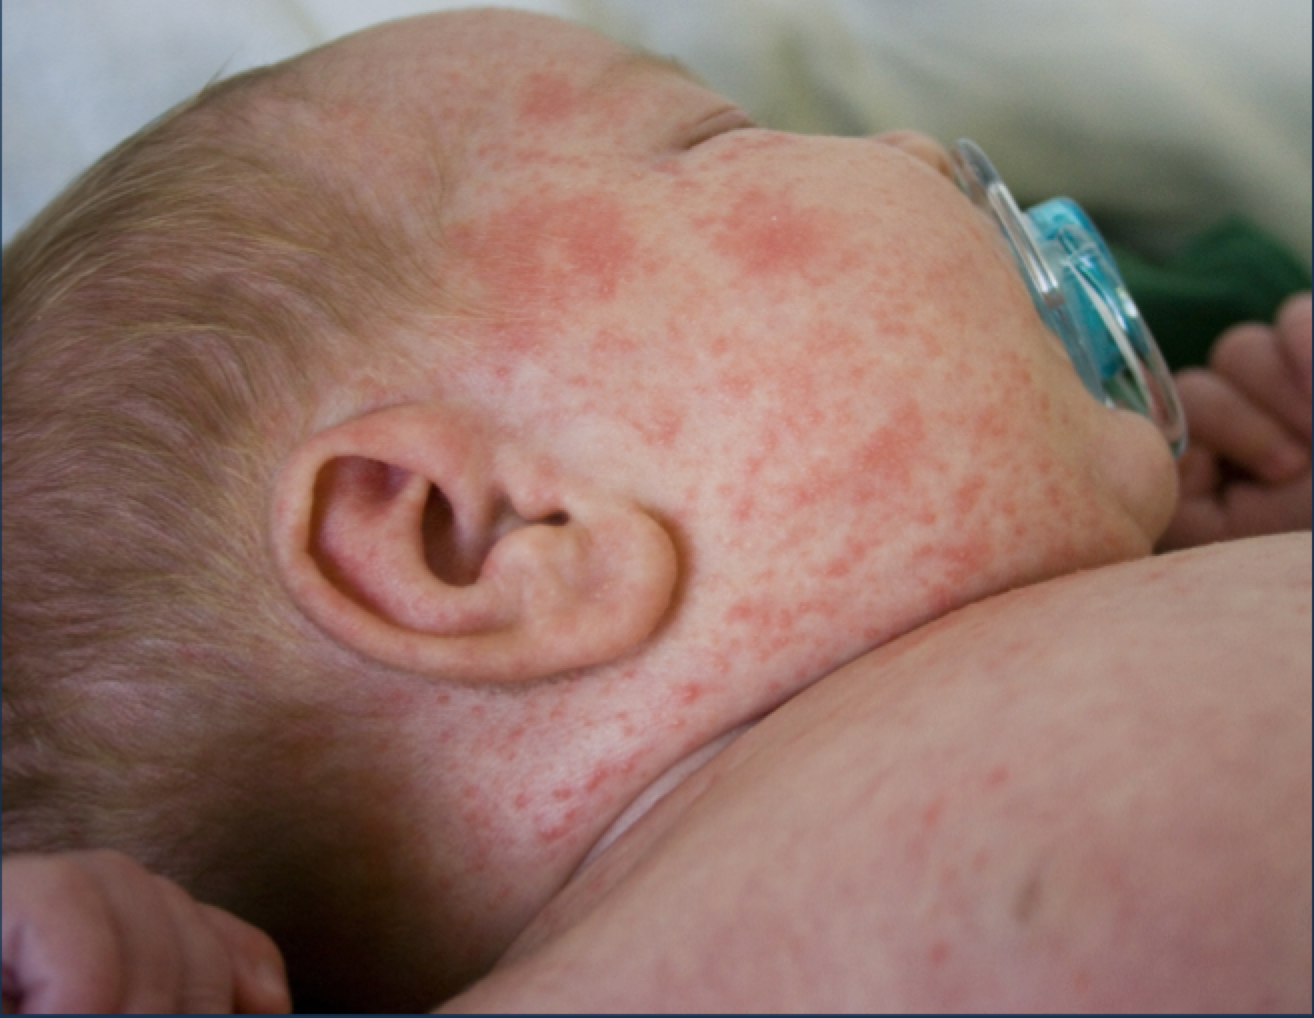
- AMeasles
- BMumps
- CChicken Pox
- DRubella
- ERoseola
- FScarlet Fever
45This severe edema of parotid glands is characteristic of what?
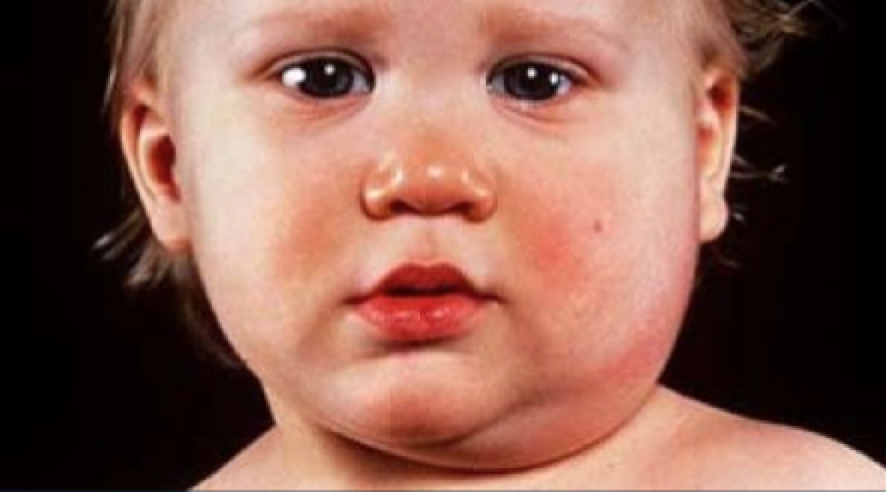
- Amumps
- Bmeasles
- Cchicken pox
- Droseola
- Erubella
- Fscarlet fever
46How might mumps present?
- Astarts off generic: malaise, fever, headache
- Bcan lead to orchiditis
- Cvomitting and cold sweats
- DKoplik spots
47The only way to manage mumps is to keep the child out of school to avoid infectious spread.
- AVerdadero
- BFalso
48Which immunoglobulin is involved in innate immunity, can act as BCR, can cross the placenta, is nonspecific and is a pentamer?
- AIgG
- BIgM
- CIgE
- DIgD
- EIgA
49Which immunoglobulin is in breast milk and helps infants until their immune system is capable?
- AIgA
- BIgE
- CIgD
- DIgM
- EIgG
50Which immunoglobulin is involved in allergy?
- AIgE
- BIgD
- CIgA
- DIgG
- EIgM
51Which is the small Y-shaped specific immunoglobulin?
- AIgG
- BIgE
- CIgD
- DIgA
- EIgM
52IgD is the only BCR of the five imunoglobulins.
- AVerdadero
- BFalso
53How might Rubella present?
- Alymphadenopathy
- Binitially very similar presentation to a normal cold
EX: anorexia, malaise, eye irritation, minor fever - Crash spreading from ears--> trunk/abdomen--> extremities
- Drash dissapears within 1-3 days
54Rubella infection during pregnancy can lead to what complication for the child later on?
- ACongenital rubella syndrome
- BRubiolla
- CAnemia
- DHeart complications
55Rubella is managed by keeping child home to avoid infectious spread, fluids, rest, and antipyretics.
- AVerdadero
- BFalso
56Chickenpox is caused by [blank_start]varicella zoster[blank_end]. It is most infectious 1-2 days [blank_start]before[blank_end] the rash appears and then stays contagious until after the rash disappears. It is a [blank_start]very itchy vesicle[blank_end] kind of rash that accompanies malaise, headache, and [blank_start]abdominal pain[blank_end]. There is no cure, but healthy individuals can be given a [blank_start]Calamine[blank_end] lotion for the itchiness. If a pregnant or immunodeficient person isn't vaccinated against chicken pox, give her the [blank_start]antibodies[blank_end]. If a pregnant or immunodeficient person develops the chickenpox rash, give them [blank_start]Aciclovir[blank_end].
- Avaricella zoster
- Bherpes zoster
- Cbefore
- Dafter
- Every itchy vesicle
- Fwidespread but merely discomforting
- Gblistering, pus-filled boils
- Habdominal pain
- Iwidespread pain
- Jpain in lymph node areas
- KCalamine
- LSilver Sulfadiazine
- Mtopical Hydrocortisone
- Nantibodies
- Ovaccination
- PAciclovir
- Qmore antibodies
- Rvaccination booster
57Shingles, most common in elderly with [blank_start]weakened[blank_end] immunity, is like the adult version of chicken pox (although adults can still also get chicken pox.) It's caused by the [blank_start]herpes[blank_end] zoster. Its characteristic difference is that the rash does not pass the [blank_start]midline[blank_end] and is limited to one [blank_start]dermatome[blank_end] (region of sensory innervation.) The patient may report [blank_start]pain[blank_end] in the area before the rash appears. Management is mainly supportive: analgesic, rest, fluids, etc. If highly severe, [blank_start]aciclovar[blank_end] is given. Not having chicken pox in childhood or getting the vaccination places you at a [blank_start]greater[blank_end] risk of getting shingles later on.
- Aweakened
- Bherpes
- Cmidline
- Ddermatome
- Epain
- Faciclovar
- Ggreater
58What bacteria causes scarlet fever?
- Astreptococcus pyogens
- Bdiptheria bacillus
- Cclostridium difficile
- Dpasteurella multocida
59Scarlet fever is not a notifiable disease
- AVerdadero
- BFalso
60How might scarlet fever present?
- Amyalgia
- Btachycardia
- Cfever
- Dsandpapery and strawberry tongue and rash
- Eaddominal pain
- Fthroat edema
- Gear infection
- Hcold sweats
61Investigation of scarlet fever is done via [blank_start]throat swab[blank_end] and culture. Management is [blank_start]penicillin[blank_end] for [blank_start]10[blank_end] days. If allergic to penicillin, [blank_start]azithromycin[blank_end] is the alternative. Management should also include symtomatic treatment: ex: [blank_start]paracetamol[blank_end]. As scarlet fever is highly contagious, person must stay home until illness resolves.
- Athroat swab
- Bblood works
- Curine test
- Dgeneral physical analysis
- Epenicillin
- Fwarfarin
- Grhogam
- Hcorticosteroids
- I10
- J7
- K14
- L30
- Mazithromycin
- Noral metronidazole
- Ooral vancomycin
- Pparacetamol
- Qibuprofen
- Raspirin
62Which bacteria are always gram +?
- Astaphylococcus
- Bstreptococcus
- Cbacillus
- Ddiplococci
- ESpiral spirochetes
63What regarding clostridium difficile is correct?
- Aopportunic pathogen
- Bgram + bacteria
- Cgram - bacteria
- Dusually due to broad spectrum antibiotic usage
- Epresents as abdominal pain and diaarea
- Fmanagement:
1. oral metronidazole for 10-14 days
2. if not responding efficiently enough, oral vancomycin - Gmanagement:
1. oral vancomycin for 10-14 days
2. if not responding efficiently enough, oral metronidazole - Hpresents as abdominal pain and diarrhoea and abdominal edema
64What regarding glandular fever is correct?
- AEpstein-barr virus found in the saliva of infected people
- Bpresentation includes Lymphadenopathy
- Cpresentation includes sore throat and enlarged tonsils
- Donly supportive management possible
- Einvestigation: an unusual increased amount of lymphocytes
- Fantiviral treatment and supportive management possible
- Gantipyretics given
- Hpresentation includes rash covering neck and abdomen
65What is true regarding Lyme disease?
- AIt is due to a parasite and bacterial infection
- Bit is due to a bacterial infection
- Cit is due to a parasite
- Dhas no characteristic rash
- Ehas characteristic "bull's eye" rash
- Fwill present as fever, lethargy, and myalgia
- Gdisease can lead to joint pathology, heart and neuro pathology
- Hthe disease can lead to respiratory failure, lower intestines pathology, and appendicitis
- Iwill present as fever, vomittting, and diarrhea
66What is meningitis?
- Ainflammation of the meninges
- Binfection of the cerebrospinal fluid
- Cinflammation of the blood-brain barriers
- Dautoimmune reaction against neurons of the central nervous system
67Which of these causes meningitis?
- Astreptococcus pneumonia
- Bneisseria meningitidis
68How does meningitis present?
- Aheadache
- Bneck stiffness
- Ca fever
- Dnon-blanching rash when glass test is done
- Eblanching rash when glass test is done
- Fvomitting
- Gmyalgia
- Hdiarrheoa
- Iseizures
69Doxycycline, an antibiotic, is given as management for [blank_start]Lyme's disease[blank_end].
- ALyme's disease
- BMeningitis
- CChicken pox
- DGlandular Fever
70Doxycycline, an antibiotic, is given as management for [blank_start]Lyme's disease[blank_end].
- ALyme's disease
- BMeningitis
- CChicken pox
- DGlandular Fever
71Intravenous ceftriaxone is given as management for [blank_start]meningitis[blank_end].
- Ameningitis
- Bscarlet fever
- Cglandular fever
- DLyme's disease
72Benzylpenicillin is given intramuscularly if there is a community danger of meningitis break out.
- AVerdadero
- BFalso
73How might the CSF appear normally?
- Aclear and colorless
- Bmurky and yellowish
- C.2-.4 protein concentration
- D<.2 protein concentration
- E60-80% plasma glucose
- F50-75% plasma glucose
- Gno organisms
- Hnatural microflora present
- Ihigh amount of lymphocytes
- Jfew amount of lymphocytes
74If the CSF has cloudy murky appearance with increased protein concentration, high amount of neutrophils, plenty of organisms, reduced glucose, and high pressure, is it a bacterial, viral, or TB infection[blank_start]?[blank_end]
- Abacterial
75What does viral infected CSF appear like?
- Aincreased protein concentration
- Bclear and colorless look
- Cnormal glucose
- Dhigher opening pressure
- Elesser glucose
- Fdecreased protein concentration
- Ghigh amount of lymphocytes
- Hhigh amount of neutrophils
- Imany organisms
- Jno organisms
76What is true regarding management of meningitis?
- Amedical emergency: do ABCD survey
- BLumbar puncture at L3/L4
- CLumbar Puncture at L1/L2/L3/L4
- DCeftriaxone 4mg intravenously
- EBlood culture if not spinal tap
- FBlood culture and spinal tap
- GCeftriaxone 4mg orally
77A [blank_start]contraindication[blank_end] is when a type of treatment backfires and ends up harming the person.
- Acontraindication
78Which of the following is NOT an example of contraindications to lumbar puncture?
- Ashock
- Bconvulsions
- Ccoagulation abnormalities
- Dinfection over site of puncture
- Edecreased intracranial pressure
- Fextensive purpura
79Sides of the tongue drain to the submandibular nodes?
- AVerdadero
- BFalso
80where does back of the tongue and middle strip drain to lymph wise?
- Adeep cervical
- Bsubmandibular
- Csubmental
- Dretropharyngeal
81Tip of the tongue does NOT drain to submental.
- AVerdadero
- BFalso
Información
- Descripción
- content courtesy of Dayo's teach
- Autor
- Usuario eliminado
- Idioma
- English
- Visitas
- 9
- Historial
- Creado el 18 ene 2018 · actualizado el 29 ene 2018
- Etiquetas
- Valoración
- Aún sin valoraciones Valora este test