
Flashcards
Week 4
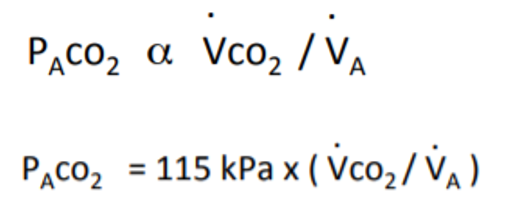
Cards in this deck (38)
- 1What is Poiseuille's law?Resistance is proportional to 1/radius^4
- 2Where is the highest resistance found?In the large airways to medium-sized bronchi
- 3Describe the general histology of the trachea-Ciliated epithelium
-Goblet cells
-Mucous glands
-Elastic cartilage ring
-Smooth muscle in ligament - 4Describe the general histology of the bronchioles-Smooth muscle
-Ciliated epithelium - 5Describe the innervation of the airways How is it stimulated?Parasympathetic nervous system
ACh stimulates M3 receptors causing bronchoconstriction. The muscarinic antagonist, atropine reduces airway resistance - 6What type of innervation is not present in the airways? What is present instead?There is no sympathetic innervation
-Adrenaline can cause bronchodilation by binding to B2 receptors on smooth muscle
-Also binds to B2 receptors on mast cells inhibiting activity
-B2 stimulation promotes muco-ciliary escalator activity (moving foreign particles) - 7How does CO2 affect the airway diameter?-Causes bronchodilation
-Feedback mechanism builds up in under ventilated parts of the lung
-Important for ventilation-perfusion matching - 8What do mast cells do?-Present in airway walls
-Mediators are released during degranulation causing bronchoconstriction
-Releases histamines, platelet aggregating factor and leukotrienes - 9What do mechanical receptors do to airway diameter?-Rapidly adapting receptors (RAR) cause bronchoconstriction
-Slowly adapting pulmonary stretch receptors (PSR) cause bronchodilation eg. during a large breath - 10What is NANC innervation?Non-adrenergic, non-cholinergic innervation
-Causes bronchodilation
-Transmitters included VIP and NO
-Substance P can also cause bronchoconstriction is asthma - 11Describe radial traction-Airways are embedded in lung parenchyma which splints airways open
-Inflation increases radial traction and airway resistance is reduced - 12Describe alveolar interdependence Why is there higher resistance in COPD patients?-Neighbouring alveoli share walls so mechanical tethering keeps airways open
There is loss of radial traction and alveolar interdependence eg. emphysema destroys lung parenchyma - 13Describe what anti-cholinergics/muscarinic antagonists such as Ipratropium do?-Blocks the bronchoconstricting action of ACh
Ipratropium. Structure prevents systemic absorption (reducing systemic side effects) and blocks anti-inflammatory effect - 14Describe the physiology of those who have asthma-Episodes of bronchoconstriction
-Bronchial hypersensitivity
-Mucosa inflammation and infiltration of immune cells (releases mediators causing bronchoconstriction)
-Increased airway secretions - 15Describe the action of B2 agonists such as salbutamol and salmeterol/turbutaline-Stimulates the AC/cAMP/PKA pathway to cause bronchodilation and reduce inflammation
Salbutamol s/e: tachycardia, tremor, airway hyper-responsiveness. Symptomatic relief
Salmeterol/turbutaline: slow-onset/long-acting - 16Describe the action of methylxanthines such as PDE inhibitors and theophylline/aminophyllinePDE inhibitors: increase cAMP, causing bronchodilation and reducing inflammation
Theophylline/aminophylline: has a narrow therapeutic window. S/e: headache, restlessness, abdominal symptoms, arrhythmias. Use has declined - 17How would you test for asthma?-Lower FEV1:FVC
-Use low doses of a cholinergic agonist. There would be more bronchoconstriction than in a healthy person - 18Describe how monoclinal anti-IgE antibodies such as Omalizumab work-S.c. injection
-Reduces circulated IgE, mast cell degranulation and inflammation
-Used to treat severe allergic asthma
-Can cause anaphylaxis in rare instances - 19Describe aspirin-induced asthma Treatment adjunct?-Sensitivity develops in adulthood
-Women>men
-Symptoms: rhinorrhea (runny nose), nasal congestion, sinusitis
Montelukast - 20Describe how sodium cromoglicate/cromolyn works-Prophylactic treatment (prevents disease)
-Inhibits release of inflammatory mediators from mast cells and RAR axon reflexes
-Mild s/e: coughing, wheezing, dry throat
-Reduces need for corticosteroids/bronchodilators - 21Describe how corticosteroids such as Bleclamethazone work-Reduces airway inflammation and hyper-responsiveness
-Prevents rather than relieves
Beclamethazone is metabolised to the active form in the lungs reducing systemic s/e. It represses genes used in inflammatory processes - 22Describe how drugs such as Zileuton and Montelukast targets leukotriene pathwaysZileuton:
-leukotriene antagonist
-has to be take 3-4x day (problems with patient compliance)
Montelukast:
-leukotriene antagonist
-single daily dose
-Used in severe chronic and exercise induced asthma
-Bronchodilates
-Reduces mucus secretion and inflammation - 23How do histamine receptor antagonists such as Ketotifen work?-Hi-receptor antagonist
-Anti-inflammatory
-Reduces reliance on steroids and bronchoconstrictors
-S/e: drowsiness - 24Describe the alveolar gas tensions. What do they set? What sets the PCO2 and PO2 in the blood leaving the lungs?They are stable and so set stable arterial gas tensions
The alveolar partial pressures - 25What 2 factors determine alveolar PCO2 tensions? Describe their effectsIncreasing V(dot) CO2 concentrates PACO2
Increasing V(dot)a dilutes PACO2 - 26What 2 calculations can be used to calculate PACO2?
- 27How does PACO2 remain constant? At what value is this? What is PaCO2 a clinical measure of?If VA increases in proportion with VCO2
5kPA
The adequacy of V(dot)A - 28Define hyper/hypoventilateHyper: ventilating alveolar gases more than metabolic need
Hypo: not breathing enough for metabolic need - 29What is the alveolar gas equation?

- 30Uses of the alveolar gas equationUsed to calculate PAO2
-P(A-a)O2 difference is calculated
-If more than 1kPa, there is an impairment in the respiratory system - 31What is Graham's law? Does CO2 diffuse slower or faster than O2?Diffusion in the gaseous phase is dependent on deltaP and is proportional to 1/(square root) MW
MW= molecular weight
Slower - 32What does diffusion of a gas through liquid depend on?Concentration difference
A more soluble gas maintains a higher concentration difference and diffuses easier - 33What is Henry's law?Concentration of gas= partial pressure x solubility coefficient (alpha)
- 34CO2 diffuses 20 times more easily than O2. What are the clinical implications of this?Any diffusion limitations will show up firstly with O2 rather than CO2 transfer ie. hypoxia before hypercapnia
- 35What is uptake of a gas into blood dependent on?The partial pressure difference which is dependent on:
-solubility
-chemical combination - 36Equation for the diffusion constant How is it measured in a real life scenario?Using CO as it has a high affinity for haemoglobin
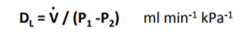
- 37What is the pulmonary diffusing capacity reduced by?Reduced effective surface area: loss of lung tissue, airway obstruction, capillary obstruction, VQ mismatch
Increased diffusion path length: thickened alveolar-capillary membrane, accumulation of lung fluid, increased intracapillary distance - 38How might a patient present clinically is their pulmonary diffusing capacity (DL) is reduced?-Hypoxic
-Cyanosis aggravated by exercise
-Increased alveolar ventilation
-Decreased PaCO2
-Normal ventilatory capacity
Information
- Description
- Drugs influencing airway resistance (including bronchodilators) Alveolar Gases and Diffusion
- Created by
- Dolu Falowo
- Views
- 4
- Rating