
Flashcards
Obstetrics 1
Cards in this deck (200)
- 1What is primary PPH?Loss of 500ml or more blood from the genital tract within 24 hours of the birth of the baby
- 2What is Secondary PPH?Abnormal or excessive bleeding from the birth canal between 24 hours and 12 weeks postnatally
- 3Minor PPH?500ml-1000ml
- 4Major PPH?>1000ml
- 5Gran-Mulltip?>4 babies. Increase risk of PPH
- 62 signs look for to establish if placenta has separated?1) Lengthening of the cord
2) Fresh blood - 7What is the risk of forcing the placenta prior to separation?Uterine inversion
- 84 general causes of PPH?1) Tone- uterus not contracted down.
2)Trauma-tear
3) Tissue- retained placenta tissue left in uterus
4) Thrombin- coagupathy - 9Drugs to use to pharmacologically promote uterine contraction?1) Syntometrine (2 doses)
2) Oxytocin (Syntocion infusion)
3) Misoprostol
4) Hemabate (PGF2a) - 10How to manually promote uterine contraction?1) uterine massage
2) Bimanual compression - 114 procedures used to stop bleeding?1) Hysterectomy
2) Balloon in uterus
3) embolisationof uterus
4) B-linch procedure - 12How much increased risk of thromboembolism by pregnancy?X6
- 13How much increased risk of thromboembolism by C-section?X10
- 14What % is the incidence of non-fatal PE or DVT in pregnancy normally compared to when have C-section?Pregnancy= 0.5%-1.0%
C-Section= 0.5% - 15What are the odds of maternal mortality from a thromboembolism?Less than 1 in 1000
- 16What treatment for a woman who is pregnant with suspected VTE?LMWH- e.g Enoxaparin (clexane) and dose is based on BOOKING WEIGHT of woman
- 17What method is used to deliver placenta actively?Syntometrine given and use of 'controlled cord traction'
- 18Define an 'Ectopic' pregnancy?Pregnancy occuring outside the uterine cavity
- 19Rate of ectopic pregnancies?11/1000 (but is increasing )
- 20Maternal mortality with ectopic pregnancies?1/2500
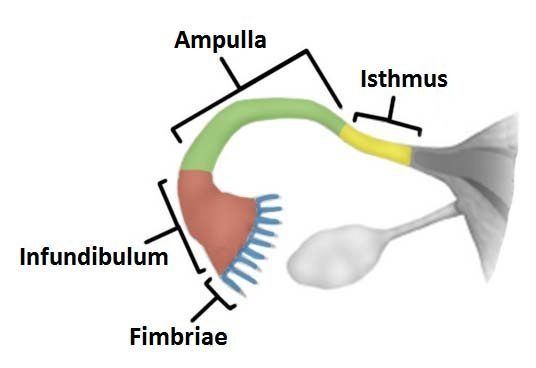
- 21Most common site of ectopic pregnancy?In the Ampullary region of the fallopian tube (70%)
- 22RF for an ectopic pregnancy? (6)-Previous PID
-Previous ectopic
-Previous tubal pregnancy (steriliation, reversal)
-Pregnancy in the presence of IUCD
-POP
-IVF - 23Symptoms of ectopic pregnancy?-Lower abdo pain (due to distention of the tube or peritoneal irritation)
-Vaginal bleeding
-Should tip pain- diaphragmatic irritation
-fainting- hypovolaemic - 24Signs of ectopic pregnancy?- abdo tenderness + rebound/guarding
-adnexal tenderness
-Shock- tachy, hypotension, pallor - 25How to diagnose an ectopic pregnancy?-Transvaginal USS
- 26What is PUL?Preganacy of Unknown Location- a positive pregnancy test with no signs of intra or extrauterine pregnancy on USS
- 27What % of early pregnancies are PUL?15-20%
- 28Methods of managing ectopic pregnancies?1) Expectant management (watch and wait)
2) Medical (methotrexate)
3) Surgical (salpingectomy or salpingotomy) - 29What is a 'threatened miscarriage'?Vaginal bleeding at <24 weeks gestation
- 30What is 'delayed (missed) miscarriage'?Where there is a gestational sac but no fetal heartbeat
- 31What defines 'recurrent misscarriages'?3 or more consecutive misscarriages without a known cause
- 32What % do misscarriages make up on clincally diagnosed pregnancies?15-20% (1 in 5 pregnancies are misscarriages)
- 33Most common cause of misscarriage?Genetiv abnormalities (50-85%)
- 34What test determines future management of PUL?-hCG (but clinical symptoms better give better indication of future managment)
- 35When would expectant managment for ectopic pregnancy be apropriate?If minimal symptoms, stable patient, painfree and falling hCG
- 36When is medical management for ectopic pregnancy first line treatment?-women can return for follow up
-no significant pain
-unruptured ectopic with adnexal mass <35mm
-no visible heart beat
-Serum hCG <1500
-USS confirming no intrauterine pregnancyIs first line for women who can return for follow up) - 37When is surgery first line management for women with ectopic pregnancy?Is first line if woman is unable to return for follow up after methotrexate or if symptoms/signs of:
-significant pain
-adnexal mass >35mm
-fetal heartbeat on USS
-serum hCG of >5000 - 38What is surgical treatment for ectopic pregnancy?Salpingectomy- removal of fallopian tubes
- 39What is offered to rhesus negative women following removal of ectopic?Anti-D
- 40If a woman is less than 6 weeks pregnant and is bleeding but not in pain- how manage her ectopcic?Expectant management:
-repeat pregnancy test 7-10 days later and return if test is positive or if symptoms get worse (then need to refer to EPAC) - 41What is the rate of reoccurance of ectopic pregnancy?18.5%
- 42What percentage of women expperience bleeding in ealry pregnancy?30%
- 43How to diagnose and manage a misscarriage?1) transvaginal USS to assess location and viability of pregnancy
2) if location not found- repeat scan, measure hCG, laparoscopy
3) if viability not established- repeat scan in 7 days - 44From how many weeks can we see a viable fetus?5.5 weeks transvaginally
- 45How does bHCG change within a viable pregnancy and with miscarriage?-viable pregnancy- doubling time is 2 days
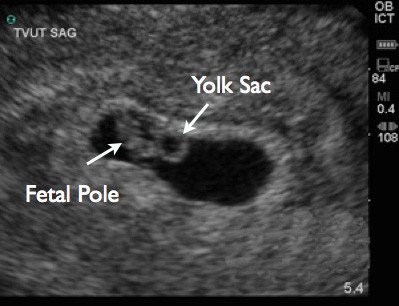
-complete miscarriage- 1-2 days - 46What is the fetal pole?thickening of the margin of the yolk sac of a fetus during pregnancy. Should see if bHCG is 1500-2000
- 47Management of miscarriage?1) Expectant- first line approach lasts 7-14 days.
2) Medical uterine evacuation- vaginal or oral misoprostol used to stimulate uterine expulsion.
3) Surgical treatment- manual vacuum aspiration under local or general - 48What 'suggests' a complete miscarrigae?If bleeding and pain settle. Woman will be advised to take a urine pregnancy test after 3 weeks to confirm.
- 49What 'suggests' an incomplete miscarriage?If bleeding and pain persist or increasing
- 50What suggests a 'missed' misscarriage?Is a 'silent' miscarriage and no bleeding or pain
- 51How much misoprosol used if missed miscarriage or incomplete?1) missed miscarriage- 800ug oral/vaginally
2) incomplete miscarriage- 600ug oral/vaginally.
--> bleeding should start 24 hours after treatment
*also offer pain relief and anti-emetics*
*must repeat preganacy test 3 weeks post to confirm Tx has worked* - 52What is Gestational Trophoblastic disease?A group of conditions in which there is abnormal proliferation of gestational trophoblast tissue.
- 53Examples of Pre-Malignant Gestational trophoblastic disease?1) Partial Molar pregnancy
2) Complete molar pregnancy - 54Examples of Malignant gestational trophoblast disease?1) Invasive mole
2) Choriocarcinoma
3) Placental site trophoblastic tumours - 55How common is a molar pregnancy?1 in 1000 live births
- 56Presentation of a Molar pregnanacy?-Vaginal bleeding
-Excessive Nausea and Vomitting (Hypermesis Gravidarum)
-Uterus is large for dates
-hyperthyroidism? - 57What is the risk that may follow complete molar pregnancy?10% of complete molar pregnancies will go on to develop invasive disease!
- 58If women continue bleeding after pregnancy- what must we always consider?Choriocarcinoma! Give methotrexate to treat and monitor bHCG fir 6 months- 2 years
- 59Genetics of partial and incomplete molar pregnancies?Complete mole: 2 sets of paternal genes, and no maternal genes.
Partial mole:
3 sets of genes, 1 maternal and 2 paternal.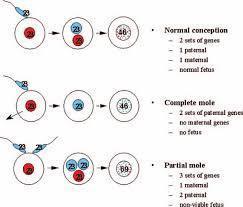
- 60What is this and used for? Risks?Amnihook- used for amniotomy for inducton of labour.
Risks- cord prolapse if lying between babies head and cervix. Can cause fetal asphyxia if untreated.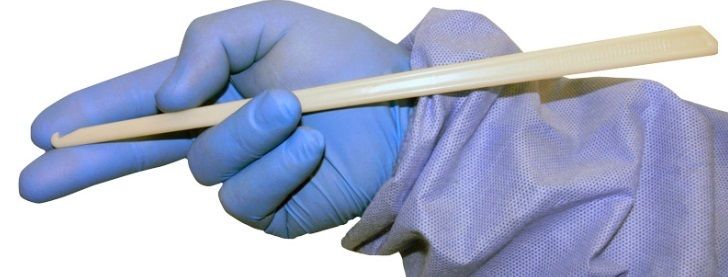
- 61How to treat cord prolapse?Decompress the cord by elevating the fetal head manually or by putting the mother in a prone knee-chest position or by filling the maternal bladder with saline.
-Emergency C-section may be needed. - 62When use membrane sweep? Evidence for use?Offered at 40-41 weeks in nullips and 41 weeks in multips.
8 women are membrane swepts to prevent one formal induction. (NNT- 7) - 63What determines a 'favourable' induction?A bishops score of >5.
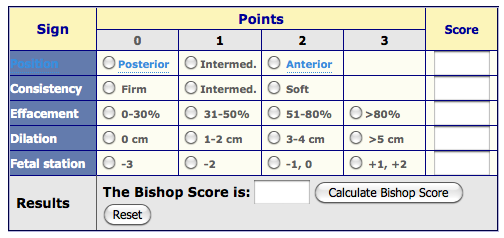
- 64Contraindications for inductions of labour?-Breach
-Fetal distress
-placenta previa
-vasa previa
-cervical fibroid - 65What is Vasa Previa?Where fetal BV run across or through uterus opening- and these BV could rupture when when the supporting membranes rupture.
- 66What is determines an 'unfavourable' induction?Bishops score <3.
- 67What % of labours are induced?20%
- 68Indications for induction of labour?-Post-dates (>42)
-IUGR
-Pre-Eclampsia
-diabetes
-previous stillbirth
-pre-labour prolonged rupture of membranes
-twins - 69Risks of induction of labour?-prolonged labour duration
-more likely to require regional anaesthesia- as sudden, V painful contraction- and therefore more likely to require instrumental delivery
-Uterine hyperstimulation
-Uterine rupture
-Umbilical cord prolapse
-Failed induction- LSCS - 70What is Bishop's score system based on?>8- woman likely to go into labour & cam break waters easily.
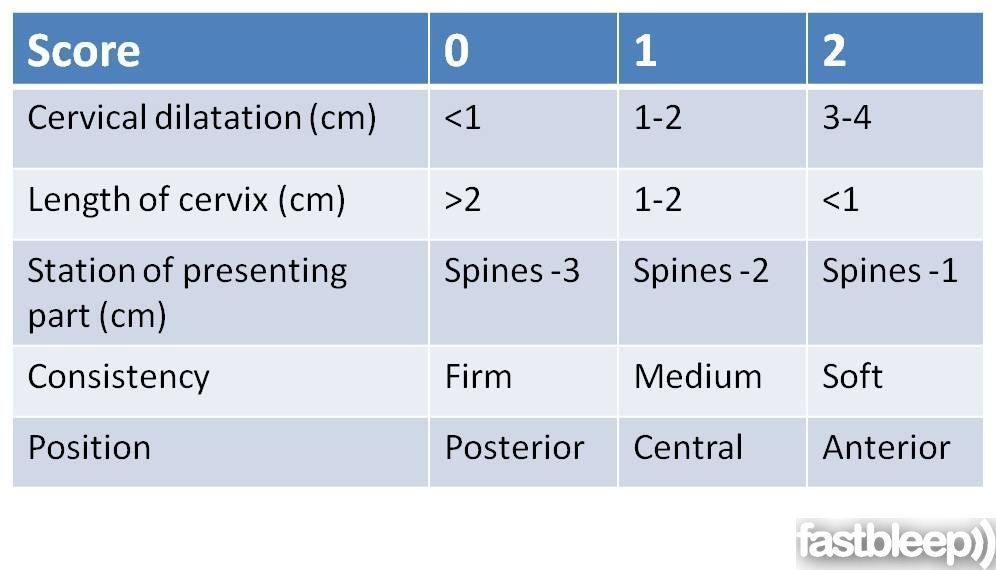
- 71Methods of induction of labour?1) Prostaglandins (Pessary/propress= 24 hour tampon) or Gel= applied locally 4 hours, and can repeat 4 horus later) which ripens the cervix to enable amniotomy
2) Amniotomy- artificial rupture of membranes
3) Syntocinion (oxytocin) infusion
4) Mechanical cervical dilators - 72What is risk of inducing labour in a woman with a previous C-section?Increased risk of uterine rupture (1 in 100 if induced, or 1 in 200 if spontaneous labour anayway)
- 73What is this method called and what for?Cook cervical ripening balloon which is used to mechanically dilate the cervix
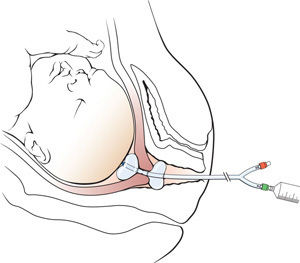
- 74What is 'Naegeles rule'?A rule to work out EDD= LMP- 3 months + 7 days
- 75What anagesia should be used in Labour?non-pharmacological:
-Hypnotherapy/relaxation
-Aromatherapy
-Tens- transcutaneous electrical nerve stimulation
-water
Pharmacological:
-paracetamol, codiene, diamorph, pethidine (short term effects on neonate if delivered within 2 hours of taking)
-Epidural
-Entonox- gas and air (nitric oxide)
-Transpudendral nerve block - 76What % of pathological CTGs mean that fetus is compromised?50% of pathological CTGS mean that fetus is in danger and needs urgent delivery
- 77What is a better marker of fetal wellbeing if CTG is pathological?Fetal blood sampling- take blood from fetus scalp
-PH>7.25 then need repeating in 1 hour if CTG the same
-PH 7.2-7.25 then repeat in 30 mins
-PH <7.20 then fetus is risk of hypoxia and needs delivery - 78What is the Harmony test?Measures free fetal DNA from mothers blood (blood taken from vein in mothers arm) and gives a strong indication if fetus is high or low risk of having a triosomy 21 (downs), 18 (edwards) or 13 (patau syndrome)
- 79How births are Trisomy 21?1 in 700 births (risk increases with maternal age)
- 80What further tests used if high chance of trisomy from Harmony test?1) Chorionic villus sampling- small sample of cells taken from the placenta either transabdominally or transcervically and checks if chromosomal abnormailities. Usually perfromed between 11-14 weeks
2) Amniocentesis- small sample of amniotic fluid taken. Carried out between 15-18 weeks of pregnancy. - 81What medication is given to women as first line treatment for moderate to severe HTN (pre-eclampsia) in pregnancy?oral labetalol
- 82If birth is considered likely within 7 days in women with pre-eclampsia, and woman is 24-34 weeks pregnant- what give?Give two doses of betamethasone* 12 mg intramuscularly 24 hours apart in women between 24 and 34 weeks
- 83What is the name of the validated questionnaire to assess the severity of nausea and vomiting in pregnancy?Pregnancy-Unique Quantification of Emesis [PUQE] score
- 84If moderate to high risk pre-eclampsia- what is recommended that women take?75mg/day of aspirin from 12 weeks onwards to reduce risk of blood clots
- 85Common symptoms of obstetric cholestasis?-Itching on palms and sole of feet
- 86What surgical approach is used with severely overweight women for C-sections?supra-panus
- 87Risk factors for pre-eclampsia?
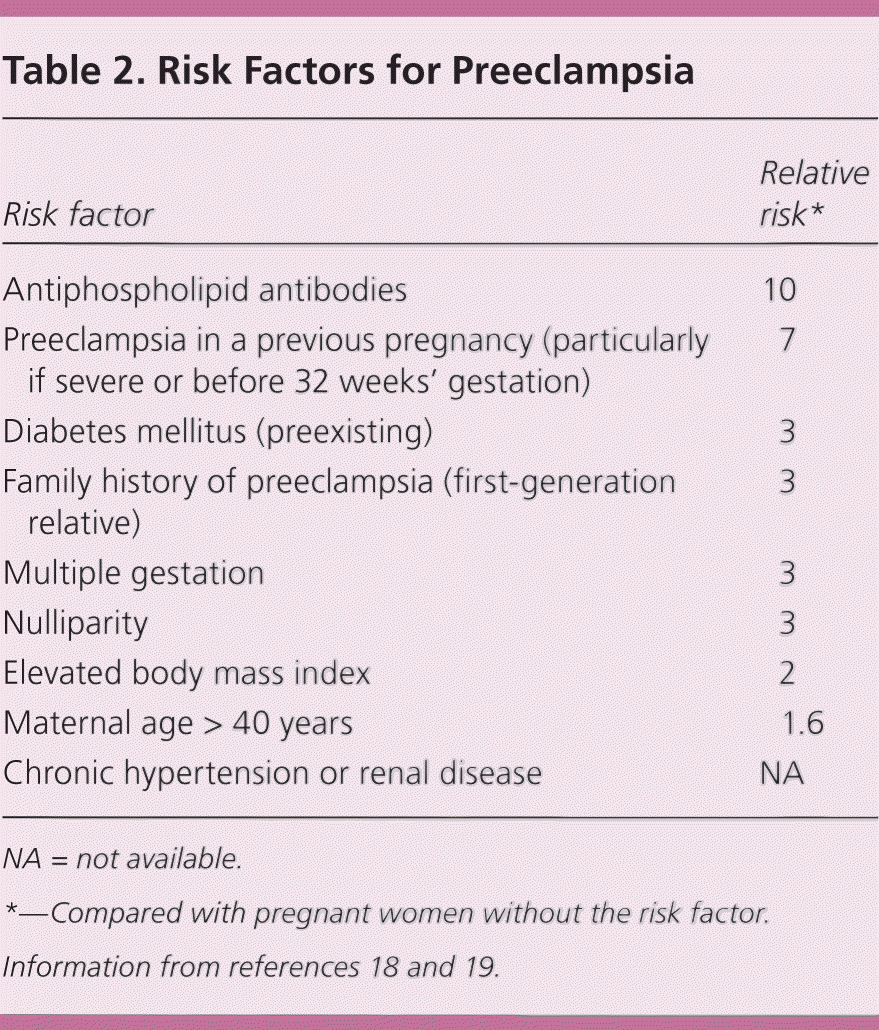
- 88From what gestation can a fetus heart beat be heard?6 weeks
- 89From what date is a pregnancy counted from?From the first date of last period
- 90What steps should be used by scanner in EPAC to determine a viable pregnancy?1) Look for fetal heartbeat
2) (If not) then look for fetal pole, and if (identiy then measure crown-rump length (7mm cut off)
3) (if not) then measure mean gestational sac diameter (25mm cut off) - 91What is deemed 'early pregnancy'?13 weeks
- 92what is Expectant management?A management approach in which treatment is not administered, with the aim of seeing whether the condition will resolve naturally.
- 93What must be offered to women who attend EPAC?A transvaginal ultrasound scan to identify the location of the pregnancy and whether there is a fetal pole and heartbeat
- 94What management should be offered as first line for a woman with confirmed diagnosis of miscarriage? (when not?)Use expectant management for 7–14 days, but NOT when:
1) woman at increased risk of haemorrhage (e.g- she is in the late first trimester)
2) previous adverse and/or traumatic experience associated with pregnancy (for example, stillbirth, miscarriage or antepartum haemorrhage)
3) At increased risk from the effects of haemorrhage (for example, if she has coagulopathies or is unable to have a blood transfusion)
4) there is evidence of infection. - 95surgical management of miscarriage offered?1) LOCAL anaesthetic manual vacuum aspiration in OP or clinic
2) surgical management in a theatre under general anaesthetic. - 96When to refer to EPAC?Woman with bleeding and other symptoms of early pregnancy complications (pain)
- 97If a pregnancy is <6 weeks, and woman bleeding but not in pain, what do?Advise to:
- repeat a urine pregnancy test after 7–10 days and to return if it is positive. (If negative then misscarriage) - 98What factors may mean that a women in EPAC requires a transabdominal scan rather than a transvaginal?-woman has enlarged uterus
-fibroids
-ovarian cysts
*but there is limitation to transabdo scans* - 99If crown-rump length of fetus is <7mm with trasnvaginal USS scan, and no visible heart beat- what do?-need to perform a second scan minimum of 7 days later to confirm miscarriage diagnosis
- 100For a woman with an increase in serum hCG concentration greater than 63% after 48 hour- what is likely?-inatruterine pregnancy is likely as HCG doubles every 48 hours in a viable pregnancy
- 101Degree classification of tears in labour?SULTAN CLASSIFICATION
1st degree- injury to perineal skin and/or vaginal mucosa
2nd degree- injury to perineum involving perineal muscles but not involving sphincters
3rd degree- injury to perineum involving sphincter....
3a- <50% external anal sphincter torn
3b- >50% external anal sphincter torn
3c- internal anal sphincter torn
4th degree- injury to perineum involing sphincter complex and anorectal mucosa - 102What type of episitomy be considered with instrumentla delivery?Medio-lateral episiotomy (cut 60 degrees away from perineum)
- 103What cell type lines the proximal anal canal?rectal mucosa (columnar epithelium)
- 104What cell type lines distal anal canal?modified squamous epithelium
- 105Which techniques should be used to accomplish the repair of the anorectal mucosa?sutures using either the continuous or
interrupted technique - 106techniques should be used to accomplish the repair of the internal anal sphincter?Interrupted or mattress sutures without any attempt to overlap the IAS
- 107Which techniques should be used to repair the external anal sphincter?overlapping or an end-toend
(approximation) method - 108Prognosis following an anal repair?Women should be advised that 60–80% of women are asymptomatic 12 months following delivery
and EAS repair. - 109Incidence of twins in UK?1 in 65 births in UK are twins
- 110Most common type of twin?DCDA (Dichorionic Diamniotic)- usually dizygotic from 2 eggs and 2 sperm and often due to IVF
- 111What do monochorionic twins mean?one fertilsed egg that then divides to form identical twins. Can be diamniotic so babies in 2 seperate sacs or monoamniotic where babies in 1 sac.
- 112What is twin-twin transfusion syndrome and what related to?Often caused by twins sharing a placenta (monochorionic twins).
It is where there is abnormal vessels through the shared placenta which mean that blood flows mainly from one baby (donor) which becomes malnourished, to another baby which can develop heart failure. - 113How treat twin-twin transfusion syndrome?Detect early and treat: laser ablation of connecting vessels in utero
- 114What type of twin is most likely to be still birth?MCMA
- 115Incidence of conjoined twins worldwide?1 in 90,000
- 116Most rare form of twins? Risk?MCMA:
High risk of cord entanglement - 117Risks of multiple pregnancies?1) Anaemia
2) Congenitial- more likely to have false positive from downs screening & more likely ot suffer complications from amniocentesis
3) Pre-term labour
4) HTN and pre-eclampsia- 2-3 times more likely to suffer. need to take aspirin daily, and BP/urinalysis taken at every scan.
5) Fetal Growth restrction - 118What % of twins are born pre-term?50% born pre-term
10% born <32 weeks - 119Delivery planning for different types of twins?DCDA elective delivery- 37-38 weeks
MCDA elective delivery- 36-37 weeks
MCMA elective delivery by C-section at 32 weeks - 120Circumstances which would enable a normal vaginal delivery for twins?If twin 1 is cephallic and there is an uncomplicated twin pregnancy (DCDA or MCDA) then vaginal birth should be offered.
**There is an increased risk of morbidity for twin 2 at delivery, and increased risk of C-section even after successful 1st vaginal birth** - 121What would be offered if first twin is not cephallic?Elective C-Section should be offered and administration of corticosteriods to help prevent respiratory distress
- 122When routine growth scans for differing twins?DCDA twins- every 4 weeks from 24 weeks
MCDA- every 2 weeks from 16 weeks
*must always annoate twins on scans to ensure monittoring growth correctly** - 123How manage anaemia of mother if twins?FBC on booking, 20, 28, 34 weeks and treat if >115 with feroud sulphate 200mg orally bd.
- 124How best to screen for chromosomal abnormailites if twins, and at what gestation?11-13 + 6 days- mucal translucency
anomaly scan- 18-20 weeks - 125What is this conditon? Incidence?Total placenta previa- where the placenta cover the os and is graded by how close/how much it covers the Os
-10% risk at 20 weeks, 1% risk at term
*avoid PV exams and sex*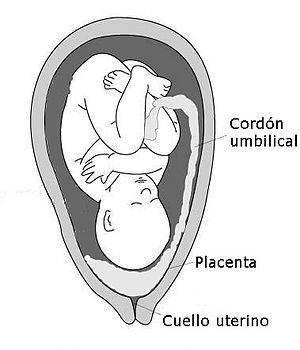
- 126What is this?Low lying placenta
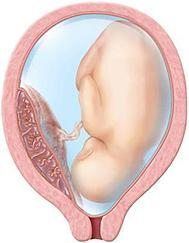
- 127RF for placenta Praevia?-Previous Termination of pregnancy
-Previous Praevia
-Increased maternal age
-Multi-parity
-Previous LSCS
-deficient endometrium (uterine scar, endometriopsis, fibroids)
-Multiple pregnancies
-Smoking - 128Significance of vasa previa?Fetal blood (cord) vessels run through the membranes covering the cervix. These vessels can rupture which can cause massive heamorrhage and baby can die.
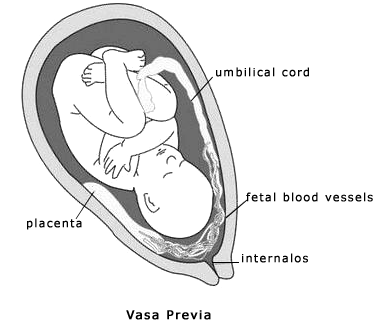
- 129Classic presentation of Vas previa?painless vaginal bleeding, rupture of membranes, and fetal bradycardia
- 130How diagnose vasa previa?Transvaginal ultrasonography
*Differential is 'funic presenation' where on US the cord moves away - 131statistics of placental abruption?-70% happen in low risk pregnancies
- 132RF for placental abruption?-previous placental abruption
-blunt trauma
-early pregnancy bleeding
-Pre-eclampsia
-Fetal Growth restriction
-malpresentation
-polyhydraminos
-increased maternal age >35
-low BMI
-IVF
-Infection
-premature rupture of membranes
-smoking
-drug misuse- *cocaine causes VC and increase in BP)
-maternal thrombolphilia - 133A theory for why placenta previa happens?Upper endometrium may not be well vascularised due to damage to this area. therefore the placenta implants in lower uterus. Damage may be from:
-previous C-section
-abortion
-uterine surgery
-multiparity - 134Types of placenta previa?1) complete- placenta completely covers cervical Os
2) Partial- placenta partially covers cervical os
3) Marginal- placanta egde extends to within 2cm of cervical os - 135When does placenta previa generally cause bleeding?from 20 weeks, when the lower uterine segment begins to grow and stretches the placenta
- 136What condition is placenta previa related to?Placenta Accreta- where the placenta grows into the myometrium wall
- 137What does placenta previa increase the risk of?-fetal hypoxia
-pre-term delivery
-ante-partum haemorrhage - 138What is happening physiologically in a placental abruption?There is a seperation between the uterine wall and the decidua basalis due to degeneration of the uterine arteries that supply blood to placenta (due to smoking/HTN)
- 139Types of placental abruption?1) partial
2) complete
**can be concealed (hidden pocket of blood behind the baby) or apparent (see vaginal bleeding) - 140Maternal complications of placental abruption?-Hypovolaemic shock
-Sheehan's syndrome (perinatal pituitary necrosis)
-renal failure
-DIC- decidualis basilis is rich in thrombolplastin which causes widespread clotthing - 141Fetal complications of placental abruption?-hypoxia and asphyxia
-premature birth - 142Types of forcep? Uses?Wrigley's (smaller and shorter)
- used in C-section
-used when babys head is very low and visible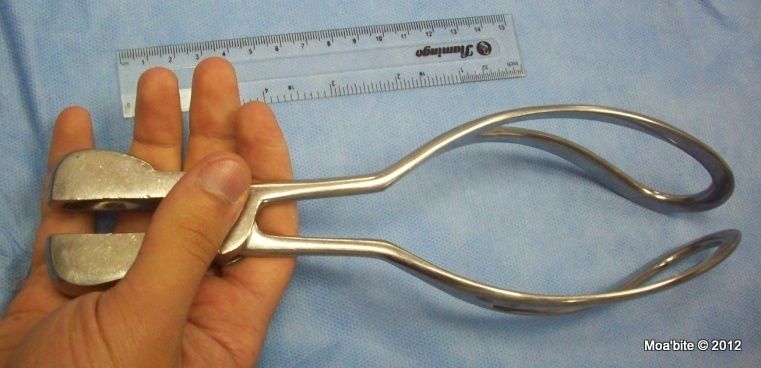
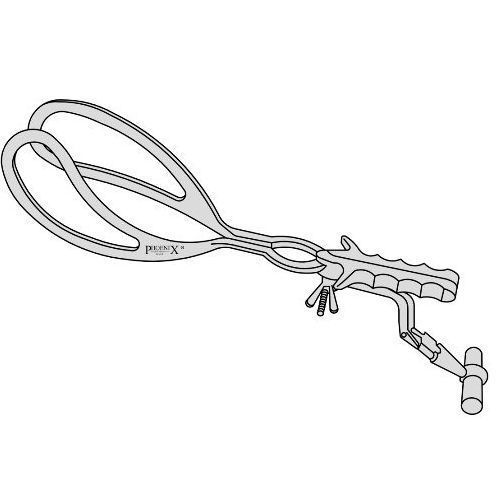
- 143What is a Neville Barnes forcep used for?If the baby’s had was looking down at the floor (direct OA – occipito-anterior position) or looking straight up (direct OP – occipito-posterior position) and the obstetrician does not want to rotate the baby’s head, and the baby is in mid/low cavity
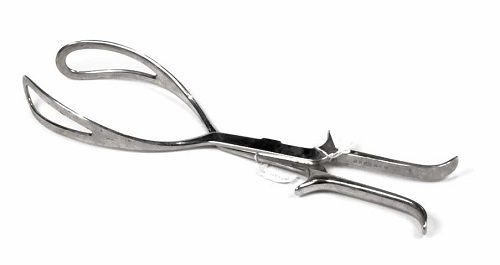
- 144When is Kiellands forceps used?ROTATES BABY- if the baby’s head is not a direct OA or OP.
- 145What is most common forcep that is used?Neville Barnes forcep
- 146Advantages of forceps?-faster than ventouse
-less cephalohaematoma
-less retinal haemorrhage
-can be used for face/breech
-can be used if <34 weeks
-less likely to fail - 147Risks of forceps?More maternal risk of tearing or lacerations and needing an episiotomy
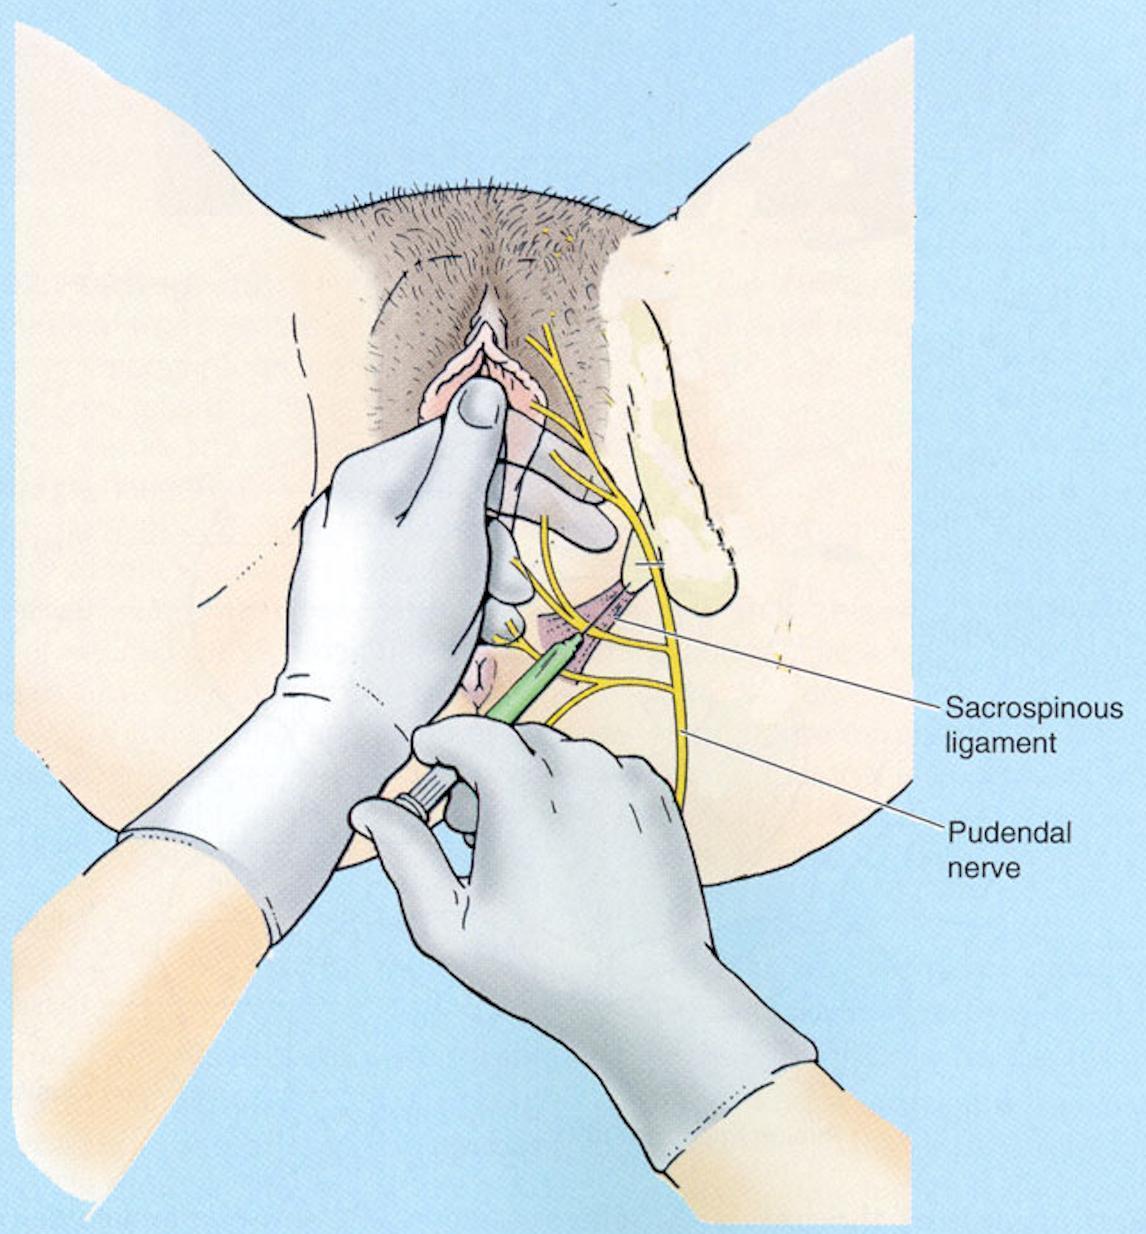
- 148Pain relief for an instrumental delivery?Pudendral nerve block (if head not past ischial spine already)
- 149Fetal complications with instrumental delivery?-bruising
-skin abrasions
-facial nerve palsy
-cephaloheamatoma
-retinal haemorrhage
-intracranial haemorrhage
-skull fracture - 150What is this?Kiwi Omnicup ventouse
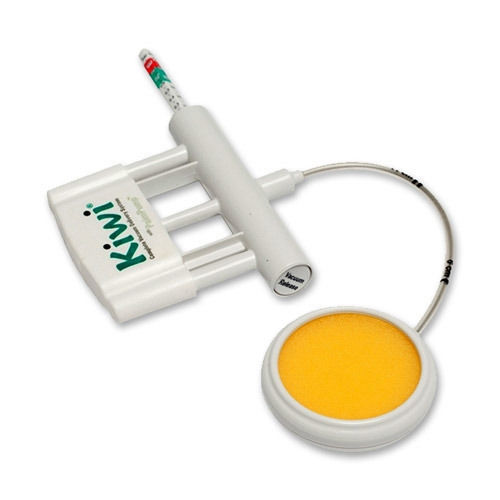
- 151What is this used for?Metal ventouse cup used if the baby is in the occipital posterior position and so head is up and need to get a ventouse on back on head to pull baby out

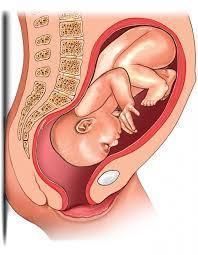
- 152Where is a ventouse cup ideally placed?Places anterior to the posterior fontanelle
- 153What must be done/given to patient before ventouse used?1) Local anasthetic into perineum
2) Bladder catheterised - 154Most common reasons for a delay in 2nd stage of labour?[POWER, PASSAGE, PASSENGER]
1) Insufficient maternal effort: due to exhaustion or because of an epidural
2) Malposition: baby may be in such a way that it physically cannot be pushed out e.g- OT or OP
3) Malpresentation- Brow/Face (1 in 1000) - 155What is OP and can a baby be delivered in this positon?Occipital-Posterior- where the back of the babies head is towards bum and the babys face is to pubes.
Babies in this postion can be delivered however the pelvis needs to be larger than normal or the baby needs to be smaller than normal. - 156—Right Occipital-posterior
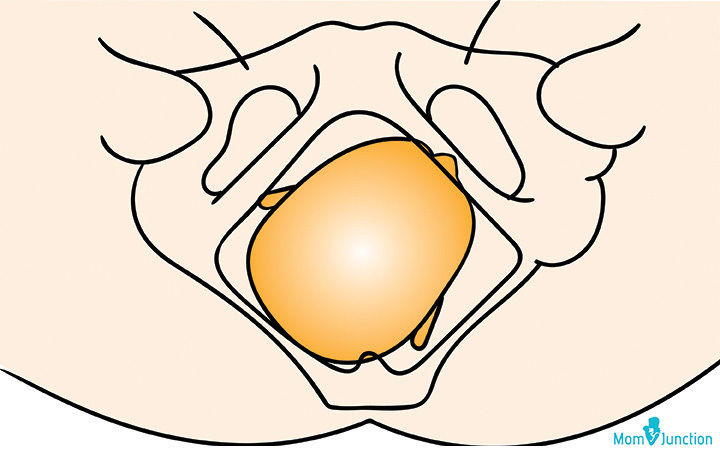
- 157Main fetal positions?1) Occipital-anterior (ideal)- face down back up
2) Occipital-transverse
3) Occipital-posterior- face to pubes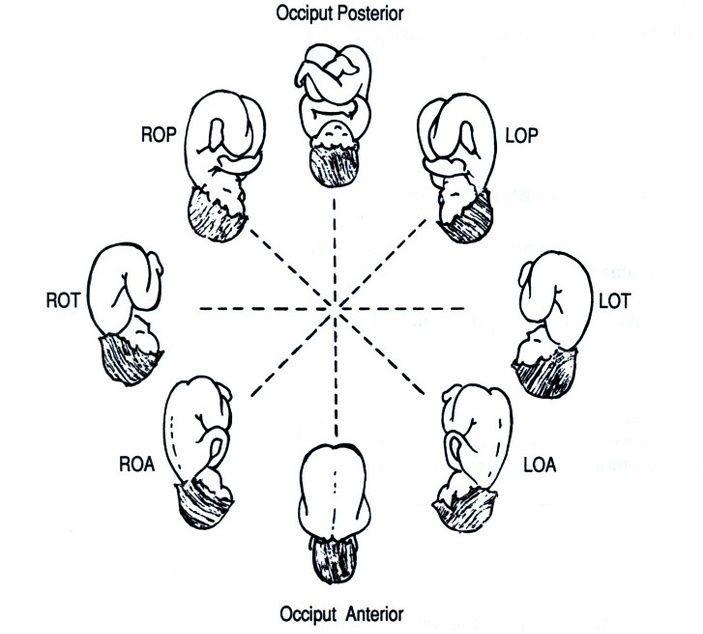
- 158What is deemed a normal length of time for second stage of labour in a nulliparous and multiparous woman?Nulliparious- within 3 hours. If >2 hours then diagnosed as 'delay'
Multiparous- within 2 hours. If >1 hour then deemed delay. - 159Normal length of active labour in a nulliparous woman?1st stage (dilating)- average 8 hours. Can be up to 18 hours but is unlikely.
2nd stage (pushing)- up to 3 hours active - 160Normal length of active labour in a multiparous woman?1st stage- 5 hours often. no more than 12 hours.
2nd stage- 2 hours (considered delay if >1) - 161What assessing when doing a vaginal examination in labour? (5)1) Dilatation
2) Position of cervix
3) Effacement of cervix- length
4) Fetal position
5) Fetal station- station 0 is when the head is at the ishial spines and is narrowest part of pelvis - 162When a baby is occipital-anterior- how large is the smallest diameter of the head to fit through the pelvic outlet?The suboccipitobregmatic diameteris 9.5cm which is the smallest diameter to fit through the pelvic outlet.
It is the diameter of the fetal head from the lowest posterior point of the occipital bone to the center of the anterior fontanelle. - 163When a baby is occipital posterior- what is the smallest diameter in which a head can fit through the pelvic outlet?11cm!
-reason why we like babies to be OA. - 164If a baby is presenting as 'brow' how big is the diameter of head to get through pelvis outlet?13cm- won't get through
- 165Advantages of ventouse over forceps?-Less analgesia
-Less perineal trauma
-Less vaginal trauma
-Less post delivery pain
-less force needed - 166Criteria for instrumental delivery?-consent
-anagesia
-cervix needs to be fully dilated
-head not palpable abdominally and below spines vaginally
-know presentation/positon
-bladder empty - 167Where is ventouse applied onto head?'Maximum fliction point'- 1.5cm anterior from posterior fontanelle
- 168At what rate does cervix dilate during active labour?1cm per hour
- 169C-section risks?-Bleeding
-Infection
-Damage to pelvic viscera
-Fetal laceration in 1%
-DVT/Thromboembolism - 170Mneumonic to looking at CTGs?DRCBRAVDO
DR- determine risk
C- contractions
BR- baseline rate
A- accelerations
V- variability- time between babies heart beats
D- decelerations
O- overal assessment - 171What is a classical C-section? When used?-Vertical incision on uterus, with either a transverse or vertical skin incision
*Rarely used, but when is due to: premature fetus, structural abnormality making lower segment not useful/formed*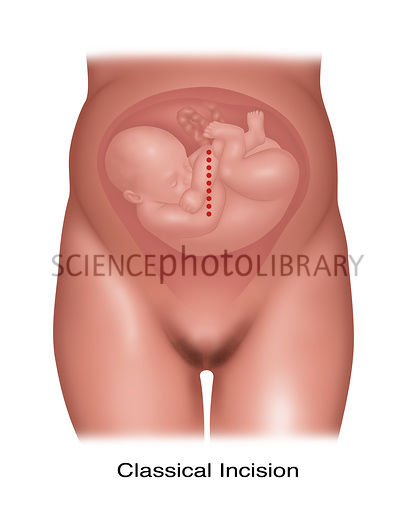
- 172Risks of classical C-section?adhesions more likely, infection, and CI to have VD following
- 173Categories of CS? What means?Determines the timing of the C-section
Cap1- Crash- immediate threat to life of woman or fetus and baby needs to be delivered in 30 mins (fetal brady, placent abruption)
Cap2- maternal or fetal compromise- 30-60mins (failure to progress)
Cap3- 'semi-elective'- (pre-eclampsia, failed induction of labour)
Cap4- elective. - 174When should elective C-sections be carried out?Always after 39 weeks- as risk of TTN (transient tachypnoea of newborn)
**if before 39 weeks then corticosteriods need to be givenfor fetal lung development** - 175What is most common C-section?Lower caesarean C-section-
'Cohen' straight incision 3cm above symphysis pubis. If transverse then reduced adhesion formation, less blood loss, lower risk of scar de-hiscence (uterine rupture)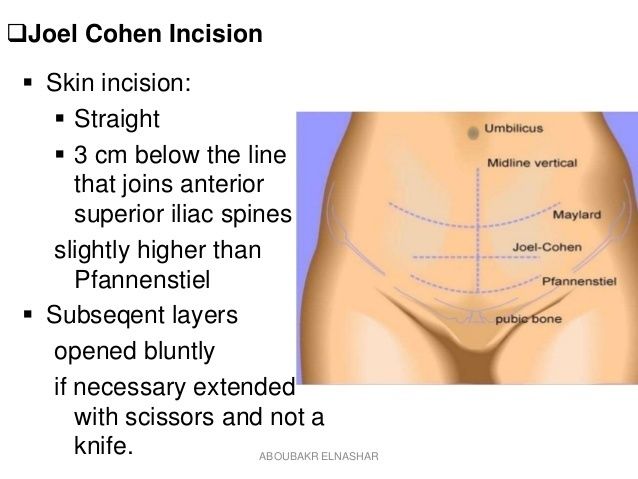
- 176Why can caffeine be used in pre-term infants?Used as a respiratory stimulant to prevent apnoeas of prematurity (>20secs of no breathing with desats and brady) and faciliate etubation.
- 177Is use of caffieine safe?(yes)
-It has a long half-life (>100 hrs)- so can be given once daily safely and has less toxicity -It has a wide therapeutic
to toxic ratio
(risks)
-tachycardia, agitation, tachpnoea, tremors, vomitting, worsens reflux - 178What dopplers can be used in addition to umbilical artery dopplers?Middle cerebral artery dopplers. They can be used to determine ratio of placental flow to MCA perfusion.
- 179Why do we worry if there is meconium stained liquor?As there is a risk that baby will inhale the meconium and and cause 'meconium aspiration syndrome'
- 180Risk factors for babies to release meconium in-utero?-Increasing gestational age
-fetal hypoxia - 181What are the risk that meconium aspiration?Meconium is a lung irritant and can result in both mechanical obstruction as well as chemical pneumonitis and predisposes to infection
- 182Intrapartum care if meconium stained liquor?1) There should be continuous electronic fetal monitrroing
2) If signs of fetal distress (brady, decelerations)- then need fetal blood sample and if ph <7.21 then emergency delivery needed
3) No suction prior to delivery - 183What is a cervical stitch (cervical cerclage) for and when put it?-Is a stitch in neck of uterus to prevent a woman going into pre-term labour
-Normally put in between 12 and 24 weeks of pregnancy and then removed at
36–37 weeks unless you go into labour before this. - 184What length cervix determines if a woman needs a cervical stitch or not?-if less than 25mm
- 185What procedure can be done to try and turn a breech baby?External cephalic version (ECV)
- 186What pain relief medication is given to women post C-section?Diclofenac in the bum
- 187What medication is given to all women having a C-section?-Ranitidine- prevents acid in stomach
-Prophalytic antibiotics - 188How does cell salvage work?Patients blood is suctioned and then is present in a container with heparin and saline- to then be processed before going back into womans body.
***Useful if woman is a Jehovahs witness*** - 189Define Pre-EclampsiaNew HTN presenting after 20 weeks gestation with significant proteinuria
- 190Define Eclampsia...Convulsive conditon associated with pre-eclampsia
- 191Define gestational hypertension...New HTN presenting after 20 weeks gestation without significant proteinuria
- 192What is chronic hypertension as related to pregnancy?HTN that is present before before 20 weeks of pregnancy OR if hypertensive medication is required prior to pregnancy
- 193Define HTN...Persistently raised BP (>140/90)
- 194Define severities of HTN in pregnancy (mild, moderate and severe)?1) Mild hypertension= 140/90- 149/99 mmHg
2) Moderate hypertension=150/100 to 159/109 mmHg
3) Severe hypertension= 160/110 mmHg or higher - 195What is HELLP syndrome?Haemolysis with elevated liver enzymes and low platelet count
- 196Symptoms of pre-eclampsia?1) severe headache
2) visual issues- 3) blurring/flashing/photophobia
4) Epigastric pain (liver)
5) Nausea/ vomitting
6) Odema (hands, feet, face - 197What % of pregnancies worldwide are complicated by HTN disorders?5-10%
- 198How many women with severe pre-eclampsia/eclampsia need admission to ITU?1 in 20 women
- 199Risk factors that make a woman at risk for developing pre-eclampsia?1) Chronic HTN or HTN during previous pregnancy
2) Diabetes
3) Chronic kidney disease
4) Autoimmune disease (lupus, anti-phospholipid)
5) First pregnancy
6) >40 yrs old
7) pregnancy interval >10 years
8) BMI >35
9) FMHX of pre-eclampsia
10) Multiple pregnancies - 200How to manage development of pre-eclampsia for a woman with risk factors?75mg of aspirin daily from 12 weeks until birth of baby
Information
- Description
- Notes from tutorial handouts in Taunton
- Created by
- Chloe Reynolds
- Views
- 86
- Tags
- Rating