
Mind map
Calcium (Ca++)
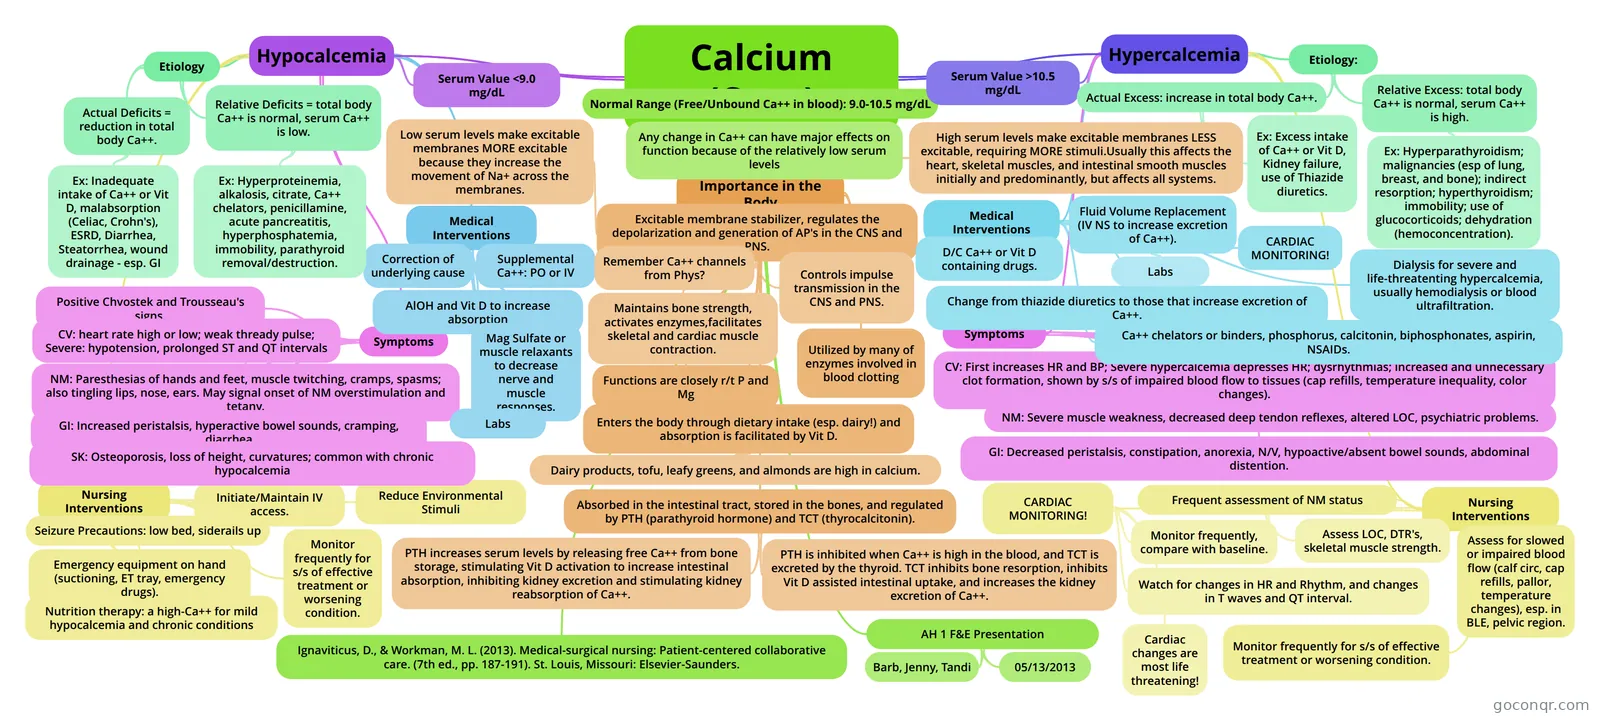
Mind map: Calcium Ca++
Map content
Calcium (Ca++)
Hypocalcemia
- Symptoms
- Positive Chvostek and Trousseau's signs.
- CV: heart rate high or low; weak thready pulse; Severe: hypotension, prolonged ST and QT intervals
- NM: Paresthesias of hands and feet, muscle twitching, cramps, spasms; also tingling lips, nose, ears. May signal onset of NM overstimulation and tetany.
- GI: Increased peristalsis, hyperactive bowel sounds, cramping, diarrhea
- SK: Osteoporosis, loss of height, curvatures; common with chronic hypocalcemia
- Medical Interventions
- Supplemental Ca++: PO or IV
- Correction of underlying cause
- AlOH and Vit D to increase absorption
- Mag Sulfate or muscle relaxants to decrease nerve and muscle responses.
- Labs
- Nursing Interventions
- Seizure Precautions: low bed, siderails up
- Nutrition therapy: a high-Ca++ for mild hypocalcemia and chronic conditions
- Reduce Environmental Stimuli
- Emergency equipment on hand (suctioning, ET tray, emergency drugs).
- Initiate/Maintain IV access.
- Monitor frequently for s/s of effective treatment or worsening condition.
- Serum Value <9.0 mg/dL
- Etiology
- Actual Deficits = reduction in total body Ca++.
- Ex: Inadequate intake of Ca++ or Vit D, malabsorption (Celiac, Crohn's), ESRD, Diarrhea, Steatorrhea, wound drainage - esp. GI
- Relative Deficits = total body Ca++ is normal, serum Ca++ is low.
- Ex: Hyperproteinemia, alkalosis, citrate, Ca++ chelators, penicillamine, acute pancreatitis, hyperphosphatemia, immobility, parathyroid removal/destruction.
- Actual Deficits = reduction in total body Ca++.
- Symptoms
Hypercalcemia
- Symptoms
- CV: First increases HR and BP; Severe hypercalcemia depresses HR; dysrhythmias; increased and unnecessary clot formation, shown by s/s of impaired blood flow to tissues (cap refills, temperature inequality, color changes).
- NM: Severe muscle weakness, decreased deep tendon reflexes, altered LOC, psychiatric problems.
- GI: Decreased peristalsis, constipation, anorexia, N/V, hypoactive/absent bowel sounds, abdominal distention.
- Medical Interventions
- D/C Ca++ or Vit D containing drugs.
- Fluid Volume Replacement (IV NS to increase excretion of Ca++).
- Labs
- Change from thiazide diuretics to those that increase excretion of Ca++.
- Ca++ chelators or binders, phosphorus, calcitonin, biphosphonates, aspirin, NSAIDs.
- CARDIAC MONITORING!
- Dialysis for severe and life-threatenting hypercalcemia, usually hemodialysis or blood ultrafiltration.
- Nursing Interventions
- CARDIAC MONITORING!
- Watch for changes in HR and Rhythm, and changes in T waves and QT interval.
- Monitor frequently, compare with baseline.
- Cardiac changes are most life threatening!
- Frequent assessment of NM status
- Assess LOC, DTR's, skeletal muscle strength.
- Assess for slowed or impaired blood flow (calf circ, cap refills, pallor, temperature changes), esp. in BLE, pelvic region.
- Monitor frequently for s/s of effective treatment or worsening condition.
- CARDIAC MONITORING!
- Serum Value >10.5 mg/dL
- Etiology:
- Actual Excess: increase in total body Ca++.
- Ex: Excess intake of Ca++ or Vit D, Kidney failure, use of Thiazide diuretics.
- Relative Excess: total body Ca++ is normal, serum Ca++ is high.
- Ex: Hyperparathyroidism; malignancies (esp of lung, breast, and bone); indirect resorption; hyperthyroidism; immobility; use of glucocorticoids; dehydration (hemoconcentration).
- Actual Excess: increase in total body Ca++.
- Symptoms
Normal Range (Free/Unbound Ca++ in blood): 9.0-10.5 mg/dL
- Any change in Ca++ can have major effects on function because of the relatively low serum levels
Importance in the Body
- Functions are closely r/t P and Mg
- Enters the body through dietary intake (esp. dairy!) and absorption is facilitated by Vit D.
- Dairy products, tofu, leafy greens, and almonds are high in calcium.
- Absorbed in the intestinal tract, stored in the bones, and regulated by PTH (parathyroid hormone) and TCT (thyrocalcitonin).
- PTH increases serum levels by releasing free Ca++ from bone storage, stimulating Vit D activation to increase intestinal absorption, inhibiting kidney excretion and stimulating kidney reabsorption of Ca++.
- PTH is inhibited when Ca++ is high in the blood, and TCT is excreted by the thyroid. TCT inhibits bone resorption, inhibits Vit D assisted intestinal uptake, and increases the kidney excretion of Ca++.
- Excitable membrane stabilizer, regulates the depolarization and generation of AP's in the CNS and PNS.
- Low serum levels make excitable membranes MORE excitable because they increase the movement of Na+ across the membranes.
- High serum levels make excitable membranes LESS excitable, requiring MORE stimuli.Usually this affects the heart, skeletal muscles, and intestinal smooth muscles initially and predominantly, but affects all systems.
- Maintains bone strength, activates enzymes,facilitates skeletal and cardiac muscle contraction.
- Controls impulse transmission in the CNS and PNS.
- Remember Ca++ channels from Phys?
- Utilized by many of enzymes involved in blood clotting
Ignaviticus, D., & Workman, M. L. (2013). Medical-surgical nursing: Patient-centered collaborative care. (7th ed., pp. 187-191). St. Louis, Missouri: Elsevier-Saunders.
AH 1 F&E Presentation
- Barb, Jenny, Tandi
- 05/13/2013
Information
- Description
- Mind Map on Calcium (Ca++), created by teej984 on 13/05/2013.
- Created by
- teej984
- Views
- 120
- Rating