
Flashcards
DI Exam 2

Flashcards do conjunto (124)
- 1What is professional writing?A writing is considered professional when a professional takes pen, pencil, word processor, or any other writing implement in hand to fulfill professional duties
- 2What is the purpose of professional writing?Purpose is to inform, instruct, persuade or entertain
- 3What are some examples of professional writing?Journal article
Review article
Book chapters
P&T drug evaluation
Policy and procedures for institutions
Final evaluation
Slide or poster presentation
Letter of recommendation
Documentation in patient chart - 4What are the advantages of professional writing?Promotion (Annual evaluation tool)
Scholarship in academia
Share ideas, knowledge, and best practices
Gratification and satisfaction
Recognition in the field - 5What are some disadvantages of professional writing?Time investment (Practice and revisions)
Criticism (Possible rejection)
Pay to publish - 6What are the 8 steps of writing?
- 7What are some simple rules?Know your purpose
Organize your thoughts
Put yourselves in readers position
Use words correctly and carefully
Edit/revise your work - 81. Purpose

- 92. Authorship

- 103. Know Your Audience

- 114. Writing Style
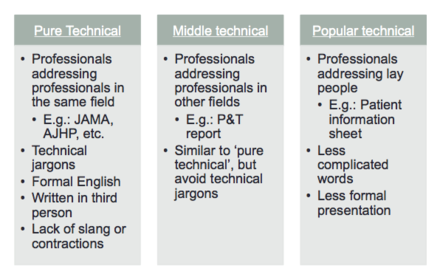
- 12Writing style continued

- 134a. Writing a Document

- 144a. Writing a Document- Introduction

- 154a. Writing a Document- Body

- 164a. Writing a Document - Conclusion

- 17General Rules of Writing

- 18General Rules of Writing – continued

- 19Specific Rules of Writing

- 20Specific Rules of Writing - continued

- 21Specific Rules of Writing - continued

- 22Specific Rules of Writing - continued

- 23What is plagarism?

- 24What are the two types of plagarism?

- 25What are some disciplinary actions for plagarising?Warning
Probation
Suspension
Dismissal - 26How can you Avoid Plagiarism?

- 27Copyright and Fair Use

- 28How to Avoid Copyright Violations

- 29References/Citation

- 30Citing a Journal Article

- 31Citing a Journal Article - continued

- 32Next Steps5. Submission to a journal
6. Peer review
7. Revision
8. Galley proofs - 33Newsletter

- 34Presentation

- 35Platform Presentation

- 36Platform Presentation - continued

- 37Platform Presentation - continued

- 38Poster Presentation

- 39Drug Information Response

- 40In conclusion…Keep the general and specific writing rules in mind
Adhere to publisher’s guidelines
Provide proper citation to avoid copyright infringements or plagiarism - 41What are the steps to a DI question?
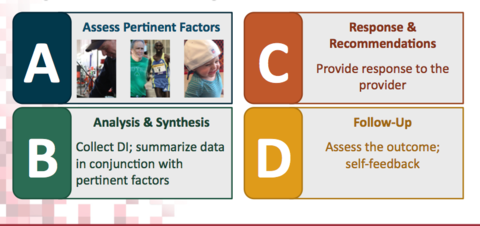
- 42Other Pertinent Factors

- 43Analysis and Synthesis

- 44Key characteristics of a responseTimely (based on acuity and expectations)
Concise yet complete
Evidence-based
Objective, balanced, unbiased - 45How could a DI response NOT be evidence-based or objective?You use your own clinical experience. “Im a cardiologist, I always see patients with hypertension… etc” But if there is evidence available, you should be relying on that
- 46General format for a response

- 47Follow-Up

- 48What is important during the call with the health care professional?Patient-specific information DURING THE CALL/REQUEST is
important for a professional, timely response - 49Key features of an effective DI response

- 50Key features of an effective DI response

- 51Key features of an effective DI response

- 52Step-wise approach for providing a drug information response

- 531. Restating the question

- 542. Brief summary of findings

- 553. In-depth review

- 56Written versus Verbal response

- 57Written response – best practices

- 58Verbal response - best practices

- 594. Offer additional assistance

- 605. Follow-up

- 61Formulary & Formulary System

- 62What and where are formularies?According to ASHP, the formulary listing is only a part of the picture. The formulary also includes the Med use policies that guide practice as well as the decision-support, and drug guidelines that are available in a health-system
When we talk about the formulary system, here we’re referring to the PROCESS in which the healthcare organization through MD, RPH and other health care professionals establishes the P&P regarding drugs tx and products. And therapies and identified drug products and therapies that are most medically appropriate and cost-effective to best serve the health interests of a given population.
Where are they: hospitals, acute care, Government, Medicare and Medicaid, VA, Insurance, and Managed Care. –for purposes of this talk, we’ll focus on the hospital - 63Formulary Systems: Where do you find them?Hospitals
Medicare/Medicaid
Pharmacy Benefit Managers (PBM)
Managed care - 64Open versus Closed Formularies

- 65What is an example of an open vs closed formulary?AN example, say a patient is admitted on a non-formulary med. While there would be other meds in the same class, it may be best to allow the NF product rather than adding another complicating factor to the hospital’s treatment.
- 66Pharmacy & Therapeutics Committee

- 67Pharmacy & Therapeutics Committee Structure
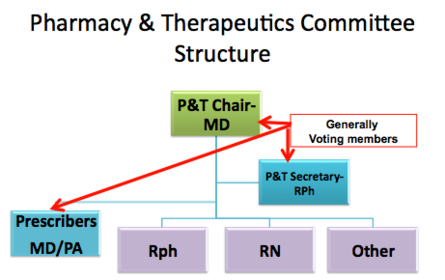
- 68P&T Committee is made of _____.P&T Committee is made of reps of medical staff, administration, pharmacy, nursing, medical records, risk management, quality assurance, risk management, and any professions medications include (anesthesia, dietary-food & nutrition, surgery etc).
- 69Organizational Structure of P&T in Hospitals
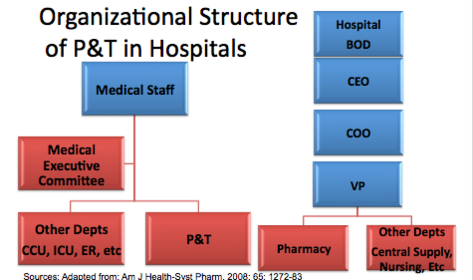
- 70P&T Adhoc Committees

- 71P&T - Conflict of Interest

- 72Pharmacist’s role on P&T

- 73P&T Functions

- 74What do P&T functions include?P&T functions include- determining which drugs are available (the formulary)
And any drug-related P&P including: who can prescribe specific drugs, how non-formulary drugs are handled, development of ordersets and drug guidelines.
And a big focus of P&T is quality assurance- specifically the focus is on patient outcomes and not solely on cost. - 75P&T Formulary Management
- 76So How are medications requested and reviewed for addition/deletion from the formulary?This process need to be structured.
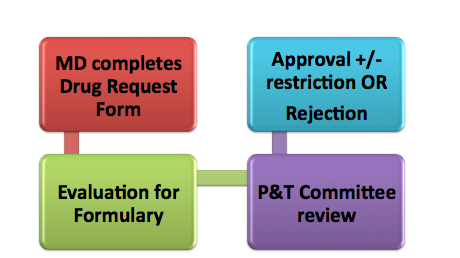
Physician generally contacts the RPh to see if they can get a drug on formulary and there is a form that they must complete. I’ll show you what needs to be included in the next slide. The evaluation of the drug for formulary involves many aspects which we’ll review and ultimately, the eval goes to the P&T for review. The P&T review at committee generally involves a pharmacist presenting some part of the drug request. Some ask the physician to presents the request in conjunction with the pharmacist.
Once the drug is reviewed at the committee, it is either approved (either with restriction or a drug-guideline) or it is rejected. - 77Formulary Management: Additions Drug Request Form
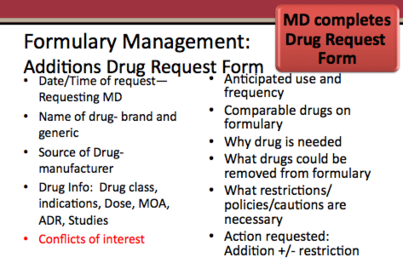
- 78What are items that are generally found on a request for formulary addition?Date and/time—this is included because behind the scenes, there’s a great deal of work that goes on even to be considered. --most hospitals restrict drug requests to come ONLY from the MD.
Name of drug: brand and generic
Drug Info: Dosage Forms and Strength, Therapeutic Class, Principal Indications:
Anticipated Use: Population, pediatrics, geriatrics, or specific
Please indicate the approximate number of patients per month that will be treated with this drug
Please indicate patient population the drug would be used in:
Neonatal Pediatric Adolescent Adult Geriatric
Why it’s needed: What are the significant benefits/advantages (including cost) of the requested drug compared with the comparable products/procedures listed above?
Formulary changes: List any drugs, therapies, or procedures currently available on the Formulary that are comparable or similar to the requested drug.
If the requested drug(s) were approved for addition to the formulary, which current formulary agent(s) would decrease in hospital. - 79Formulary Management Types of P&T Drug Reviews
- 80P&T Drug Reviews: New Drug Monographs

- 81P&T Drug Review: Financial Analysis
- 82P&T Drug Review: Safety

- 83Institute for Safe Medication Practices (ISMP) ismp.org

- 84P&T Drug Review Safety: FMEA
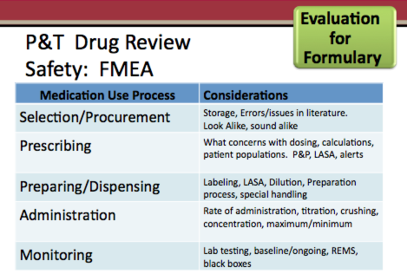
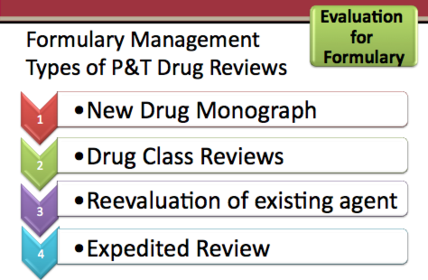
- 85P&T Drug Review: Drug Class ReviewsJoint Commission: All formulary medications are to be reviewed at least annually.
Includes ALL agents (formulary/non-formulary)
May lead to removal, guidelines or drug restrictions
May lead to removal of redundant agents, or restrictions or guideline additions. - 86Drug Re-evaluation & Expedited Review: In most cases, this might be that the drug is just newly released in a new dosage form (say different strength capsule/tablet). But in some cases there could be new information that is released that warrants the drug being looked at. (this might be that it has a new black box, or that it has a specific indication that was newly studied or in some cases, there may be cost data that is relevent.

- 87Managing Medication Use StrategiesGeneric Drugs
Non-formulary drug request
Therapeutic Interchange
Guided-Use
Guidelines
MUE - 88Generic DrugsGeneric Substitution
FDA bioequivalent products
Doesn’t require P&T approval if FDA approved
However in some states law, or local P&P may prohibit substitution (e.g. narrow therapeutic index-anticoagulants, anticonvulsants)
P&P must allow: MD to opt-out if clinically justified - 89Non-Formulary Requests

- 90Therapeutic Interchange

- 91Therapeutic Interchange: Common ExamplesH2 Antagonists: famotidine-ranitidine-cimetidine
Proton Pump Inhibitors: omeprazole-esomeprazole
Statins: simvastatin-lovastatin-rosuvastatin
Quinolones: ciprofloxacin-moxifloxacin-levofloxacin
IV to PO - 92Guided Use Examples: Drug Approval + Restriction

- 93Drug Approval and RestrictionPatients need to meet a specific criteria before you dispense the drug. (there needs to be a process in case the patient doesn’t meet the criteria but is still medically necessary). This is also a strategy when drugs are on shortage. An example of this is a drug Vaprisol or Conivaptan (that is very costly and is used for hyponatremia)
Some drugs must be approved by a specific service or those with specific training before you dispense it. This is the case when the drug poses a serious threat if not used correctly (Xigris- an agent used for sepsis, for example must receive the ID attending’s approval before being dispensed. OR a specific chemo agent that can only be prescribed by an oncologist.
Limiting to specific areas. This may be because the drug needs specific equipment to be used. Like a neuromuscular blocker in an ICU setting.
Approval of a medical director. –this might be for very high cost agents when you see that there’s very little role but the MD wants to use the drug non-formulary - 94Clinical Practice GuidelinesEvidence-Based
Decrease variability in practice
Reduce costs
Improve patient outcomes
Examples: Anticoagulation use-heparin, Renal dosing, Aminoglycosides
Clinical practice guidelines are another tool in managing medication use that can ensure medications are used appropriately. - 95Order Set Development

- 96Order SetP&T responsible for overseeing all medication-related use
Reducing variability, chance for error, and cost.
May contain non-formularies if they are not updated
Should be reviewed on a periodic basis (annually) to ensure they keep up with practice, P&P and the formulary - 97Medication Use Evaluation (MUE)Evidence-based
Focus: Quality Improvement
Any part of medication use process (Problem-prone high-risk, high-cost medications)
Paper/EMR
Accreditation
MUE, is a way to systematically review a medication in the organization again with evidence based criteria.
Although some have referred to these as Drug use evals, or reviews, they are all systematic, and using a quality improvement approach.
Can be as simple a finding out what common doses are used of an specific drug to a complex look at the specific prescribing protocol.
Joint Commission requires MUE as a component of the medication management system
ASHP guidelines dictate how this is conducted. - 98Example MUE

- 99P&T Medication Policies and ProceduresAs needed PRN medications
Automatic stop/resume medications
Patient’s Own Medications
Self-administered medications
Medication-related devices (pumps)
Drug Samples
Investigational medications
Discharge medications - 100Drug Shortages
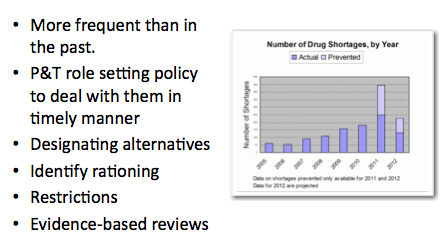
- 101P&T EducationInservices
Grand rounds
Pharmacist ->MD education during prescribing/dispensing
Staff meetings
Email
Newsletters
Mailings
Prescriber detailing
Pharmacy/Hospital websites - 102What is a medication error?

- 103Adverse Drug Event (ADE)

- 104Adverse Drug Reaction (ADR)

- 105ASHP Definition of an ADR

- 106ME, ADE and ADR

- 107Incidence and Mortality10-20% of hospitalized experience an ADR
20% of ambulatory patients experience an ADR
ADRs accounts for 5-10% of hospital admissions
ADRs cause between 40,000 and 100,000 deaths/year
About 50% of ADRs are considered preventable! - 108Impact of ADRsPatients lose confidence in health care practitioners
Patients may refuse to try other treatment options based on previous experience
Patients may seek self-care which can result in further ADRs
Annual cost estimated to be 5-7 billion dollars/year - 109Pharmacovigilance

- 110Post-Marketing ADR Example

- 111Classification of ADRs
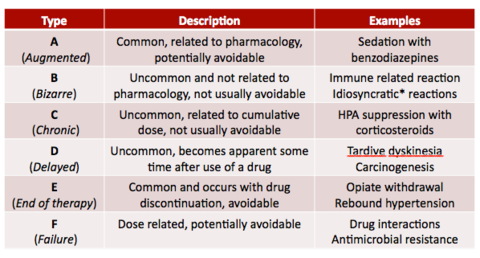
- 112Severity of ADRs
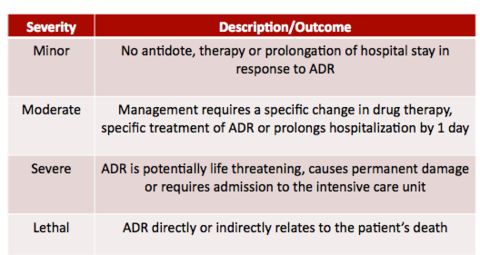
- 113Identifying ADRs

- 114ADR Indicator Drugs
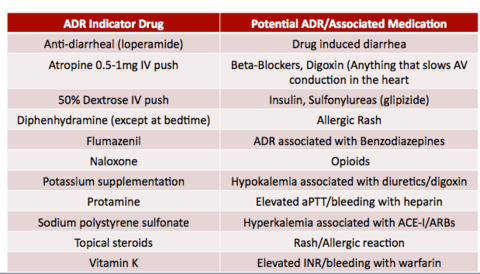
- 115Causality and Probability

- 116Assessing Probability/Causality

- 117Assessing Probability/Causality

- 118Naranjo Probability Scale
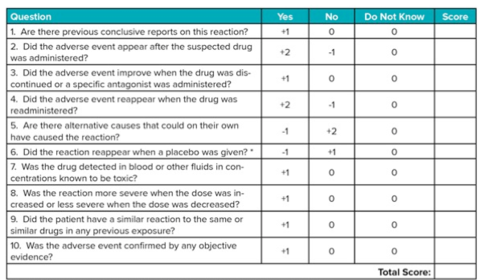
- 119Naranjo Probability Scale (cont)
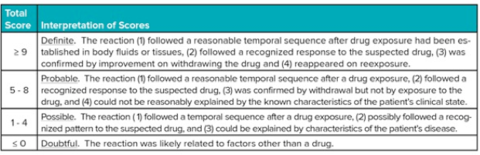
- 120At-Risk Populations

- 121MedWatch and FAERS

- 122Additional Resources

- 123Preventing ADRs

- 124Summary

Informações
- Descrição
- Pharmacy FlashCards sobre DI Exam 2 , criado por Lauren Pattah em 12-10-2016.
- Criado por
- Lauren Pattah
- Visualizações
- 2
- Avaliação