
Flashcards
Acute Loss of Vision

Flashcards do conjunto (29)
- 1Key questions in history of acute loss of visionHeadache - giant cell arteritis
Eye movements hurt - optic neuritis
Lights or flashes preceding visual loss - retinal detachment
Like a curtain descending - retinal artery occlusion/giant cell arteritis - 2What are the the two types of retinal vein occlusion and what is it associated with? What kind of visual loss does it give?Central and branch retinal vein occlusion (CRVO and BRVO)
Associations: age, diabetes, HTN, smoking, obesity, raised IOP, polycythaemia
Unilateral visual loss - 3Non-ischaemic CRVO75% of CRVO
Variable VA
Dilated, tortuous retinal veins
Widespread haemorrhages
Good prognosis
Progression to ischaemic in ~30% - 4Ischaemic CRVOSudden severe visual loss and more severe retinal signs
Causes: glaucoma, polycythaemia, HTN
Macular oedema
Widespread cotton wool spots
Deep haemorrhages
Marked RAPD - 5Complications of ischaemic CRVOPermanent visual loss
Neo-vascularisation (VEGF):
- Risk of vitreous haemorrhage
- Rubeotic glaucoma (new vessels on iris, blocking aqueous drainage)
- Treat with pan-retinal photocoagulation
and anti-VEGF agents - 6BRVO and its presentation3x more common than CRVO
Not an emergency (eg. OP appointment)
Presentation:
- Reduced VA (often central, worse on waking)
- Visual field defects (often altitudinal) - 7What is seen on fundoscopy with BRVO?Findings restricted to area drained by affected vein
Haemorrhage
Cotton wool spots
Venous dilatation
Oedema - 8Central renal artery occlusion: PresentationSudden unilateral severe decrease in VA (usually counting fingers or worse)
May be complete loss of light perception
RAPD (relative afferent pupillary defect)
Cherry red spot on pale retina
Intermittent prodrome phase common - 9What is seen on fundoscopy with CRAO?Pale retina (oedema)
Cherry red spot (fovea contains photoreceptors only, supplied by choroid - for 6 weeks)
Possible signs of hypertensive retinopathy - 10Management of CRAOOcular massage, rebreathing into paper bag > hypercapnia and vasodilatation -> may dislodge embolus
Acetazolamide, paracentesis (aspiration of aqeous from anterior chamber) - to lower IOP - 11What is Temporal Arteritis/Giant Cell Arteritis?Causes AION
Immune-mediated vasculitis of medium and large vessels
Overlaps with polymyalgia rheumatica (PMR) - 12Clinical features of temporal arteritisTypically patient > 60 years old
Usually rapid onset (e.g. < 1 month)
Headache (found in 85%)
Jaw claudication (65%)
Visual disturbances secondary to anterior ischemic optic neuropathy
Tender, palpable temporal artery
Features of PMR: aching, morning stiffness in proximal limb muscles (not weakness)
Also lethargy, depression, low-grade fever, anorexia, night sweat - 13Management of temporal arteritisHigh-dose prednisolone - there should be a dramatic response, if not the diagnosis should be reconsidered
- 14What is Anterior Ischaemic Optic Neuropathy and how does it present?Compromise of blood supply of optic nerve (posterior ciliary artery)
Jaw claudication, tender scalp, temporal headache, abnormal temporal artery, decreased VA, RAPD, diplopia, optic disc swelling/atrophy - 15Investigations and management for AIONInvestigations:
- CRP/ESR raised
- Temporal artery biopsy (but high false -ve due to skip lesions)
Management:
- Oral prednisolone
- May take >1 year to settle - 16Posterior vitreous detachmentDegenerative changes in vitreous (liquefaction) leads to detachment from posterior retina
Occurs earlier in myopia, trauma, inflammation, connective tissue disease
Usually benign, leads to increased numbers of floaters - 17What are the complications of posterior vitreous detachment?Vitreous haemorrhage
Retinal tear
Retinal detachment - 18Retinal detachment: what can cause it, what are they more common in and where do they happen more rapidly?Causes: Vitreous detachment and retinal tear, trauma, surgery
More common in myopes
Detaches more rapidly in superior retina - 19How does retinal detachment present?4 F's: Floaters, Flashes, Field loss, Fall in acuity (if macula involvement)
Abnormal red reflex
Grey, ballooning retina - 20Management of retinal tears and detachmentTreat larger retinal tears with laser photocoagulation
Surgical intervention for detachment - 21Optic neuritisOptic disc swelling
Unilateral decrease in visual acuity over hours or days
Blurring of vision (blind spot enlargement/paracentral scotoma)
RAPD
Red desaturation
Retrobulbar aching
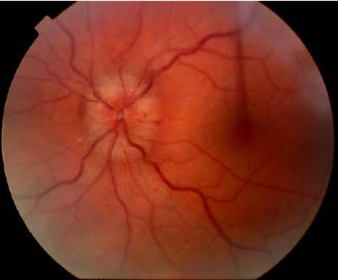
Eye movements painful - 22PapilloedemaBilateral disc swelling due to increased ICP
Headache
Transient blurring of vision, enlarged blind spots
May be splinter haemorrhages, exudates, cotton wool spots if severe
Eventual atrophy - 23Causes of papilloedemaSpace-occupying lesion: neoplastic or vascular
Malignant hypertension
Idiopathic intracranial hypertension
Hydrocephalus
Hypercapnia
Rare: hypoparathyroidism and hypocalcaemia, vitamin A toxicity - 24Optic atrophyDisc pallor from loss of axons, glial proliferation and decreased vascularity
May occur without optic disc swelling, or following optic disc swelling - 25Causes of optic atrophyPapilloedema, optic neuritis, ischaemic optic neuropathy, POAG, optic nerve compression
Retinal V/A occlusion
Retinitis pigmentosa - 26Most common causes of sudden painless loss of visionIschaemic optic neuropathy (e.g. temporal arteritis or atherosclerosis)
Occlusion of central retinal vein
Occlusion of central retinal artery
Vitreous haemorrhage
Retinal detachment - 27Differentiating posterior vitreous detachment, retinal detachment and vitreous haemorrhage
- 28What does this show?Retinal detachment
Features:
- Dense shadow that starts peripherally progresses towards the central vision
- A veil or curtain over the field of vision
- Straight lines appear curved
- Central visual loss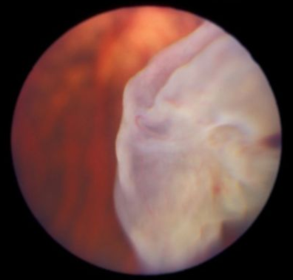
- 29What does this show?Papilloedema
Informações
- Descrição
- Specials (Opthalmology) FlashCards sobre Acute Loss of Vision, criado por Liam Musselbrook em 17-12-2016.
- Criado por
- Liam Musselbrook · dez 2016
- Atualizado
- 29 mar 2017
- Visualizações
- 28
- Tags
- Avaliação