
Flashcards
Macrolides

Flashcards do conjunto (55)
- 1spriomycin
- 2Erythromycin
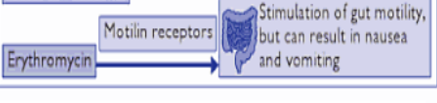
- 3classification of macrolidesolder: Erythromycin
Newer/ 2nd -Generation (semi-synthetic) : Roxithromycin, Clarithromycin & Azithromycin
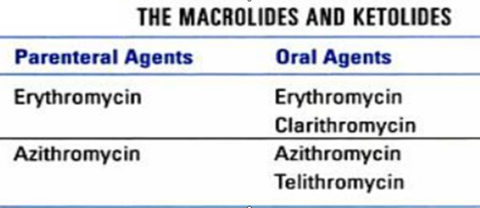
Newest one: (Ketolide) Teilthromycin - 4route of administration
- 5MOA: reversibly inhibit 50S subunit of bacterial ribosome by “dual MOA”1-Translocation movement of aminoacyl t-RNA from A-site to P-site on the mRNA
2-Transpeptidation by inhibiting peptide-transferase enzyme - 6Macrolide, Chloramphenicol, Clindamycin may competitively inhibit each other activityChloramphenicol &Clindamycin have the similar MOA & have closely related binding-site on the 50S ribosome
combination should be avoided - 7Cidal/ Static:usually -Static
- 8Pharmacokinetics of Macrolides:
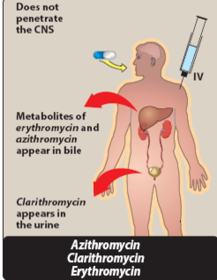
- 9Absorption: Erythromycinorally is destroyed by gastric acid (acid-labile/acid-sensitive)
It is activity is ↑ at the alkaline PH - 10Erythromycin is given as:→Enteric-coated tablets
→ Add acid-stable salts
Erythromycin
(-stearate / -ethylsuccinate /-estolate) conjugates - 11The best absorption is obtained withErythromycin-estolate salt
- 12absorption Azithromycin, Roxithromycin ,Clarithromycin &Telithromycinare stable to gastric acid (acid-stable) & rapidly absorbed
Food affects their absorption - 13Distributionwidely distributed to most body fluids & body tissues.
CSF penetration is poor even when meninges are inflamed - 14Azithromycin > Clarithromycin → has unique pharmacokinetic propertiesphagocytosed by macrophage→ travel to sites of infection → can enhance intracellular phagocyte killing of bacteria
- 15Azithromycin is taken up extensively in high amounts by “tissues”much greater concentration of the drug in the tissues as compared to its serum concentration
Azithromycin → is slowly released from tissues over subsequent days (tissue half-life ~ 2–4 days) & has a prolonged T1/2 - 16unique properties of azithromycin permit once-daily dosing & shortening of the duration of treatment in many cases how??3-5 day course of Azithromycin oral therapy may be adequate for most infections, instead of 7–10 days with other drugs
- 17Metabolism & Excretion MacrolidesMainly metabolized in the liver & excreted through bile
dose adjustment is not needed in renal failure
Except → Clarithromycin needs to be adjusted - 18Advantages of newer 2nd -Generation macrolides Azithromycin-More acid-stablegood oral absorption)
-Longer duration of action
-Less frequent administration/once-a-day administration (better compliance)
-Low side effect profile:
+Less GI side effects (better tolerated)
+Less effect on hepatic drug metabolizing enzymes→ less drug-drug interactions - 19(Azithromycin has no effect on hepatic metabolizing enzyme)less drug-drug interactions
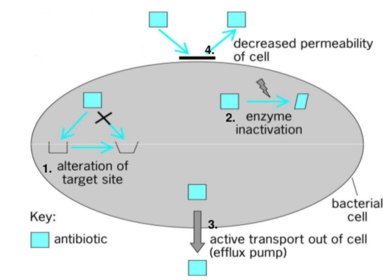
- 20Resistance is becoming increasingly common& occurs by one of several mechanisms1- Mutation that alter a 50S ribosomal binding-site
2- ↓Bacterial uptake of Macrolide→↓ Macrolide accumulation mediated by active efflux pump
3- Enzymatic inactivation of the Macrolides - 21Efflux & methylase production are the most important resistance mechanisms inGram+Ve organisms]
- 22Resistance Macrolides
- 23- Complete cross-resistance between Erythromycin & the other MacrolidesBacteria that have developed resistance to Erythromycin are usually resistant to the newer Macrolides
- 24Partial cross-resistanceresistance to structurally unrelated Macrolides such as Clindamycin & StreptograminB →which share the same ribosomal binding site
- 25Antibacterial spectrum of activity of Telithromycin,Clarithromycin & Azithromycin1- effective against aerobic Gram+ve organisms
Gram+ve cocci: Streptococcus > Staph.aureus
Gram +ve bacilli: C.diphtheriae, B.anthracis - 26Antibacterial spectrum of activity of Telithromycin,Clarithromycin & Azithromycin2- Atypical bacteria:As → Chlamydia, Mycoplasma, Rickettisae
3-few Gram -ve organisms: - 27Some/few Gram -ve organismsGram-ve cocci: as Moraxella catarrhalis
Gram-ve bacilli: as → H.influenzae, B.pertussis ,
& Campylobacter jejuni causes → Traveler’s diarrhea treated by → Azithromycin
H.Pylori causes →GI ulcer treated by→ Clarithromycin - 28Ketolides: As Telithromycin orally-effective against many Macrolide
-resistant Gram+ve organisms
-it binds to 2 sites of contact instead of one on the 50S ribosome
-poor substrate for bacterial efflux pumps - 29Telithromycin is active against manystrains of Strepto. pneumoniae, Strepto. pyogenes &Staph.aureus that are resistant to Macrolides
- 30Teilthromycin is limited bysevere hepatotoxicity
- 31antimicrobial spectrum of Teilthromycin

- 32Therapeutic uses of ErythromycinMLCDPSS (mnemonics)
- 33Therapeutic uses of AzithromycinMLCDPSS + MAC + LGV + H.influenzae
- 34Therapeutic uses of ClarithromycinMLCDPSS + MAC + M. leprae
+ H.pylori - 35Therapeutic uses of Macrolide

- 36Older-generation (Erythromycin)-has a similar spectrum of activity to PenicillinG
-alternative drug to treat Penicillin-sensitive infections in Penicillin-allergic patients - 37MLCDPSSMycoplasma pneumoniae
Legionnaire’s pneumonia
Chlamydia pneumoniae
Diphtheria
Pertussis
Staphylococcal & Streptococcal infections
Syphilis - 38Mycoplasma pneumoniae

- 39Legionnaire’s pneumoniaAzithromycin is the DOC
- 40Chlamydia pneumoniae

- 41: Macrolides in Chlamydia pneumoniaepreferred for
1- initial uncomplicated Chlamydial
infections
2-for Chlamydial infections in children & pregnant women - 42Tetracyclines in Chlamydia pneumoniaepreferred for recurrent infections
- 43Diphtheria Macrolide (Erythromycin) is very effective for eliminating the carrier state

- 44Pertussis (Whooping cough) caused by Bordetella pertussisMacrolides (Erythromycin) is most effective treatment as well as for prophylaxis of close contacts
- 45“alternative” in patient who are allergic to PenicillinG-Staphylococcal infections in mild cases
(but not MRSA strains)
-Streptococcal infections:→ URTIs
- Syphilis caused by Trepenoma pallidum - 46Macrolides good for!!!1-Atypical bacterial infection -- Upper & lower RTI Atypical-CAP
2-Traveler’s diarrhea (Azithromycin)
3- Clarithromycin is a key component in the treatment of H. pylori
4-Atypical mycobacterial infections - 47URTIs
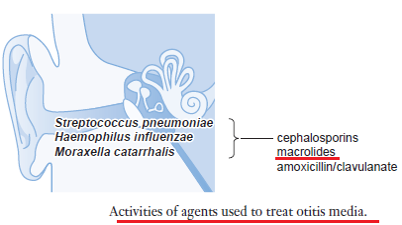
- 48TX of H. influenza
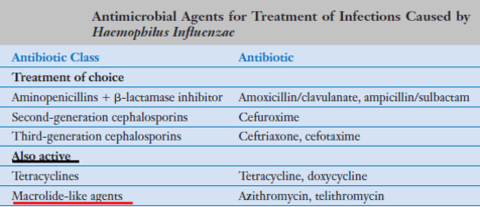
- 49TX of M. catarehalis
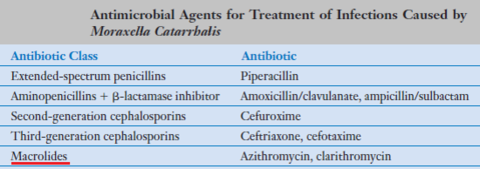
- 50Empiric Tx Acute otitis media
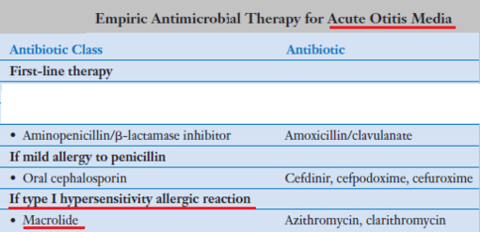
- 51Empiric Tx CAP
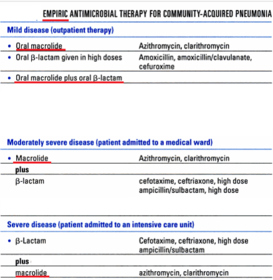
- 52Q- A 54- year-old man with no significant past medical history who presents with CAP of mild-moderate severity. He is probably allergic to Penicillin
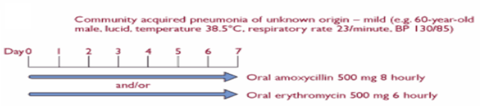
- 53A 27-year-old pregnant patient with a history of pyelonephritis has developed a severe upper respiratory infection that appears to be due to a bacterial pathogen. The woman is hospitalized. Which Macrolide is to be selected for treatment!ddd
- 54Antimicrobial drugs that are eliminated via hepatic metabolism or biliary excretion includeerythromycin, cefoperazone,
clindamycin, doxycycline, isoniazid, ketoconazole, and nafcillin - 55pseudomembranous colitis has been associated with the use of many agents including ؟؟ampicillin and clindamycin