
Flashcards
Alimentary System: Gall Stones, Cholecystitis, Ascending Cholangitis
Flashcards do conjunto (14)
- 1Give a DDx fo RUQ P.* Acute cholecystitis
* Duodenal ulcer
* Hepatitis
* Congestive hepatomegaly
* Pyelonephritis
Appendicitis
* Pneumonia
OHOCM p609. - 2Bile contains c......, b..... p..... (from broken down Hb), and p..... If the concentrations vary, different stones may form.Bile contains *cholesterol, bile pigments* (from broken down Hb), and *phospholipids* If the concentrations vary, different stones may form.
OHOCM p636. - 3What are the different types of stones that may form and some risk factors?* Pigment stones:
(<10%) Small, friable & irregular. Causes: haemolysis.
* Cholesterol stones:
Large, often solitary. Causes: ♀, age, obesity (Admirand’s triangle: ↑risk of stone if ↓lecithin, ↓bile salts, ↑cholesterol).
* Mixed stones:
Faceted (calcium salts, pigment, & cholesterol).
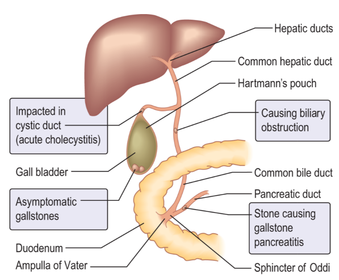
OHOCM p636. - 4Describe the anatomical positions required for stones to cause acute cholecystitis, biliary obstruction, gallstone pancreatitis, and asymptomatic gallstones.
- 5What are some complications of gallstones?In the gallbladder & cystic duct:
• Biliary colic
• Acute and chronic cholecystitis
• Mucocoele
• Empyema
• Carcinoma
• Mirizzi’s syndrome (stone in the GB presses on the bile duct causing jaundice)
In the bile ducts:
• Obstructive jaundice
• Cholangitis
• Pancreatitis
In the gut:
• Gallstone ileus
OHOCM p637. - 6What is biliary colic?Symptomatic gallstones temporarily obstructing the cystic duct or common bile duct.
K & C p352. - 7S & Sx of biliary colic.* P may be severe but constant with a 'crescendo' characteristic
* P may be epigastric, RUQ +/- radiation to R shoulder
* Sx often follow heavy meal
* N & V frequent
K & C p352. - 8What is acute cholecystitis and what complications may it cause?* Obstruction to gall bladder emptying (95% of cases due to a gall bladder stone)
* Leads to progressive distension - may compromise vascular supply
* Also an inflammatory response secondary to retained bile (unlike biliary colic)
* Infxn may follow
* Rarely it can become distended by pus (empyema), become gangrenous, & perforate leading to peritonitis
K & C p352. - 9S & Sx of acute cholecystitis.* Initial features similar to biliary colic
* Over hours progresses to severe RUQ P due to inflammation irritating the peritoneum
* Muscle guarding & rigidity
* Murphy's sign +ve
* RUQ mass may be palpable (phlegmon - inflamed adherent bowel & omentum)
K & C p352 & OHOCM p636. - 10Describe the Ix used to confirm a Dx of gallstones.* BD's - often show ^WCC & inflammatory markers (eg CRP), ^serum bilirubin
* LFT's - ^ALP, ^GGT
* USS - most useful Ix
* If Dx uncertain after USS HIDA cholescintigraphy
* MRCP may be used for stones in CBD
* Ix for exclusion of DDx - CXR, urinalysis, ECG
OHOCM p636. - 11Rx & Mx of acute cholecystitis.Initially conservative:
* NBM
* IVI
* ABx according to local protocol
After initial Rx laproscopic cholecystectomy - used to be after 6-12/52 now being done early to avoid complications. If GB perforation then open Sx.
OHOCM p636 & 637. - 12What is ERC/P?Endoscopic retrograde cholangiography/pancreatography. Usually used to visualise & remove stones seen via other Ix's from the CBD.
- 13What is cholangitis, what are the S & Sx, & Rx?Infxn of the bile duct. S & Sx:
* RUQ P
* Jaundice
* Rigors
(Charcot's triad)
Rx with ABx - eg cefuroxime 1.5g/8h IV & metronidazole 500mg/8h IV/PR
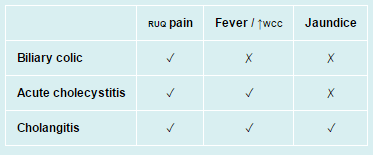
OHOCM p636. - 14Compare & contrast the S & Sx of RUQ P, fever/^WCC, & jaundice in biliary colic, acute cholecystitis, & cholangitis.
Informações
- Descrição
- SGUL LOB's for Alimentary System: Gall Stones, Cholecystitis, Ascending Cholangitis.
- Criado por
- Andrew Street
- Visualizações
- 112
- Avaliação