
Karteikarten
pre and post operative care
Karten in diesem Stapel (29)
- 1pharmacist role in pre operative careget a true medical history
help doctors communicate with each other
ensure the patient understands what they are meant to do with their medications in the lead up to surgery and help them follow this regimen
ensure any meds that may interact with anaesthetics are considered and dealt with - 2things to consider in Anti-coagulation and anti-platelets with pre-operative carehold vs continue
what sort of surgery is it?
what is the duration of the surgery?
what are the risks?
balance between bleeding and thromboembolic complications
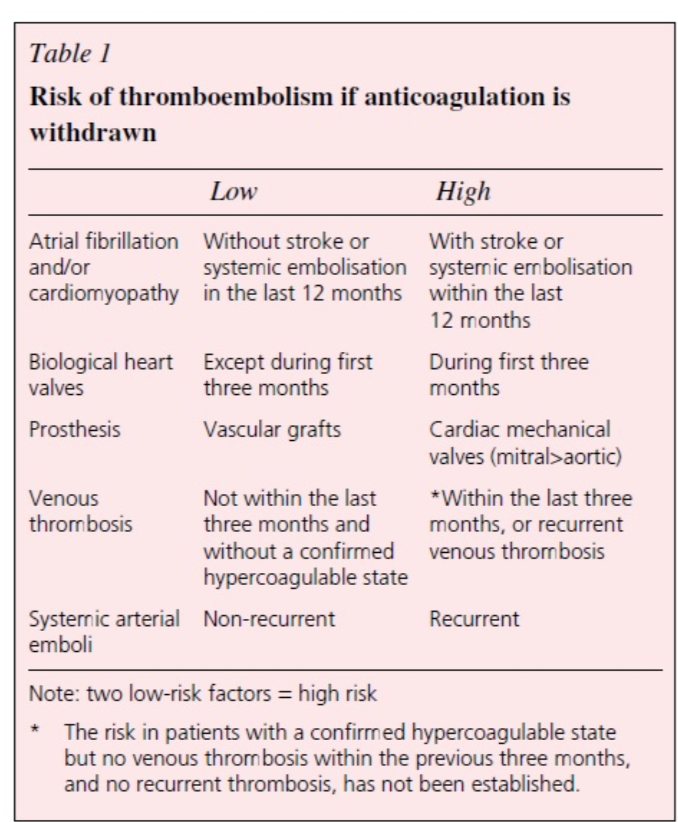
class patient as high risk or low risk for thromboembolism, this helps guide decision making along with T-Guidelines
complex cases (eg hx of heparin induced thrombocytopenia) - 3risk tool exampleeveryone to use same guidelines in the hospital; communicate.
avoid thromboembolism on the table - 4warfarin for patient at HIGH risk of thromboembolismHOLD warfarin 5 DAYS prior to procedure (t1/2 is 40-60hrs)
bridging therapy:
enoxaparin SC 1.5mg/kg daily (depends on renal function - may need to reduce dose)
cease enoxaparin 24 hrs prior to surgery - ensure patient understands when to take last dose
check INR - must be <1.5
vitamin K may be indicated if >1.5 (this will affect how warfarin is restarted) - 5warfarin for patient who is at LOW risk of thromboembolismhold for 5 days prior to surgery
bridging therapy is not required if assessed and found to be low risk
check INR on day of procedure, aim for <1.5
vitamin K may be required if >1.5 - 6restarting warfarin after surgerydue to the time to onset for warfarin, both warfarin and enoxaparin are started after surgery, (approx 24 hours after)
patient needs adequate haemostasis before commencing (Hb, platelets, INR etc)
bloods monitored to ensure adequate haemostasis
remember enoxaparin and renal: CrCl monitoring and dose adjusted accordingly
cease enoxaparin when INR is therapeutic (may still need on D/C if INR isn't right) - 7DOACs and pre surgery guidelinesDOACs have a shorter half life than warfarin
renal function determines how long they need to hold DOAC for before surgery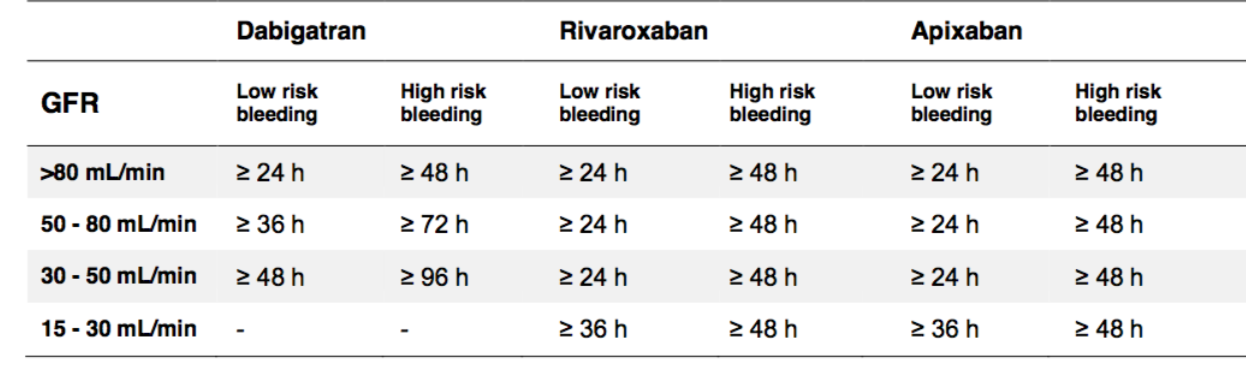
- 8restarting DOACs after surgery24 hrs after minor procedures
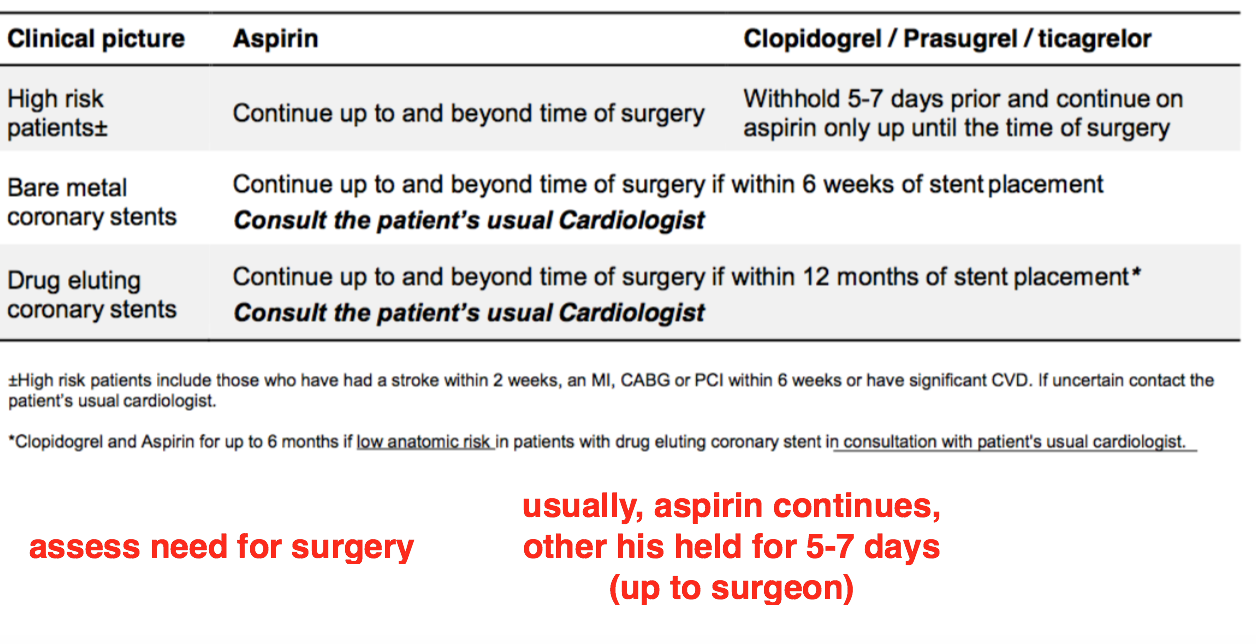
48-72 hours after major procedures - 9anti platelets before surgery
- 10diabetes medications in preoperative care; considerationspeople with diabetes have a higher mortality risk following surgery
hyperglycaemia increases risk of complications
take HbA1c preoperatively - if >8% (64mmol/mol) surgery should be rescheduled
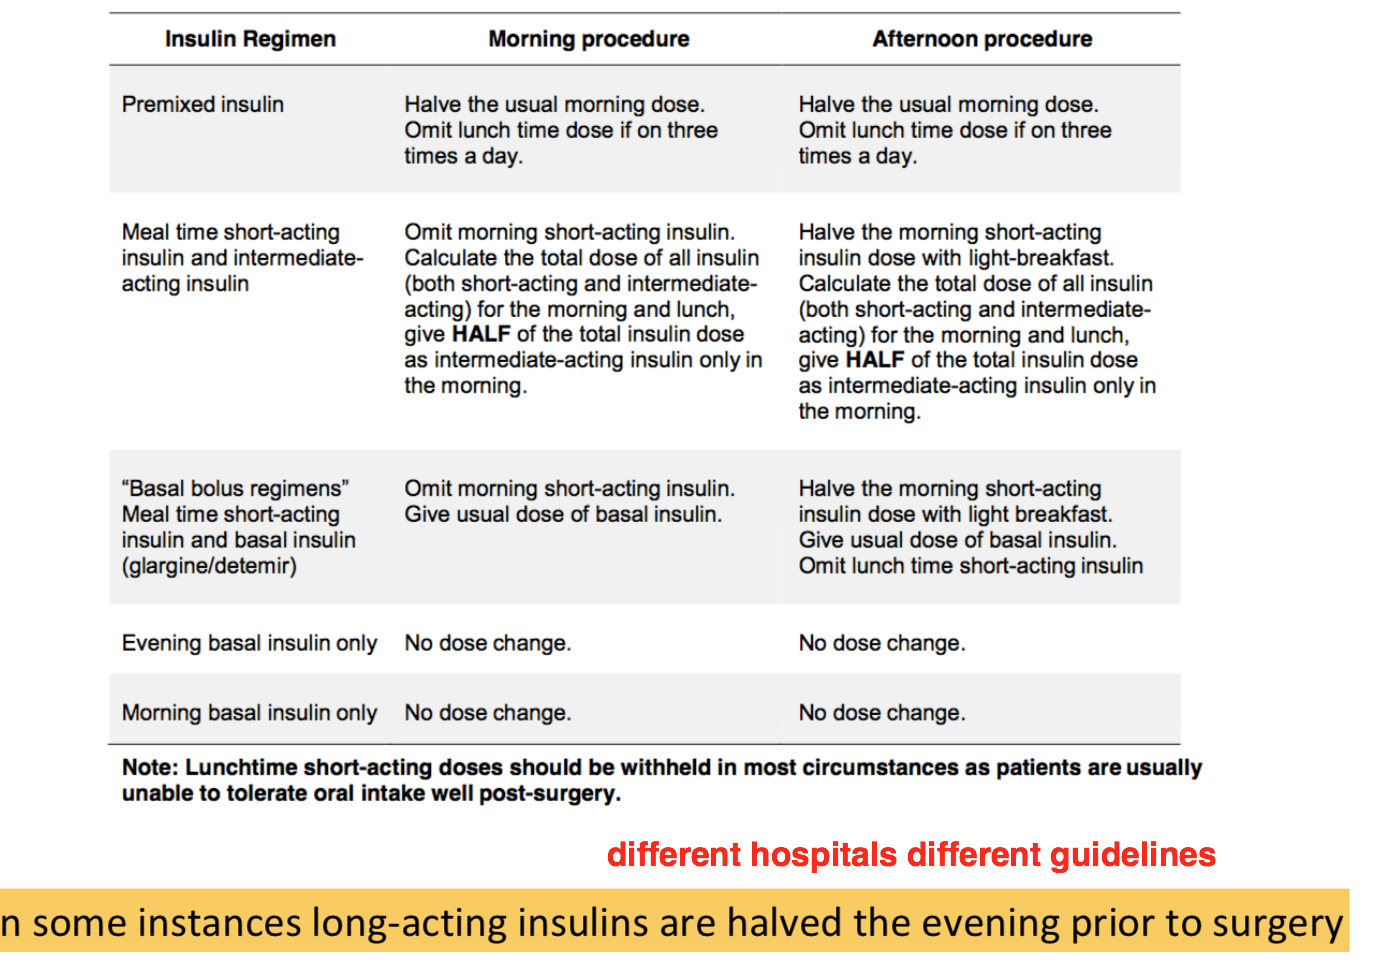
if insulin dependent, patient should be scheduled first thing in the morning to avoid disruption to insulin regime and hyperglycaemia risk, and to avoid prolonged fasting which can cause hypoglycaemia - 11current guidelines pre operative diabetes medications: metforminHOLD morning of surgery
may increase risk of renal insufficiency and lactic acidosis
slow release metformin, consider holding from evening prior to surgery
restart when CrCl is >30mL/min - 12current guidelines pre operative diabetes medications: sulfonylureasHOLD morning of surgery - patient will be fasting, risk of hypoglycaemia
consider holding slow release formulation from evening before surgery - 13current guidelines pre operative diabetes medications: GLP1 analogues (exenatide,, liraglutide)HOLD morning of surgery
can restart when patient is eating and drinking again
GLP1 analogues can cause stomach upset and delay gastric emptying which can negatively affect post-op outcomes - 14current guidelines pre operative diabetes medications: glitazonesHOLD morning of surgery
(fluid retention) - 15current guidelines pre operative diabetes medications: DDP4 inhibitors (sitagliptin)HOLD morning of surgery
restart when patient is eating and drinking again - 16insulin guidelines
- 17current guidelines pre operative diabetes medications: SGLT2 inhibitors (flozins)risk of ketosis
HOLD 3 days prior to surgery - 18post op N&V risk factorspreoperative N&V
female
non-smoker
<50yrs
type of anaesthesia
post op opioids
type of surgery - 19prophylactic treatment of N&Vhigh risk patients should be treated
ondansetron
Droperidol
dexamethasone
use propofol over a volatile anaesthetic (such as -fluranes) can reduce N&V by 19%
multimodal analgesia instead of relying on opioids, including IV paracetamol - 20'rescue therapy' for post op N&V (N&V within 48hrs)consider contributing factors
- inadequate pain relief
- hypotension
- opioids
- dehydration
- blood in GIT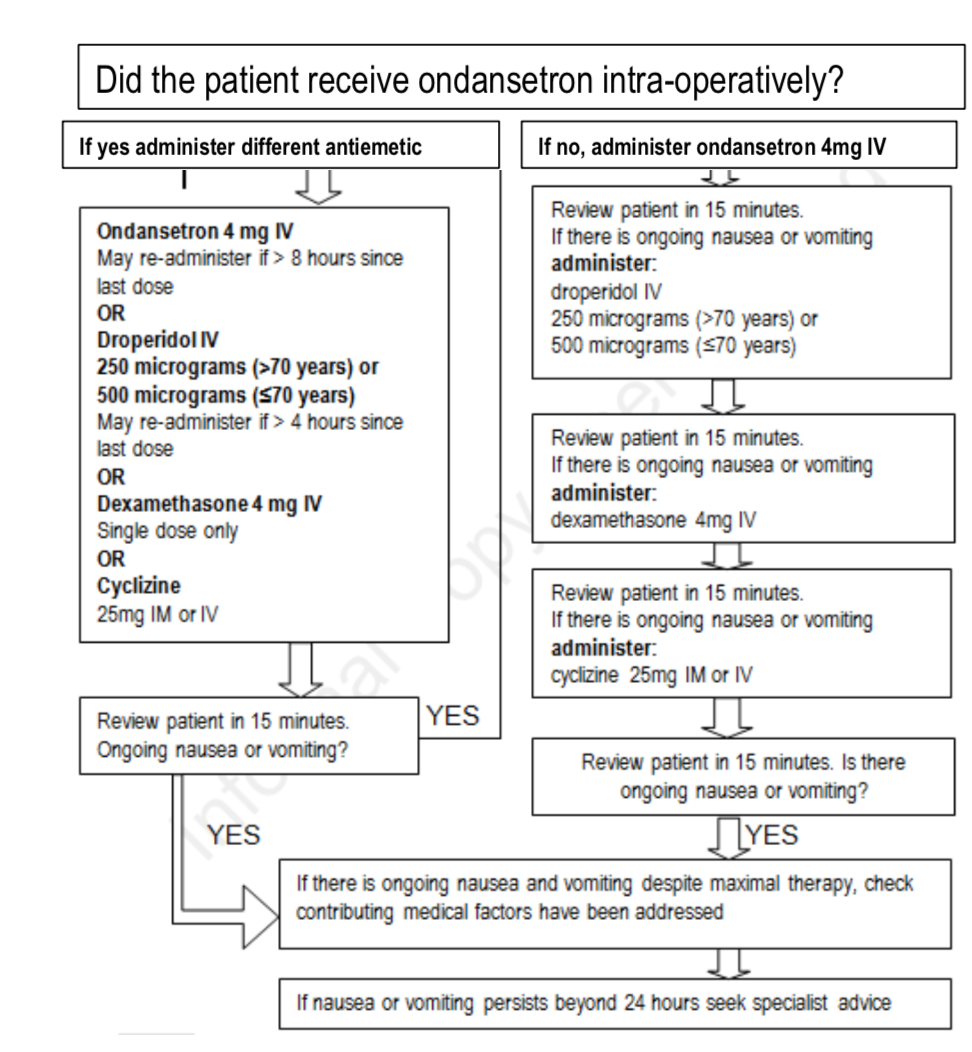
- 21risks with ondansetronserotonin syndrome
prolonged QT interval
pregnancy (?)
apomorphine (severe hypotension)
(ondansetron safe in pregnancy??) - 22risks with droperidolcardiac disease (bradycardia, prolonged QT interval)
other drugs prolonging QT (eg amiodarone)
parkinson's disease
Phaeochromocytoma (tumour on adrenal gland) - 23risks with dexamethasoneactive infection
- 24risks with cyclizinesedation
- 25managing risks associated with antiemeticschoose the one that will not interact with other medicines or disease states
consider ECG/monitoring QT
lower dose?
risk v benefit - 26prophylactic antibiotics - considerationsnot always indicated
only use if chance of infection
Individual risk factors
High-risk of MRSA
Renal function (aminoglycosides)
Allergies
Type of surgery
eg. Small bowel resection vs. vascular surgery
Timing of antibiotic administration IS CRITICAL
IV bolus should be administered 15 to 30 minutes prior to incision IV infusion should begin 30 to 120 minutes prior to skin incision - 27guidelines for plastic surgery (MRSA risk)*****First line antibiotic cefazolin 2g IV– coverage of Staphylococcus aureus (S.aureus)*****
If patient is high-risk of methicillin-resistant S. aureus (MRSA) add vancomycin 1g IV infusion to cefazolin
If patient has severe penicillin allergy substitute cefazolin for vancomycin 1g IV infusion - 28guidelines GI surgerydifferent organisms (anaerobic cover and gram neg)
Metronidazole 500mg IV plus either
Cefazolin 2g IV or gentamicin 2mg/kg IV
High risk of MRSA add vancomycin 1g IV infusion
Penicillin allergy substitute cefazolin with vancomycin 1g IV infusion - 29how to be a pharmacist and positively influence patient careBe aware of the guidelines used in your local health network
Understand the evidence which supports these guidelines
eg. Why anaerobic antibiotics are indicated for colorectal surgical prophylaxis
Make evidence based recommendations to the Anaesthetist, Surgeons and Medical officers to optimise patient safety and their medication regimen
Counsel the patient to ensure that they understand their medication regimen both pre and post-operatively
Informationen
- Beschreibung
- therapeutics (pre/post op) Karteikarten am pre and post operative care, erstellt von Amelia Claire am 14/10/2018.
- Erstellt von
- Amelia Claire
- Aufrufe
- 18
- Bewertung