
Karteikarten
Lower Extremitys
Karten in diesem Stapel (60)
- 1The Lower Extremity OverviewFunction:
• Locomotion
• Carry weight of entire erect body
• Subject to exceptional forces
Components:
1. Thigh - Femur
2. Knee - Patella
3. Leg - Tibia, Fibula
4. Foot - Tarsals (7)
Metatarsals (5)
Phalanges (14) - 2The FemurLargest, longest, strongest bone in the body!!
• Receives a lot of stress.
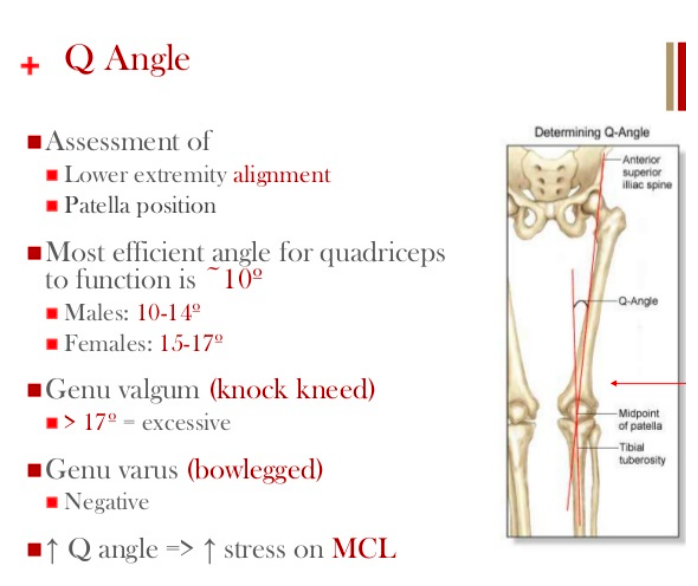
• Larger Q-angle in women.
• Articulations:
1. Acetabulum proximally – Hip
2. Tibia (medial and lateral plateau) - Knee
3. Patella - Knee - 3The PatellaTriangular Sesamoid bone.
• Protects knee joint.
• Improves leverage of thigh muscles acting
across the Knee. Mechanical advantage.
• Contained within Patellar Ligament.
• Articulates only with distal Femur.
• Surrounded by Bursaes. - 4The TibiaReceives the weight of body from Femur and
transmits to foot.
• Second to Femur in size and weight
• Articulations:
1. Femur (medial and lateral condyles)
2. Proximally and distally Fibula
3. Interosseous membrane. - 5The FibulaDoes NOT bear weight.
• Increase surface space for muscle attachment.
• Not part of Knee joint.
• Stabilize Ankle joint.
Articulations:
1. Femur (medial and lateral condyles)
2. Proximal and Distal Tibia
3. Lateral Talus.
4. Interosseous - 6Joints of Lower ExtremityHip (femur + acetabulum)
• Ball + Socket
• Multiaxial Synovial / Diarthrodial
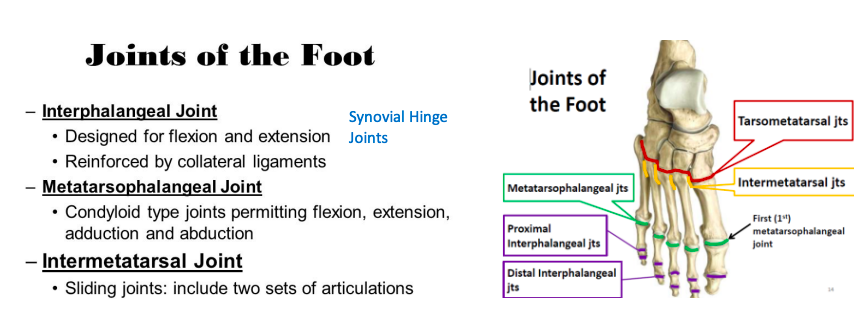
• Labrum deepens socket
• Good ROM – limited by deep socket
Knee (femur + tibia)
• Modified Hinge
• Biaxial Synovial / Diarthrodial
• Intracapsular menisci and ligaments
Knee (femur + patella)
• Plane
• Gliding of Patella
• Uniaxial Synovial / Diarthrodial - 7Joints of Lower ExtremityProximal Tibia + Fibula
• Plane, Gliding
• Synovial / Diarthrodial
Distal Tibia + Fibula
• Slight “give” (synarthrosis)
• Fibrous (Syndesmosis)
Ankle (Tibia / Fibula + Talus)
• Hinge. Ankle Mortese
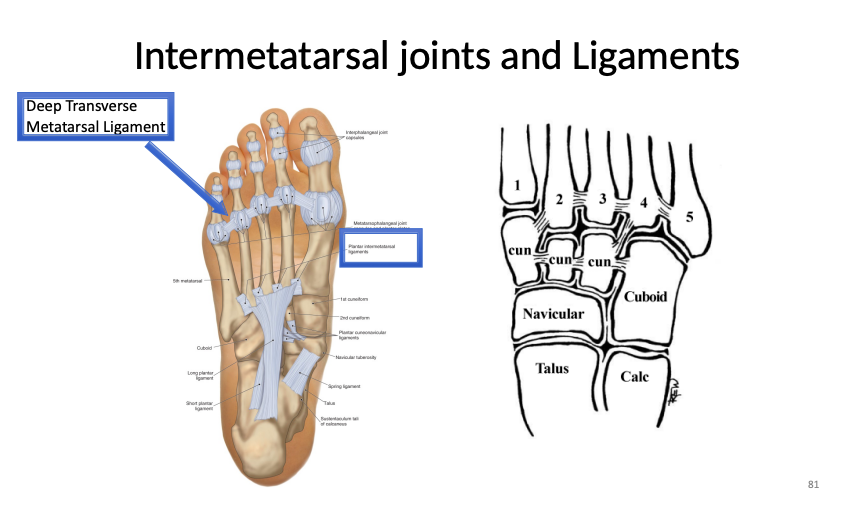
• Uniaxial Synovial / Diarthrodial - 8Angle of InclinationCoxa = HIP
*Normal angle of inclination is 120-135.
• Frontal Plane - 9Coxa Vara1. If the angle of inclination is less than
120 degrees = Coxa Vara.
2. This shortens the limb.
3. Reduces the load on the Femoral head.
4. Increases the load on the Femoral
neck. - 10What are the causes of Coxa Vara1. Trauma
2. Congenital
3. Paget’s disease
4. Perthes disease ( interruption of its blood supply)
5. Osteomyelitis [inflammation of bone due to infection.]
6. Osteogenesis imperfecta [a congenital disorder in which the bones are usually brittle and fragile.
7. Tumors - 11Coxa Valga1. If the angle of inclination is
greater than 135 degrees =
Coxa Valga
2. This lengthens the limb
3. Increases the load on the
Femoral head
4. Reduces the load on the
Femoral neck - 12Causes of Coxa Valga1.Skeletal disease
2. Spasticity of adductor muscles of hip.
3. Cerebral palsy [a disorder of movement and or posture as a result of permanent
damage to the developing brain.
4. Spinal dystrophism [ It's a type of neural tube defect.]
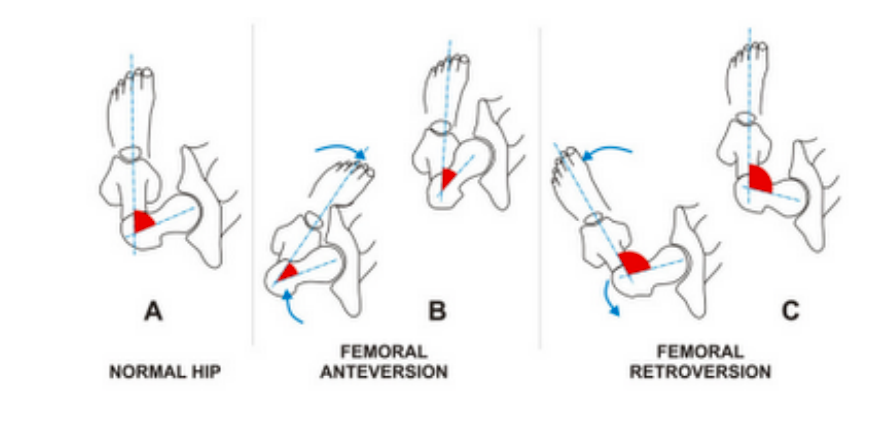
5. Poliomyelitis [an infectious virus disease affecting the CNS. ] - 13Angle of Torsion• The angle of the Femoral neck in the Transverse plane is
termed the angle of Torsion. (some text call it Anteversion.)
• Normally the Femoral neck is rotated anteriorly 12º to 15º
(males and females) with respect to the Femur.
• The Acetabulum faces obliquely anterior, lateral and
inferior. - 14Angles of Torsion pic
- 15Excessive Anterior Torsión / AnteversionExcessive anterior rotation / anteversion beyond 15 degrees would cause the Head of the Femur become
uncovered.
In order to keep the Head of the Femur within the Acetabulum, a person must internally rotate the Femur = Toe in. - 16RetroversionIf the angle of torsión is less than 15 º of anterior rotation, it is termed Retroversion.
• This condition causes the person to externally rotate the Femur = Toe out. - 17Hip JointArticulation: - Head of the Femur
and Acetabulum of the Innominate
(Pelvis).
• Ball and Socket Joint - 18Weight bearing at the HipWeight of the body (at
least ½?) goes thru the
Hip and ground
reaction forces come
up thru the Hip.
The two forces create
shear forces across the
Femoral neck - 19Hip ligaments1. Iliofemoral - anterior, v-shaped, strongest in the body. (one of)
2. Pubofemoral – medial inferior, triangular, blends with iliofemoral, limits
Abduction and external rotation of hip.
3. Ischiofemoral – posterior, spirals around to ant greater trochanter, weakest of 3
ligaments, limits internal rotation.
4. Ligamentum Teres / Capitus Femoris – flat, intracapsular lig, attaches head of
femur to floor of acetabulum, contains an artery.
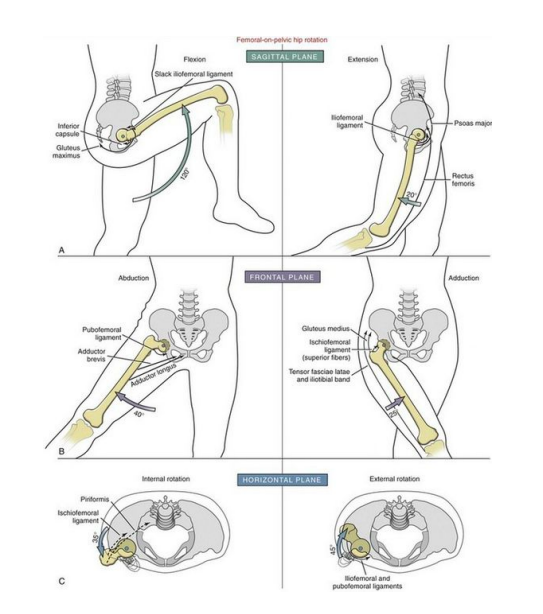
** All ligaments limit Extension of the hip. Muscle bulk limits flexion. - 20Hip Biomechanics and Axis of Rotation
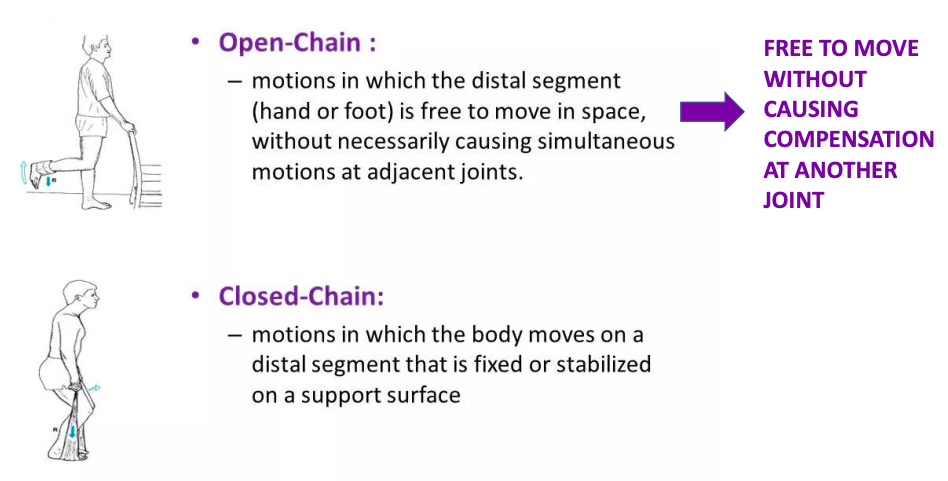
- 21Open chain and closed chain
- 22The Knee JointLargest and most complex joint in the body.
• One of the most frequently injured joints in the body.
• Synovial, Diarthrodial, Biaxial Joint.
• “Modified” Synovial Hinge Joint –
1. It mainly Flexes and Extends in the Sagittal Plane.
2. Also has a small rotational component as well.
(part of the knee locking mechanism) Transverse
Plane. - 23What part does the knee joint articulate?Medial and Lateral Femoral Condyle articulates with the
Medial and Lateral Tibial Plateau (via the meniscus).
Modified Hinge Joint.
Posterior surface of the Patella articulates with the anterior surface of the Femur in the Patellofemoral Groove. Plane Gliding Joint. - 24Knee Tendon structure• Capsule is reinforced by muscle tendons:
➢ E.g., quadriceps and
semimembranosus tendons
• Anteriorly, the quadriceps tendon gives
rise to:
➢Lateral and medial patellar retinacula
➢Patellar ligament - 25Q knee angle
- 26Ligaments of the Knee1. Medial Collateral Ligaments – protects
against Valgus Strain / Force.
2. Lateral Collateral Ligaments – protects against Varus Strain / Force.
3. Anterior Cruciate ligaments - Intra articular ligament, protects against anterior
shear forces. Attaches to anterior Tibia. Taut during extension. Shorter and
stronger.
4. Posterior Cruciate ligaments- Intra articular ligament, protects against posterior shear forces. Attaches to posterior Tibia. Taut during Flexion.
5. Ligamentum Patallae – extension of Quadriceps tendon.
*All Ligaments help to prevent excessive extension / hyperextension. - 27Pes Anserine of the KneeThe Pes Anserine, also called the 'Goose
Foot' is the insertion of the sartorius,
gracilis and semitendinosus muscles,
which are conjoined proximally on the
medial side of the Tibia.
The three tendons of the Pes Anserine
are located superficial to the medial
collateral ligament (MCL) of the knee. - 28ACL and PCL attachmentACL and PCL
They are “Intracapsular Ligaments” and named for their attachment on the Tibia. - 29MenisciPrimary Functions:
1. Absorption of shock.
2. Increased congruency of the condyles of
the femur with the condyles of the tibia.
3. Moves the synovial fluid though the joint - 30Biomechanics of the Knee• Flexion
• Extension
• Slight medial rotation
• Slight Lateral rotation
• The main muscles that move the Knee joint are the Quadricep and Hamstring
muscles.
• Popliteus muscle helps to unlock the Knee. - 31The Locking MechanismBuilt-in locking device that provides steady
support for the body in the standing position.
• As we stand up, and our knee moves from a flexed to an extended position.
• The Femoral condyles roll like ball bearings on the Tibial condyles.
• Mostly rolls in sagittal plane but last few
degrees of extension also spins in the
transverse, to lock the knee. - 32The Locking Mechanism / Screw Home MechanismAs the knee extends the ACL becomes taut – which also causes external rotation of
the knee
• The external rotation”screws” the Tibia into a closed pack position - locking the
knee for maximal stability.
• To unlock the Knee, the Popliteus muscle contracto causing the Femur to rotate
lateral / Tibia Medially. - 33Patella biomechanicsPatella acts like a space between the quad tendón and Femur, which increases the moment arm, giving a mechanical advantage to the quadricpes muscles
FN of the Patella:
1. Reduce Tendon / Ligament Strain.
2. Spread the forces to the Condyles.
3. Increase the forcé of the Quad ms. - 34Patella positioningPatella Baja:
Patella Baja is a condition
where the knee cap is
positioned too low. It can
make bending your leg
past 90 degrees difficult
to impossible.
Patella Alta
Patella Alta
Is associated with
chondromalacia on
the articular surface
of the patella and
pain - 35Patella contact pointsThe contact points between the patella and
fémur change throughout the ROM;
accordingly, the joint forces change too.
More contact área = less stress / damage to
any one área of the joint / articular surface.
PF stress also changes during open and closed chain activities. - 36Patellar Reaction ForceIn non-weightbearing, (open chain) the contact area between
patella and fémur increases during flexión from 0-90 degrees.
Therefore less patellofemoral stress occurs as knee flexion increases. Open chain exercises should occur from 90 to 30 of
knee flexion.
Weighbearing: (closed chain) when the foot is fixed, the RF increases from 90 to 45 degrees, then decreases as the knee
approaches full extension.
Therefore Closed chain exercises should occur from 45 to 0 of
knee flexion. - 37Patellar Reaction ForcesAbnormal tracking will also create
undue stress on the patellofemoral
joint.
Patellofemoral joint stress can be tremendous during even the simplest of activities of daily living, not to mention with sports and recreational activities. - 38Proximal and Distal Tib-Fib JointsProximal Tibia + Fibula:
• Plane, Gliding
• Synovial
Distal Tibia + Fibula:
• Slight “give” (synarthrosis)
• Fibrous Syndesmosis
Interosseous Membrane:
• Syndesmosis
• Amphiarthrotic - 39Tibiofibular articulationArticulations:
1. Proximal or Superior Tibiofibular - small facet on head of Fibular articulates with
facet on Lateral surface of the Lateral Condyle of the Tibia. (AP/SI motion.)
2. Distal or Inferior Tibiofibular – concave surface of the medial side of the inferior
Fibula articulates with the convex surface of the Fibular notch of the Tibia. No
Capsule bc not Synovial joint. Want a tight non moving joint.
3. Interosseous Membrane (intermediate joint) – attaches to the interosseous borders
of Tib and Fib and provides sites for ms attachment. - 40Proximal Tibio-Fibular LigamentsLigaments:
1. Anterior Superior Tib-Fib
2. Posterior Superior Tib-Fib
3. Fibular / Lat Collateral - 41Distal Tibio-Fibular LigamentsLigaments:
1. Inf. Ant [Tib-Fib Ligament]
2. Inf. Post [Tib-Fib Ligament]
3. Transverse [Tib-Fib Ligament] - 42Joints of the foot and ankle1. Ankle (Tibia/Fibula + Talus)
• Hinge, Uniaxial
• Synovial
2. Intertarsal & Tarsal-Metatarsal:
• Plane, Ball and Socket, Condyloid
• Synovial
3. Metatarsal-Phalangeal
• Condyloid, synovial
4. Interphalangeal
• Hinge, uniaxial - 43The Foot and Ankle contains how many bones?• There are 28 bones and 25 joints in the
Foot and Ankle complex.
• These structures are configured to
accommodate the stability and mobility
responsibilities of the foot and ankle on
various surfaces during varying degrees of
weight bearing
xx - Talus transfers most of the weight from
the Tibia to the Calcaneus. - 44Foot and Ankle function:1. Supports the weight of the body.
2. Act as a lever to propel the body forward.
3. Shock absorber – 3 arches and ligaments
act like a “Spring”. - 45Joints of the Foot and Ankle1. Talo-Crural (True Ankle)
2. Sub-Talar (Talocalcaneal)
3. Talo-Calcaneo-Navicular
4. Calcaneo-Cuboid
5. InterTarsal
6. Tarso-Metatarsal
7. Intermetatarsal
8. Metatarso-Phalangeal
9. Interphalangeal - 46Talo-Crural JointAka: True Ankle Joint
Type: Synovial, Uniaxial, Hinge
Crus = latin for leg (knee to foot)
Crural = plural of crus
Articulation:
• Superior surface of the body of the Talus articulates with
the inferior surface of the Tibia forming the true ankle joint
• Lateral surface of the Talus articulates with medial surface
of the lateral Malleous of the Fibula. - 47Talo-Crural Ligaments (Lateral Collateral) Whats the function?1. Anterior Talofibular Ligament (most
commonly injured ligament.)
2. Posterior Talofibular Ligament.
3. Calcaneofibular Ligament.
• Function: to resist Inversion of the ankle.
• if the force is excessive = Inversion ankle
sprain. - 48Talo-Crural Ligaments (Medial collateral ligament) and whats the function?Medial collateral ligaments
A strong, flat, triangular band that is much
stronger than lateral collateral.
1. Anterior Tibiotalar ligament
2. Posterior Tibiotalar ligament
3. Tibiocalcaneal ligament
4. Tibionavicular ligament.
Function: Resists Eversion of the Ankle joint. - 49Biomechanics of the Talo-Crural JointDorsiflexion and
Plantar Flexion
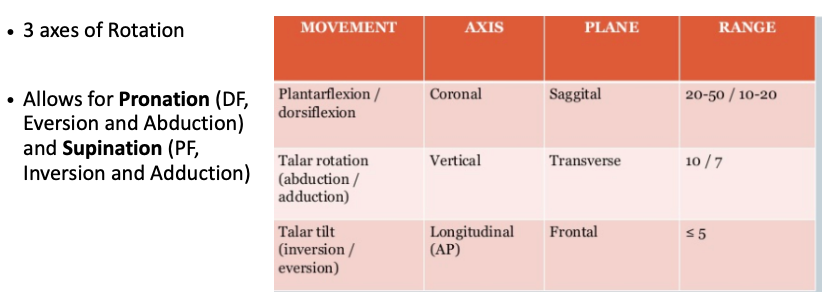
Dorsiflexion and plantar flexion in the foot and ankle occur around an oblique axis, and eversion and inversion occur around the longitudinal axis. - 50TaloCalcaneal (Subtalar) JointType: Synovial Condyloid joint
Articulations:
• Anterior, Posterior and Middle facets of
the Talus articulate with corresponding
facets of the Calcaneus. - 51Talocalcaneal (Subtalar) Joint Ligaments1. Interosseous Talo-calcaneal
2. Lateral Talo-calcaneal
3. Medial Talo-calcaneal
4. Posterior Talo-calcaneal
5. Anterior Talo-cancaneal (anterior
interosseus)
• All function to stabilize the joint against
excessive movement - 52Sub-Talar Biomechanics
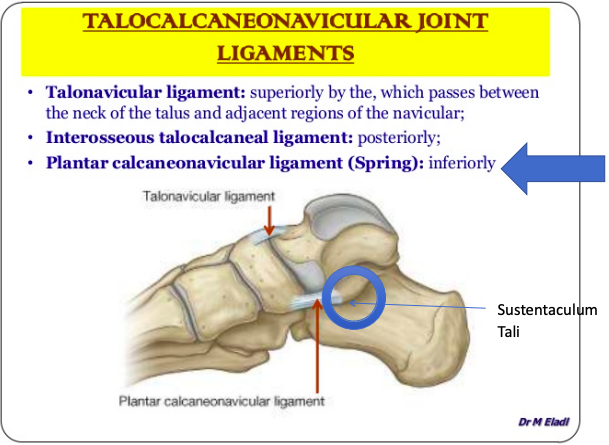
- 53Talo -”Calcaneo”- Navicular JointType: Synovial, multi-axial, tri-planar ball-and-socket
joint
Articulations:
• Round head of the Talus (distal) articulates with the
concave surface of the Navicular (proximal), and the
Plantar Calcaneonavicular ligament below (spring
ligament)
• Allows for gliding, rotation movements producing -
pronation / supination and inversion /eversion - 54Talo -”Calcaneo”- naviclar ligaments
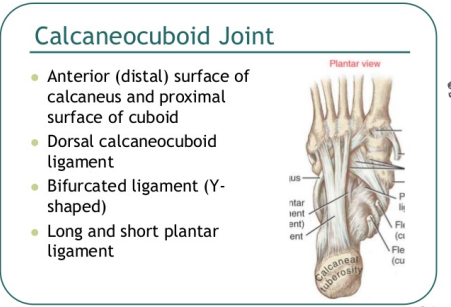
- 55Calcaneocuboid JointPlane Synovial Joint
***The least mobile joints in
the human foot = Boring - 56Calcaneocuboid ligament
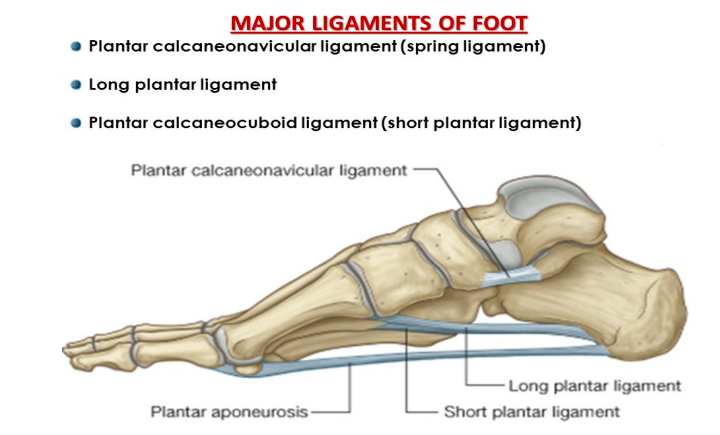
- 57What are the major ligaments of the foot?
- 58Joints of the foot
- 59Intermetatarsal joints and Ligaments
- 60What is the plantar FasciaThe plantar fascia is the thick
connective tissue (aponeurosis) which
supports the arch on the bottom
(plantar side) of the foot.
It runs from the tuberosity of the
calcaneus (heel bone) forward to the
heads of the metatarsal bones (the
bone between each toe and the bones
of the mid foot).
Informationen
- Beschreibung
- Grado Superior Biomechanics and Technique Karteikarten am Lower Extremitys , erstellt von Calvin Soares am 09/06/2022.
- Erstellt von
- Calvin Soares
- Aufrufe
- 0
- Bewertung