
Apuntes
Notes
Contenido del apunte (3)
Página 1
Week 1
Indicators of Abnormality
•Subjective Distress
•Maladaptiveness
•Statistical Deviancy
•Violation of the Standards of Society
•Social Discomfort
•Irrationality and Unpredictability
•Dangerousness
DSM-5 Definition of Mental Disorder
•Biological, psychological, or developmental dysfunction in individual
•Clinically significant disturbance in behavior, emotional regulation, or cognitive function
•Associated with distress or disability
Classification and Diagnosis
Classification Systems
•Provide nomenclature and common language
•Allow information structuring
•Facilitate research
•Establish the range of problems to address
Disadvantages:
•Loss of individual’s information
Stigma and stereotyping associated with diagnosis
Self-concept impacted by diagnostic labeling
Reducing prejudice:
•Negative reactions are widespread global phenomena
•Understanding of neurobiological basis does not lessen stigma
•Contact with individuals does not lessen stigma
Culture and Abnormality:
Cultural Influences:
•Presentation of disorders found worldwide
•Certain forms of highly culture-specific psychopathology
•Certain forms of psychopathology highly specific to certain cultures
•Taijin kyofusho in Japan
•Ataque de nervios in Latinos and Latinas especially from the Caribbean
How Common are Mental Disorders
•Significant question for many reasons
•Planning, establishing, and funding mental health services for specific disorders
•Providing clues to causes of mental disorders
•Epidemiology
Prevalence
•Number of active cases in population during any given period of time
•Typically expressed as percentages
•Different types of prevalence estimates (point, 1-year, lifetime)
Incidence
•Number of new cases in population over given period of time
•Incidence figures are typically lower than prevalence figures
•Lifetime prevalence of having any DSM disorder is 46.4% but does not include all disorders
•Most prevalent category is anxiety disorders, followed by mood disorders
•Most common individual disorders are major depressive disorder, alcohol abuse, phobias, and conduct disorder
•Comorbidity—two or more disorders in the same person—is high, especially when a person has one serious disorder
Treatment
•Vast majority of treatment is done on outpatient basis
•Inpatient hospitalization typically in psychiatric units
•Diagnosis and assessment involves participants who
•Play differing roles in the process
•Gather comprehensive evaluation patient data
Research Approaches in Abnormal Psychology
Benefits:
•Learn about a disorder’s symptoms, prevalence, duration (acute, chronic), and accompanying problems
•Understand etiology and nature of disorder
•Discover how to provide the best patient care
Case studies:
•Specific individual observed and described in detail
•Subject to bias of author of case study
•Conclusion have low generalizability
Self-Report Data
•Participants asked to provide information about themselves
•Interviews and Questionnaires
•May be inaccurate
People may not know why they do something or may intentionally be misleading
Observational Approach
•Collecting information without asking participants directly for it
•Outward behavior can be observed directly
•Biological variables can be observed via technologically advanced methods
Forming and Testing Hypothesis
Hypothesis
•An effort to explain, predict, or explore something
•Often sparked by anecdotal accounts and unusual research findings
•Must be tested in well-designed research studies
•Frequently determine therapeutic approaches used to treat a particular clinical problem
Sampling and Generalisation
•Who should researchers include in a study?
•Individuals who are similar in their behavioral abnormalities (representative)
•Study group should mirror underlying population in all important ways
•Large, randomly selected groups are ideal
Finding Research Participants
•Samples of convenience (using subjects who are easily accessible)
•Online recruitment of subjects (Amazon’s Mturk)
Disadvantages
•Not a representative sample of the population as a whole
Validity
Internal validity
is the extent to which a study is methodologically sound
Internally valid studies are free of confounds and lead to valid conclusions
External validity
is the extent to which a study’s findings can be generalized beyond the study itself
Externally valid studies typically use samples representative of the population
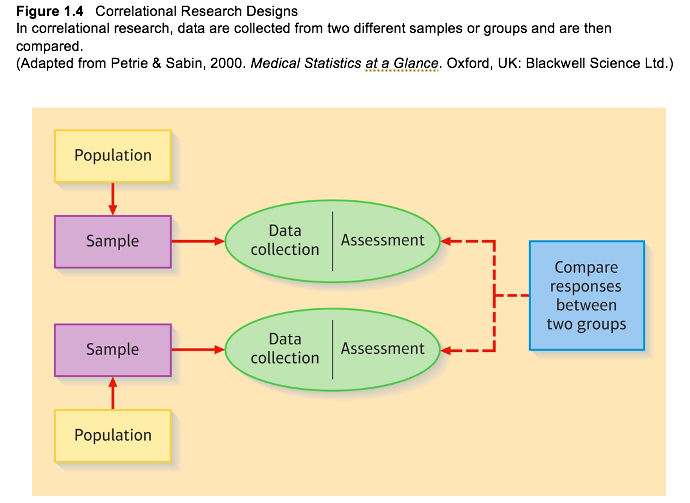
Correlational Research Designs
Correlational research studies the world as it is
It does not involve any manipulation of variables, but rather, the researcher selects certain groups of interest and compares the groups on a variety of different measures.
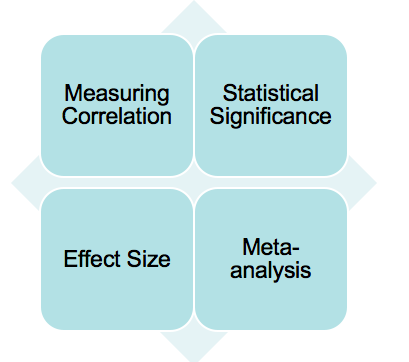
Statistical Significance
Research articles often identify correlations as significant by noting p < .05
This means there is less than a 5 in 100 chance that the correlation would happen by chance
Both the strength of the correlation and the size of the sample influence statistical significance
Effect Size
Can’t use significance to compare findings if sample sizes were different
Effect size is a stable measure used to compare across studies
An effect size of zero means there is no association between the variables
Meta-Analysis
•More effective than literature review summary
•Calculates effect sizes and then combines them for all studies included in analysis
•Each study is equivalent to one individual participant
•Correlation does NOT mean causation!
Retrospective versus Prospective Strategies
Retrospective research strategies involve looking back in time, often to a point before the participant developed a disorder
Prospective research strategies involve looking ahead in time, usually with participants with a high likelihood of becoming disordered
A study that follows people over time and that tries to identify factors that predate the onset of a disorder employs a longitudinal design.
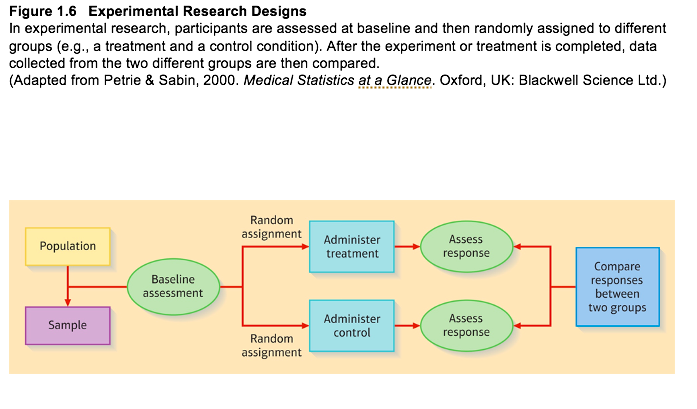
The Experimental Method in Abnormal Psychology
•Studying the Efficacy of Therapy
•Should a treated group show significantly more improvement than an untreated group, one can have confidence in the treatment’s efficacy
•It is important to make the treated and untreated groups as equivalent as possible
•As an alternative to no treatment, standard treatment can be used as a comparison group
•Single-Case Experimental Designs
Single-case experimental designs (e.g., ABAB designs) can also be used to make causal inferences in individual cases
ABAB designs involve alternating baseline condition (no treatment) with treatment condition
•Animal Research
•Factors to consider
•Ethical issues
•Advantages
•Generalizability (analogue studies)
•To draw conclusions about causality, resolve questions of directionality
•Scientists control all factors except independent variable
•Actively manipulate independent variable
•If dependent variable changes as independent variable changes, it is regarded as a cause of the outcome
Unsolved Issues:
•Categorization of increasing numbers of people as mentally ill
•Financial interests of mental health professionals benefit from inclusive definitions
•How broadly should abnormality be defined?
Historical Views of Abnormal Behaviour
•Edwin Smith papyrus
•Wound treatment
•Brain as site of mental functions
Ebers papyrus
•Covers internal medicine and circulatory system
•Explains cures diseases with incantations and magic
•Ancient Mesopotamia
•Clear recognition of mental health problems
Demonology, Gods, and Magic
Religious or mystical significance to hallucinations considered good
If overexcited or behaved against religious teachings thought to be possessed by angry god
The primary type of treatment for demonic possession was exorcism, which included various techniques for casting an evil spirit out.
Hippocrates’ Early Medical Concepts
Thought the brain was the central organ of intellectual activity
Mental disorders due to brain pathology
Emphasized the importance of heredity and predisposition
Pointed out that injuries to the head could cause sensory and motor disorders.
Used clinical observation to classify disorders
First to associate temperament with four humors and thought dreams could reveal aspects of personality
Early Philosophical Conceptions of Consciousness
Plato
•Viewed psychological phenomena as responses of the whole organism
•Emphasized individual differences and sociocultural influences
•Discussed hospital care
Aristotle
•Wrote lasting description of consciousness
•“Thinking” as directed would eliminate pain, attain pleasure
Rejected idea that mental illness was due to psychological factors
Later Greek and Roman Thought
Egyptians used diet, massage, hydrotherapy, gymnastics, bleeding, restraints
•Asclepiades
proposed disease based on flow or atoms
•Galen
provided anatomy of nervous system
divided causes of disorders into physical and mental categories
Roman
medicine focused on comfort, contrariis contrarius
Early Views of Mental Disorders in China
•One of earliest foci on mental disorders
•Emphasis on natural causes
•Chung Ching: “Hippocrates of China”
•Experienced brief “Dark Ages” that blamed supernatural causes
•Incorporation of ideas from Western psychiatry in last 50 years
Medicine based on natural causes of illness not supernatural: yin and yang are opposing forces that must be kept in balance to have good health
Chung Ching: used observations, thought organ pathology was primary cause of disease, used drugs and emotional balancing as treatment
Views of Abnormality During the Middle Ages
•Middle East
had scientific approach
First mental hospital in Baghdad in 792 A.D.–used humane treatment
Avicenna from Persia (c. 980–1037), the “prince of physicians,” was the author of The Canon of Medicine, perhaps the most widely studied medical work ever written
Mass madness: group behavior disorders. Ex: tarantism--a disorder that included an uncontrollable impulse to dance that was often attributed to the bite of the southern European tarantula or wolf spider or lycanthropy: people thought they were possessed by wolves
Mass madness occasionally appears in modern times: 1983 Palestinian girls
Witches not all thought to be mentally ill but poor women with bad temper. Some were spiritually possessed
•Europe
was plagued with mass madness and treatment included exorcism
•Fear of witchcraft now questioned
Toward Humanitarian Approaches
•Resurgence of Scientific Questioning in Europe
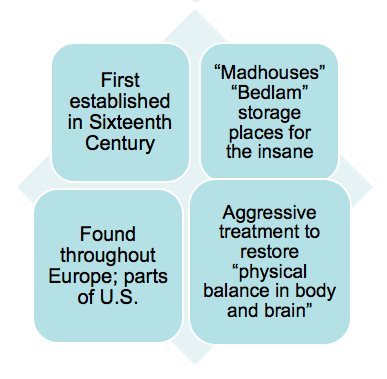
•Establishment of Early Asylums
•Humanitarian Reform
•Nineteenth Century Views of Causes and Treatments of Mental Disorders
•Changing Attitudes Toward Mental Health in Early Twentieth Century
•Mental Hospital Care in Twentieth Century
The Resurgence of Scientific Questioning in Europe
•Renaissance
•Led to resurgence of scientific questioning in Europe
•Part of humanism movement
Paracelsus (1490-1541) and Weyer (1515-1588) questioned supernatural causes of disorders. Weyer wrote criticism of witchcraft possession.
Weyer was one of the first physicians to specialize in mental disorders, and his wide experience and progressive views justify his reputation as the founder of modern psychopathology
Humanitarian Reform
•France
•Philippe Pinel
Unchained patients, placed them in sunny rooms and treated them with exercise and kindness. This was very successful.
•England
•William Tuke, Quakers
established the York Retreat, a country house for the mentally ill. He treated with kindness and acceptance
In 1845, the Country Asylums Act was passed in England. Required every county to provide asylum to “paupers and lunatics”
•America
Benjamin Rush
pushed moral management in America (emphasized spiritual and moral development
•Benjamin Franklin
proposed using electricity to treat melancholia (depression)
•Dorothy Dix
From 1841 to 1881, Dorothy Dix lobbied for better treatment for the mentally ill in asylums. The caused the growth of the mental hygiene movement. Suitable hospitals were built
•The military’s role in mental health treatment
•American Civil War
•First mental health facility opened
•Germany 1870-1914
•Developed program of military psychiatry following Franco-Prussian War
•Contributed to field of abnormal psychology
Nineteenth-Century Views of the Causes and Treatment of Mental Disorders
Early part of century, psychiatrists (alienists) had little to do with treatment of insane because of moral management treatment
Later part of century, took over asylums. Used both moral management and physical treatments
Psychiatrists thought that emotional problems (“shattered nerves”) were caused by the expenditure of energy or by the depletion of bodily energies as a result of excesses in living
Changing Attitudes Toward Mental Health in the Early Twentieth Century
•Clifford Beers
•Described own mental collapse in A Mind That Found Itself
•Began campaign for reform
Mental Hospital Care in the Twentieth Century
•1940: Hospital stays lengthy. Care was punitive, harsh and inhumane
1946: The Snake Pit called attention to the plight of mental patients and argued for community care
1946: NIMH: support for psychiatric research and training
1946: Hill-Burton Act: funded community mental health hospitals
1963: The Community Health Services Act: develop outpatient psychiatric clinics, community consultations, and rehab programs
•Deinstitutionalization lead to mixed results
•Large numbers of mental hospital closures and shift to community-based residences
•Global movement: Asia, Europe, U.S.
•Considered more humane and cost effective
•Created problems for both patients and society as a whole
The Emergence of Contemporary Views of Abnormal Behavior
Recent changes:
•Biological discoveries
•Development of mental disorders classification system
•Emergence of psychological causation views
•Experimental psychological research developments
Establishing the Link Between the Brain and Mental Disorder
•Biological and anatomical factors recognized as underlying both physical and mental disorders
•Cure for general paresis (syphilis of the brain)
•Raised hopes that organic bases would be found for many other mental disorders
•Mental disorders an illness based on brain pathology
•Downside: removal of body parts, lobotomies
The Development of a Classification System
•Kraepelin
•Compendium der Psychiatrie (1883): forerunner to DSM
Certain symptoms occur together frequently enough to be considered separate mental disorders
•Course of each disorder predictable and therefore outcome can be predicted
Specific types of mental disorders identified
Development of the Psychological Basis of Mental Disorder
•Freud’s psychoanalytic perspective
•Comprehensive theory of psychopathology
•Emphasis on inner dynamics of unconscious motives (psychodynamics)
•Ancestral roots the study of hypnosis
•Mesmerism
•Diseases treated by “animal magnetism”
•Source of heated discussion in early nineteenth century
Franz Anton Mesmer (1734–1815) was an Austrian physician who further developed the ideas of Paracelsus
•All people possessed magnetic forces that could be used to influence the distribution of the magnetic fluid in other people, thus effecting cures
Discredited in Europe, but mesmerism was popular in United States, intriguing a number of Americans, such as the poet Emerson to the physician Benjamin Rush
•Nancy School
•Hypnotism and hysteria are related and due to suggestion
•Hysteria, a form of self-hypnosis, could be caused and removed by hypnosis
•Nancy School–Charcot debate
•Are mental disorders caused by biological or psychological factors
Toward the end of the nineteenth century, it became clear that mental disorders could have psychological bases, biological bases, or both.
Major question remained: How do the psychologically based mental disorders actually develop?
•Sigmund Freud (1856–1939)
took the first major steps toward understanding psychological factors in mental disorders
•His theories have evolved into the psychoanalytic perspective
•Psychoanalysis emphasizes the inner dynamics of unconscious motives
•Psychoanalysis
•Catharsis
•The unconscious
•Free association
•Dream analysis
Experimental Psychology
•Wilhelm Wundt
established the first experimental psychological laboratory at the University of Leipzig
•J. McKeen Cattell
brought Wundt’s methods to the United States
•Lightner Witmer
established the first American psychological clinic at the University of Pennsylvania
•Soon after, the first psychological journals hit the press
The Behavioral Perspective
•Role of learning in human behavior
Classical conditioning:
•Neutral stimulus repeatedly paired with unconditioned stimulus; naturally elicits an unconditioned behavior
•Ivan Pavlov demonstrated that dogs will salivate to a nonfood stimulus once regularly accompanied by food
•John B. Watson emphasized the study of overt behavior
•Abnormal behavior was the product of unfortunate, inadvertent earlier conditioning and could be modified through reconditioning
•Operant Conditioning
•E. L. Thorndike and B. F. Skinner studied how the consequences of behavior influence behavior
Unresolved Issues
•Interpretation of historical events and influence of biases
•Controversy over importance and relevance of some historical events
Página 2
Week 2
•Study of causes and risk factors for abnormal behavior includes:
•Necessary, sufficient, and contributory causes
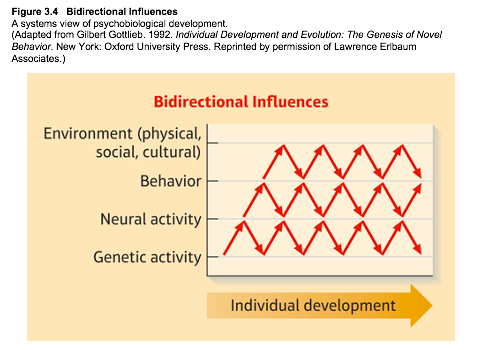
•Feedback and bidirectionality in abnormal behavior
•Diathesis-stress models
Many mental disorders are believed to develop when someone who has a preexisting vulnerability for that disorder experiences a major stressor.
•Diathesis: Relatively distal necessary or contributory cause that is not sufficient to cause disorder
•Stress: Response of individual to taxing demands
•Diathesis-stress models: Combination of diathesis and stress to cause disorder
Causes:
•Etiology: Causal pattern of abnormal behavior
Necessary cause (X): Must exist for disorder to occur
Sufficient cause (Y): Guarantees occurrence of disorder
Contributory cause: Increases probability of developing disorder; reinforcing contributory cause maintains maladaptive behavior that is already occurring
•Distal causal (or risk) factors occur early in life or don’t show effects for many years
A reinforcing contributory cause is a condition that tends to maintain maladaptive behavior that is already occurring.
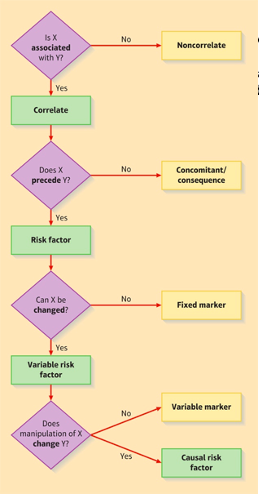
Diathesis - Stress Model
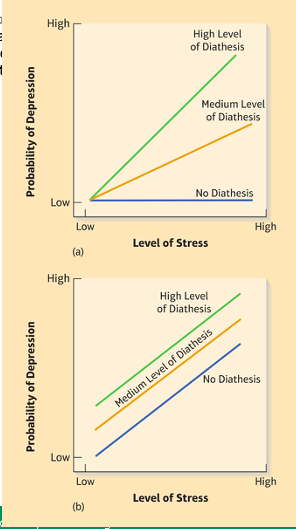
Diathesis - Stress Model
Diathesis–stress models need to be considered in a broad framework of multicausal developmental models
To understand what is abnormal, one must always have a good understanding of normal human development at biological, psychological, and sociocultural levels of analysis (developmental psychopathology)
Protective factors: Influences that modify person’s response to environmental stressors, making adverse consequences less likely
Can be positive (ex: good attachment to one parent), negative (response to medium amount of stress), or inherent trait in an individual
Perspectives for Understanding the Causes of Abnormal Behavior
Viewpoints:
Help professionals organize observations
Provide systems of thought
Suggest areas of focus
Perspectives are theoretical constructions devised to orient psychologists in the study of abnormal behavior – may cause psychologists to overlook other viewpoints
Many theorists are pushing for a more integrative biopsychosocial viewpoint that acknowledges that biological, psychological, and social factors all interact and play a role in psychopathology and treatment
Biological Perspective
Traditional biological viewpoint
focuses on mental disorders as diseases
Current viewpoint
acknowledge psychosocial and sociocultural causal factors play a role as well
•Four categories of biological factors relevant to maladaptive behavior
•Genetic vulnerabilities
•Brain dysfunction and neural plasticity
•Neuro-transmitter & hormonal abnormalities in brain and CNS
•Temperament
Chromosomes:
A normal human male has 23 pairs of chromosomes, including an X chromosome and a Y chromosome.
Vulnerability to mental disorder almost always polygenic–not coded for by one gene. Genes affect behavior indirectly.
Personality traits and mental disorders are not affected by chromosomal abnormalities per se, but more often influenced either by abnormalities in some of the genes on the chromosomes or by naturally occurring variations of genes known as polymorphisms
•Genotype: Total genetic endowment. What is inherited
Phenotype: Observed structural and functional characteristics. What is expressed (interaction between genes and environment)
Genotype–Environment Interactions
•Genetic factors can contribute to a vulnerability or diathesis to develop psychopathology
•PKU-induced intellectual disability
•Genetic risk for depression
Individual’s genotype may shape environment in the following ways:
Passive effect: Resulting from the genetic similarity of parents and children
Evocative effect: Child’s phenotype may evoke particular kinds of reactions from social and physical environment
Active effect: Child seeks out or builds environment that is congenial; “niche building”
Methods for Studying Genetic Influences
•Behavioral geneticists use 3 traditional methods:
•Family history (pedigree): Observe samples of relatives of each proband or index case & compare incidence rate in family to rate in population
•Twin method: Compare rates of disorders in identical twins to rates in nonidentical twins, expecting higher concordance rate for identical twins
•Adoption method: Compare adopted offspring with normal biological parents to offspring with biological parents with disorder
Shared environmental influences are those that would make children in a family more similar, whether the influence occurs within the family or in the environment
Nonshared environmental influences are those in which the children in a family differ, such as experiences at school and also some unique features of upbringing in the home, such as a parent treating one child in a qualitatively different way from another
More modern methods:
•Association studies: Compare frequencies in population with and without disorder and compare frequencies of traits with known genetic markers.
•Linkage analysis: See if family members with disorder share commonality of a trait with known genetic marker. Infer gene location for disorder. Best for locating single-gene disorders such as Huntington’s
Imbalances of Neurotransmitter Systems
•Neurotransmitter imbalances
•Can result in abnormal behavior
•Created in various ways:
•Excessive production and/or release of neurotransmitter into synapse
•Dysfunction in deactivation of neurotransmitter in synapse
•Receptors may be abnormally sensitive or insensitive
•Hormones: Chemical messengers secreted by a set of endocrine glands in our bodies
•Can affect risk of depression and PTSD; sex hormone imbalances can also cause problems
•5 most studied neuro-transmitters
•Norepinephrine
•Dopamine
•Serotonin
•Glutamate
•Gamma aminobutyric acid (GABA)
Hormonal Imbalance
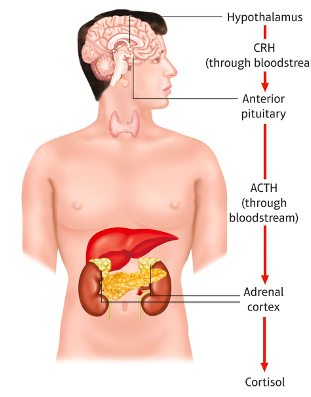
•Hypothalamic-pituitary-adrenal (HPA) axis
•Messages (CRH) travel from the ypothalamus to the pituitary
•Pituitary releases ACTH, which stimulates cortical part of the adrenal gland, produces epinephrine (adrenaline) and cortisol
•Cortisol provides negative feedback to hypothalamus and pituitary to decrease their release of CRH and ACTH, which in turn reduces the release of adrenaline and cortisol
Some forms of psychopathology have also been linked to hormonal imbalances.
Major glands of the endocrine system:
Negative feedback loop once cortisol is produced by the adrenal gland. Cortisol tells hypothalamus to stop producing CRH and ACTH, which in turn reduces the release of cortisol and adrenaline.
When negative feedback system malfunctions, there is an increased risk for depression and PTSD.
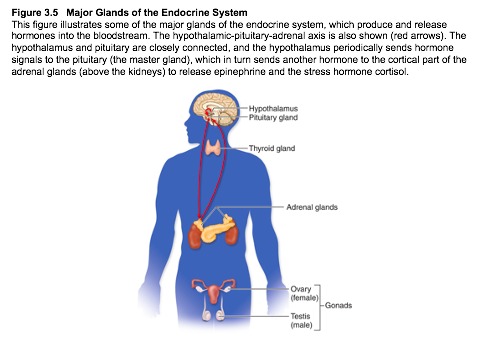
Temperament
Child’s reactivity and characteristic ways of self-regulation
Early temperament is basis from which personality develops
Babies show differences in their characteristic emotional and arousal responses to various stimuli and in their tendency to approach, withdraw, or attend to various situations
Some parts of temperament stable at least through middle childhood
Five Dimensions of Temperament
•Fearfulness
•Irritability and frustration
•Positive affect
•Activity level
•Attentional persistence and effortful control
Related to three dimensions of adult personality:
neuroticism (fearfulness and irritability)
extraversion (positive affect and activity level)
constraint (attentional persistence and effortful control)
These may be related to psychopathology later on in life
Impact of Biological Viewpoint
•Importance of biochemical factors and innate characteristics in both normal and abnormal behavior.
•Effects of psychological events are always mediated through CNS
•Require multiple perspectives to fully understand abnormal (and normal) behavior
The Psychological Perspectiv
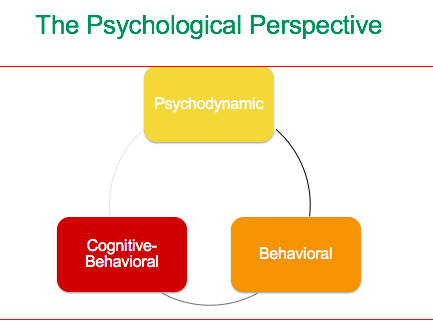
The Psychodynamic Perspective
•Freud theorized that a person’s behavior results from interaction of:
The id: Source of instinctual drives; operates on pleasure principle
The ego: Mediates between demands of id and realities of external world; operates on reality principle
The superego: Outgrowth of internalizing taboos and moral values of society; conscience
The concept of anxiety is prominent in the psychoanalytic viewpoint
Ego often deals with neurotic or moral anxiety by resorting to ego-defense mechanisms such as:
Displacement, fixation, projection, rationalization, reaction formation, regression, repression, and sublimation
Discharge or soothe anxiety by pushing painful thoughts out of consciousness

Psychosexual Stages of Development
•Freud conceptualized five psychosexual stages of development
•Oral stage (ages 0 to 2)
•Anal stage (ages 2 to 3)
•Phallic stage (ages 3 to 5 or 6)
•Latency period (ages 6 to 12)
•Genital stage (after puberty)
Each stage is characterized by a dominant mode of achieving libidinal (sexual) pleasure
Appropriate gratification during each stage is important if a person is to avoid being stuck, or fixated.
The Oedipus Complex and the Electra Complex
A child with Oedipus complex symbolically relives Oedipus drama
Castration anxiety
The Electra complex is female counterpart of Oedipus complex
•Penis envy
This perspective thus presents a deterministic view of human behavior that minimizes rationality and freedom of self-determination.
On a group level, it interprets violence, war, and related phenomena as the inevitable products of the aggressive and destructive instincts present in human nature.
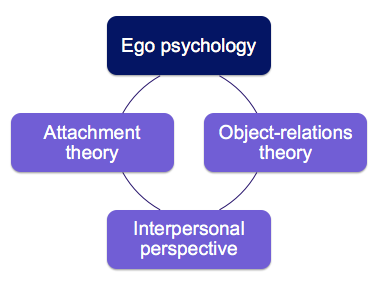
Newer Psychodynamic Perspectives
•Ego: Psychopathology develops when the ego does not function adequately to control or delay impulse gratification or does not make adequate use of defense mechanisms when faced with internal conflicts.
•Object-relations: Focus on individuals’ interactions with real and imagined other people (external and internal objects) and on the relationships that people experience between their external and internal objects
•Interpersonal: Emphasis on social and cultural determinants of behavior
•Attachment: Emphasizes early experiences with attachment figures as determinant of behavior in adolescence and adulthood
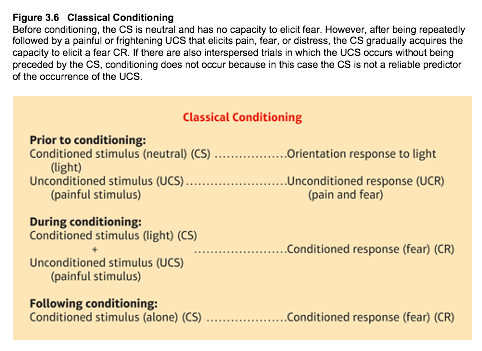
Classical Conditioning
•Specific stimulus may come to elicit specific response through process of classical conditioning.
•A formerly neutral stimulus—the CS—acquires the capacity to elicit biologically adaptive responses through repeated pairings with the UCS
•If conditioned stimulus is repeatedly presented without unconditioned stimulus, extinction will occur
Operant Conditioning
Operant (instrumental) conditioning: New responses are learned and tend to reoccur if they are reinforced
Generalization and Discrimination
The concepts of generalization and discrimination have many implications for the development of maladaptive behavior.
Although generalization enables us to use past experiences in sizing up new situations, the possibility of making inappropriate generalizations always exists.
Generalization: Response is conditioned to one stimulus and can be evoked by other similar stimuli
Discrimination: Learning to distinguish between similar stimuli
Observational Learning
Learning through observation alone
Without directly experiencing an unconditioned stimulus
Impact of the Behavioral Perspective
The focus of therapy is on changing specific behaviors and emotional responses—eliminating undesirable reactions and learning desirable ones.
The behavioral approach is well known for its precision and objectivity, for its wealth of research, and for its demonstrated effectiveness in changing specific behaviors.
•Maladaptive behavior
•Failure to learn necessary adaptive behaviors or competencies
•The learning of ineffective or maladaptive responses
The Cognitive-Behavioral Perspective
•Focuses on how thoughts and information processing become distorted
•Leads to maladaptive emotions and behavior
Albert Bandura
Developed an early version: human beings regulate behavior by internal symbolic processes—thoughts.
That is, we learn by internal reinforcement.
Bandura argued that human beings have “a capacity for self-direction” and later developed a theory of self-efficacy, the belief that one can achieve desired goals
People develop different schemas based on their temperament, abilities, and experiences.
People develop different schemas based on their temperament, abilities, and experiences.
Self-schemas include our views on who we are, what we might become, what is important to us, and our notions of the various roles we occupy or might occupy in our social environment such as “woman,” “man,” “student.”
Most people have clear ideas about at least some of their own personal attributes and less clear ideas about other attributes
Schemas may be distorted and people may hold on to them strongly making them resistant to change. Can lead to psychopathology
Cognitive-behavioral clinicians attempt to alter their patients’ maladaptive cognitions
Way we interpret events determines our emotional reactions to them
Schema:
•Underlying representation of knowledge that guides current processing of information
Attributions:
•Process of assigning causes to things that happen
Attributional Style:
•Characteristic way in which individual may tend to assign causes to bad or good events
Cognitive therapy:
•The way we interpret events and experiences determines our emotional reactions to them
•Clinicians use a variety of techniques designed to alter a client’s negative cognitive biases
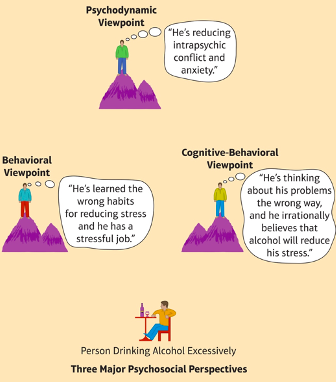
What the Adoption of a Perspective Does Do
•All perspectives contribute to an understanding of psychopathology, but none can provide a complete explanation!
What the Adoption of a Perspective Does Not Do
•Perception of maladaptive behavior
•Types of evidence sought
•Data interpretation
The Social Perspective
•Factors with detrimental effects on a child’s socioemotional development
•Early deprivation or trauma
•Depriving essential resources
such as food, shelter, love, and attention can cause irreversible psychological scars
•Institutionalization
can lack physical contact and social stimulation; e.g., Romanian orphans
•Neglect and abuse at home
is alarmingly common and results in negative effects
•Separation from parents
can be traumatic
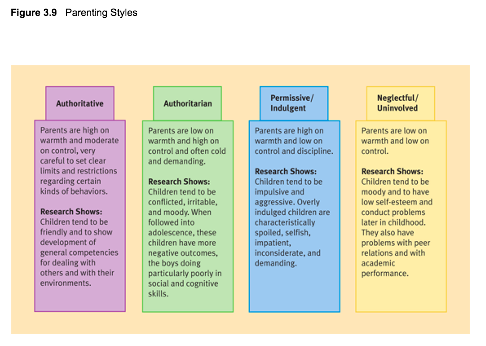
•Problems in parenting style
A parent–child relationship is always bidirectional: the behavior of each person affects the behavior of the other
Parents who have various forms of psychopathology tend to have one or more children at heightened risk for a wide range of developmental difficulties.
A parenting style reflects an attitude and values that are expressed toward a child across a wide range of settings
•Marital discord & divorce
•Long-standing marital discord
Is damaging in its effects on both adults and children; children can learn negative interaction styles which will influence their own adult relationships
Divorce
Divorce can cause negative effects in children, but many adjust quite well. Effects of divorce can be more favorable than staying in discordant home
•Low socio-economic status & unemployment
In the U.S., the lower the socioeconomic class, the higher the incidence of mental disorders
Especially true for certain disorders, such as antisocial personality disorder
Reasons may include greater stressors, fewer resources for help
Unemployment is linked with higher vulnerability to psychopathology
Economic crises since 1990 have centered on the effects that corporate restructuring and downsizing have had on upper middle-class people, many of whom find themselves having to look for jobs requiring lower skills and paying much lower incomes than they earned in the past.
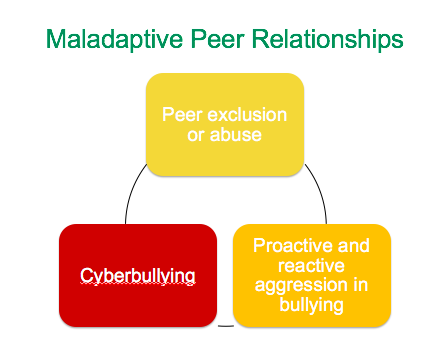
•Maladaptive peer relationships
Exclusion or abuse by peers can lead to poor school performance or to avoiding school entirely
Bullies are high in both proactive and reactive aggression
Cyberbullying is a new form of bullying that can have serious effects
Good peer relationships in children can lead to social competence and preparation for real world of adulthood
•Sources of popularity
•Prosocial
Antisocial
•Sources of rejection
•Too aggressive
•Too withdrawn
Peer social problems may reflect some heritable diathesis, but they also serve as stressors that make it more likely that the underlying vulnerability will lead to full-blown disorder later.
•Prejudice & discrimination
•Increased prevalence of certain mental disorders may be related to:
•Prejudice against minority groups and women
may explain why some groups show increased prevalence of certain mental disorders
•Perceived discrimination and self-esteem
The Impact of the Social Perspective
•How environmental factors can influence the occurrence of mental disorders
•Programs to improve social conditions
•Community facilities for the early detection, treatment, and long-range prevention
The Cultural Perspective
The cultural perspective is concerned with the impact of culture on the definition and manifestation of mental disorders
•Cultural context of behavior
•Ideas about normal and abnormal differ in different places around the world.
•Individual personality development reflects the larger society
Universal and Culture-Specific Symptoms of Disorders
•Universality of some disorders
•Certain psychological symptoms are consistently found among similarly diagnosed clinical groups
•Many disorders are fairly universal
–Schizophrenia, for example
•Sociocultural factors
•Which disorders develop
•Prevalance can vary widely across cultures
–Major depressive disorder, for example
Norms for control over one’s own behavior, as well as parent-child attachment, vary widely across cultures
Culture and Over- and Undercontrolled Behavior
•Undercontrolled behavior
•Agression, disobedience, disrespect
•Less tolerated by some cultures (Thai)
•Overcontrolled behavior
•Shyness, anxiety, depression
•Less tolerated by some cultures (U.S.)
Social Change and Uncertainty
•Rate and pervasiveness of change
•Change and stress
•National and global crises and predisposition to mental illness
Unresolved Issues
•None of the current theories address whole spectrum of abnormality
•Eclectic approach not successful at theoretical level
•Biopsychosocial perspective only current attempt at unified approach
Página 3
Week 3
Factors that predispose an individual to a negative response to stress
Age differences
Psych characteristics
Higher optimism
Self esteem
Self-efficacy/control/mastery
Perceived social support minimises –ve response
Genetic factors
Amount of stress:
Cumulative
Self-perpetuating cycle
Cognitions
Stressors
Severity (importance of the event)
Chronicity (how long it lasts)
Timing (how many at the same time?)
Closeness to the event (child fails exams vs third cousin never met)
Expected (not predicted is worse)Controllable (uncontrollable worse)
Resilience
The capacity to recover from adversity
Relatively new way of examining the stress area
Predicted by demographic & psych factors
Article: Development of a multi-dimensional measure of resilience in adolescents: the Adolescent Resilience Questionnaire
Stress and Physical Health
Stress can lead to physical outcomes & physical problems can exacerbate stress: Bidirectional
Stress response:
SMA system: mobilise resources to ‘fight’ stressor. Stimulates CNS to secrete adrenaline and nor-adrenaline = ↑ HR
HPA system: release cortisol-> inhibits immune response
Read text book for the impacts of stress on the physical body
Emotions and health
Personality:
Type A personality (heart)
Type D (heart)
Type C (cancer)
Depression: immune function, heart disease
Anxiety: heart disease, neurological
Low Social Support/loneliness: heart disease
Positive emotions= post health
Treatment of stress-related disorders
Biological: for the physical prob; to help the psych prob (e.g. SSRIs)
Psychological: effective emotional regulation; emotional disclosure, biofeedback; relaxation; CBT
Stress & Mental Health
Adjustment disorder:
Psychological response to common stressor resulting in clinically significant behavioural or emotional symptoms.
PTSD:
A normal response to abnormal stressor, but symptoms do not abate with time and when the danger is over. Causes extreme stress. Symptoms must last at least one month.
PTSD Symptom categories: Intrusion; Avoidance; Negative alterations to cognitions and mood; Arousal and reactivity.
Acute Stress Disorder:
When symptoms develop shortly after a traumatic event and last at least two days. These people are at risk of PTSD
PTSD
Risk Factors
Gender: being female
Higher neuroticism
Pre-existing depression and/or anxiety
Familial depression, anxiety, substance abuse
Low social support
Shame
Protective Factors
Protective factors
Good cog ability / high IQ
Higher Cortisol levels? Exaggerated cortisol response; PTSD women have higher baseline cortisol; may vary due to type of trauma
Gene/environment interaction
Brain differences: hippocampus smaller if have PTSD (direction?)
Socio-Cultural
Member of a minority group
Having a non-supportive home environment
Poverty
Others
Long term effects
Survivor guilt (holocaust)
Can become chronic
Preventative
Reduce traumatic events (government policy; sex abuse e.g.)
Prepare people?
Improve coping skills
CBT : Inoculation training- what to say to self during trauma; paramedics
Treatment
Telephone hotlines (lifeline; beyondblue)
Crisis intervention
Psych debrief
Medication
CBT
Relaxation training
Stress
Behavioural medicine
•Concerned with psychological factors that may predispose an individual to medical problems
•Health psychology
•The effects of stress and other psychological factors in the development and maintenance of physical problems
•External demands placed on an organism
•Organism’s internal biological and psychological responses to such demands
Stress and DSM
•Significant component of multiple DSM diagnostic categories
•DSM-5: Trauma- and stressor-related disorders
Predisposing factors
•Nature of stressor
Crises are especially stressful because the stressors are so potent that typical coping techniques are overwhelmed
Life changes, positive or negative, can increase stress
Perceiving benefit from a disaster, such as personal growth, can lessen the experience of stress
•Experience of crisis
•Life changes
•Individual perception of stressor
•Individual stress tolerance
•Lack of external resources and social supports
Stressors:
Key factors
•Severity
•Chronicity
•Timing
•Degree of impact
•Level of expectation
•Controllability
Measuring Life Stress
Social Readjustment Rating Scale
•Self-report checklist
•Limited
Life Events and Difficulties Schedule
•Interview-based
•Rates chronic and acute stress
Resilience
Resilience is a healthy psychological and physical functioning after a potentially traumatic event
Factors:
•Male gender
•Older age
•Higher education
•Economic resources
•Positive life outlook
•Self confidence
Stress and Physical Help
•Allostatic load: Biological cost of adapting to stress
•High load = more stress
•Everyday forms of stress can also elevate risk for heart disease and death
•Mental stress raises blood pressure and elevates epinephrine levels
Stress response
•Sympathetic-adrenomedullary (SAM) system
Prepares fight-or-flight response
•Hypothalamus-pituitary-adrenal (HPA) system
Prolonged stress leads to secretion of the adrenal hormone cortisol, which elevates blood sugar and increases metabolism. These changes help the body sustain prolonged activity but at the expense of decreased immune system activity.
If the cortisol response is not shut off, cortisol can damage brain cells, especially in the hippocampus
Psychoneuroimmunology - the mind- body connection
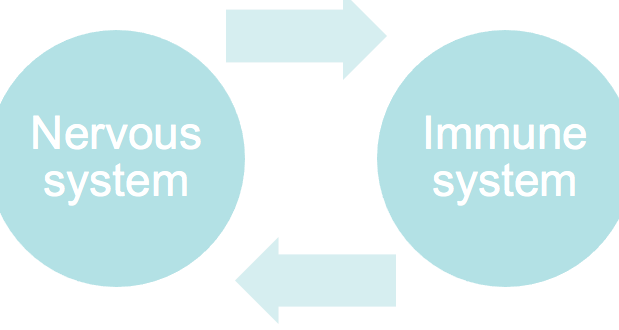
Evidence continues to grow that the brain influences the immune system and that the immune system influences the brain.
A person’s behavior and psychological state can affect immune functioning.
Example: Glucocorticoids can cause stress-induced immunosuppression. In the short term, this can be adaptive (escape first, heal later). However, it makes sense that longer-term stress might create problems for the immune system. why this might be, we need to describe briefly the basics of immune functioning.
Understanding the Immune System
Immune System
•Protects body from such things as viruses and bacteria
•Provides leukocytes: front lines of defense
•Communicates with brain via cytokines
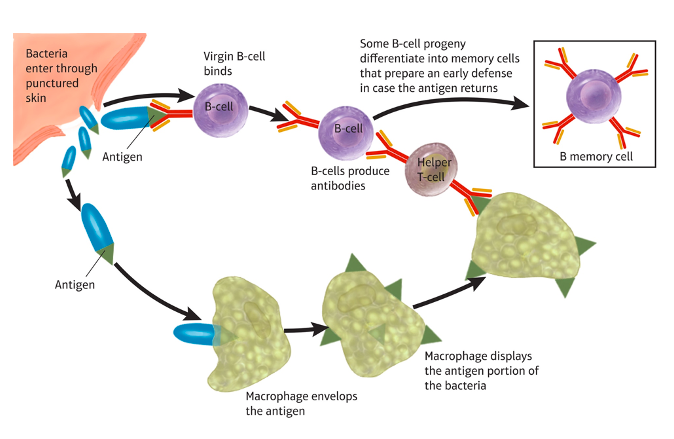
B-cells: produce antibodies to specific antigens (foreign invaders, tumors, cancer cells)
T-cells: Helper cells. Help destroy antigens after activation from a macrophage that releases interleukin-1
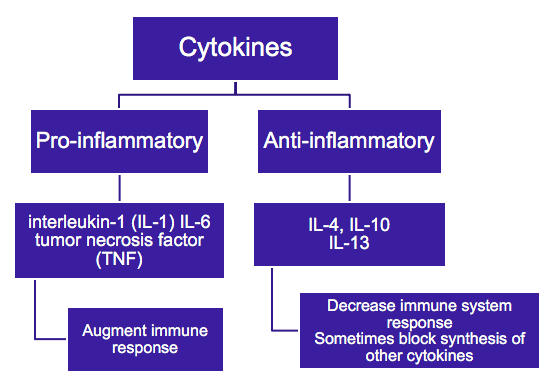
Cytokines mediate inflammatory and immune response and send signals to the brain about infection and injury. Also stimulate the HPA axis which creates a negative feedback loop.
Immune System Responses to a Bacterial Infection
(Adapted from J. W. Kalat, 2001, Biological Psychology, 7th ed. Belmont, CA: Wadsworth.) [Below]
Stress and Immune System Functioning
•Stress is linked to immune system suppression
•Short-term stress compromises immune system
•Long-term stress associated with global immunosuppression
Stress and Cytokines
Cytokines serve as chemical messengers and allow immune cells to communicate with each other
Cytokines influence the brain
The close communication between the brain and the immune system also means that the brain is capable of influencing immune processes
Chronic problems at the level of the immune system may lead to behavioral changes or even to psychiatric problems
Under conditions of stress, the production of proinflammatory cytokines is disrupted
Chronic Stress and Inflammation
•Longterm stress
•Body cannot turn off cytokine production
•Chronic inflammation
Chronic inflammation is a risk factor for a wide range of health problems and diseases, including cardiovascular disease, type 2 diabetes, asthma, osteoporosis, rheumatoid arthritis, and many others
Stress and premature aging
•Stress
•Shortens telomere length
•Shorter telomeres affect cell function, increase disease risk
Traumatic stressors that are experienced during childhood seem to increase risk of premature death in later life.
Unchecked stress can compromise the immune system, create conditions of chronic inflammation, and shorten the length of our telomeres
We are also learning that drinking too much sugar sweetened soda might shorten telomeres
Telomeres
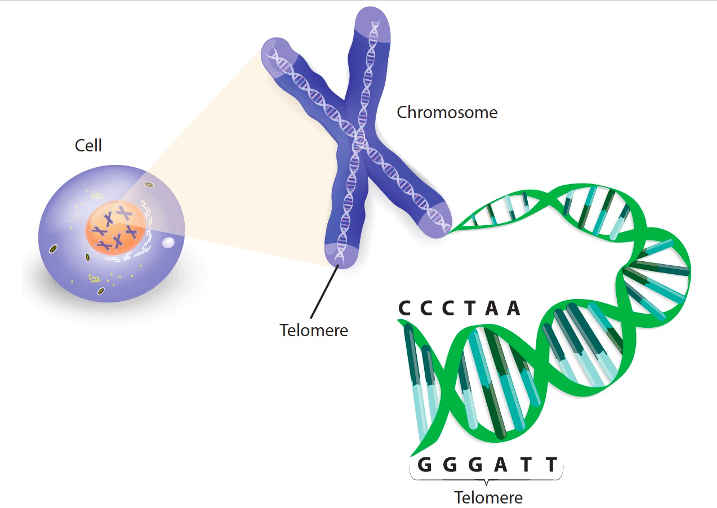
Telomeres are the protective end parts of chromosomes. Telomeres shorten with age, increasing the risk of disease. Stress also shortens telomeres. Telomere length is maintained by an enzyme called telomerase and the activity of telomerase is reduced by the stress hormone cortisol. If you needed a reason to reduce the amount of stress in your life, you have a good one now!
Emotions and Health
Certain personality types are linked
Type A:
Type A behavior is characterized by excessive competitive drive, extreme commitment to work, impatience or time urgency, and hostility.
Framingham Heart Study confirmed and earlier study that Type A personality in otherwise healthy men ages 35 to 59 was associated with a twofold increased risk for coronary artery disease and an eightfold increased risk of having a heart attack over the course of an 8.5-year, and extended the findings to women, too
Type D:
Distressed; tendency to experience negative emotions and also to feel insecure and anxious
Depression
•Associated with disrupted immune function beyond stressors that precipitated depression
This is especially true when the depression is chronic
People with heart disease are approximately three times more likely than healthy people to be depressed
Depression also appears to be a risk factor for the development of CHD
New findings also suggest that people who are depressed have shorter telomeres
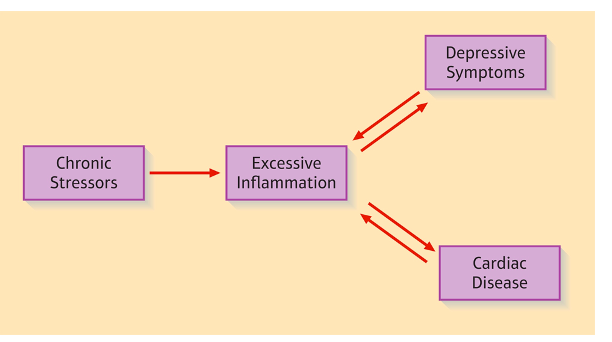
Figure 5.7 Stress, Inflammation, Depression, and Heart Disease
Model of how inflammatory processes mediate the relations among chronic stressors, depressive symptoms, and cardiac disease. Stressors activate the immune system in a way that leads to persistent inflammation. With long-term exposure to the molecular products of inflammation, people are expected to develop symptoms of depression and experience progression of cardiac disease.
(Adapted from Miller & Blackwell, 2006. Turning up the heat: Inflammation as a mechanism linking chronic stress, depression and heart disease. Current Directions in Psychological Science, 15(6), 269–272(4). Copyright © 2006. Reproduced with permission of Blackwell Publishing Ltd.)
Emotions and health
•Anxiety
•Phobic anxiety is linked to increased risk for sudden cardiac death
•Positive emotions
•Forgiveness may lower stress levels
•Social isolation and lack of social support
•Lonely people at increased risk of developing heart disease
•Emotion regulation
•Psychological well-being
•Physical health
Treatment of Stress-Related Physical Disorders
•Biological interventions
•Psychological interventions
Biological interventions
•Surgical procedures
•Lipid-lowering medications
•Aspirin or other anticoagulants
•Antidepressant medications
Psychological Interventions
•Emotional disclosure
•Biofeedback
•Relaxation and meditation
•Cognitive-behavior therapy
Stress and mental health
•Some DSM disorders are triggered by exposure to stress
•Adjustment disorder
•Psychological response to common stressor
•Occurs within 3 months of stressor
•Symptoms disappear when stressor ends or person adapts
•Often caused by unemployment
Acute Stress Disorder
Diagnostic category for use when symptoms develop shortly after traumatic event and last for at least 2 days
•People can receive treatment immediately
•Diagnosis can change to PTSD if symptoms persist
•Posttraumatic stress disorder
•DSM classification
•Trauma and stressor-related disorder
•Examples of Causes
•Combat, rape, concentration camp, natural disaster
•Clinical description
•Trauma memory reexperienced involuntarily, with same emotional force
•Symptoms last for at least 1 month
Causes and factors:
Symptoms
•Intrusion
•nightmares, intrusive images, physiological reactivity to trauma reminders
•Avoidance
•efforts to avoid thoughts, feelings, or reminders of trauma
•Negative alterations in cognitions and mood
•detachment, shame, anger, distorted blame self/others
•Arousal and reactivity
•hypervigilance, excessive response when startled, aggression, reckless behavior
Prevalence of PTSD in General Population
•Lifetime prevalence rate in the U.S. is 6.8%
In women, 9.7%
In men, 3.6%
Some have suggested that the gender difference reflects the fact that women are more likely to be exposed to certain kinds of traumatic experiences, such as rape, that may be inherently more traumatic
However, even when the type of traumatic event is controlled for, women still show higher rates of PTSD and tend to have more severe symptoms (Tolin & Foa, 2006). This suggests that there are differences between men and women that may determine their risk of developing PTSD after experiencing trauma
Rates of PTSD after a traumatic event
Rates of PTSD throughout the world tend to be lower in areas where people experience fewer natural disasters and where wars and organized violence are less common.
Traumatic events that result from human intent (ex. rape) are more likely to cause PTSD than are traumatic events (such as accidents and natural disasters) that are not personal in nature
Military combat can be especially traumatic
Creation of the PTSD diagnostic category was stimulated by combat experience
Prisoner of war, concentration camp, and torture experience are all recognized traumas that can lead to PTSD
A recent meta-analysis has reported rates of PTSD of 12.9 percent in military personnel following deployment to Iraq and a rate of 7.1 percent for those who served in Afghanistan
Causal Factors in Posttraumatic Stress Disorder
•Individual risk factors
•Biological factors
•Sociocultural factors
Individual risk factors
Risk factors for exposure to trauma: occupation, male gender, lack of college education, family history of psychiatric disorder, and scoring high on measures of extraversion and neuroticism, being black
Risk factors for developing PTSD: Being female, higher levels of neuroticism (negative affect), preexisting problems with depression and anxiety, family history of depression, anxiety, and substance abuse, low levels of social support
New evidence suggests that people who have disturbing thoughts or images about traumatic events that could happen in the future may be at elevated risk of developing PTSD later
Protection against PTSD: higher pretrauma cognitive abilities
Biological factors
•Gender
•Higher cortisol levels in females
•Genetics
•5HTTLPR gene
•Reduced size of hippocampus
•Brain site related to memory & stress response
Socio-cultural Factors
Higher risk for PTSD
•Membership in minority group
•Returning to negative and unsupportive social environment
In combat related trauma
•Justification for combat
•Identification with combat unit
Prevention and Stress Disorders
•Prevention and treatment of stress disorders
•Advanced preparation of stressor (Inoculation training)
•Military service
•Medical procedures
•Relationship termination
•Psychological debriefing
•Challenges in studying crisis victims
•Trauma and physical health
•Approaches to treatment include:
•Telephone hotlines
•Crisis intervention
•Psychological debriefing
Are designed to help and speed up the healing process in people who have experienced disasters or been exposed to other traumatic situations
Critical Incident Stress Debriefing (CISD) lasts between 3 and 4 hours and is conducted in a group format, usually 2 to 10 days after a “critical incident” or trauma
Although those who experience the debriefing sessions often report satisfaction with the procedure and with the organization’s desire to provide assistance, no well-controlled study has shown that it reduces symptoms of PTSD or hastens recovery in civilians
•Medications
Include antidepressants and antipsychotics, but evidence for the effectiveness many of these medications is slim
•Cognitive-behavioral treatments
Include prolonged exposure, which is effective for PTSD
Trauma and physical health
Traumatic events are not only bad for the mind, they also damage the body.
Findings again highlight the role that stress and trauma play in both physical health and psychological well-being
Unresolved issues
•Individual risk factors for PTSD was a taboo topic for many years
•Viewed as blaming the victim
•Advocacy a higher priority than science
•Scientists are still subjected to attacks when they present unwanted findings
Información
- Descripción
- 30010PSY Abnormal Psych Apunte sobre Notes, creado por Juliette Cross el 05/09/2020.
- Creado por
- Juliette Cross
- Visitas
- 4
- Valoración