
Diabetes
Diapositivas del conjunto (28)
-
- 100 amputations a week on patients with diabetes
- 3.8m Britons have diabetes
- 600,000 of people don't know they have the disease
- 24,000 diabetic die early each year
- Chronic metabolic disease caused by insulin deficiency - the pancreas does not produce enough insulin to maintain a normal blood glucose level
- OR
- Reduced effectiveness- insulin that is produced does not work correctly suggesting a defect of insulin action at the receptor, this is known as insulin resistance.
- OR
- BOTH
-
-
- CLINICAL FEATURES
- Characterised by a raised blood glucose concentration
- Presents with acute symptoms and severe multisystem chronic complications
- Age of diagnosis >40 and onset is low
- Increased weight
- The endogenous insulin is present but insuffienct/ inefficient
- SCREENING IN THE COMMUNITY
- NHS health check - aged 40 - 7
- If exhibit symptoms of diabetes
- If have multiple risk factors - overweight, family history, ethnicity
-
- RISK FACTORS
- Age - being over 40 (over 25 for south Asian). This may be because people tend to gain weight and exercise less as they get older.
- Genetics- first degree relative with the T2D. Parent with T2D increases risk to 1 in 3.
- Weight- overweight/obese. Abdomen fat increases risk because chemicals are released with can disrupt the body's cardiovascular and metabolic systems. This increases the risk of CVD and stroke.
- Ethnicity - South Asian (x6 more common), Chinese, African-Caribbean and Black African (x3 more common).
- CAUSE
- Impaired insulin secretion from pancreas and insulin resistance.
- There is a strong genetic component involved more than Type I, so there is a probability of inheriting Type II. A missense mutation is the glucagon gene has been shown to be associated with the development of type II.
- Environmental - lifestyle; excessive calorie intake and inadequate calorie expenditure, high sugar diet.
-
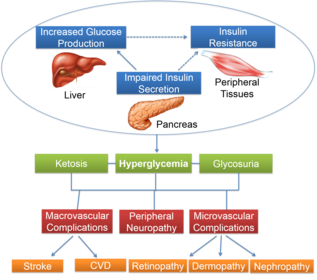
- As tissues are not taking up the insulin, the liver continues to produce and secrete glucose → hyperglycemia and glycosuria. Glycosuria occurs because the filtered glucose exceeds the renal threshold → glucose appears in the urine and acts as an osmotic diuretic → frequent urinations and excessive thirst which are the most common symptoms → over time the hyperglycemia damages the blood vessels → macro/microvascualr complications.
- The main cause of morbidity and mortality in diabetes in the poorly controlled hyperglycemia over a period of years. The damage is irreversible.
-
- Macrovascular Complications
- Macroangiopathy - large vessel disease which leads to accelerated atherosclerosis. Increases the risk of:
- IHD ( Angina/MI)
- Stroke
- CVD - 8/10 people with T2D die from CV events.
- Hypertension
- Peripheral vascular disease (PVD) - pain in legs and arms due to poor perfusion, skin ulcers and amputations
- Atherosclerosis also increases susceptibility to infection
- Microvascular Complications
- Microangiopthay - disease of fine capillary damage. This occurs due to protein glycation and small osmotic damage in small blood vessels.
- Retinopathy - can cause blindness, cataracts, glaucoma.
- Nephropathy - result in renal failure
- Neuropathy - damage to nerves
- Sensory: numbness, tingling and neuropathic pain. Autonomic: impotence, GI disturbance, postural hypotension. Damage to sympathetic/parasympathetic nerves may result in loss of normal cardiovascular reflexes.
-
- CHRONIC
- 'Diabetic Foot' - caused by PVD, neuropathy, increased susceptibility to infection.
- The peripheral nervous tissue becomes progressively damaged, → pain → eventual numbness in the feet →Can result in amputation.
- ACUTE
- Hyperosmolar Hyperglycemic State (HHS) - due to high glucose → dehydration and high osmolarity. Treated with sliding scale insulin and IV saline.
- Diabetic ketoacidosis - state of uncontrolled catabolism associated with insulin deficiency(usually Type 1). Breakdown of fatty acids → which ↑ ketone bodies → ↓ plasma pH. Treated with sliding scale insulin, IV saline and potassium. (as there will be electrolyte imbalances.
- Hypoglycaemia - symptomatic if glucose <202mmol/L. Treat onsite with 2 teaspoons of sugar/equivalent and hospital IM Glucagon (will ↑ conc. of glucose)
-
- SYMPTOMS
- Fatigue
- Polydipsia
- Frequent urination - especially at night
- Genital itching or thrush
- Always hungry
- Blurred vision
- Sudden weight loss
- Wounds taking longer to heal
-
- Symptoms
- Urine sample - detection of glucose
- HbA1c - gives the average blood glucose levels over the previous 2-3months.
- Glucose Tolerance Test (GTT) - 75g glucose in water. Blood glucose before and 2 hours after the glucose has been given. Fasting plasma glucose ≥7.0mmol/L
- Random plasma glucose ≥ 11.1mmol/L
- Blood pressure
- Blood lipids
- Family history
-
National Service Framework (NSF)
- The NSF for Diabetes sets quality standards for diabetes care. The standards aim to improve care for people with diabetes. There are 12 standards.
- Standard 4:
- Improve blood glucose control - drug choice/monitoring
- Control hypertension - reduce CVD/retinopathy/nephropathy
- Reduce raised cholesterol levels - give statin + aspirin (secondary prevention)
- Encourage smoking cessation - NRT
-
- Diet Alone
- Diet + oral antidiabetic drugs
- Diet + oral antidiabetic drugs + Insulin
- AIMS
- Avoid hypo and hyper
- Maintain normal body weight
- Reduce risk of CVD
- Overall health through good nutrition
-
- STRATEGIES
- Refer to dietician
- Aim for realist BMI
- portion and proportion control
- Eat smaller, more frequent meals
- Vary content
- Adjust for any unusual activity
- DIET
- Carbohydrate - 50-60% calories. Low glycaemic index foods such as fibre (slow absorption of sugar), complex carbohydrates (polysaccharides) - pasta, potatoes, rice. Small amount of sugar allowed.
- Fat - low fat diet. <35% energy from fat. More polyunsaturated fats and low cholesterol.
- 5 Portions of fruit and veg
- Reduce salt intake
- Alcohol - ok in moderation. BUT blood glucose will ↑ and then ↓↓. Best with food and count the calories.
-
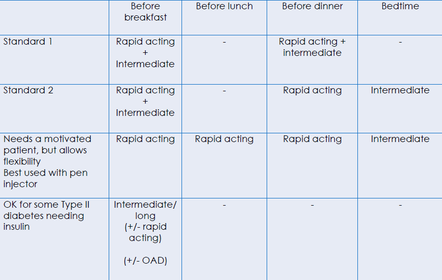
- Porcine, Bovine, Human sequence insulin, recombinant human insulin
- Route - SC, IM, IV
- T2D - when other methods have failed to achieve good control.
- Temporarily in the presence of intercurrent illness or peri-operatively
- Insulin Pump - The insulin is houses inside the pump in a cartridge called a reservoir. The insulin travels into your body through a flexible tube that ends with a cannula inserted just under the skin.
- Dosage - tailor to the individual depending on motivation, comprehension, lifestyle and pattern of eating and activity.
- Aim- to keep blood glucose 4-10mmol/L and HbA1c <7.5%
- Patients can self-monitor and fine tune dose themselves.
- AE's - weigh gain, hypo, resistance, allergy, lipoatrophy/lipohypertrophy at injection site - rotate injection site.
- Rapid acting -Lispro (Humalog), Asparte (Novarapid) - works within in 15 mins. peaks 30-90misn and can last 4 hours.
- Short- acting - regular insulin. works within 30 mins. peaks 2-4hours and last 4-8 hours
- Intermediate -Isophane/NPH, Humulin I. usually taken with short acting. work within 1 hour, peak up to 7 hours, and lasts 18-24 hour.
- Long acting- Ultralente, Glargine (Lantus), Determir (Levermir) . works within 6-14 hours, peaks at 10-16hrs and last 20-24hrs.
-
- Insulin absorption - to be aware of the factors influencing insulin absorption which can have an effect on blood glucose control
- Injection site - to ensure that the appropriate sites are used for injecting insulin
- Injection technique - to ensure that insulin is injected correctly
- Injection site rotation - to prevent lipohypertrophy
- Timing of injection - to optimize glycemic control
- Self-injecting - support parents and young children using self-injecting insulin
-
-
- Initial drug treatment-
- Treatment with a single non‑insulin blood glucose lowering therapy (monotherapy)
- Metformin OR if contra - DPP-4 Inhibitor or Pioglitazone or Sulfonylurea
- First intensification of drug treatment -
- Treatment with 2 non‑insulin blood glucose lowering therapies in combination (dual therapy)
- Metformin + DPP-Inhibitor/Pioglitazone/Sulfonylurea OR if contra - DPP-4 + Pioglitazone/Sulfonylurea or Pioglitazone + Sulfonylurea
- Second intensification of drug treatment -
- Treatment with either 3 non‑insulin blood glucose lowering therapies in combination (triple therapy) or any treatment combination containing insulin
- Metformin + DPP-4 Inhibitor + sulfonylurea or Metformin + Pioglitazone + Sulfonylurea
- + Insulin
-
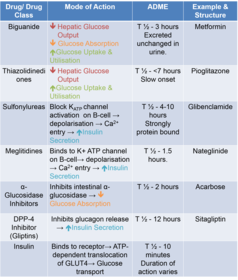
- Pie de imagen: Drug treatment if diabetes is not controlled by diet alone for 3 months
- Insulin sensitizers - bigunaide, glitazones
- Insulin secretogogues - sulphonylureas, meglitinides, DPP-4 inhibitors (gliptins)
- GI glucose absorption inhibitor - acarbose
-
Pharmacology and Pharmacokinetics
- BIGUANIDE (METFORMIN)
- ↓ gluconeogenesis
- ↑ peripheral utilisation of glucose
- First line treatment in obese patients as it does not increase appetite
- AE's- anorexia, N&V&D
- SULPHONYLUREAS
- ↑ Insulin secretion
- For patients who metformin is contra
- Common AE- hype
- long acting - glibenclamide - greater risk of hypo
- short acting - gliclazide, tolbutamide
- ALPHA- GLUCOSIDASE INHIBITORS (ACARBOSE)
- Inhibits intestinal glucosidase, impairing carb digestion and glucose absorption
- Small but significant effect in lowering blood glucose
- AE- GI effects; flatulence, bloating and D.
- THIAZOLIDINEDIONES (PIOGLITAZONE)
- Enhance insulin receptor sensitivity → ↓ peripheral insulin resistance
- Used alone or in combo
- Small increase risk of bladder cancer
- GLIPTINS (DPP-4 INHIBITORS)
- Inhibit DPP-4 → ↓ glucagon secretion and ↑ insulin secretion
- POST-PRANDIAL REGULATORS
- Stimulate insulin release
- Rapid onset and short duration
- Administered shortly before each meal
- Repaglinide - mono or combo with metformin
- Nateglinide - ONLY with metformin
- ↑ ketone bodies → ↓
-
-
- 10% of the NHS budget is spent of the disease
- £17b will be cost to NHS by 2025
-
-
- Not all drugs are appropriate
- B-Blockers should generally be avoided - mask some symptoms of hypo
- Diuretics used with caution - Hypokalemia can impair insulin release and worsen glucose tolerance
- ACEI- usually drug of choice. Especially in presence of proteinuria and in presence of HF.
-
- RECOMMENDATIONS
- Individualized care - tailored to the individual taking into account their personal preferences, comorbidities, risks from polypharmacy, and their ability to benefit from long‑term interventions because of reduced life expectancy.
- Patient education - structured education programme meets all patient needs, eg. linguistics, culture
- Dietary advice - Individualize, Integrate and emphasize
- Blood pressure management - check annually, lifestyle advice. Repeat blood pressure measurements within:
- 1 month if blood pressure is higher than 150/90 mmHg
- 2 months if blood pressure is higher than 140/80 mmHg
- 2 months if blood pressure is higher than 130/80 mmHg and there is kidney, eye or cerebrovascular damage.
- Antiplatelet therapy - Do not offer antiplatelet therapy (aspirin or clopidogrel) for adults with type 2 diabetes without cardiovascular disease
- Blood glucose management - HbA1c measurements and targeting measure very 6 months if stable. Managed either by lifestyle and diet, or by lifestyle and diet combined with a single drug not associated with hypoglycaemia, support the person to aim for an HbA1c level of 48 mmol/mol (6.5%). For adults on a drug associated with hypoglycaemia, support the person to aim for an HbA1c level of 53 mmol/mol (7.0%).
-
- 7. Managing complications
- Gastroparesis - antiemetic not helpful but maybe erythromycin and metocloprimaide alternated.
- Neuropathy - treat neuropathic pain
- Erectile dysfunction
- Diabetic foot problems
- Eye Disease: Retinopathy - regular eye tests. Can be managed with laser treatment. Need good glucose and BP control. Refer to optometrist or ophthalmic optician. Free eye tests for diabetics.
- Kidney Disease: Nephropathy - minimize by good glucose and BP control. Characterised by microalbuminaemia. Worsens to proteinuria. ACEI slows progression.
-
- Diabetic Foot care
- Provide advice on good basic foot care, avoid narrow fitting, tight shoes
- Keep toenails well trimmed, cut straight across
- Seek attention of chiropodist/podiatrist if appropriate
- Warn of danger signs - pins and needles
- Get cuts, burns on feet treated
- Watch for fungal infections
-
- Need to inform DVLA if on insulin injections not on oral medication
- If on oral medication advise patient to avoid delaying or missing meals and snacks
- If had 2 or more episodes of hypo in last 12 months inform DVLA
- Take breaks on long journeys
- Always keep hypo treatments to hand in the car
- Consider timing of meals and snacks
- Be aware of hypo signs and stop driving
- Declare diabetes when applying for motor insurance.
-
Medicine's Management & Optimisation

- MEDICINES OPTIMISATION
- Ensure all appropriate drugs prescribed
- Best choice of anti-diabetic agent
- Correct dosage regime
- Compliance with regime
- Complications optimally managed
- Education - eg - hypo, seeking help
- Insulin - how to use, storage, test strips, monitors, diary
- Pie de imagen: If use insulin or medication to manage diabetes - entitled to free prescription with a medical exemption certificate - FP92A
-
- Signposting - Diabetes UK


Información
- Descripción
- Masters (TFW) Pharmacy Diapositivas sobre Diabetes , creado por skr94 el 31/03/2016.
- Creado por
- skr94
- Visitas
- 319
- Valoración