
Mind map
thalassaemias
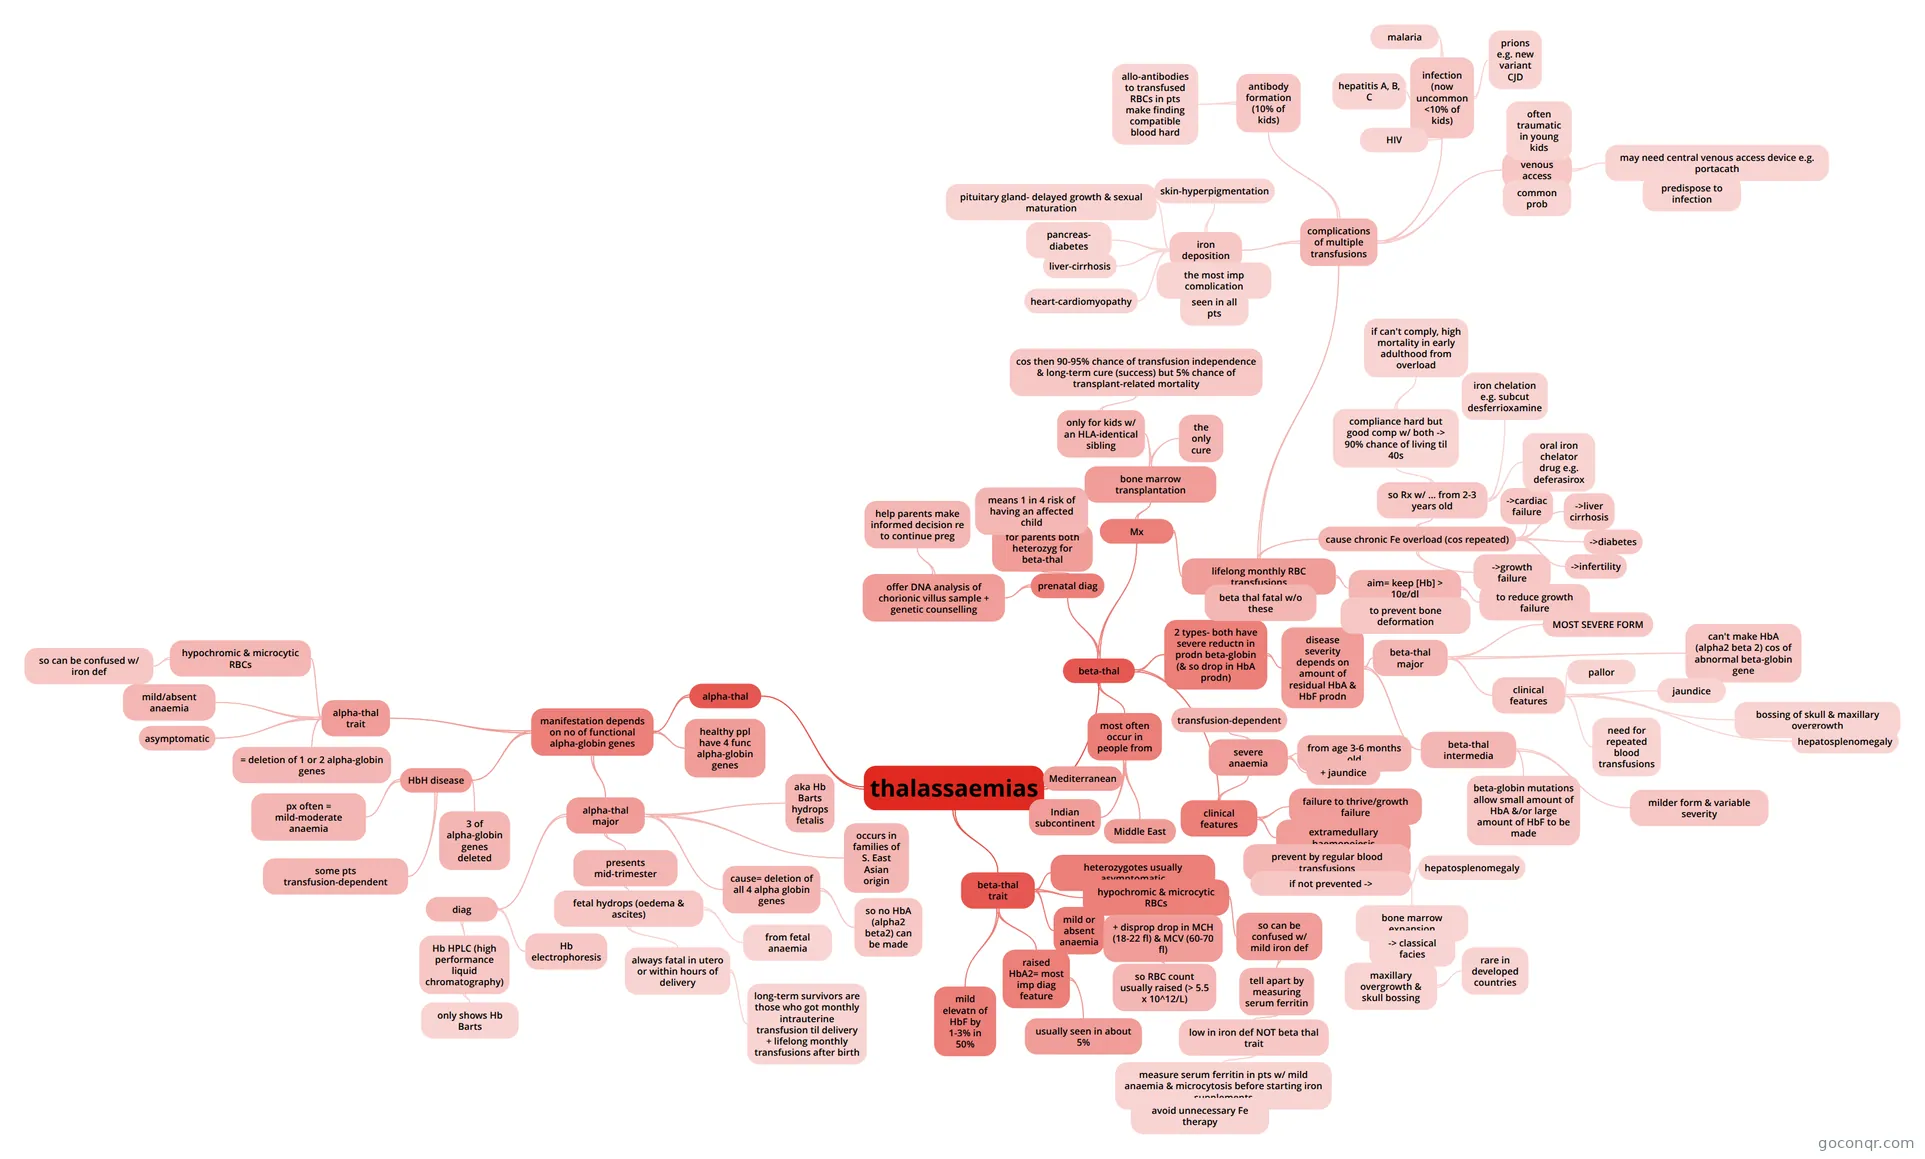
Mind map: thalassaemias
Map content
thalassaemias
beta-thal
- most often occur in people from
- Indian subcontinent
- Mediterranean
- Middle East
- 2 types- both have severe reductn in prodn beta-globin (& so drop in HbA prodn)
- disease severity depends on amount of residual HbA & HbF prodn
- beta-thal major
- MOST SEVERE FORM
- can't make HbA (alpha2 beta 2) cos of abnormal beta-globin gene
- clinical features
- pallor
- jaundice
- bossing of skull & maxillary overgrowth
- hepatosplenomegaly
- need for repeated blood transfusions
- beta-thal intermedia
- milder form & variable severity
- beta-globin mutations allow small amount of HbA &/or large amount of HbF to be made
- beta-thal major
- disease severity depends on amount of residual HbA & HbF prodn
- clinical features
- severe anaemia
- transfusion-dependent
- from age 3-6 months old
- + jaundice
- failure to thrive/growth failure
- extramedullary haemopoiesis
- prevent by regular blood transfusions
- if not prevented ->
- hepatosplenomegaly
- bone marrow expansion
- -> classical facies
- maxillary overgrowth & skull bossing
- rare in developed countries
- maxillary overgrowth & skull bossing
- -> classical facies
- if not prevented ->
- prevent by regular blood transfusions
- severe anaemia
- Mx
- lifelong monthly RBC transfusions
- beta thal fatal w/o these
- aim= keep [Hb] > 10g/dl
- to reduce growth failure
- to prevent bone deformation
- cause chronic Fe overload (cos repeated)
- ->cardiac failure
- ->liver cirrhosis
- ->diabetes
- ->infertility
- ->growth failure
- so Rx w/ ... from 2-3 years old
- iron chelation e.g. subcut desferrioxamine
- oral iron chelator drug e.g. deferasirox
- compliance hard but good comp w/ both -> 90% chance of living til 40s
- if can't comply, high mortality in early adulthood from overload
- complications of multiple transfusions
- iron deposition
- the most imp complication
- seen in all pts
- heart-cardiomyopathy
- liver-cirrhosis
- pancreas- diabetes
- pituitary gland- delayed growth & sexual maturation
- skin-hyperpigmentation
- the most imp complication
- antibody formation (10% of kids)
- allo-antibodies to transfused RBCs in pts make finding compatible blood hard
- infection (now uncommon <10% of kids)
- hepatitis A, B, C
- HIV
- malaria
- prions e.g. new variant CJD
- venous access
- common prob
- often traumatic in young kids
- may need central venous access device e.g. portacath
- predispose to infection
- iron deposition
- bone marrow transplantation
- the only cure
- only for kids w/ an HLA-identical sibling
- cos then 90-95% chance of transfusion independence & long-term cure (success) but 5% chance of transplant-related mortality
- lifelong monthly RBC transfusions
- prenatal diag
- for parents both heterozyg for beta-thal
- means 1 in 4 risk of having an affected child
- offer DNA analysis of chorionic villus sample + genetic counselling
- help parents make informed decision re to continue preg
- for parents both heterozyg for beta-thal
- most often occur in people from
beta-thal trait
- heterozygotes usually asymptomatic
- hypochromic & microcytic RBCs
- so can be confused w/ mild iron def
- tell apart by measuring serum ferritin
- low in iron def NOT beta thal trait
- measure serum ferritin in pts w/ mild anaemia & microcytosis before starting iron supplements
- avoid unnecessary Fe therapy
- measure serum ferritin in pts w/ mild anaemia & microcytosis before starting iron supplements
- low in iron def NOT beta thal trait
- tell apart by measuring serum ferritin
- so can be confused w/ mild iron def
- mild or absent anaemia
- + disprop drop in MCH (18-22 fl) & MCV (60-70 fl)
- so RBC count usually raised (> 5.5 x 10^12/L)
- + disprop drop in MCH (18-22 fl) & MCV (60-70 fl)
- raised HbA2= most imp diag feature
- usually seen in about 5%
- mild elevatn of HbF by 1-3% in 50%
alpha-thal
- manifestation depends on no of functional alpha-globin genes
- alpha-thal major
- aka Hb Barts hydrops fetalis
- cause= deletion of all 4 alpha globin genes
- so no HbA (alpha2 beta2) can be made
- occurs in families of S. East Asian origin
- presents mid-trimester
- fetal hydrops (oedema & ascites)
- from fetal anaemia
- always fatal in utero or within hours of delivery
- long-term survivors are those who got monthly intrauterine transfusion til delivery + lifelong monthly transfusions after birth
- fetal hydrops (oedema & ascites)
- diag
- Hb electrophoresis
- Hb HPLC (high performance liquid chromatography)
- only shows Hb Barts
- HbH disease
- 3 of alpha-globin genes deleted
- px often = mild-moderate anaemia
- some pts transfusion-dependent
- healthy ppl have 4 func alpha-globin genes
- alpha-thal trait
- = deletion of 1 or 2 alpha-globin genes
- asymptomatic
- mild/absent anaemia
- hypochromic & microcytic RBCs
- so can be confused w/ iron def
- alpha-thal major
- manifestation depends on no of functional alpha-globin genes
Information
- Description
- Paediatrics (Haematological disorders) Mind Map on thalassaemias, created by v.djabatey on 18/03/2014.
- Created by
- v.djabatey
- Views
- 45
- Tags
- Rating