
Flashcards
Lectures 4 EENT
Flashcards do conjunto (50)
- 1Parts of the Eye ExamVisual acuity
Inspection
Pupils equal, round, react to light, accommodation, convergence (PERRLAC)
Extra ocular movements (EOMs)
Visual fields by confrontation VFs
Corneal reflex (optional)
Tonometry (optional)
Fundoscopic exam - 2Far visual acuity vs. near visual acuityFar visual acuity: Snellen chart (20 ft)
Near visual acuity: Rosenbaum chart (14 inches- use string attached to chart) or other charts
*Myopia or hyperopia disguised as “legally blind”: 20/200
*remember to cover the other eye, not close - 320/20 vs. 20/4020/20= twenty feet away/ a normal eye can see this at 20 feet
20/40= a normal eye can see this at 40 feet
If patient misses 2: 20/40-2 - 4Eye Exam Process and Termsusually done first
Read the line backwards for second eye
Large “E” at top of Snellen chart- record in feet
“Tumbling E” test if patient is illiterate
Hand motion (HM)
Light perception (LP)
Right eye= OD
Left eye= OS
Both eyes= OU - 5Pinhole Testinguse pinhole if patient needs refraction
- 6Ishihara Test PlatesTest for color vision
- 7Eye InspectionEye brow hair/distribution
Orbit: swelling/ edema
Eye lids: open/ closed, lesions, lashes, evert/ invert, erythema, ptosis
Eye brow hair distribution
Conjunctiva: erytherma, discharge, lesions
Notice exophthalmus: (bulging)
Scleral color (jaundice?)
Note lid ptosis
Evert upper lids if indicated
Cataract - 8CataractOpacification of the lens
- 9Inspect Cornea/PupilsClear, cloudy, lesions of cornea
Pupil size and shape
Direct and Indirect light reflex
“PERRLAC”
P upils
E qual
R ound
R eact to
Light
A ccomodation
C onvergence/ consensual response - 10Testing Direct & Consensual Pupillary Light ReflexDim room lights
Look for both direct (same eye) & consensual (other eye) reactions
Use a second light tangentially to view consensual response
Record any asymmetry or irregularity - 11APD: Afferent Pupillary DefectDetects a problem in pathway:
front of eye --> afferent nerves (CN III) --> brain--> efferent nerves (CN VII)--> pupil
Instead of pupil constricting with light shown in eye, it dilates - 12RAPD: Relative Afferent Pupillary DefectAffected side does not constrict as strongly (as unaffected side) with light shown in it
- 13AccommodationHold your finger 10 cm from patient's nose.
Ask them to alternate looking into distance & at your finger.
Observe pupillary response in each eye.
Pupils should constrict when the eyes focus on near object - 14Argyll Robertson Pupil (Abnormal Pupillary Response)Seen in pts with Tabes Dorsalis
bilateral, miotic pupil w/ irregular margins, asymmetrical
absent light reflex but retained accommodation
lesion is at pretectal area
Other causes include:
diabetes, Wernicke's encephalopathy, encephalitis, midbrain tumours, hereditary neuropathies - 15Testing for Shallow AnglesRisk factor for acute glaucoma
- 16Testing EOMsStand 3 ft. in front of patient
follow finger w/ eyes w/out moving head
Check gaze in six cardinal directions using a cross, "H" pattern / large figure 8
eye movement = full extent
Check convergence by moving your finger toward the bridge of patient's nose.
Observe for nystagmus and “lid lag” - 17Nerves controlling which eye movementsLR6 (SO4)3
*Lateral rectus: Cranial nerve VI (abducens)
*Superior oblique: Cranial nerve IV (trochlear)
*All other muscles: Cranial nerve III (oculomotor) - 18NystagmusInvoluntary oscillating movements of eyes
Lateral, vertical, circular (torsional)
Usually slow and fast beat components
Normal variation on lateral gaze
Indicates vestibular or brain stem dysfunction - 19Visual Fields by ConfrontationStand two feet away from patient at equal eye level to the patient’s eyes
Test 8 areas of visual field
Compare patient’s response time to yours
Do the test slow enough
Do one field of vision at a time
Patient’s fields are (grossly) full if they correspond with yours
Abnormal test necessitates formal visual fields test - 20Fundoscope/ Ophthalmoscope ExamRed Reflex
Look 15 degrees lateral of midline gaze, toward nose
Follow the red color to move within a few inches of the patient's eye.
Adjust diopter dial to bring the retina into focus
Black/ green: focus closer to you, convex lens
Red: focus farther away, concave lens
Find a blood vessel and follow it to the optic disk - 21Optic DiscVeins larger and darker red than arteries
Both emanate from central optic disk
Cup/ disc ratio approximately 3:1
2:1 ratio is considered cut off of normal - 22Maculasite of central vision & located 2 disc diameters temporal (lateral) to optic disc
To view macula, ask patient to look directly at the light of the ophthalmoscope or stand directly in front of patient
Use “crosshair” setting on ophthalmoscope to reduce corneal glare - 23Fundoscopic Exam ObservationOptic Disc: C/D ratio, papilledema
Vessels, all 4 quadrants: A/V nicking
Macula, Hemorrhages
Background retinopathy: bleeding, hard exudates, cotton wool exudates - 24Cotton Wool ExudatesYellow-white spots, flecks
lipid residues of serous leakage from damaged capillaries
Caused by retinal nerve fiber layer micro infarcts.
Exploded retinal ganglion cell axons extrude their axoplasm like toothpaste.
*Any process that occludes small retinal arterioles:
hypertension, diabetes (most common), HIV, severe anemia or thrombocytopenia, hypercoagulable states, connective tissue disorders, viruses, syphilis - 25Ear ExamInspection of auricle
Palpation of auricle/ tragus/ mastoid
Whisper or watch test for hearing
Formal hearing tests if abnormal
Weber and Rinne tests
Otoscopic exam - 26Inspection of External Auditory CanalNote integrity. Is it clear?
Any tenderness, discharge, odor?
Is it patent?
If occluded: cerumen (ear wax), foreign body? edematous (swollen)? - 27Weber TestTests conductive vs sensorineural hearing loss
Hit tuning fork on palm of hand
Place tuning (512HZ) fork on middle and top of head (or forehead)
Sound should be equal, AD=AS (AD=right ear, AS=left ear)
"Do you hear the tone better on one side or is it equal?" - 28Rinne (rin′nĕ) TestTest air conduction vs bone conduction
Place tuning (512HZ) fork on mastoid process
“Tell me when you stop hearing the sound” and note time
Place the tuning fork next to auricle
“Tell me when you stop hearing the sound” and note time
Air conduction should be 2X > bone conduction - 29Inspection of Tympanic Membrane (TM)Start with “normal” side
Use largest speculum that canal will accommodate (2 mm pediatric, 4 mm adult)
Note color & translucency: intact TM shiny, opaque, & translucent, cone of light
Note if perforated, bulging, red (erythematous) & inflamed, retracted, dull or scarred - 30Abnormal TMComplete the quizlet
- 31Nose/Sinus ExamInspection of External Structures
Septum position
Nasal patency
Inspection of:
*septum *nasal mucosa *turbinates - 32Sinuses Percussion1. Frontal
2. Ethmoid
3. Sphenoid
4. Maxillary - 33Sinus ExamInspect frontal & maxillary areas for swelling
Palpate frontal sinus: press upward under both eyebrows with thumbs.
Palpate maxillary sinus: using either thumbs or index/ middle fingers to press up under the zygomatic processes
Percuss sinuses: press/ tap directly over sinus areas with index finger
Transillumination optional - 34Mouth ExamWith light source and tongue depressor:
Inspection of mouth, lips (cheilitis), dentition, gums
Inspection of tongue, frenulum, buccal mucosa, ducts
Inspection of soft/ hard palate, pharynx, uvula, tonsils
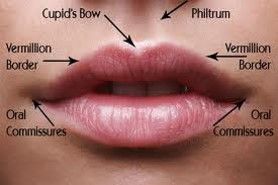
Tongue strength, tapping of teeth (optional for this lab) - 35Lips and Mouth Superficial Anatomy
- 36Torus palatinus/ Taurus Palatinebony protrusion on the palate
- 37Tongue ExamCan use 4x4 gauze to grasp tongue
Inspect for color, swelling, coating, deviation from midline, or fasciculations (part of neuro exam)
Inspect dorsal surface for frenulum, varicosities, masses, Wharton’s ducts
If masses suspected/ risk factor, palpate with glove - 38Throat ExamInspect palate and uvula: “yawn” or “say ah”
Note if uvula is midline and check gag reflex if needed (neuro exam)
Use tongue blade to assist in viewing
Tonsil enlargement is rated 1-4+, erythema, exudates - 39Chest Pain Onset & DurationSudden or gradual
Precipitating factors
Time episode lasted
Frequency/Recurrent? - 40Chest Pain CharacterSeverity
Sharp, burning, pressure, stabbing. aching, crushing or tingling - 41Chest Pain LocationSubsternal
precordial
epigastric - 42Chest Pain RadiationJaw, teeth, down arms, into back, scapula or neck
- 43Chest Pain Associated SymptomsDyspnea, syncope, palpitations, diaphoresis
- 44Chest Pain Differential DiagnosisCardiac Causes
Acute Coronary Syndrome
Acute MI
Unstable Angina Pectoris
Stable/Prinzemetal Angina
Pericarditis
Aortic Dissection
Aortic Stenosis/Aortic Insufficiency
Hypertrophic Cardiomyopathy (HOCM)
Non Cardiac Causes
GERD
(Peptid Ulcer Disease) PUD
Esophageal Spasm
Gallbladder Disease
Herpes Zoster
Musculoskeletal
Costochondritis
(pulmonary thromboembolism) PTE
Pleurisy (inflammation of lung linings)
Trauma - 45Dyspnea of lung diseaseDyspnea intensified by effort
Chronic cough with expectoration/hemoptysis
Respirations are shallow & rapid
Postural changes have little effect
Rate of recovery to normal respiration fast
Do not usually have dyspnea at rest
Smoking most frequent precipitating & aggravating factor
Usually more gradual in onset than that of heart disease & related to activity
Exacerbations & remissions.
Patients often have periods when they are severely limited by SOB, but these may be interspersed with periods in which symptoms are minimal or absent - 46Dyspnea of heart diseaseHeart disease is more acute & often not exertional
May occur at rest
Relieved by sitting up or sleeping on pillows (orthopnea)
Occurs when sleeping (Paroxysmal nocturnal dyspnea or PND)
Rate of recovery to normal respiration slow
May be angina equivalent
Associated PE findings(S3, edema, bibasilar crackles) - 47Causes of Dyspnea1. Acute
Asthma
CHF (PE)
Acute infectious (bacterial pneumonia)
Hemo/Pneumothorax
Pulmonary thromboembolus (PTE)
Panic Disorder/ Hyperventilation
Upper airway obstruction
2. Chronic
COPD
Chronic interstitial lung disease
Chronic infectious
Chronic cardiac disease - 48Common Sx of CVD1. Palpitations (associated w/fainting, dizziness, (chest pain) CP, dyspnea, or anxiety)
2. Syncope (decrease perfusion to brain, ask fall, head trauma, assc. w/ palpitation, turning of neck, rapid change in position, exertion, hypotension, CM use, neurological sxs?)
3. Fatigue
Associated sx (DOE, orthopnea, anorexia, nausea, wt loss)
inability to keep up with peers
interfere with normal activities
bedtime earlier, increased rest periods
may be due to non-cardiac issue (anemia, depression) - 49Selected CV Symptoms*Pedal edema, ascites or general anasarca
*Weight loss or wasting syndrome due to cardiac cachexia
*Fever in an IV drug user or in a patient with any valvular disease
*Episodes of cyanosis
*Symptoms of peripheral embolization including CVA/TIA’s due to cardiac arrhythmia's or valvular vegetations
*Full cardiac arrest - 50CAD Risk FactorsHyperlipidemia
Hypertension
DM
Smoking
Obesity (Central) = Abdominal girth >40” for men or 35” for women
Male Gender
Age males > 45; female > 55
Hypoestrogenemia in women
Physical inactivity
Positive family history
History of CAD or MI
Informações
- Descrição
- Physical Diagnosis FlashCards sobre Lectures 4 EENT, criado por Vy Nguyen em 29-09-2017.
- Criado por
- Vy Nguyen
- Visualizações
- 1
- Avaliação