
Flashcards
Week 4
Flashcards do conjunto (70)
- 1What is Addison's disease?Failure of the adrenal gland
Treated with steroids - 2Define endocrine glandsGlands that release secretions (hormones) into the blood directly from cells. They are ductless.
They regulate metabolism, reproduction and homeostasis - 3Define exocrine glandsThey are not a part of the endocrine system.
Glands that release their secretions outside of the body and may be ducted eg. gut secretions (considered outside of the body) and sweat glands. - 4Example of a mixed gland? What does it secrete?Prancreas
Produces digestive juice, insulin, glucagon and somatostatin (inhibits secretion of other hormones such as insulin, glucagon, GH, TSH) - 5What are neuroendocrine cells? ExampleCells which secrete hormones from an axon into the blood. It has a rapid response.
Example: in posterior pituitary gland - 6What is a hormone? How do they work?A substance that is secreted (in minute concs) directly into the blood by specialised cells. They are carried in the blood to target organs, where they bind to specific receptors in target cells.
- 7What are the different mechanisms of chemical signalling?Intracrine
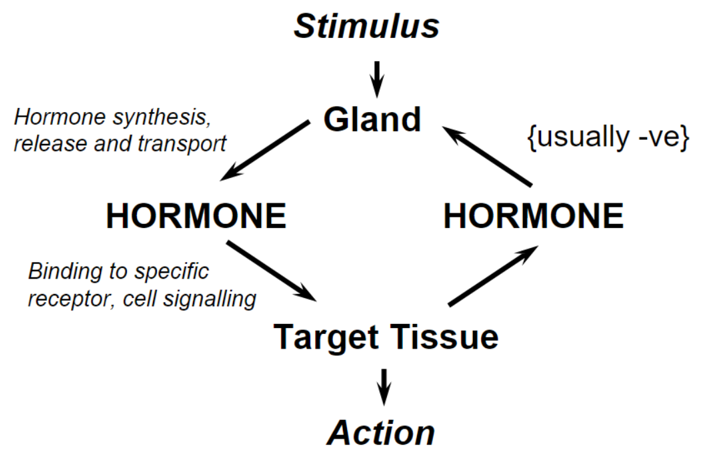
Autocrine
Paracrine
Endocrine
Neuroendocrine - 8Describe: intracrine autocrine-Signal is generated by a chemical acting within the same cell.
-Signal is generated by a chemical acting on the same cell. The chemical leaves the cell and binds to a receptor on the same cell. - 9Describe: paracrine (neuro)endocrine-Chemical communication between neighbouring cells within a tissue or organ.
-A chemical is released by a specialised group of cells into the circulation and acts on a distant target tissue - 10Describe the feedback mechanism of the endocrine system
- 11Define feedbackProcess by which body senses change and responds to it
- 12Define...feedback: -negative -positive-Process by which the body senses change and activates a mechanism to reduce it (ie. in the final stage of the endocrine cascade, there is an inhibitory effect on hormone release).
-Process by which the body senses change and activates a mechanism to amplify it. - 13What is a tropic hormone? What is an endocrine axis? Example?A hormone that stimulates another endocrine gland.
Functional grouping of endocrine glands. The hormones secreted are tropic hormones and the system is controlled by -ve feedback. Example: hypothalamo-pituitary-adrenal (HPA) axis. - 143 main groups of hormones?-protein/peptide
-steroid
-amine - 15Properties of peptide hormones?-Hydrophilic
-Preformed and stored in membrane bound vesicles (released via exocytosis)
-Produced on ribosomes (rER) as large precursor molecules-->pre-prohormone
-Mostly made in the pituitary/hypothalamus - 16What is a pre-prohormone?A large protein that contains the active molecule (needs to be cleaved using lysosomes).
Pre-prohormone --> prohormone --> hormone - 17How are protein hormones structured?-Have a common alpha subunit
-Have unique beta subunits which results in specificity - 18Features of steroid hormones?-All have cholesterol as a precursor
-From the adrenal cortex and sex hormones
-Lipophilic (needs a transport protein to make them soluble in the blood)
-Diffuses out of the cell straight away (cannot be stored)
-Synthesised in the sER from cholesterol/acetate - 19Pathway cholesterol undergoes?1) Cholesterol
2) CYP11A (enzyme)
3) Pregnenolone (formed in mitochondria but moves to ER for processes to hormones)
4) Other hormones (location in the adrenal gland determines what enzymes are used on pregnenolone, which determines the hormone) - 20How are steroid hormones formed inside the cell?1) Hydrolysis of esters and release of cholesterol
2) In the mitochondrion, cholesterol is converted to pregnenolone. Movement to mitochondria is controlled by StAR (steroid acute regulatory protein). ACTH regulates StAR activity/processing of cholesterol.
3) In the sER, pregnenolone is processed
4) Hormone leaves by (facilitated) diffusion - 21Where is... produced? -aldosterone -cortisol -adrenal androgens- zona glomerulosa
- z.fasciculata
- z.reticularis - 22What can secretion rates of steroid hormones tell us? How are steroid hormones excreted?Increased rates in secretion reflect accelerated rates of synthesis.
Eliminated by inactivating metabolic transformations and excreted in the urine/bile - 23Features of amine hormones-Tyrosine derivatives bound together
-T4 (4 iodine molecules), T3 (3 iodine molecules- more potent)
-Lipophilic/hydrophobic
-Small, non-polar molecules (soluble in plasma membranes) - 24How are hormones transported in the blood?-Peptide hormones are freely water soluble
Steroid hormones need to be transported in the blood by specific/non-specific binding proteins (bound/free hormones are in equilibrium). This:
-increases solubility in the blood
-increases half-life
-creates readily accessible reserve in the blood - 25How do peptide hormones interact with cells?They bind to cell surface receptors activating the second messenger cascade.
Phosphorylation of proteins within the cell occurs and the activated proteins bring about a change in cellular function. - 26How do steroid hormones interact with cells?They bind to intracellular receptors in the cytoplasm/nucleus.
The hormone receptor complex binds to the specific hormone response element (ie. oestrogen response element) to cause a response. - 27How do endocrine disorders occur?-Overproduction/underproduction of a hormone
-Non-functional receptors that cause target cells to become insensitive to hormones - 28How can excess of a hormone occur? Treatment?-Tumour
-Exogenous administration of a hormone as part of treatment
Surgical removal of part of a gland - 29How can deficiency of a hormone occur? Treatment?-Primary organ is inadequate so tropic hormone levels increase
-Deficiency in tropic hormone so further glands are not stimulated
-Autoimmune organ destruction (most common cause)
Replacement therapy:
-orally absorbed for substances with a long half-life (steroid/amine hormones)
-injected (peptide- otherwise degraded in GI tract) - 30What is diabetes a disease of?High glucose, blood pressure and lipid levels
- 31Symptoms of diabetes?-Often none at all
-Weight loss
-Tiredness
-Infection (candidiasis/ urinary)
-Osmotic symptoms (urine amount increases, thirst, tiredness)
-Blurred vision
-Coma - 32Is testing urine useful for diagnosing diabetes?Yes but not very
-not sensitive or specific
-any glucose in the urine should however be investigated - 33Procedure for the oral glucose tolerance test1) Patient fasts (8-12 hours)
2) Blood sample is taken at time 0hrs (after fasting) and glucose is measured
3) 75g of glucose drink is taken over 5 mins
4) Blood sample is taken at time 2hrs and glucose is measured - 34What is the HbA1c test?-Test to measure glycated haemoglobin content
-Target amount for people with diabetes: 6.5%
-Reflects the past 10 weeks of ambient circulating glucose
-Used to target treatment and make a diagnosis - 35Purpose of insulin?-Moves glucose out of the blood stream for storage/building
Major anabolic hormone used for:
-maintaining supply of glucose to tissue
-regulating metabolism in muscle
-promoting protein synthesis
-inhibiting fat breakdown - 36Cause of Type 1 diabetes?Insulitis
-It is a lymphocytic infiltration of the Islets of Langerhans. This produces an inflammatory/autoimmune response which leads to the destruction of beta cells in the pancreas. - 37Causes of Type 2 diabetes?-Insulin resistance in skeletal muscle and liver (higher insulin levels than normal, which results in beta cell failure- they are overworked)
-Genetic predisposition
-Association with obesity
-Beta cell dysfunction (leads to reduced insulin secretion) - 38What is another type of diabetes?Gestational diabetes (form of Type 2 diabetes in pregnancy)
- 39Differences in Type 1/2 diabetes in terms of: -age -onset -family history -ketone presence -is insulin needed for life?<40 yrs/ >40 yrs
Dramatic/Slow
Less common/common
Yes/no
Yes/no - 40What are the treatments for Type 1/2 diabetes?Type 1:
-lifestyle
-insulin injections
Type 2:
-lifestyle
-reduce insulin resistance
-increase insulin secretion (from beta cell)/excretion (in urine)
-insulin injections - 41How does high blood pressure arise form diabetes?-Blood vessels stiffen
-Endothelial dysfunction occurs where there is an imbalance between vasodilating and vasoconstricting substances produced by the endothelium - 42Complications of diabetes?-Platelet dependent thrombosis
-Angina/heart attacks
-Stroke
-Gangrene
-Retinopathy (leads of vision impairment/blindness)
-Neuropathy (damage to sensory, motor and autonomic nerves) - 43Symptoms of autonomic neuropathy?-Digestive problems (eg. feeling full, nausea)
-Vomiting, diarrhoea, constipation
-Bladder problems
-Problems having sex
-Dizziness/faintness
-No warning signs of a heart attack/low blood glucose
-Increased/decreased sweating
-Changes to how eyes react to light/dark - 44Define agonismVarious ways in which effects are produced when drugs bind to receptors and activate them
- 45Define antagonismWays in which effects are blocked when drugs bind to receptors
- 46Define desensitizationWays in which effects are reduced after long-term use of a drug
- 47Describe the path-clamp technique What does it show about the nature of partial agonists?1) A micro-pipette is placed around a single receptor
2) An electrode is connected to the single receptor to measure its current. This means that the response is a quantifiable current
3) A current is produced, showing 2 different levels: when the channel is open or shut
4) Agonists cause the channel to be either fully open or closed
5) It shows that partial agonists are less effective as there is a decreased frequency of channel openings, however the conductance level is the same. - 48Do all channels need a drug to open? How do antagonists affect these type of channels?No some open spontaneously
They bind and do nothing. They do not alter spontaneous openings - 49What are inverse agonists?-They bind to the same site as agonists do
-They have negative efficacy
-They reduce spontaneous activity
-Ions appear to flow in the reverse direction - 50How are inverse agonists different to antagonists?-They both reduce the activity of receptors
-Antagonists reduce the effect of agonists by preventing them from binding to the receptor
-Unlike inverse agonists, antagonists have no effect in the absence of an agonist - 51What are GABAA receptors?-Ligand-gated chloride ion channel in the brain
-Benzodiazepine agonists bind to GABAARs and increase the affinity of the GABA binding site for GABA. Channel opening increases - 52Describe glutamate-gated Cl- receptors-common channel in nervous system
-important target for anti-parasitic drug
-pentamer (5 identical polypeptides in a circle) - 53What are competitive agonists?-Bind reversibly at the same site as the agonist
-Produce a parallel shift to the right of agonist dose/response curves (ie. a higher conc is needed for the same response) - 54What are irreversible agonists?-Binds irreversibly at the same site as the agonist forming a covalent bond
-They decrease the maximal response to agonists by reducing the number of receptors)
-Can be evidence for spare receptors - 55What are allosteric antagonists?-Bind reversibly at a distinct site from the agonist
-Decrease agonist affinity
-Reduce likelihood of agonist binding - 56What are channel blockers?-Bind inside the channel (plug the channel)
-Prevent the passage of ions
-Enhanced by receptor activation
-Use dependent - 57What are physiological antagonists? Examples?-Produce opposite effects on a tissue
-Mechanism does not involve binding to the same receptor
-Provides a non-selective suppression of the response
EXAMPLE: ACh and adrenaline in the heart - 58What is desensitisation?-Prolonged/repeated exposure to an agonist reduces the response to that drug
-Different mechanisms are present to prevent desensitisation - 59Define: -pharmacodynamics -pharmacokineticsWhat the drugs do to the body
What the body does it the drugs - 60What happen when a drug is taken?-Adsorption
-Distribution
-Metabolism
-Excretion - 61What is the therapeutic window?The plasma concentration of a drug between its toxic and effective concentration. It is ideal if it this window is as large as possible
- 62Routes of drug administration?-External eg. oral, rectal
-Parenteral eg. subcutaneous, intra-muscular, intra-venous
-Percutaneous eg. inhilation, sublingual (v. effective), topical/transdermal - 63What does absorption depend on?- Route of administration
-Blood flow at site of administration/surface area
-Dose of drug
-Active/passive diffusion
-Drug solubility eg. hydrophilic/lipophilic - 64What does distribution depend on?-Blood flow -different in different organs
-Lipid solubility/diffusion barriers eg. BBB, placenta
-Tissue binding
-Plasma protein binding (needed for lipophilic molecules) - 65What is first pass metabolism?-When drugs are taken orally, it is absorbed through the interstinal mucosa
-It is then transported via the portal vein into the liver
-Some of the drug is metabolised, so only a part of it reaches the bloodstream - 66What happens when a drug is metabolised?-Oxidation and conjugation (makes it more hydrophilic)
-Oxidation is via cytochrome p450 enzymes only
-Conjugation occurs with small soluble molecules to make the drug more hydrophilic
-Usually inactivates a drug - 67Describe the 2 phases in drug metabolismPhase I: hydroxyl groups are introduced making it more hydrophilic.
Phase II: conjugation occurs with charged groups and compounds - 68How are drugs excreted?-Kidney (into urine)
-Liver (into bile. Enters enterohepatic circulation)
-Lungs
-Saliva
-Sweat
-Milk - 69How is the drug lost in the body from start to finish?-Part of it not dissolved when taken orally
-Broken down in stomach acid/intestine
-Secreted into bile
-First pass metabolism in the liver
-Metabolised/excreted in tissues (not at site of action) - 70What does the dose interval depend on?The plasma half-life: time taken for half of the drug to be eliminated from plasma
Informações
- Descrição
- Hormone synthesis and action Diabetes Receptors and the effects of drugs Intro to Pharmacokinetics
- Criado por
- Dolu Falowo
- Visualizações
- 0
- Avaliação