11984069
Descrição

FlashCards por Anna Hogarth, atualizado more than 1 year ago

|
Criado por Anna Hogarth
mais de 8 anos atrás
|
|
| Questão | Responda |
| What are the function of the following salivary secretions? 1) Amylase 2) Lysozyme 3) Bicarbonate 4) Growth factors 5) Transcobalamin II | 1) Enzyme - breaks down polysaccharides 2) Enzyme - destroys bacterial membranes 3) Buffer - neutralises food and bacterial acids 4) Stimulates epithelial proliferation, particularly protective for oesophageal epithelium. 5) Binds and chaperones cobalamin (vit B12) |
| What are the functions of the following gastric luminal secretions? 1) Mucus 2) Acid 3) Proteases (pepsin and chymosin/rennin) 4) Lipase 5) Intrinsic factor | 1) Secrete bicarbonate-rich mucus that coats and lubricates the gastric surface, protects the epithelium 2) Activation of pepsinogen, inactivation of ingested microorganisms 3) Pepsin (activate by low pH) digests proteins, chymosin coagulates milk proteins 4) Initiates triglyceride digestion 5) Glycoprotein (from parietal and chief cells), binds vit B12 in intestine for absorption |
| Where is intrinsic factor produced? Transcobalamin? | 1) Stomach 2) Ileum |
| What are/what do the following secrete? 1) Mucous neck cells 2) Parietal cells 3) ECL cells 4) Chief cells 5) G cells | 1) Stem cells 2) Secrete acid and intrinsic factor 3) Histamine secretion 4) Pepsinogen secretion 5) Paracrine endocrine |
| Describe the mechanism which facilitates acid secretion into the lumen. | Bicarbonate/chloride antiporter pumps chloride across the basolateral enterocyte surface and HCO3- out of the cell. Cl- is pumped out of the cell across an apical CFTR. CO2 and H20 diffuse into the cell. CO2 is converted into HCO3- by carbonic anhydrase (generates HCO3- gradient). HCO3- in cell can also be used to buffer pH. H20 in cell is split into OH- (contributes to HCO3-) and H+. H+ is pumped into the lumen (combines with Cl- to make HCL) via a H+/K+ antiporter (proton pump). |
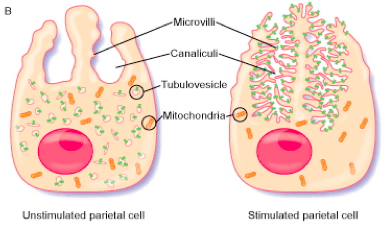
| How do the cells of the gastric pits vary between a quiescent state and digestion? | |
| Describe the pH difference across the gastric mucus gel layer? What is present in the mucous layer? What can increase the solubility of the mucous? | 1) pH in lumen is ~1-2, pH at the apical surface of the enterocytes is ~7. 2) HCO3- to help reduce acidity 3) Alcohol |
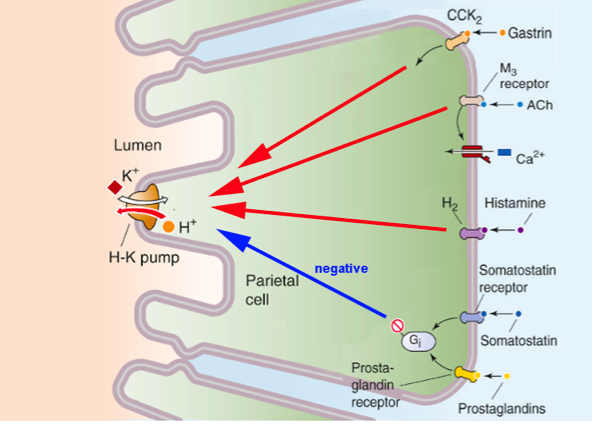
| What are the main mechanisms of feedback control of acid secretion? | 1) Enteric nervous system - stimulates through ACh (and ECL cells) 2) D cells (inhibitory) 3) G cells (stimulatory) |
| Describe the effect of activation of the enteric nervous system on gastric secretions. | Peristalsis of the gut (initially started by the vagus) releases acetylcholine. ACh acts on M3 receptors, directly stimulating parietal cells. Also acts on M3 receptors on ECL cells. Activated ECL cells secrete histamine which acts on H2 receptors on parietal cells (stimulatory). M3 on D cells is inhibitory. |
| How do D cells modulate gastric secretions (note the type of signalling)? | D cells - negatively modulated by acetylcholine. When stimulated (by HCL, proton receptors). They secrete somatostatin. PARACRINE & ENDOCRINE signalling. This acts on parietal somatostatin receptors - inhibitory, reduces secretions. |
| How do G cells modulate gastric secretions? | Stimulated by digested protein (amino acids). Secrete gastrin - this activates both D cells (negative feedback as somatostatin will switch off G cells) and parietal cells. Gastrin stimulates cholecystokinin receptors on parietal cell - increases secretion. |
| What is Zollinger-Ellison syndrome (ZES)? | Caused by gastric acid hypersecretion which characteristically leads to gastroesophageal peptic ulcer disease. Due to ectopic secretion of gastrin by a neuroendocrine tumour. Neuroendocrine tumours (gastrinomas) are usually present in the duodenum or pancreas. Secrete so much gastrin because neuroendocrine tumours are rich in G cells. |
| How do calcium and prostaglandins affect acid secretion? | 1) Calcium enhances through Gq signalling - increases Ca2+ release from ER and PKC activation 2) Prostaglandins contribute to the inhibition of parietal cells. |
| X | |
| Describe the neural control of gastric secretion in the cephalic phase? | Conditioned reflexes (sight, sound, smell) all feed into the cerebral cortex. The cerebral cortex stimulates medullary nuclei. Mechano- and chemoreceptors also feed into the medullary nuclei. Impulses carried from the vagus to the submucosal plexus stimulates secretion. |
| What happens in the gastric phase? How is it regulated neuronaly? | 1) Digestion 2) Distention (stimulates stretch receptors) in the stomach feeds back via the vagus nerve to increase drive to the medullary nuclei and therefore secretion. The drop in pH and gastric distention trigger peristalsis and gastric secretions. |
| How is the gastric phase terminated? | Have to stop secretion towards the end - this is mediated through the SNS, PNS and hormones (CCK, GIP and secretin). |
| What two substances are responsible for bile production? | Cholecystokinin and secretin |
| What are the actions of CCK and secretin? | 1) CCK - produces fatty acids in the duodenum, causes gallbladder contraction and sphincter of Oddi relaxation. 2) Stimulate biliary ductal cells to produce HCO3- (and proteases) to neutralise stomach acid. |
| What percentage of the world are infected with helicobacter pylori? When does it cause a problem? Where is the infection usually located? | 1) >50% 2) Can cause peptic ulcer (in about 20% of infections) when combined with stress, smoking and alcohol and NSAIDs 3) Duodenum |
| How does H. pylori cause damage? | Secretes urease (neutralises pH) - urease produces ammonia from urea and water. This causes the de-gelling of mucus, exposing the epithelial cells to acid and pepsin etc. This result in peptic ulcers. |
| What are the diagnostic tests for detecting H. Pylori? What is the main treatment? | 1) Blood antibody test, stool antigen test, urea breath test, CLO test 2) Triple therapy - 2 antibiotics and 1 proton pump inhbitor |
| What are all the different treatments for treating peptic ulcer disease? (3) | 1) Histamine (H2) receptor antagonists (reduce acid secretion) 2) Proton pump inhibitors (omeprazole) 3) Antibiotics (e.g. amoxicillin + clarithromycin) to eradicate H. Pylori |
| How do proton pumps inhibitor drug names end? | -prazole |
| What is reflux? What is GORD? How much of the population does it affect? What is it not? | 1) Retrograde flow of gastric contents into oesophagus 2) Gastro-oesophageal reflux disease 3) 10-20% of the population 4) Not HCL secretion |
| What causes GORD? | 1) Excessive reflux of normal gastric juice (increased frequency of transient lower oesophageal sphincter relaxations) 2) Weakened oesophageal epithelium 3) Hiatus hernia (weakness in diaphragm) 4) Hypersensitivity of oesophageal nociceptors Note that it can be caused by bile and non-acid components of gastric juice |
| How is GORD treated? | 1) With PPIs (i.e. omeprazole) 2) Possibly eventually by neurological drugs (not effective yet) 3) Antacids to neutralise acidity (Gaviscon) 4) ZANTAC to block H2Rs 5) Activate prostaglandin R 6) Inhibit M3 receptors |
| What is the surgical option for GORD? | Laparoscopic Nissen Fundoplication - the upper part of the stomach is wrapped around the outside of the lower oesophagus to strengthen the sphincter |
| What are the two major active components of gaviscon and what do they do? | 1) Sodium alginate - forms a barrier which protects the oesophagus 2) Potassium hydrogen carbonate (but this can negatively affect digestion as you do need acid) |
Quer criar seus próprios Flashcards gratuitos com GoConqr? Saiba mais.