
Mindmap
Coronary Heart Disease
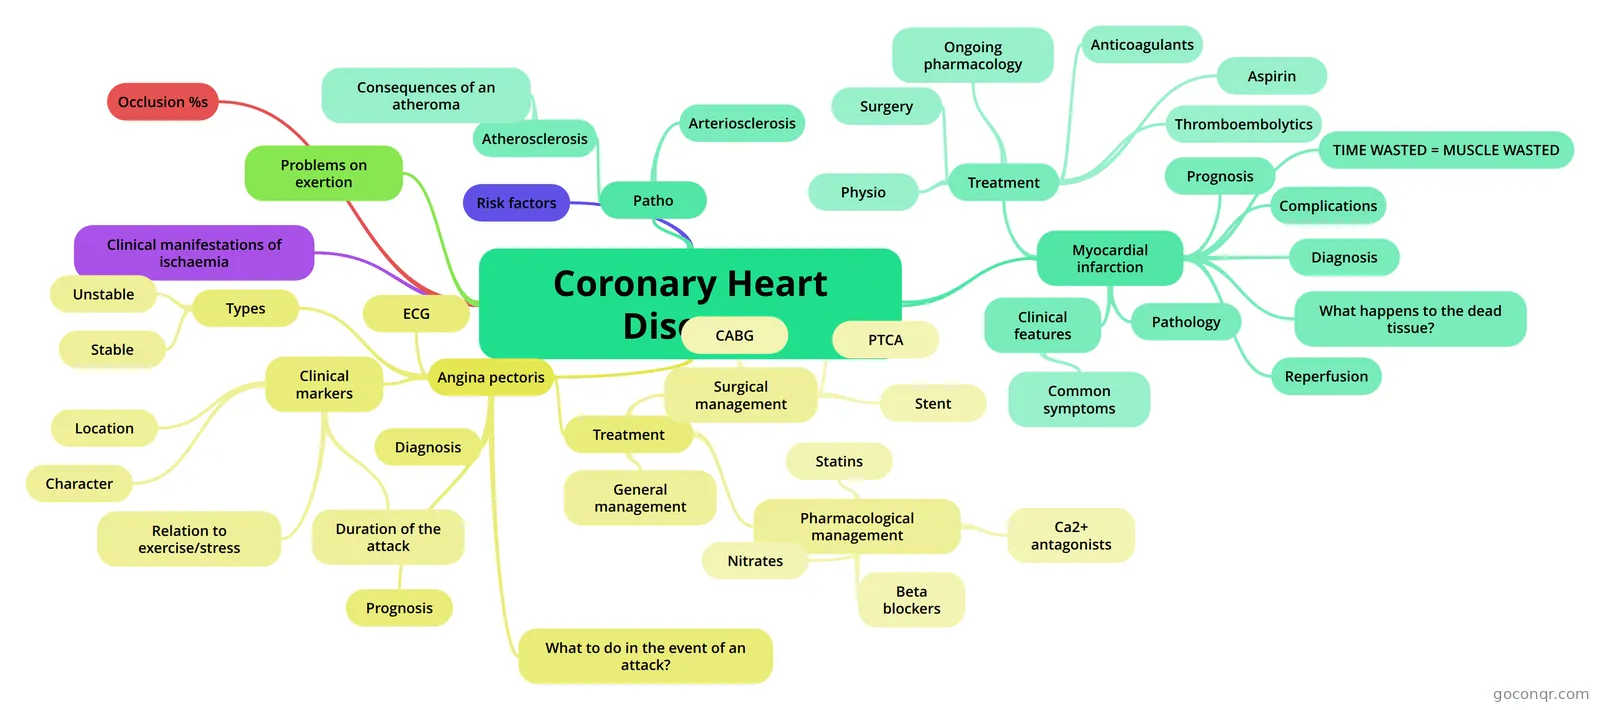
Mind map: Coronary heart disease
Inhalt der Mindmap
Coronary Heart Disease
- Coronary arteries become clogged with plaques.
Patho
- Arteriosclerosis
- Hardening of the arteries. Walls become thick and stiff, lose their elasticity and become calcified. They can no longer VD and therefore can't respond to changes in BP.
- Atherosclerosis
- 1. Damage to the tunica intima 2. Fatty streak formation 3. Fibrous plaque 4. Unstable plaque
- Consequences of an atheroma
- Obstructs lumen - impairing blood flow Impaired blood flow - thrombus formation Plaque rupture - thrombus formation.
- Arteriosclerosis
Risk factors
- Type 2 diabetes Hypothyroidism High diet sat fat (high LDLs) HTN - shearing forces - afterload, increased O2 demand Obesity Smoking Sedentary lifestyles Alcohol
Problems on exertion
- On exertion the demand of the heart increases meaning the myocardium has to contract quicker and more forcefully. This demand is only met by increasing BP, however the heart doesn't have enough O2 and nutrients to cope with the demand and the heart becomes ischaemic.
Occlusion %s
- At rest - 75% occlusion of at least one point of the arterial system leads to ischaemia. On exercise - 50% occlusion of at least one point of the arterial system leads to ischaemia.
Clinical manifestations of ischaemia
- 1. Angina 2. Myocardial Infarction.
Angina pectoris
- 98% due to atheroma 2% due to extreme vasospasm or hypotension. A discomfort in the chest and surrounding areas due to a transiently inadequate blood supply to the myocardium
- Types
- Stable
- A reproducible pattern of intensity and duration.
- Unstable
- A changeable pattern of pain that may occur at rest. It is more serious than stable angina.
- Stable
- Clinical markers
- Location
- Behind upper/middle 2/3 of sternum +/- lower sternum May extend to chest, neck, lower jawRadiating down arms to fingers
- Character
- Relation to exercise/stress
- Stable - comes on with exertion and is relieved by rest. Unstable - may be present at rest
- Duration of the attack
- Usually lasts for 1-5mins but can last for 15-20mins. S + S: - SOB - faintness - anxiety The longer the pain lasts the higher the risk of infarction.
- Location
- ECG
- shows flattened/depressed ST segment - suggestive of ischaemia - more than 0.5mm indicates ischaemia.
- Diagnosis
- Prognosis
- 35% live for 10 years +
- Treatment
- General management
- - Decrease the risk factors e.g. stop smoking, diet and exercise - Increase aerobic fitness - Avoid intense cold, walking in the wind etc as this will cause VC - affecting afterload so heart has to work harder. - Regular assessment of blood lipid profiles
- Pharmacological management
- Nitrates
- GTN immediately relieves angina pain by promoting rapid VD of coronary arteries, and therefore increasing blood flow and O2 delivery to the myocardium. Side effects: CAUSES HYPOTENSION AND SYNCOPE. - causes widespread VC in arterioles and veins. Both decreasing BP. Hypotension can cause fainting, dizziness and headaches as a result of decreased cerebral perfusion.
- Beta blockers
- Block the action of the SNS. Therefore limiting HR max and cardiac contractility. They are cardio-protective as they limit the work of the heart, reducing its demand for O2 and reduces the chances of it becoming ischaemic. Side effects: Fainting Fatigue Dizziness NB. 1. They can block the action of the SNS on brochioles (therefore poor oxygen exchange) 2. May not be able to take if on beta2 agonists for pts with bronchial hyper-responsiveness (e.g. asthma or COPD) 3. lower HRmax during cardiac rehab = 220-age-30bpm.
- Ca2+ antagonists
- Cardio-protective Limit contractility and promote coronary artery VD which increases blood flow to the myocardium and causes peripheral VD. Increased peripheral VD lowers TPR and BP, reducing the work of the heart. Side effects: - dizziness - fainting - headaches
- Statins
- Reduces the rate of LDL:HDL, reducing the likelihood of further atheroma formation. Side effects: - muscle cramps - headaches - heart burn
- Nitrates
- Surgical management
- PTCA
- Percutaneous transluminal coronary angiplasty - inflation of a balloon to compress the fatty tissue in the artery and increase lumen size, therefore improving blood flow.
- Stent
- Metal coil to hold the artery open. Need to take aspirin to prevent clot formation.
- CABG
- PTCA
- General management
- What to do in the event of an attack?
- - stop and rest - seat upright - give GTN - check pulse and respiration - is O2 required - 3 doses of GTN in 10 mins if no relief then treat as a heart attack. - Don't want to lie them down because it displaces blood, increasing VR, increasing the work of the heart, making it more likely to be ischaemic. MUST BRING NITRATES WITH THEM!
Myocardial infarction
- myocardial necrosis secondary to an acute and irreversible interruption of coronary blood supply. The fibrous cap on the atheroma has split, triggering a platelet response and thrombus formation. Occluding the artery. Tissue doesn't cope well with prolonged ischaemia.
- Clinical features
- Pain, similar to angina in distribution and type. Duration 20-30mins Not associated with exertion and not relieved by GTN.
- Common symptoms
- Breathlessness Dizziness Hypotension Rapid pulse Cold and clammy peripheries Distress, anxiety and fear.
- Pathology
- Central zone - irreversible damage. Peripheral zone - can be salvaged providing it is repurfused quickly. This limits myocardial dysfunction.
- Reperfusion
- Achieved by - Thromboembolytics causing fibrinolysis. Has to be given within the hour. - PTCA - ballooning +/- stent - CABG
- What happens to the dead tissue?
- Macrophages engulf the debris 2/52 Scar tissue replaces necrotic myocardium 2-8/52 Scar tissue (collagen fibres) is non contractile and can't conduct electrical impulses so leads to some dysfunction of the heart.
- Diagnosis
- ECG - look for ST elevation STEMI Clinical presentation Biomechanical markers - the greater the enzyme release the greater the size of the infarction.
- Prognosis
- Depends on: - extent of the infarction - extent of collateral channels - location of infarct - PMH - is the myocardium already compromised?
- Treatment
- Ensure viable SaO2 levels - give O2 Pain relief - give morphine Rapid dissolution of an occluding thrombus - Thromboembolytics Prevention of post MI coagulaton e.g. intramural thrombus formation - Anticoagulants Long term prevention of thrombus formation - aspirin.
- Thromboembolytics
- Within 1 hr. Vital for reperfusion. Breaks down the thrombus, salvaging as many myocytes as possible, limiting size of infarct
- Anticoagulants
- To prevent progression or occurrence of a thrombus in the coronary arteries or the left side of the heart (mural thrombus). Also prevents DVTs/PEs that may occur post-op.
- Aspirin
- Long-term anti-platelet therapy. Low dose aspirin 75mg a day to reduce platelet adhesion and therefore reducing thrombus formation.
- Surgery
- Emergency balloon angioplasty or CABG where reperfusion is unsuccessful. May need to repair any secondary damage e.g. to valves or septum. Pt must be stable for surgery.
- Physio
- Early mob - anti-PE stategy Progressive exs Increase confidence/empowerment Prevent deconditioning Life-style education Home exs Cardiac rehab
- Ongoing pharmacology
- Aspirin ACE inhibtors Beta blockers Anti-arrythmics Statins
- TIME WASTED = MUSCLE WASTED
- Complications
- SEE WORKBOOK! Cardiogenic shock LVF or RVF PEs CVA Post infarct angina Shoulder-hand syndrome
Informationen
- Beschreibung
- Cardiac Physiology Mindmap am Coronary Heart Disease, erstellt von jasminejohnson09 am 25/04/2013.
- Erstellt von
- jasminejohnson09
- Aufrufe
- 74
- Tags
- Bewertung