
Mapa mental
Musculoskeletal Disorders
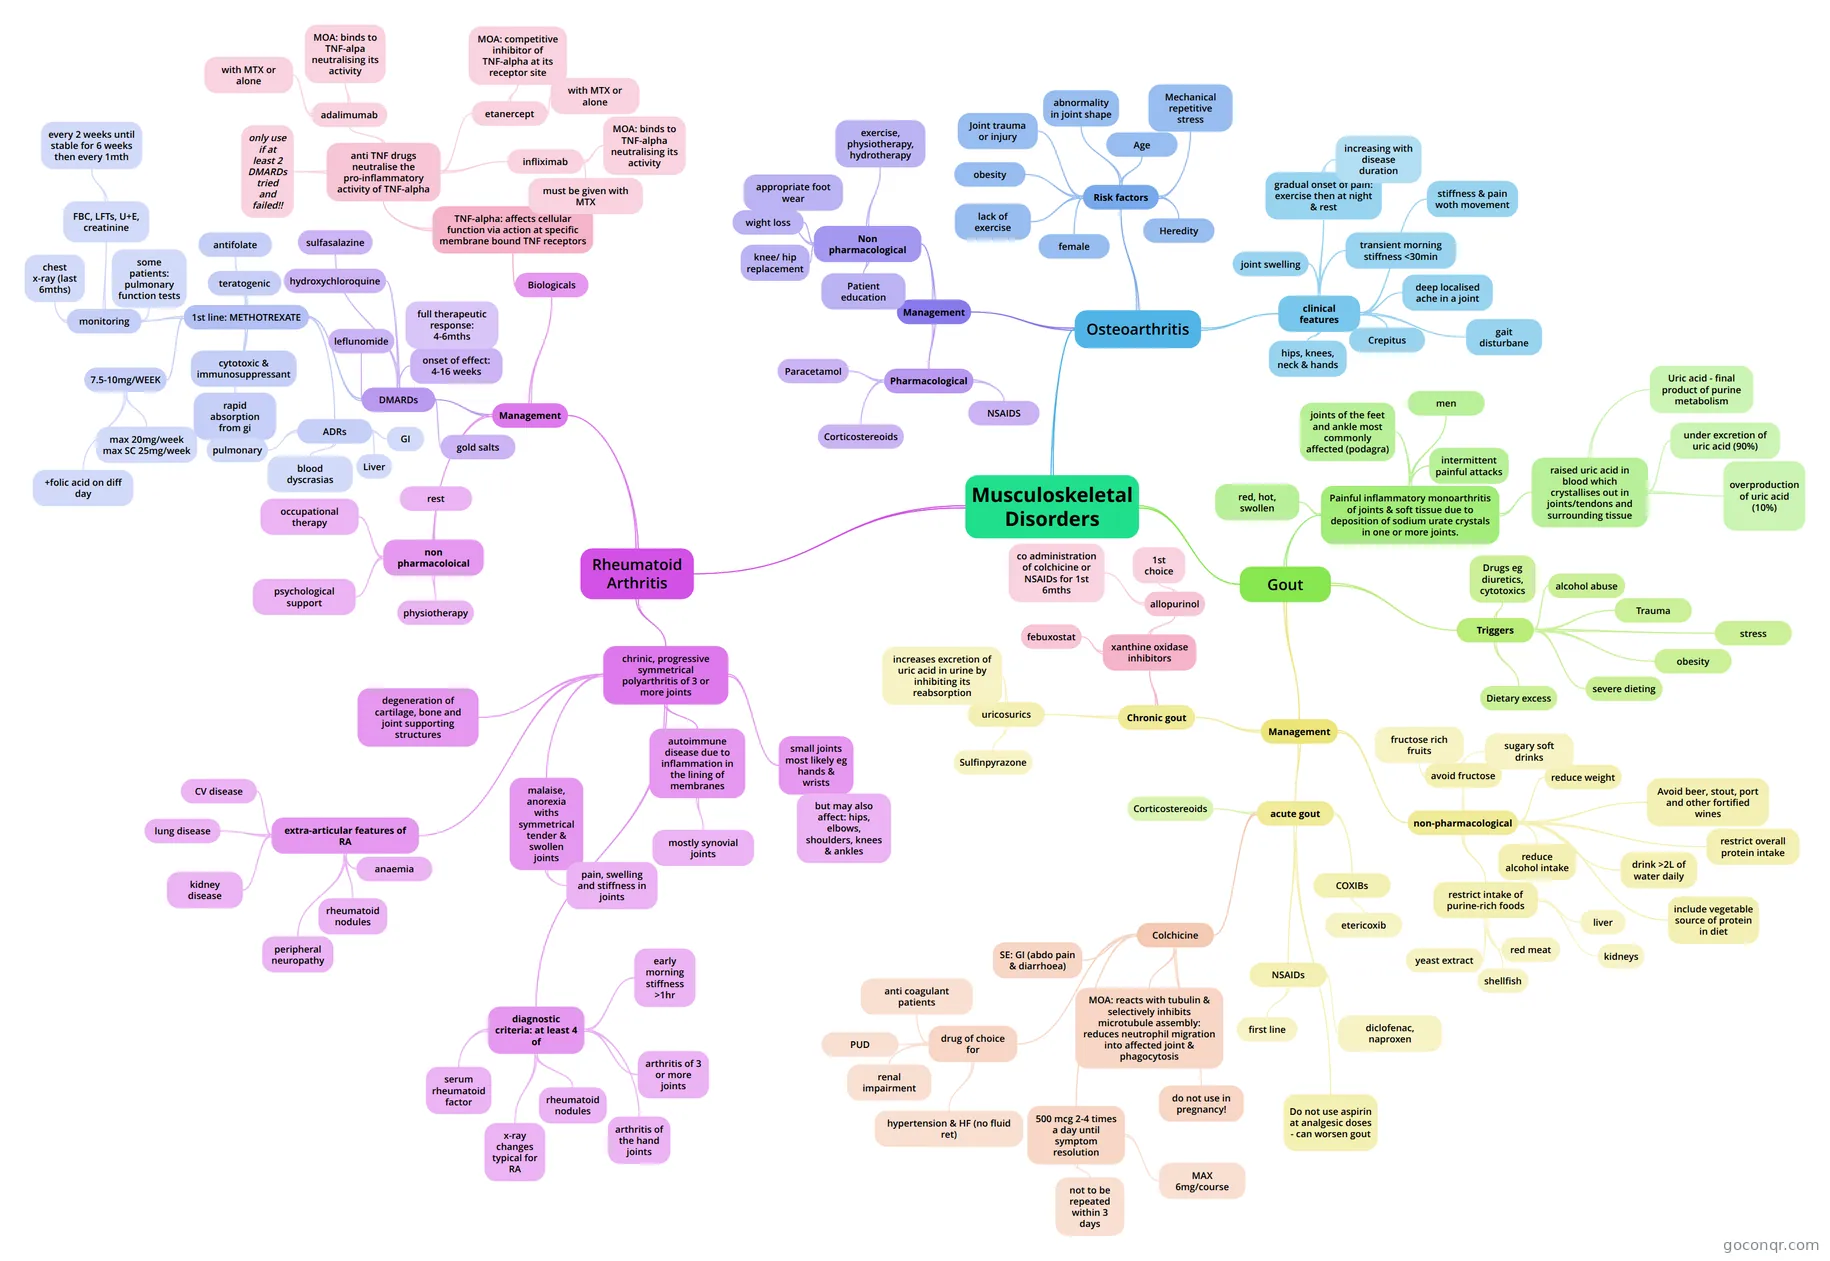
Mind map: Musculoskeletal disorders
Contenido del mapa
Musculoskeletal Disorders
Osteoarthritis
- Joint cartilage degeneration (wear&tear). Non inflammatory The most common form of arthritis
- clinical features
- stiffness & pain woth movement
- transient morning stiffness <30min
- deep localised ache in a joint
- gradual onset of pain: exercise then at night & rest
- increasing with disease duration
- gait disturbane
- joint swelling
- Crepitus
- cracks or creaks on movement
- hips, knees, neck & hands
- Risk factors
- Age
- 50% of >65 have x-ray evidence of OA
- Joint trauma or injury
- abnormality in joint shape
- Mechanical repetitive stress
- Heredity
- female
- obesity
- lack of exercise
- Age
- Management
- Non pharmacological
- Patient education
- wight loss
- exercise, physiotherapy, hydrotherapy
- appropriate foot wear
- knee/ hip replacement
- Pharmacological
- Paracetamol
- first-line therapy
- NSAIDS
- Act on the COX enzyme system. Inhibits synthesis of prostaglandins & thromboxanes. Reversibly inhibits COX1 & COX2 enzymes as well as thromboxane synthase. eg ibuprofen, diclofenac, naproxen Anti-inflammatory effect mainly due to inhibition of COX2. Therapeutic effects: 1. anti-inflammatory 2. anti-pyretic 3. analgesic
- Corticostereoids
- intra-articular corticostereoid injections
- Paracetamol
- Non pharmacological
Gout
- Painful inflammatory monoarthritis of joints & soft tissue due to deposition of sodium urate crystals in one or more joints.
- raised uric acid in blood which crystallises out in joints/tendons and surrounding tissue
- under excretion of uric acid (90%)
- overproduction of uric acid (10%)
- Uric acid - final product of purine metabolism
- intermittent painful attacks
- men
- joints of the feet and ankle most commonly affected (podagra)
- red, hot, swollen
- raised uric acid in blood which crystallises out in joints/tendons and surrounding tissue
- Triggers
- Trauma
- Drugs eg diuretics, cytotoxics
- alcohol abuse
- Dietary excess
- severe dieting
- obesity
- stress
- Management
- non-pharmacological
- reduce alcohol intake
- Avoid beer, stout, port and other fortified wines
- avoid fructose
- sugary soft drinks
- fructose rich fruits
- reduce weight
- restrict intake of purine-rich foods
- red meat
- liver
- kidneys
- shellfish
- yeast extract
- include vegetable source of protein in diet
- restrict overall protein intake
- drink >2L of water daily
- acute gout
- NSAIDs
- first line
- diclofenac, naproxen
- COXIBs
- lower GI risks than NSAIDs
- etericoxib
- only COXIB licensed for gout
- Colchicine
- -factors (chemotactic) released which stimulates neutrophil migration into the joint -neutrophils engulf urate crystals & release inflammatory mediators
- MOA: reacts with tubulin & selectively inhibits microtubule assembly: reduces neutrophil migration into affected joint & phagocytosis
- SE: GI (abdo pain & diarrhoea)
- 500 mcg 2-4 times a day until symptom resolution
- MAX 6mg/course
- not to be repeated within 3 days
- do not use in pregnancy!
- drug of choice for
- hypertension & HF (no fluid ret)
- renal impairment
- PUD
- anti coagulant patients
- Corticostereoids
- Do not use aspirin at analgesic doses - can worsen gout
- NSAIDs
- Chronic gout
- prophylaxis initiated 2-3 weeks after acute attack
- xanthine oxidase inhibitors
- allopurinol
- 1st choice
- co administration of colchicine or NSAIDs for 1st 6mths
- febuxostat
- allopurinol
- uricosurics
- Sulfinpyrazone
- increases excretion of uric acid in urine by inhibiting its reabsorption
- non-pharmacological
- Painful inflammatory monoarthritis of joints & soft tissue due to deposition of sodium urate crystals in one or more joints.
Rheumatoid Arthritis
- pathogenesis of RA 1.antigen presenting cell 2.activate T cells - produce interleukins & gamma interferon 3.stimulates B cells to differentiate into plasma cells 4. stimulate macrophages - IL1 & TNF-a (stimulate osteoclasts and fibroblasts) 5.autoantibodies (RF) produced from plasma cells 6.RF binds with IgG - immune complex - joint deposition 7.fibroblasts - produce enzymes - destroy joint collagen
- chrinic, progressive symmetrical polyarthritis of 3 or more joints
- small joints most likely eg hands & wrists
- but may also affect: hips, elbows, shoulders, knees & ankles
- autoimmune disease due to inflammation in the lining of membranes
- mostly synovial joints
- malaise, anorexia withs symmetrical tender & swollen joints
- pain, swelling and stiffness in joints
- diagnostic criteria: at least 4 of
- early morning stiffness >1hr
- arthritis of 3 or more joints
- arthritis of the hand joints
- rheumatoid nodules
- x-ray changes typical for RA
- serum rheumatoid factor
- extra-articular features of RA
- rheumatoid nodules
- anaemia
- peripheral neuropathy
- kidney disease
- lung disease
- CV disease
- degeneration of cartilage, bone and joint supporting structures
- small joints most likely eg hands & wrists
- Management
- non pharmacoloical
- rest
- physiotherapy
- psychological support
- occupational therapy
- DMARDs
- -reduce inflammation and delay progression of joint damage & disability -preserve joint function -no evidence of superiority of one DEMARD over another
- onset of effect: 4-16 weeks
- full therapeutic response: 4-6mths
- 1st line: METHOTREXATE
- more rapid onset of action than other DMARDs
- antifolate
- inhibits dihydrofolate reductase
- cytotoxic & immunosuppressant
- 7.5-10mg/WEEK
- max 20mg/week max SC 25mg/week
- +folic acid on diff day
- rapid absorption from gi
- teratogenic
- ADRs
- GI
- Liver
- blood dyscrasias
- pulmonary
- monitoring
- chest x-ray (last 6mths)
- FBC, LFTs, U+E, creatinine
- every 2 weeks until stable for 6 weeks then every 1mth
- some patients: pulmonary function tests
- sulfasalazine
- hydroxychloroquine
- leflunomide
- gold salts
- Biologicals
- TNF-alpha: affects cellular function via action at specific membrane bound TNF receptors
- anti TNF drugs neutralise the pro-inflammatory activity of TNF-alpha
- only use if at least 2 DMARDs tried and failed!!
- adalimumab
- MOA: binds to TNF-alpa neutralising its activity
- with MTX or alone
- etanercept
- MOA: competitive inhibitor of TNF-alpha at its receptor site
- with MTX or alone
- infliximab
- MOA: binds to TNF-alpha neutralising its activity
- must be given with MTX
- anti TNF drugs neutralise the pro-inflammatory activity of TNF-alpha
- TNF-alpha: affects cellular function via action at specific membrane bound TNF receptors
- non pharmacoloical
Información
- Descripción
- pham1008 Mapa Mental sobre Musculoskeletal Disorders, creado por Karo el 28/04/2013.
- Creado por
- Karo
- Visitas
- 345
- Etiquetas
- Valoración