
Flashcards
ALF and ascites
Cards in this deck (45)
- 1What are the characteristic signs of acute liver failure?Jaundice
Asterixis
Confusion - 2What are the four systemic features of ALF?Acute renal failure
Metabolic derangement
Haemodynamic changes
Hepatic encephalopathy - 3What are the initial investigations in ALFFBC and group and save
U&Es
LFTs, clotting and albumin
Glucose
ABG to measure lactate and pH
CXR
Blood, urine and sputum cultures (ALF often leads to infection) - 4Which LFT is significantly raised in cholestatic causes of ALF?Gamma-glutamyl transferase (GGT)
- 5What is the AST/ALT ratio likely to be like in hepatocellular causes of ALF?AST/ALT>5x the upper limit
- 6What does AST>ALT indicate?Established cirrhosis
(aSt-Cirrhosis) - 7What does ALT> AST indicate?ALF or chronic disease without cirrhosis
- 8What does ALT/AST in the thousands indicate ?Viral, drug or ischaemic causes of ALF
- 9What imaging would you use for ALF?Ultrasound
CT/MRI if there is massive ascites - 10Which further investigations would you carry out to distinguish between the differential diagnosis of ALF? (Liver Screen)Viral Serology
Autoimmune screen (ANA, AMA, SMA)
Caeruloplasmin levels and urinary copper
Ferritin and TIBC
Alpha-1-antitrypsin levels
Paracetamol and toxicology screen - 11What is viral serology used to identify in ALF?Hep A, B, C
- 12What could a positive antinuclear antibody (ANA) indicate?Autoimmune Hepatitis
- 13What could a positive anti-mitochondrial antibody (AMA) indicate?Primary Biliary Cirrhosis, Autoimmune Hepatitis
- 14What could a positive anti-smooth muscle antibody (SMA) indicate?Primary Biliary Cirrhosis, Autoimmune Hepatitis
- 15What tests would be used for Wilson's disease?Caeruloplasmin levels and urinary copper
- 16What test would be used for hereditary haemochromatosis?Ferritin levels and total iron binding capacity (TBIC)
- 17How would you manage a patient with ALF?Intubation may be needed
Risk of shock so monitor urine and blood P
+ give fluid resuscitation + inotropes
Vit K to increase PT
Prophylactic IV Taz and Fluconazole
Lactulose to reduce encephalopathy
If AKI then haemodialysis
Transplant waiting list - 18What is therapeutic dose of paracetamol and how much is needed to cause damage?Therapeutic- 4g/day
Damage->10g/day (75mg/kg) - 19How does paracetamol damage the liver?The NAPQI metabolite deplete the glutathione (antioxidants) stores and directly damages the liver cells
- 20How do patients with paracetamol overdosing usually present?First 24 hours: Nausea & vomiting, generally unwell
After 48 hours: Jaundice, hypoglycaemia, encephalopathy - 21What drug level is it important to measure and when?Plasma paracetamol levels and after 4 hours of ingesting the drug
- 22What is the antidote to paracetamol overdose?N-acetylcysteine within 8 hours of overdose, still give to late presenters
- 23What bag dosage of N-acetylcysteine is given in a paracetamol overdose?1hr: 150mg/kg acetylcysteine in 200ml 5% glucose solution
4 hr: 50mg/kg acetylcysteine in 500ml 5% glucose solution
16hr: 100mg/kg acetylcysteine in 1000ml 5% glucose solution - 24How do acute hepatitis viruses (A, B & E) present?Jaundice and tender hepatomegaly. Hep A has a 6 week prodromal phase. All will cause an increase in ALT. Diagnosis made by testing for respective antibodies.
- 25What is diagnosed after all other causes of liver failure have been excluded?Seronegative ALF:
Related to autoimmune, viral, medication, toxin causes - 26How does seronegative ALF present?Few days of non-specific symptoms. Patient may be on multiple medications and will usually have a recent history of foreign travel
- 27What is the pathophysiology of Wilson's disease?Impaired incorporation of copper into caeruloplasmin, causing build up in tissues and decreased excretion in the bile
- 28How is Wilson's disease diagnosed?Kayser-Fleischer rings, low caeruloplasmin, low serum copper, positive liver histology and genetic analysis
- 29How is Wilson's disease treated?Avoid foods with high copper content and give penicillamine
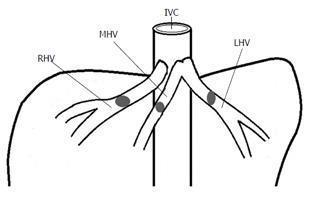
- 30What is Budd-Chiari syndrome?Obstruction by one of the main hepatic veins by thrombus formation
- 31How can patients with Budd-Chiari Syndrome present?Portal hypertension (ascites) and can lead to ALF in rare cases
- 32How is Budd-Chiari Syndrome diagnosed?Dopper USS, contrast CT, Venogrophy
- 33How do you treat Budd-Chiari syndrome?Thrombolysis and anticoagulation.
TIPSS procedure - 34What diseases can Budd-Chiari Syndrome be associated with?Thrombophilia, hepatocellular carcinoma and abnormalities of the IVC
- 35What are the 4 possible causes of ascites?1. Portal hypertension
2. Peritoneal inflammation
3. Reduced plasma oncotic pressure
4. Impaired lymphathic drainage - 36What can cause portal hypertension?Liver disease
Right Heart Failure
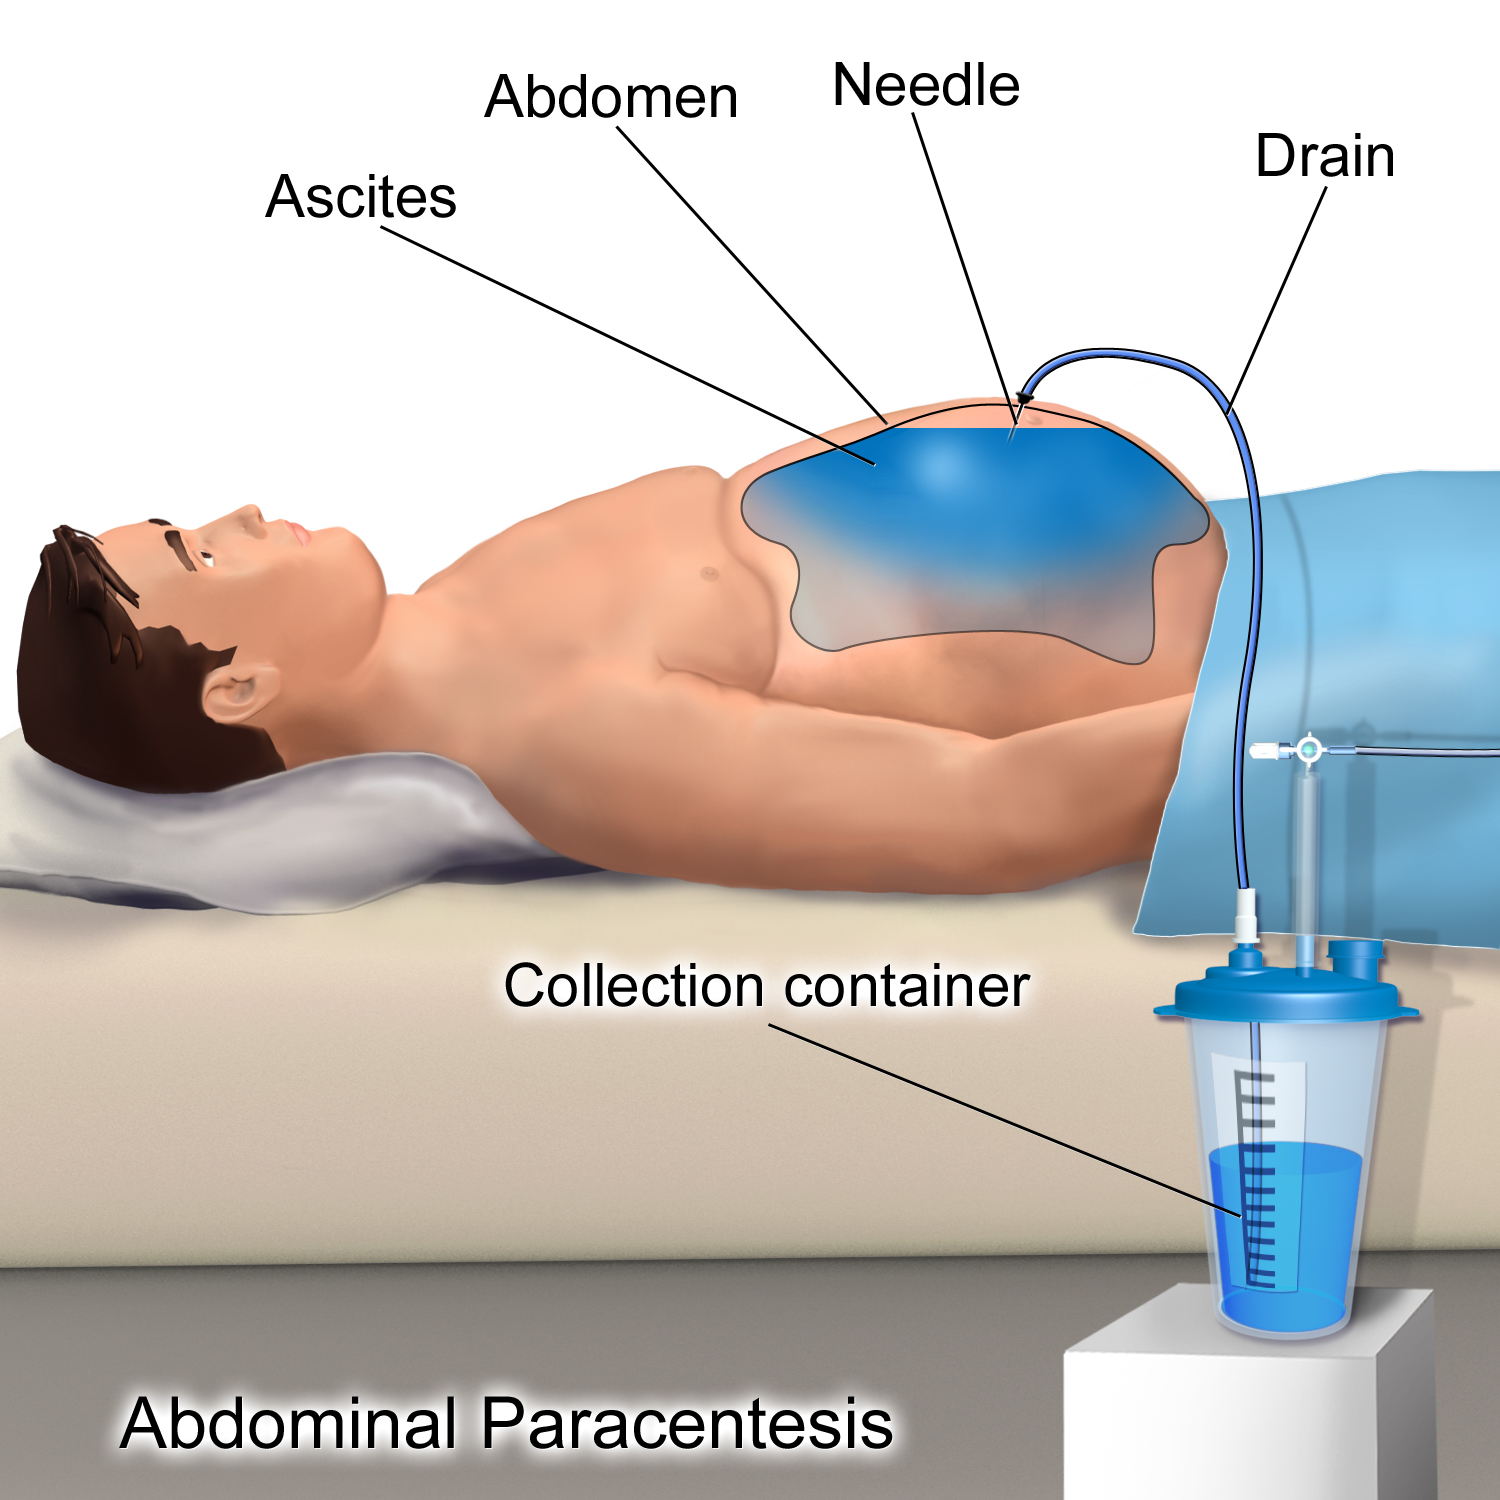
Veno-occlusive disease - 37What should ascites fluid be sent off for ?MC&S, glucose, red cell count, amylase, cytology and protein levels
- 38What do high neutrophils in an ascitic sample mean?SBP (spontaneous bacterial peritonitis) or TB
- 39What could low glucose indicate?TB or malignancy
- 40What are protein levels used to calculate?Serum ascites albumin gradient
- 41What does SA-AG indicate when it is >1.1g/dL?Portal hypertension
- 42What does SA-AG <1.1g/dL indicate?Exudative ascites, more likely to be cancer or inflammation
- 43How do you manage portal hypertensive ascites?Salt and fluid restriction.
Diuretics (spironolactone 100mg and furosemide 40mg)
if this doesn't work: TIPSS procedure - 44How to manage refractory non-portal hypertensive ascites?
- 45What should be given to patients with high risk of SBP ?Prophylactic antibiotics - ciprofloxacin