
Mind map
Dysphagia Other Assessments
Map content
Dysphagia Other Assessments
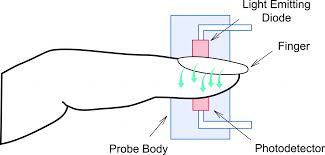
Pulse Oxometry
- Smith et al. (00) Screen by saturation detects 86% of asp./pen. follow immediate w. bedside S.A. (best. pos prediction)
- Sellars et al (98) - small study. Not a clear cut relationship between arterial oxygenation and aspiration. Some support for altered ox and oral feeding in people with dys.
- i.e. that resp status may be altered
- Non invasive, minimal patient cooperation
- Desaturate by 2% or more, NBM*
- Doesn't tell you exactly the mechanism causing the desaturation
- Collins & Bakheit (97) - Pulse ox is a reliable method of detection of asp in most dys patients. Careful if they have pulmonary disease though
3 Oz water swallow test
Cervical Auscultation
- Doesn't tell you what the problem is, only that there may be one
- Mills (13) "C.A. should be used as a screen only"
- Leslie et al. (07) no evidence to suggest that sounds are consistenly associated with physiologic event!!
- Hibbs (13) found agreement between C.A. and V.F. findings on determining oral delay and aspiration
- Stroud (02) Did not find SLT's classification reliable. However, some individual SLTs = high reliability - what internal criteria using???
- Median line cricoid
- Sound of bubbles if resp. mixed with fluid
- Can be digital
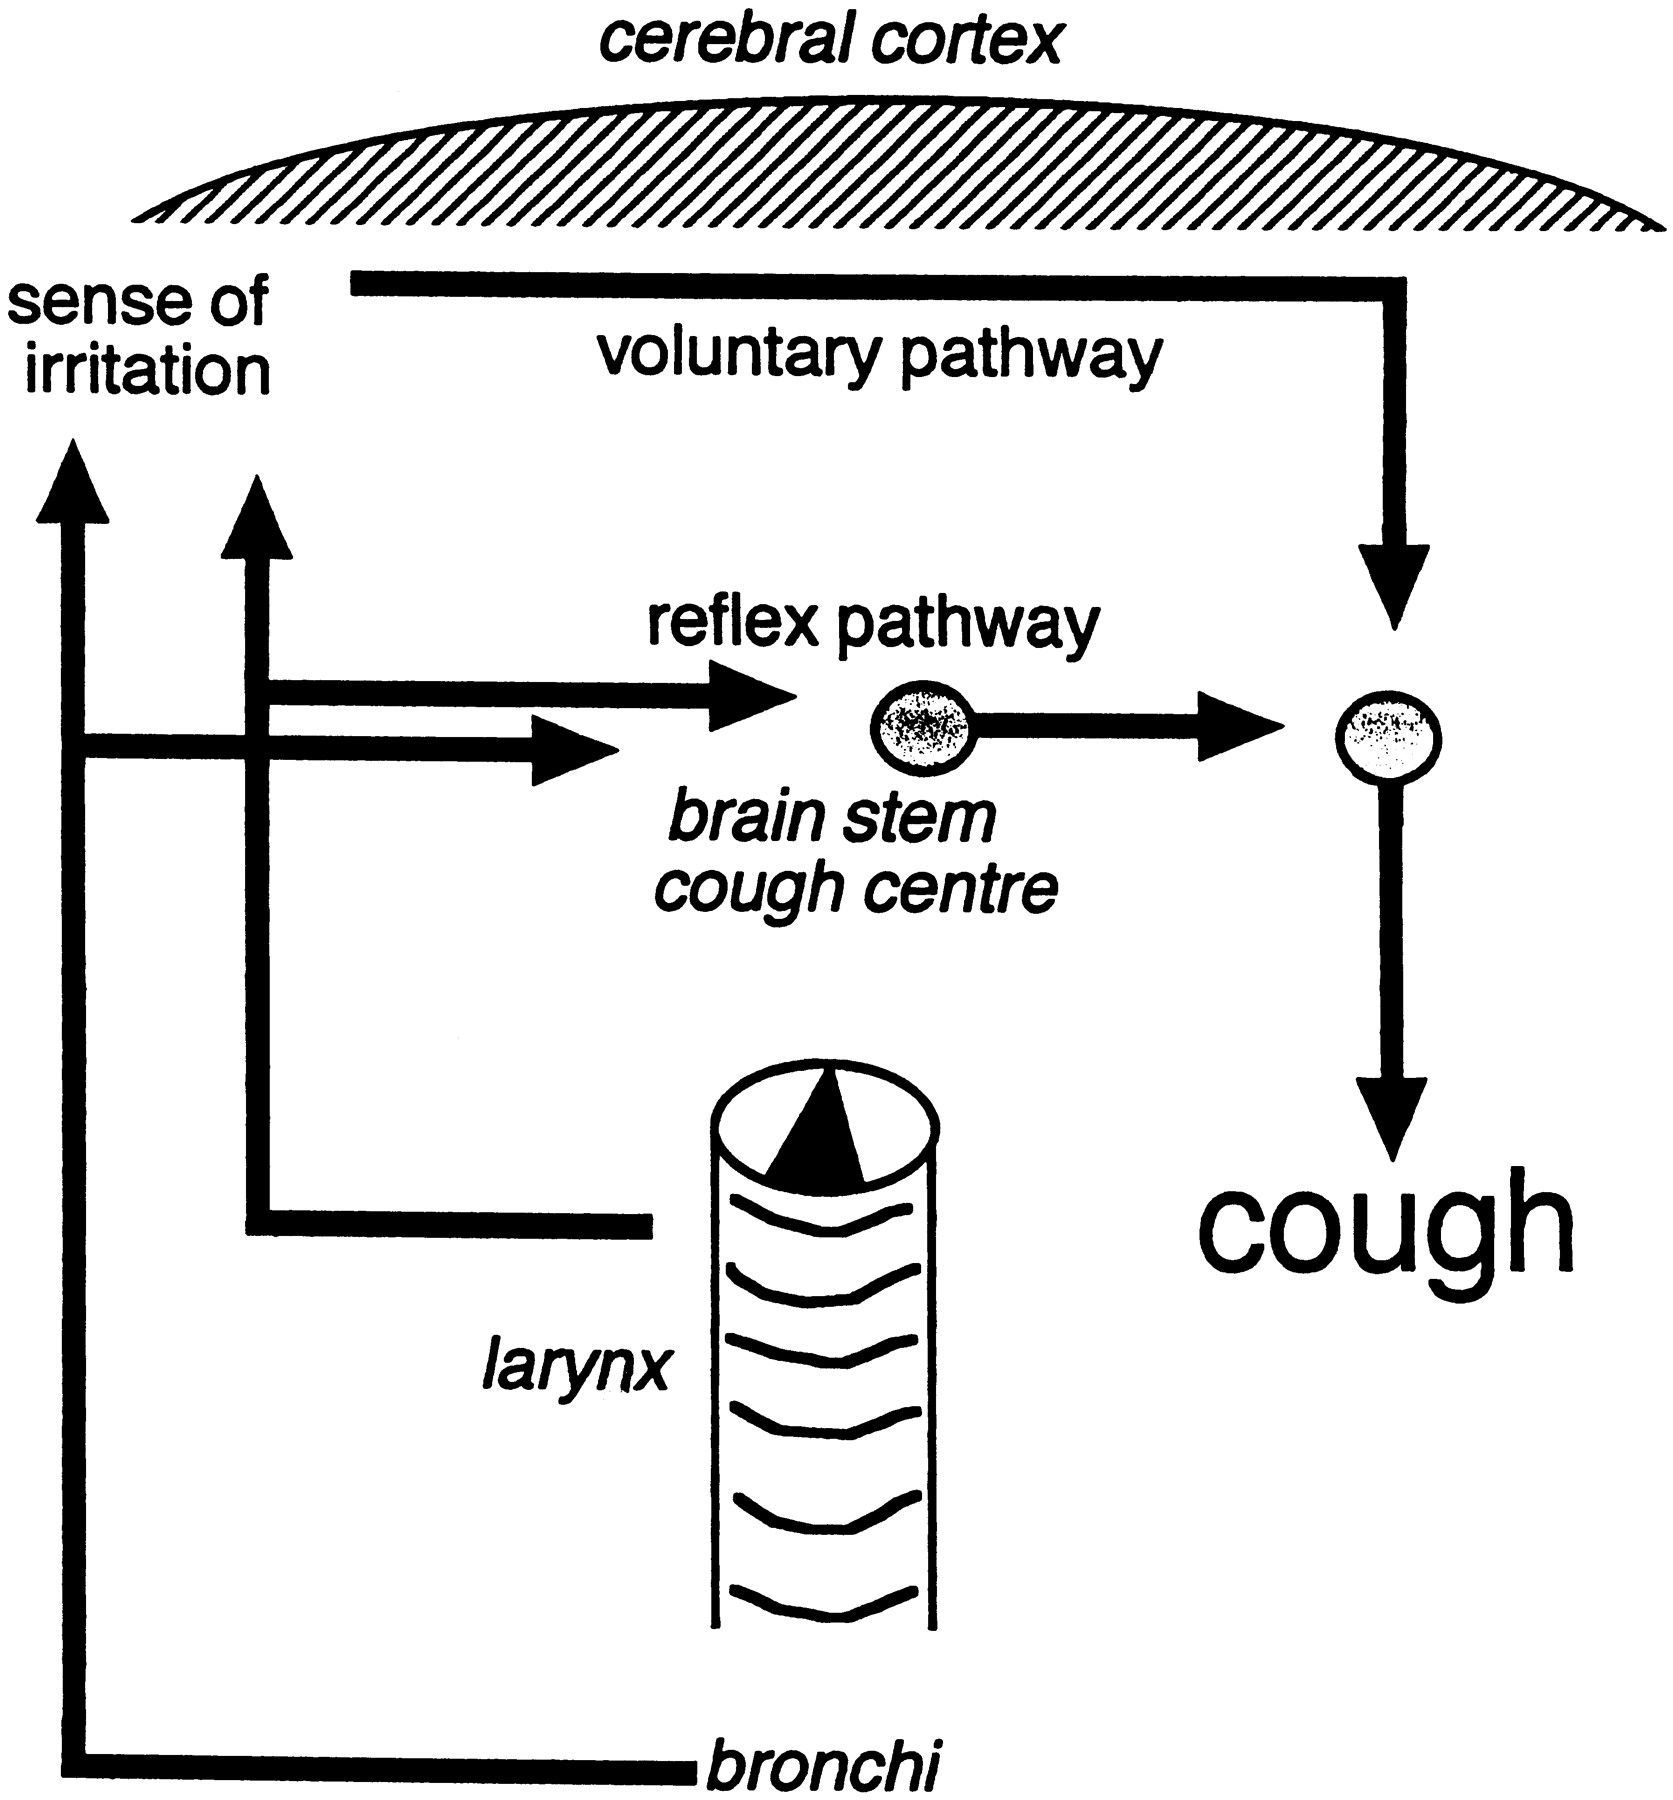
Cough Reflex Testing
- Miles et al (13), found positive association between failed CRT and aspiration but also weak CRT and weak resp to asp. NUMBERS TOO SMALL for statistical anal.
- Threshold at which an individual can no longer supress a cough
- 92.5% people (healthy) show natural cough, 0.8mol/L of irritant (nebulized citric acid e.g.)
- Nebulizer may rule out those with weak face muscles (confound)
- Pass if you cough.
- Clinicians judge if strong or weak
- Results not used along but combined with MDT dysp. management & other ass.
- Does not answer dysphagia severity or pnumonia risk
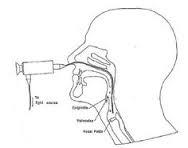
Fibreoptic Evaluation of swallowing (FEES)
- Flexible endoscope inserted through nose
- Coloured food / liquid of different consistencies given to patient to assess swallow
- Colodny (02) Fees more reliable on ass. penetration that VF, VF better on severity of aspiration, Equal on desc. betwn pen and asp
- Leder & Espinosa (02), stroke patients (blind testing). Clinical examination correctly identified 19 of 49 people at risk, but missed 3 people picked up on FEES. Clinical exam also INCORRECTLY identified 19 as being at risk (when not of FEES). Clinical exam less reliable
- Image qual not as good as rigid endoscope
- Could detect posterior overspill before swallow trigger
- Pharyngeal residue
- Suitable diet in terms of consistency
- Does not visualise oral stage, or ACTUAL SWALLOW due to white out
- Pos better for patients with lower awareness / cog issues, but does not give info about their mental state like VF
- No oes. stage or bolus flow
- Does not visualise oral stage, or ACTUAL SWALLOW due to white out
- Puffs of air to test sensory reception
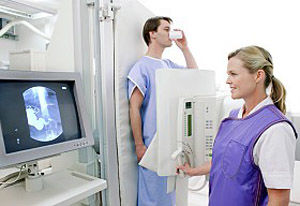
Videoflouoroscopy (VFS)
- Bolus flow and biomechanics
- TIMING
- DIRECTION
- CLEARANCE
- Gold standard: ORAL, PHARNG, & OES stages observed
- Determining swallow safety
- Effects of compensatory managment
- Determinatino of app diet
- Planning of rehab approaches
- AIRWAY invasion, PRE, DURING or POST - only see on VFS
- Radiation exposure limits length of ass.
- Patient positioning prob with hemiplegia
- Preferred initial for STROKE PATIENTS (Daniels & HUckabee 14)
- View frame by frame, w sound 30fps
- Usually lateral position
- POst swallow residue, might do Ant - post position to see if uni, or bilateral
- Unilateral pharyn. hemiparesis results in residue in contralesional pyriform sinus
- Also good to identify unilateral VF paresis
- POst swallow residue, might do Ant - post position to see if uni, or bilateral
- Usually lateral position
- IF NG in, may affect stage of transit duration and UES opening (Huggins et al. 99)
- May also result in early evocation of pharn swallow - sometimes removed for VFSS
- Protocol driven or patient driven... For STROKE combination of the two recommended
- Small vol thin liquid: less risk is asp and also less residual - therby smaller effect on subsequent swallows
- SEQUENTIAL SWALLOWS evaluated if managing large volume already
- OES. dysfunction may contribute to phar. dysfunction (Martin-Harris & Easterling 06)
- Only cursory screen on VFSS
- OES. dysfunction may contribute to phar. dysfunction (Martin-Harris & Easterling 06)
- SEQUENTIAL SWALLOWS evaluated if managing large volume already
- SELF admin preferred
- Cup vs straw not empirically investigated
- Calibrated volumes can help w recommendations, 3-5ml uo to 20-25ml (normal size bolus volume)
- Some people demo a 'warm up' period
- Small vol thin liquid: less risk is asp and also less residual - therby smaller effect on subsequent swallows
- THINGS TRIALLED
- 1. Postural compensation
- 2. Consistency mod.
- How many cues nec to instigate a strategy
- 1. Postural compensation
- SOLIDS: Barium alone or mixed with food, e.g. mash
- Bolus flow and biomechanics
Images and files in the map
Information
- Description
- Dysphagia Mind Map on Dysphagia Other Assessments, created by Heather Snaith on 25/11/2016.
- Created by
- Heather Snaith
- Views
- 4
- Rating