
Flashcards
14. Infection and osteomyelitis
Cards in this deck (49)
- 1Musculoskeletal Infection - 3 categoriesOsteomyelitis
Infectious arthritis (septic arthritis)
Cellulitis - 2Osteomyelitis Three mechanisms by which infection reaches bone? (3)Haematogenous spread
Contiguous source
Direct implantation - 3Haematogenous spread.This relates to infection spread via the blood stream from a remote site of infection - an example would be a UTI leading to infection in the foot. Infection enters the bone via the nutrient arteries.
- 4Contiguous sourceInfection spread to the bone from neighbouring structures. This is the common cause of osteomyelitis in the feet particularly in diabetic patients and those with poor vascular supply to the foot.
- 5Direct implantationThis relates to infection spread to the bone by direct puncture which may be the result of injury or indeed surgery.
- 6Within the adult population osteomyelitis of the foot is more likely caused by? If you will be working in a paediatric environment then it is particularly important to recognise that ............... spread of infection is more common in children. The infection usually focussed on the metaphysis of the bone. This is the result of differing osseous-vascular supply in children than in adults. In adults the shaft of long bones is the most common site of infection. The most common cause is which organism?Contiguous or direct implantation.
Haematogenous
Staphylococcus aureus. - 7Infectious Arthritis (Septic Arthritis) Three mechanisms by which infection reaches joints? (3)Haematogenous spread
Contiguous source
Direct implantation - 8Haematogenous spread As with osteomyelitis it is possible for infection to travel from a remote site via the blood stream and result in infection of the joint. Contiguous source? Direct implantation?*Infection from adjacent soft tissues but also can be via adjacent bone.
*In podiatry and surgical practice direct implantation may follow joint injection, surgery to the joint (i.e cheilectomy, arthroscopy, joint replacement), penetrating injury. - 9Soft tissue infection (Cellulitis) Infection of the skin is usually from a break in skin - (2 examples) Cellulitis can lead to blood poisoning known as septicaemia which can lead to death.Penetrating injury
Ulceration (vascular / diabetic) - 10For musculoskeletal infection what is the first line imaging modality and may be sufficient for diagnosis?Plain xray
- 11What type of imaging can demonstrate the extent of infection in bones and soft tissues and at times can help to make a specific diagnosis?CT scans
- 12What else can be particularly useful in infection?Scintigraphy
- 13What is the gold standard diagnostic test for osteomyelitis?Biopsy
- 14Radiographs - earliest changes are seen in adjacent soft tissues? What are the changes? (3)Swelling in adjacent soft tissues +/- muscle outlines
Loss or blurring of normal fat planes
Effusion in adjacent joint (possible) - 15Radiographs - Bone changes? (7) R, P, F, E, L, N, PRegional osteopaenia
Periosteal reaction
Focal bone lysis
Endosteal scalloping
Loss of bony trabecular architecture
New bone apposition
Peripheral sclerosis - 16Osteomyelitis must extend at least ...cm and compromise ..........% of bone mineral content to produce noticeable changes on a plain xray. Early findings can be very subtle and may not be seen on plain xray until .......days in children and .......... in adults.1
30-50%
5-7 days
10-14 days - 17Regional OsteopeniaA localized or regional decrease in bone mineral density
This can be seen in early osteomyelitis - 18However there are other causes, which are? (3)Disuse (from immobilization ie walker boots & casts)
Complex Regional Pain Syndrome
Regional migratory osteoporosis - 19Periosteal ReactionNon-specific finding which occurs with periosteal irritation which can be classed as either Benign or Aggressive.
- 20BenignThickening of the cortex in a wavy or uniform appearance.
- 21AggressiveCortex may appear lamellated, amorphous or sun burst like.
- 22Focal Bone LysisLytic lesions (appearing low density or black).
A possible finding in osteomyelitis - 23Unfortunately this finding is not diagnostic and there are many differential diagnosis for lytic bone lesions that must be considered?[FOG MACHINES]
F: fibrous dysplasia or fibrous cortical defect (FCD)
O: osteoblastoma
G: giant cell tumour (GCT)
M: metastasis(es)/myeloma
A: aneurysmal bone cyst (ABC)
C: chondroblastoma or chondromyxoid fibroma
H: hyperparathyroidism (brown tumour)
I: infection (osteomyelitis)
N: non-ossifying fibroma (NOF)
E: enchondroma or eosinophilic granuloma (EG)
S: simple (unicameral) bone cyst - 24Endosteal ScallopingEndosteal scalloping refers to erosion of the inner cortex of the bone.
Non-specific - 25Can be caused by infection but differential diagnosis include? (2)Enchondroma
Multiple myeloma - 26Loss of bony trabecular architecture due to? (2)Due to bone death
Osteolytic areas in the bone - 27New Bone Formation (2)Inflammation and pus create expansion of bone
Irregular appearance - 28Sclerotic appearanceLate change in osteomyelitis
- 29Other Involucruma layer of new bone growth outside existing bone (after 20 days)
- 30Sequestrumis a piece of dead bone that has become separated during the process of necrosis from normal bone (develops after 30 days)
- 31CloacaSpace in which dead bone resides
- 32Classification systems for osteomyelitis (2)There are a number of systems but the 2 most common:
Waldvogel system
Cierny-Mader classification - 33Waldvogel systemosteomyelitis is first described according to duration, either acute or chronic. Second, the disease is classified according to source of infection. A final category of the classification is vascular insufficiency.
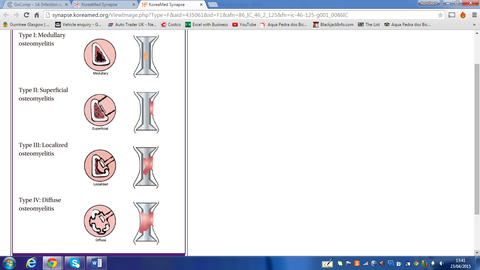
- 34Cierny-Mader classificationThe Cierny-Mader classification is a clinical classification based on anatomic, clinical, and radiologic features. It characterizes osteomyelitis as being in one of four anatomic stages.
- 35Stages (4)Medullary
Superficial
Localised
Diffuse - 36Stage I: Medullaryconfined to the medullary cavity of the bone.
A) Host, good systemic defence and local vascularity - 37Stage II: SuperficialOsteomyelitis involves only the cortical bone and most often originates from a direct inoculation or a contiguous focus infection.
B) Host, good systemic and local compromise - 38Stage III: LocalizedStage 3, or localized, osteomyelitis usually involves both cortical and medullary bone. In this stage, the bone remains stable, and the infectious process does not involve the entire bone diameter. C) Host, non-candidate for surgery with treatment more problematic than disease process
- 39Stage IV: DiffuseStage 4, or diffuse, osteomyelitis involves the entire thickness of the bone, with loss of stability, as in infected nonunion.
- 40VISUAL IMAGE OF OSTEOMYELITIS
- 41Clinical Findings (12)None
Pain
Tenderness
Fever
HA
Nausea Vomiting
Erythema
Swelling
Sinus tract
Drainage
Limp
Fluctuence - 42SEPSIS Systemic Inflammatory Response Syndrome (SIRS) Pt must have 2 or more of the following?-Temp <36 or > 38.3
-HR >90 bpm
-Resp >20 breaths per min or PaCO2 <32 mm Hg
-WBC count >12,000 / uL, <4,000 / uL or 10% immature (band) forms - 43Differential Diagnosis for Osteomyelitis (7)Diabetic Charcot
Other neuropathic osteoarthropathy
Aseptic arthritis
Acute Trauma
Gout
Recent surgery
Ewings sarcoma - 44Lab Tests for osteomyelitis (6)FBC, ESR and CRP (WCC usually raised but not always!)
Blood culture (positive in about 60% of cases)
Wound swab of any expressed pus
Bone culture (or curettage via ulcer)
(Gold standard)
Lab tests are less reliable in chronic cases - 45MRINo radiation
Good soft tissue imaging
T1 dark
T2 bright or mixed - 46Nuclear Medicine Scan Overall accuracy %? Useful in.............osteomyelitis?Overall accuracy 90%
Gallium-67
Scans are 100% sensitive
increased uptake 1 day earlier than TC-99m MDP
Useful in chronic osteomyelitis
Technetium 99
83% sensitivity - 47Treatment (6)-Antibiotics - correct organism
-Surgical Bone Debridement –
-Hardware removal – may require staged surgery
-Irrigation
-Wound care
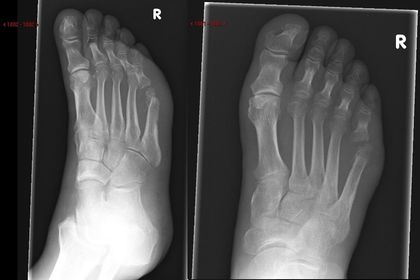
-Monitoring - 48—Osteomyelitis and septic arthritis at the 5th MTPJ
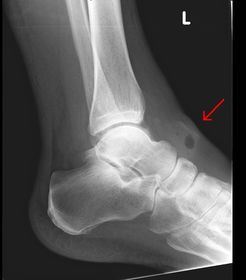
- 49—Gas in the tissues over the left ankle. This is always a serious sign. Must have quick admission to hospital via A&E or via your outpatient dept if you are hospital based..
Information
- Description
- University Medicine, Surgery & Radiology Flashcards on 14. Infection and osteomyelitis, created by Morgan Morgan on 29/03/2015.
- Created by
- Morgan Morgan
- Views
- 27
- Rating