
Flashcards
PACES Questions
Cards in this deck (146)
- 11. List the main causes of chronic liver disease1. Alcohol
2. Viral hepatitis
3. Autoimmune hepatitis
4. Primary biliary cirrhosis - 22. What investigations would you initiate to investigate the underlying cause of chronic liver disease?Viral and autoimmune hepatitis screen
Metabolic screen(ceruloplasmin, ferritin, alpha-1 antitrypsin)
AFP (hepaocellular carcinoma)
liver US and biopsy. - 33. Which three things suggest decompensated liver function?1. Jaundice
2. Ascites
3. Encephalopathy (asterixis) - 44. Up to how many spider naevi can be considered normal on examination of a patient?4
- 55 List the main stigmata of chronic liver diseaseSpider angioma (naevi)
Jaundice
Scleral icterus
Palmar erythema
Gynecomastia
Encephalopathy
Asterixis (liver flap) - 66. What are the main feature of decompensated pulmonary fibrosis?Cor pulmonale
central cyanosis
(Hypercapnic flap?) - 77. What are the main causes of pulmonary fibrosis?Idiopathic (70%)
Connective tissue disease (RA, SLE)
Extrinsic Allergic Aveolitis
Industrial lung disease (asbestosis, silicosis)
Drugs (methotrexate, amiodarone) - 88. What Ix would you initiate for pulmonary fibrosis?FBC (incl ESR due to CTD)
ABG (Type 1 failure)
CXR (reduce lung vol, diffuse reticular nodular shadowing + honeycombing in severe disease)
High res CT - 99. Main points to elicit in the Hx of a Bell's palsy?Onset sudden or over several hours?
Severe pain at Sx onset? (RHS/bad prognosis)
Signs of stroke? (arm or leg weakness)
Any blisters in mouth/tongue? Tinnitus, hearing loss or vertigo (vestibulocochlear involvement) - 1010. What would you examine to assess a Bell's palsy?CN 5, 7 (excluding Glabellar sparing) and 8
nb. The corneal reflex is often absent.
The ears and oral cavity looking for herpetic rashes (RHS). - 1111. What would your Mx plan for a Bell's palsy consist of?1. Steroids in the acute phase
2. Slit lamp eye exam (corneal ulcers)
3. Otoscopic ear exam. - 1212. What are the functions of the facial nerve?-Blinking and closing the eyes, smiling, frowning, flaring nostrils and raising eyebrows.
-Lacrimation and salivation.
-Taste in the anterior two-thirds of the tongue, via the chorda tympani nerve.
-Innervates the stapedius muscle of the inner ear (via tympanic branch) - 1313What are the muscles of mastication and what is their innervation?The masseter, temporals, medial pterygoid, and lateral pterygoid are innervated by the 3rd (mandibular) branch of the trigeminal nerve
- 1414. Which nerve mediates both the efferent and afferent limb of the jaw jerk?The trigeminal nerve
- 1515. The combination of pes caves, muscle wasting, a high stepping gait and a predominantly motor peripheral neuropathy is characteristic of which condition?Charcot-Marie-Tooth (aka Hereditary Sensory Motor Neuropathy and Peroneal Muscular Atrophy. Axonal and demyelinating forms can be differentiated by EP.
- 1616. What investigations would you request to investigate episodes of collapse of a presumed cardiac origin?FBC(?anaemia)
U&E(?arrhythmia)
TFT
ECG + 24 hour tape
Echocardiogram
Tilt test - 1717. After valvular replacement surgery how should a patient ideally be followed up?In the short term, post op, est. that the prosthetic valve is well seated, not sig regurgitant, and no para-prosthetic leak.
Once est. long term FU should is usually an annual echo. - 1818. How do you assess the risk of a prosthetic valve developing thrombus?Tissue valves carry low risk and usually require only anti-platelets. Both aortic and mitral metallic valves are at thrombus risk, mitral>aortic, due to lower trans-mitral velocities and associated AF and require anti-coagulation with wafarin.
- 1919. What are the indications for urgent aortic valve replacement?1. Symptomatology: incl. new onset angina, dyspnoea or syncope.
2. Using reg echos: precipitous change in LV size or function. - 2020. What are the characteristic features of psoriasis on examination?Well circumscribed erythematous silvery scaly plaques
Nail changes(pitting and onycholysis)
Assymetric joint involvement (esp. DIPJs) - 2121. What are the management options for psoriatic arthropathy?Physio
OT
simple analgesia/NSAIDS
In severe cases: methotrexate or other systemic Tx
(nb.systemic steroids may cause a flare on withdrawal) - 2222. What is the most usual indication for thoracoplasty?Old TB
- 2323. What are the causes of bronchiectasis?Childhood infection (e.g. measles)
Obstruction (tumour, nodes, FB)
CF
Hypogammaglobulinaemia
Kartagener's Syndrome - 2424. What would bronchiectasis show on spirometry?Obstructive pattern (type IV)
red FVC and FEV1
FEV1/FVC <0.7 - 2525. What is the differential for a ejection cardiac murmur?Aortic stenosis
Aortic sclerosis (?doesn't radiate)
HCM (Hokum)
Pulmonary valve stenosis
VSD
Tetralogy of Fallot - 2626. What is the differential for a regurgitant systolic cardiac murmur?Mitral regurg
Tricuspid regurg
VSD (a. Roger's type 1 (with pulm HTN) and 2 (wo pull HTN)
b. slitlike) - 2727. What are indications for thoracoplasty?Cavitary TB
Empyema
Bronchopleural fistula
Persistent spaces following pulmonary resection - 2828. What are the three classical signs of Parkinson's disease?Tremor
Rigidity
Hypokinesia - 2929. What are the classical features of cerebellar syndrome?Dysdiadochokinesia
Ataxia
Nystagmus
Intention tremor
Slurring
Hypotonia - 3030. What is the DDx for expyramidal Sx?Parkinson's
PSP
MSA
Normal pressure hydrocephalus - 3131. What is the differential for hepatomegalyHEPATIC
Heamatological (CLL, haemochromatosis)
Ethanol (ASH and NASH)
PSC, PBC, Portal HTN
Autoimmune or vial hepatitis
Tumour
Infiltration (Wilson's, sarcoid, amyloid, )
Cardiac (CCF, pericarditis) - 3232. What are the causes of Parkinsonian syndrome?Idiopathic
Drugs -(phenothiazides, metoclopramide, haloperidol, reserpine)
Postencephalitis
Cerebral tumours (involving the BG) - 3333. What are the complications of Parkinson's disease?Dysphagia
Constipation
Recurrent falls
Postural hypotension
Memory loss
Depression - 3434. What is the most common organism causing exacerbvation of bronchiectasis?pseudomonas
- 3535. What complications of liver cirrhosis do you know?Ascites
Coagulopathy
Portal HTN
Encephalopathy - 3636. What might precipitate encephalopathy?GI bleed
Infection
Constipation
Increased protein intake
Renal failure
Electrolyte imbalance
Drugs (benzos, opiates) - 3737. How would you Mx a Pt with encephalopathy?Tx precipitating cause
Give lactulose (to decrease ammonia)
Correct hypokalaemia
Involve liver team - 3838. What are the clinical signs of coarctation of the aorta?HTN
Radiofemoral delay
Absent femoral pulses
Mid-systolic or cont murmur
Subscapular bruit
Rib notching (figure of 3 on CXR)
Post-stenotic dilatation of aorta (CXR) - 3939. What at the signs of a third nerve palsy?Eye is deviated downwards and outwards
Ptosis
Pupil dilatation (Surgical -parasymp damage)
No pupil dilatation(medical-no parasymp damage) - 4040. What are common causes of a medical third nerve palsy?Mononeuritis multiplex (eg. DMII)
MS
Midbrain infarction
Migraine - 4141. What are common causes of a surgical third nerve palsy?Cavernous sinus pathology
PCA aneurysm (classically painful) - 4242. What are the contents of the cavernous sinus?O TOM CAT
Oculomotor nerve
Trochlear nerver
Ophthalmic div of 5th
Maxillary div of 5th
Carotid (internal)
Abducens nerve
Trochlear nerve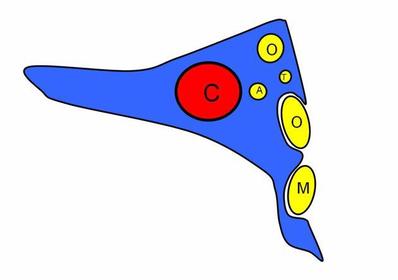
- 4343. What are the typical clinical signs in COPD?Tar stains
CO2 flap and bounding pulse
Central cyanosis
Pursed lips (prolonged expiratory phase)
Use of accessory muscles
Hyper-expanded chest
Crackles if infection present - 4444. What are the signs of cor pulmonale?Loud P2
Rt ventricular heave
Raised JVP
Peripheral oedema - 4545. What is COPD?COPD is a spirometric diagnosis characterised by airflow obstruction which is not fully reversible. It comprises chronic bronchitis with emphysema.
FEV1/FVC<0.7 - 4646. How would you investigate a possible new diagnosis of COPD seen in clinic?Spirometry after bronchodilators
CXR (hyperinflation or other causes of SOB)
FBC (polycythaemia or anaemia)
ABG (type II resp failure)
ECG (Rt heart failure)
Anti-trypsin deficiency (in a young person) - 4747. What Tx would you offer a stable COPD Pt seen in clinic?Smoking cessation clinic
'Reliever' inhaler (e.g. salbutamol)
'Preventor' inhaler (eg. salmeterol or seretide ie. salmeterol + fluticasone)
Aminophylline IV/PO - 4848. What features of a patient's presentation with COPD would suggest LTOT should be considered?FEV1<0.3 of predicted
Peripheral oedema
raised JVP
cyanosis
polycythaemia
Sats<92% on RA - 4949. What are the criteria for LTOT?2 ABGs 3 weeks apart where stable &
PaO2<7.3 or
7.3 - 5050. How long does LTOT need to be used for?At least 15 hours per day
- 5151. Are there any risks associated with aminophylline?Aminophylline has a fairly narrow therapeutic window. Toxicity: nausea, vomiting, diarrhoea, agitation, dilated pupils. Severe toxicity: arrhythmias and convulsions.
Can also cause hypokalaemia. - 5252. What dosing regime would you use for aminophylline?5mg/kg loading over 30mins.
Then:
Infusion of 0.5mk/kg/hour.
Check levels at 24 hours and daily thereafter. - 5353. How would you manage an exacerbation of COPD?Controlled O2 through a venturi mask
Salbutamol and ipratropium nebs
Oral pred
IV aminophylline if poor response to above.
If infective give ABx
NIV if required. - 5454. How and why would you initiate NIV?If after 1 hour of medical Mx the Pt is still acidotic and in type II respiratory failure, then NIV should be considered.
(initially IPAP = 10, PEEP=5 and titrate IPAP us as per ABGs) - 5555. What is alpha-1 antitrypsin deficiency?Alpha-1 antitrypsin is a protease inhibitor produced by the liver. In the lungs this protects alveolar tissue from damage by neutrophil elastase. Deficiency makes COPD likely in the 3rd or 4th decade in a smoker.
Classic pattern: pan lobar emphysema in lower lobes. - 5656. How do you categorise haematological causes of hepatosplenomegaly?With anaemia: myeloproliferative or lymphoproliferative disorders
With lymph nodes: CLL or lymphoma - 5757. How would you CONFIRM a diagnosis of liver cirrhosis?Liver US may be suggestive, but a liver biopsy is required for definitive diagnosis.
- 5858. What is the Child Pughs score used for?59. Prognosis in liver cirrhosis (i.e. predicting 1 and 2 year survival)
- 5960. What features contribute to the Child Pughs score?Bilirubin
Serum albumin
INR
Ascites
Hepatic encephalopathy - 6061. What is the purpose of the Rockall score?To identify patients at risk of an adverse outcome following an acute GI bleed.
- 6162. What factors contribute to the Rockall score?Age
Shock
Co-morbidity
Diagnosis
Evidence of bleeding on endoscopy
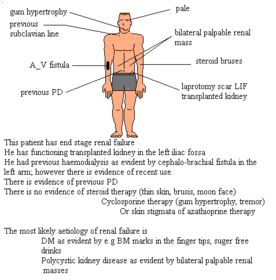
(score<3 = good prognosis, but >8 = high risk) - 6263. What might the examination findings be in a patient with a renal transplant?
- 6364. What are the causes of hepatosplenomegaly?1-Infection: Acute viral hepatitis, Infectious mononucleosis, Cytomegalovirus
2-Haem: Myelo- (CML ,Myelofibrosis) and lympho-(CLL, Hodgkin's Lymphoma) proliferative disease.
Anaemia:Pernicious anaemia, Sickle cell anaemia, Thalassaemia
3-Chronic liver disease and portal hypertension:
Chronic active hepatitis
4-Amyloidosis
5-Acromegaly
6-Systemic lupus erythematosus - 6465. What is your differential for splenomegaly?CHINA
Congestion - portal HTN
Heam (Haemolytic anaemia, SSD, hereditary spherocytosis)
Infection (Malaria, EBV, CMV, HIV)
Neoplastic (CLL, Myelofibrosis, lymphoma)
Autoimmune (sarcoid, amyloid, RA) - 6566. What are the causes of a massive spleen?Three Ms
CML
Myelofibrosis
Malaria - 6667. What drugs do you know which cause pulmonary fibrosis?Chemo Tx: Methotrexate, cyclophosphamide, bleomycin
Cardiac Tx: amiodarone, propanolol
Abx: nitrofurantoin, sulphasalazine - 6768. What is caplan's syndrome?Large rheumatoid nodules in coal workers' lungs.
- 6869. What would you expect to happen to the second heart sound in cor pulmonale?loud HS II
- 6970, What investigations would you do to assess acromegaly?CXR: cardiomegaly
ECG and echo: IHD (DM and HTN)
Pituitary function tests (GH, IGF-1, T4, ACTH, PRL and testosterone)
Glucose: DM
Visual perimetery: bitemporal hemianopia
MRI pituitary - 7071. What are the important points to check for in taking a Hx of acromegaly?Increased hand, feet and jaw size
Change in appearance
Coarse oily skin
Headaches
Peripheral vision loss
Joint pain - 7172. What classes of disease would you consider if asked to examine the hands in PACES?Neurological (nerve entrapment or muscle disease)
Rheum (RA)
Endocrine (acromegaly) - 7273. How long would you expect a bioprosthetic versus a mechanical valve replacement to last?A bioprosthetic valve would be expected to fail within 10-15 years whereas a mechanical valve would function for 20-30 years.
- 7374. What is the mortality rate of a patient with prosthetic valve endocarditis?PVE has an overall mortality of around 50%. If the PVE occurs within 60 days of implantation the mortality is much higher, at around 75%
- 7475. What are the causes of mitral regurgitation?Acute:
IHD, endocarditis (BE)
Chronic:
Degenerative mitral valve disease
Rheumatic heart disease
LV dilatation
mitral valse prolapse
papillary muscle dysfunction
Connective tissue disease - 7576. What are the clinical signs of severity in mitral regurgitation?Soft first heart sound
Palpable thrill
Heaving apex beat
3rd heart sound - 7677. What are the consequences for group 1 and 2 driving licence holders after an MI?Group 1: must stop for 4 weeks but need not inform the DVLA.
Group 2: Must stop and can only retrieve licence if can pass stage 3 of and ETT off anti-anginal Tx. - 7778. What conditions would be expected to give rise to a pure motor syndrome?Distal myopathy
Multifocal motor neuropathy
MND
Myasthenia gravis - 7879. What are the complications of coronary angiography?Heamatoma at access point
Reaction to contrast/renal toxicity
Embolic stroke (1/500) - 7980. What clotting disorders might be associated with DVT?Factor V Leiden
Protein C or S deficiency
Antithrombin III deficiency - 8081. What would your DDx be for a unilateral swollen arm?Lymphoedema (+/- lymphadenopathy, Pancoast's tumour)
Subclavian thrombosis
Superior VC obstruction - 8182. What are the main complications of cardiac valve replacement?Heamorrhage
Thomboembolus
Infective endocarditis - 8283. What is your DDx for spastic paraparesis?Transverse myelitis (eg. MS)
Cord compression
Vit B12 deficiency
MND
Trauma
Cerebral palsy - 8384. What are the radiologic features of osteoarthritis?Narrowing of joint space
Subchondral bone sclerosis
Osteophytes
Bone cysts - 8485. What are the clinical features of osteoarthritis in the hands?Heberden's nodes (osteophytes)
Squaring of the thumb
Reduced ROM - 8586. What is your Ddx for pain and swelling in the joints of the hands?RA
OA
Psoriatic arthritis
Crystal arthropathy - 8687. How would you distinguish between inflammatory and non-inflammatory causes of pain and swelling in the hands?Duration of morning stiffness
Pattern of joint involvement (Prox and symmetric = RA, distal and asymmetric = gout or psoriatic )
Involvement of CMC (carpometacarpal) joint is typical of OA (squaring of thumb). - 8788. What is your Ddx for the cause of end stage renal failure?DM
HTN
Glomerular nephritis
PKD
Reflux nephropathy
Renal vascular disease - 8889. What autoantibodies are seen in lupus?ANA: pres in 95%
Anti-histone: may suggest a drug cause
Anti-dsDNA: v specific but sen = 60%
Anti-Sm: v specific bu sen = 20%
Anti-Ro and ant-La: ANA -ve subacute cutaneous lupus
Antiphospholipid: sens = 40% - 8990. What Ix would you request to investigate the cause of end stage renal disease?BP
Bloods: glucose, renal function, ESR, Ab-screen for vasculitis.
Renal US +/- renal angiography - 9091. What are the stages of kidney failure based on the eGFR levels?1: eGFR>90 + evidence of damage
2: eGFR 60-90 + evidence of damage
3: eGFR 30-60
4: eGFR 15-30
5: eGFR<15 - 9192. What is the frequency of testing and FU required for each of the 5 stages of renal failure?1 & 2: Annually
3: 6 months
4: 3 months
5: 6 weeks - 9293. What are the principal side effects of haemodialysis?Fatigue
Hypotension
Staph infections
Muscle cramps
Itchy skin
Insomnia
Bone and joint pain
Loss of libido
Dry mouth
Anxiety - 9394. What pharmacological agent might you use to treat neuropathic pain in diabetic neuropathy?Tricyclics (eg Amitriptyline) or anticonvulsants (e.g. gabapentin)
IV lidocaine or topical capsaicin in intractable cases - 9495. What are the indications for lobectomy?Old TB
Non-small cell carcinoma
Bronchectasis with recurrent haemoptysis
Solitary pulmonary nodule - 9596. What are some of the complications of lung cancer?SVC obstruction
Recurrent laryngeal nerve palsy
Horner's + wasted small muscles of hand T1
Endocrine: gynaecomastic (ectopic \[\beta\]HCG)
Neuro: LEM, periph neuropathy, proximal myopathy, paraneoplastic cerebellar degeneration.
Derm: acanthosis nigricans, dermatomyositis - 9697. What are the possible treatments for NSCLC?Surgery: lobectomy or pneumonectomy
Rx
Chemo: EGFR +ve - erlotinib - 9798. What are the possble treatments for SCLC?Chemo: benefit with 6 courses.
- 9899. What form might palliative medical care take in lung malignancy?MDT
Dexamethasone and Rx for mets
Stent and dex for SVCO
Rx for haemoptysis, bone pain, cough
Chemical pleurodesis - talc
Opiates for cough and pain - 99100. What is the Abx Tx for pulmonary TB?PIRE
Pyrazinamide (6M): se=hepatitis
Isoniazid (2M): se = periph neuropathy
Rifampicin(2M): se = Hepatitis + rogers the OCP
Ethambutol(6M): retrobulbar neuritis and hepatitis - 100101. What is the Tx for extra pulmonary TB?Abx (PIRE) up to 12 months
Corticosteroids (e.g. pred) if cerebral disease - 101102. When should latent TB be Tx?1. People aged <36
2. People with HIV
3. Healthcare workers
4. People with evidence of scarring caused by TB, as shown on a chest X-ray, but who never received treatment - 102103. What is the Ddx for a new proximal myopathy?Endocrine disorders (Cushing's)
Polymyositis - 103104. How would you distinguish polymyositis from PMR?CK, AST, ALT +/- muscle biopsy
- 104105. Which of the following drugs is contraindicated in severe aortic stenosis?... Beta-blockers, furosemide, spironolactone, ACE inhibitors, amiodarone.ACE inhibitors
- 105106. What are the indications for aortic valve replacement?Secondary dyspnoea, angina, syncope or pre-syncope.
Pressure gradient >60mmHg
Serial evidence of left ventricular dysfunction - 106107. What are the complications of prothetic cardiac valves?All valves
Valvular dysfunction
Infective endocarditis
Metallic only
Microagiopathic haemolytic anaemia
Thromboembolism - 107108. What are the causes of aortic stenosis?Degenerative calcific change
Bicuspid valve
Rheumatic heart disease - 108109. What is the difference between an essential tremor and an intention tremor?An intention tremor is only present as the target is approached, whereas an essential tremor may be present throughout all phases of movement.
- 109110. What is the difference between a stroke and a TIA?They are both focal neurological deficits secondary to a vascular lesions, however a TIA resolves within 24 hours and a stroke does not.
- 110111. What is a consent form 4?A form documenting a decision to perform a procedure on a patient where…
1. The patient lacks capacity to consent to or refuse the treatment.
AND
2. The treatment is in the best interest of the patient. - 111112. What is the differential diagnosis for erythema nodosum?Sarcoidosis
Streptococcal infection
Drugs (sulphonamides)
TB
IBD - 112113. What skin lesions are seen in sarcoid?Lupus pernio
Erythema nodosum
Nodules
Scar infiltration
Plaques - 113114. What are the most common organs affected in sarcoidosis?The lungs (90%), eyes (25%), skin (25%) lymph nodes.
- 114115. What investigations would you request in a suspected new presentation of sarcoid?FBC, U&E, LFTs, ACE level,
CXR
ECG
Pulmonary function tests
Urinalysis
Eye clinic
Specialist referral (eg resp in pulmonary involvement) - 115116. What symptoms should you ask about in sarcoid?Fever, fatigue, SOB, weight loss, vision changes, palpitations, abdominal symptoms, LOC.
- 116117. What treatment approaches exist for sarcoid?Inhaled steroids (for minor cough)
Topical steroids (for skin)
NSAIDs for joint involvement
Oral steroids (prednisolone) - 117118. Which joints are commonly affected by RA?PIPJs, MCPJ, MTPJ, wrists, knees.
- 118119. What are the causes of anaemia in RA?Chronic disease
Felty's syndrome
Irod deficiency
NSAIDS
Folate deficiency
Coexisting pernicious anaemia
B12 deficiency - 119120. What is Felty Syndrome?RS, splenomegaly and neutropenia.
- 120121. What are the grades of diabetic retinopathy?Background: micro-aneurysms, retinal haemorrhages, +/- exudates
Pre-proliferative: cotton wool spots.
Proliferative: new vessel formation.
+/- maculopathy (hard exudates near macula) - 121122. What is the Tx for background, pre-proliferative and proliferative retinopathy?Diabetic control, HTN control etc.
+
Background: annual screening
Pre-proliferative: every 4 months
Active proliferative requires pan-retinal photocoagulation. - 122123. What are the clinical features of cor pulmonale?Parasternal heave
Raised JVP
Ankle/sacral oedema. - 123124. What are the consequences for a group 1 driving licence holder who has a seizure?Stop driving for 1 year, with 3 exceptions
1. First fit: no driving for 6 months
2. All seizures in past 3 years were nocturnal-you can drive.
3. Seizure was provoked (e.g. head injury) - 124125. What are the consequences for a group 2 driving licence holder who has a seizure?Needs to stop driving for 10 years, and can only regain it if fit free for 10 years and off anticonvulsants when reassessed. i.e. end of career.
- 125126. What are the implications for a group 1 driving licence holder who is diabetic?Okay as long as you do not have poor vision, frequent hypos, severe hypos (requiring hospitalisation), or loss of hypo awareness.
- 126127. What are the implications for a group 2 driving licence holder who is diabetic?You can drive even on insulin provided:
1. You have stable glycaemic control over 3 months.
2. You can evidence this using a monitor with a memory function.
3. You are checking your BM at least twice a day. - 127128. What is the target HbA1c for a type II diabetic?<6.5%
- 128129. At what HbA1c would you consider beginning insulin Tx on top of oral Tx for diabetes?>7.5%
- 129130. What are the second line oral Txs available if diet and metformin fail to achieve glycaemic control?1. Sulphonylureas (weight gain + hypo risk)
2. Gliptins
3. GLP-1 mimetic
4. Glitazone
5. SLGT-inhibitor
(2-5 have low hypo risk and are weight neutral or induce weight loss) - 130131. What is your Ddx for binocular diplopia?Nerve palsies
Thyroid eye disease
Myasthenia
Ocular myopathies (e.g. Oculopharyngeal muscular dystrophy) - 131132. What is an Adies pupil? Who gets it typically? What other sign is commonly present?A tonically dilated pupil.
More common in women.
Absent ankle reflexes often accompany it. - 132133. What does an RAPD generally denote?Optic nerve disease
- 133134. What is your differential for painful loss of vision?Retrobulbar neuritis
Giant cell arteritis - 134135. What are the possible components of treatment for hypopituitarism?Hydrocortisone
Thyroxine
Sex hormones (HRT or testosterone)
Desmopressin (ADH anologue) - 135136. What are the clinical features of hyperthyroidism?Eyes: lid retraction & lid lag
Peripheral: agitation, sweating, tremor, palmar erythema, tachy/AF, brisk reflexes - 136137. What are the clinical features of Grave's which distinguish it from simple hyperthyroidism?Eyes: Proptosis, chemosis, ophthalmoplegia
Peripheral: Thyroid acropachy, Pretibial myxoedema - 137138. What are the potential complications of thyroid eye disease?Exposure keratitis
Optic nerve compression
Papilloedema - 138139. What Ix would you undertake for suspected case of Grave's disease?TFTs: TSH and T3/T4
Thyroid autoantibodies
Radioisotope scanning: increased I-131 uptake in Graves, reduced in thyroiditis. - 139140. What treatments exist for Grave's disease?B-block (e.g. propanolol) & Thionamide (e.g. Carbimazole)
Stop at 18 months and assess. 1/3 remain euthyroid.
For other 2/3 repeat thionamide
Radioiodine I-131
Subtotal thyroidectomy. - 140141. What are the salient complications of carbimazole?Bone marrow suppression causing neutropenia and agranulocytosis.
- 141142. What are the clinical features of hypothyroidism?FAT, TIRED and COLD
Fatigue and low energy levels
Cold intolerance
Weight gain - 142143. What drugs are known to cause hypothyroidism?Amiodarone, lithium, thionamides (e.g. carbimazole)
- 143144. What are the causes of a Goitre?Idiopathic
Iodine deficiency
Hashimoto's thyroiditis
Grave's
Goitrogens (e.g. lithium)
Multinodular goitre
Adenoma
Carcinoma. - 144145. What is your differential for a mixed sensorimotor peripheral neuropathy?Diabetes
Hypothyroidism
Charcot-Marie-Tooth
CIDP
CTD (SLE and RA)
POEMS
Paraneoplastic (esp haem)
Drugs (phenytoin) - 145146. What tool would you use to assess risk in a new presentation of angina or hypertension?QRISK2
(USES: age, BP, smoking, ratio of total serum cholesterol to high-density lipoprotein cholesterol) body mass index, ethnicity, deprivation, family history, CKD, RA, AF, DM, and antihypertensive treatment.) - 146147. What is your differential for haemoptysis?LRTI (pneumonia, abscess, TB, fungus)
Malignancy
PE
Vasculitis
Osler-Weber-Rendu
Parenchymal disease (sarcoid, fibrosis)
Cardiac (pulm oedema, mitral stenosis)
Bleeding diathesis