
Notes
No More Tears for Henry
Content of the notes (1)
Page 1
No More Tears for Henry Learning Aims:
1. Understand the complexities of fluid and electrolyte imbalances in children - Dawn
2. Explore health care values from a transcultural perspective - Michelle
3. Identify the impact of a child's illness on individual family members and the family. Apply family theory in caring for children and caregivers - Mary
Required Reading:
Managing acute gastroenteritis among children: Oral rehydration, maintenance, and nutritional therapy. MMWR: Morbidity & Mortality Weekly Report, 52(RR-16), 1-16. Retrieved from http://www.cdc.gov/mmwr/index.html
Canadian fundamentals of nursing (5th ed.). Toronto, ON: Elsevier (pg. 339-345)
Learning Activities for Students
Utilize the a family assessment tool to guide interviewing Henry’s mother
in a role playing situation - CALGARY Assessment tool - Kate
Have students contact a resource agency to learn more about the Mennonite culture and share findings with group - Gabriella
No More Tears for Henry…Chart Data
History of present problem:
2 day history of vomiting and diarrhea; not eating or drinking well
Mother states Henry felt “warm” to touch
Decreased appetite, refusing solids, Henry is drinking small amounts of chamomile tea
Sleeping poorly
Helen reports that Henry has been lethargic, irritable and clingy the last 2 days
Health History:
Mother states her pregnancy with Henry was normal
He was born at 40 weeks gestation; uneventful labour and delivery
His immunizations are up to date.
Family History:
Helen is 23 years old. Husband, Peter, is 28 years old.
At age 2, Henry is the youngest of three children. He has a brother who is 3 and a sister who is 4 ½ years.
Gordon’s Functional Health Patterns
1. Health Perception - Health Management:
Folk remedies are frequently used in this culture. Helen believes the chamomile tea is helping with Henry’s symptoms. When Henry has had an ear infection in the past, he has taken Tylenol to help his symptoms.
The family has a pattern of seeking medical care late in an illness
2. Nutrition/Metabolic:
Henry was breastfed until 1 year of age. He now drinks milk, water or juice from a Sippy cup. He is able to hold his own spoon and feed himself finger foods
Under usual circumstances, Henry is a “good eater”. His diet consists mainly of homemade soups, fruits, vegetables and stews.
For the last 2 days, he has been vomiting and refusing to eat
3. Elimination
Henry is not toilet trained; he wears cloth diapers
He usually has 1 formed bowel movement per day and 5 heavy, wet diapers
For the last 2 days, he has been having 5 liquid, loose stools per day
4. Activity & Exercise
Henry is meeting all developmental milestones appropriately. He started walking at 13 months and is very active.
5. Values & Beliefs
Helen and Peter are Old Order Mennonite and believe in God. Their lives are very tied to their Mennonite culture.
6. Coping and Stress
Helen states that having 3 children under the age of 5 can be very busy and stressful. Henry’s current illness has impacted her ability to spend time with the other children.
7. Sleep & Rest
Henry usually sleeps 10 hours a night and takes a 1-hour afternoon nap. His usual bedtime is 8 pm. He sleeps in a room with his older siblings.
8. Roles & Relationships
Peter works on the family farm. Helen is a stay at home mom with the 3 children.
Helen does not drive, and needs to wait for Peter to drive her or the children to any appointments.
9. Cognitive/Perceptual
Helen states that Henry recognizes and repeats a few words and can obey simple commands. His vision, hearing and speech are normal.
Physical Assessment1. General Appearance:
Sitting on mother's lap resting against her chest
Skin pale in colour
Feels warm to touch.
Weight – 11 kg. (24 lbs); Height – 83 cm (33”)
2. Vital Signs:
Temperature 37.5°C (axilla)
Heart rate: 120 beats per minute
Respiratory rate: 24 breaths per minute
Blood pressure 92/56
Skin
Warm to touch, pale in colour, pink nail beds, mucous membranes dry and pink, skin turgor poor, no bruises, red rash around anus
4. Respiratory:
Lungs clear to auscultation, no crackles, no wheezes
5. Cardiac
Heart – normal, no murmurs heard
Capillary refill 3 seconds, skin pale
6. Abdomen:
No masses
Not tender to touch
Hyperactive bowel sounds
7. Musculoskeletal:
Full range of movement in neck without complaints of pain
No joint pain
8. Neurological:
Irritable and lethargic
9. Genital/Urinary:
Normally has 5 wet diapers per day.
Has been having loose stools for the last 2 days. Helen is not sure if he has been voiding along with the loose stools.
Patient’s Lab Data for Nurse to Review
Test
NORMAL
Henry’s RESULTS
Na
136-145 mmol/ L
133 mmol/L
K
3.4-4 .7 mmol/ L
4.3 mmol/ L
CL
90-110mmol/L
112 mmol/ L
C02
20-28 mmol/L
24 mmol/L
Blood Urea Nitrogen
1.8-6.4 mmol/L
6.8 mmol/L
CREATININE
18-62 mcmol/L
65 mmol/ L
Stool for Culture and Sensitivity (C&S)
Normal Intestinal Flora
Stool for Ova and Parasites (O&P)
Normal Intestinal Flora
1. Understand the complexities of fluid and electrolyte imbalances in children
http://ovidsp.tx.ovid.com.libaccess.lib.mcmaster.ca/sp-3.18.0b/ovidweb.cgi?WebLinkFrameset=1&S=BLCKF...
-
Changes in fluid and electrolyte balance may
happen quickly in infants and children (I & Y C, increasing the nurses
responsibility to anticipate often discreet signs of an imbalance
-
Children and infants present unique problems in
managing fluids and electrolytes.
Differences in the rate of metabolism and body surface area are two
unique aspects
-
a Childs body composition and homeostatic
controls differ from those of an adults the younger the child the greater the
differences
-
Fluid and electrolyte imbalances occur more
quickly in children
-
a newborn’s body is 70-80% water and an adults
body is approx. 60%
-
By the time a child is almost 3 yrs old, the
total body water is approx. 60%
-
Although infants have more fluid in their
bodies, they are more susceptible to fluid loss problems because they intake
and output more water volume daily than do adults
-
Insensible water loss (fluids lost through the
skin and lungs) are higher for infants and children than for adults.
-
Any situation that causes an increase in loss of
water and electrolytes through he skin threatens the body fluid balance of the
infant and small child to a greater degree than it would an older adult
-
Basal metabolic rate (BMR) for children than it
is for adults. An infants high BMR means
the fluid intake per Kg body weight per day actually must exceed the per
kilogram fluid requirements of an adult.
-
Infant kidneys are not mature enough to
concentrate urine efficiently. The infant needs more water to excrete a given
amount of solute.
Assessment
-
As fluid volume decreases extremities become
cool, even if the child is febrile
-
Assess fluid deficit in the mouth
-
If the pulse rate is greater than 160 beats per
min for infants and 120 for children, hypervolemia should be suspected.
-
Children often hyperventilate to compensate for
acidosis
-
BP is the last vital sign to show changes and
not be relied on as an assessment indicator of dehydration
-
Fontanels of infants will be depressed with a
moderate fluid deficit.
Dehydration
-
In children, dehydration is usually attributable
to vomiting or an acute viral or bacterial diarrhea
2. Explore health care values from a transcultural perspective
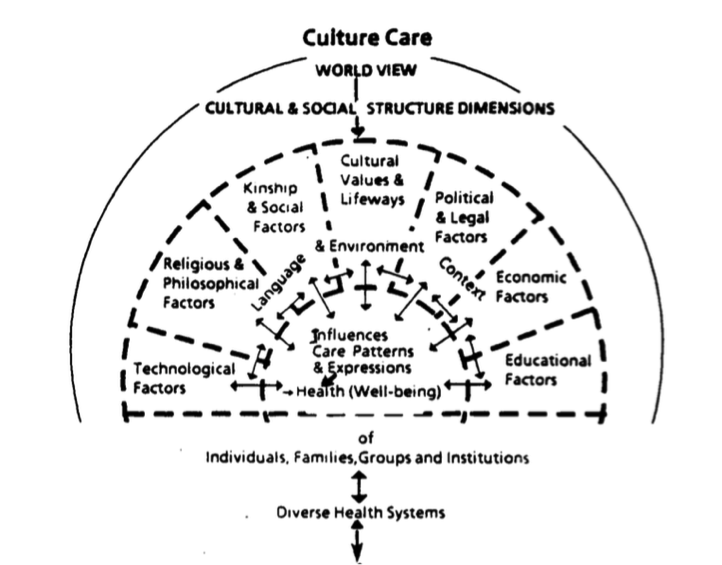
Sunrise Model:
See the diagram at the bottom of the page. I wasn't able to paste it here.
CNO
Culturally Sensitive Care Practice guideline
Culture- Refers to the learned values,
beliefs, norms, and way of life that influence an individuals thinking,
decisions and actions in certain ways.
· Client centered care requires that
nurses recognize the clients culture, the nurses culture and how both affect
the nurse client relationship.
· There is no single “RIGHT” way to
do this for everyone, each client and situation is unique and therefore needs
to be assessed and planned for individually
· The focus must always be on the
clients needs
Assumptions
· Everyone has a culture
· Culture is individual
· Individual culture is influenced
by many factors (See Figure Sunrise Model)
· Culture is always changing
· Reactions to other cultures can be
automatic, subconscious and have an impact on the nurse client relationship
· A nurses own culture is influenced
by personal beliefs in addition to our nursing values
· We are responsible for assessing and
responding appropriately to the clients cultural expectations and needs
Acquiring cultural knowledge
· It is impossible for nurses to
know the details of every culture
· It is however, possible for nurses
to have a broad understanding of how culture can affect beliefs and behaviours
· In health care culture may affect
beliefs and values regarding
o
Perception
of health illness and death
o
Meaning
and role of suffering
o
View
of hospitals, nurses, doctors and other healers
o
Rituals
and customs (religious and other)
o
Boundaries
related to privacy, age, gender, and relationships
o
Effectiveness
and values of different types of therapies
o
Individual
time keeping beliefs and practices that may direct activities
o
Family
and social relationships
o
Decision
making on consent to treatment
o
Independence/self
care versus interdependence/being cared for
o
Communication
norms (eye contact)
Facilitating client choice
· Nurse role is to help client meet
their specific health goals.
· We need to investigate into the
clients view and try to understand the meaning behind a particular request, in
addition to their overall treatment goals
· If it becomes apparent that a
clients cultural preference will negatively affect the client, the nurse works
with the client to explain the harm/risks associated with that choice
· Likewise, if the preference will
affect the wellbeing of other clients, the nurse must look for some ways of
achieving some parts of the clients preference, while safeguarding the other
clients.
Assessment
Ask
open-ended questions to find out relevant cultural information, nurse needs to
listen with respect and remain nonjudgmental
1. What do you think has caused your
problems?
2. Why do you think the problem
started when it did?
3. What do you think the sickness
does to you?
4. What are the major problems the
sickness has caused?
5. What have you done for the illness
until now?
6. What kind of treatment do you
think you should receive?
7. Is there anything else that could
be done either by you or by others (family priest)
8. What are the most important
results you hope to achieve form these treatments?
9. What do you fear most about your
sickness?
10. What do you fear most about the
treatment?
11. Who should be consulted or
involved in your care?
http://www.cno.org/globalassets/docs/prac/41040_culturallysens.pdf
Leininger,
M. M. (1988). Leininger’s theory of nursing: cultural care diversity and
universality. Nursing Science Quarterly,
1 (4), pp. 154-160.
Mennonite Culture
· In Ontario often difficult to
distinguish Mennonites from others
· Old Order – easier to recognize
- Typically live without
electricity, card and dress in simple, plain clothing
- Men wear plain trousers and
jackets with a plain straw hat
- Women wear their hair long,
covered by a prayer cap and have plain dresses
- Sometimes use horse drawn buggies
to get around
- Often choose to educate the
children in schools run by themselves ensuring their beliefs continue to get
passed down each generation
· Many don’t accept heath care and
education by the government
· Founding beliefs – Anabaptists
· New order – live like
non-Mennonites but religion is a major aspect
- Also called Third Way
- Try to connect faith to daily
actions
- Some believe that baptism and
church involvement are voluntary
- Use some forms of technology –
depends on the community
· Woolwich Community Health Centre
- Non-profit organization
- Provides health care, illness
prevention and health promotion services
- Funded by Ontario Ministry of
Health but not through OHIP
- Works with groups of people who
face barriers to health and accessing health care
http://www.thecanadianencyclopedia.ca/en/article/mennonites/
http://www.wchc.on.ca/about_chc.php
3. Identify the impact of a child's illness on individual family members and the family. Apply family theory in caring for children and caregivers
Impact of Pediatric Critical Illness and Injury on Families: A Systematic Literature Review
Marysia Shudy, Mary Lihinie de Almeida, Susan Ly, Christopher Landon, Stephen Groft, Tammara L. Jenkins, Carol E. Nicholson
http://pediatrics.aappublications.org/content/118/Supplement_3/S203#T2
As shown in Table 1, studies using the PSS:PICU indicate that the most severe parental stress is role alteration.
This is understood as the sense of helplessness in parents who are accustomed to control in providing safety and advocacy.
Those we reviewed concluded that the main sources of stress in siblings were changes in parental behavior and care by a substitute caregiver
Needs: Contact with child; nearby resting place, Know what is wrong with child; informed of changes, Feeling of hope; assurance of best care; maintaining caregiver role
Parents felt guilty, excited, discouraged, and exhausted during hospitalization; siblings felt isolated, unimportant, and resentful
Parents of children with LT illnesses were given more emotional support than those with NLT illnesses
Family dynamics were negatively affected; siblings exhibited increased fears and withdrawal from injured child
Family unit experienced increased stress, social distress, and adverse psychological effects
In some instances, a major illness brings a family closer together; in others, even a minor illness causes significant strain.
4. Utilize the a family assessment tool to guide interviewing Henry’s mother in a role playing situation - CALGARY Assessment tool
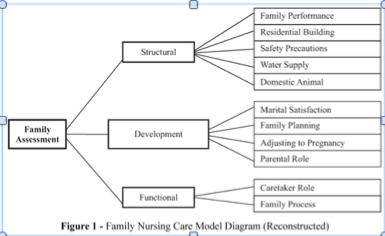
Calgary
Assessment model (diagram pasted at the bottom of the page showing the flow chart)
Wright, L. M., & Leahey, M. (2009). Nurses and
families: A guide to family assessment and intervention (5th ed., p. 5).
Philadelphia, PA: F. A. Davis Company.
and
Potter, Patricia, Anne Perry, Janet Ross-Kerr, Marilynn
Wood, Barbara Astle, Wendy Duggleby. Canadian Fundamentals of Nursing, 5th
Edition. Mosby Canada, 2014. VitalBook file.
Be selective
in which subcategories to use as it could be overwhelming to the family
Structural
Assessment
•
Internal structure is who is included in
the family /how they are related to one another
·
ie. gender roles, sexual
orientation, family composition, ranking (number of children, their ages, their
expectations based on age)
·
Questions to ask:
o Who is in your
family?
o Does anyone else
live with you: for example, grandparents, boarders?
o Has anyone recently
moved out of your household, married, or died?
o Can you think of
anyone else who is like a family member but is not biologically related?
o How have your
parents' ideas about masculinity and femininity affected your own? Have your
ideas about gender been challenged in any way since you became parents?
o Do you have
expectations of your children on the basis of their gender?
o Is the division of
labour at home based on gender roles?
o How many children
are in your family?
o What are the
children's ages?
o Do you have
distinct expectations for the oldest and younger children?
•
External structure is relationships the
family shares with people and institutions outside of the family unit
·
ie. extended family
·
Context is the whole
situation/background relevant to the family
·
ie. religion, socioeconomic
class, ethinicity
·
Questions to ask:
o Where do your parents
live? How often do you have contact with them and your siblings?
o Which family
members do you see or speak with regularly? Who in your extended family are you
the closest to?
o Have members of
your extended family been helpful to you during this time of illness? In what
way?
o What is your job?
How many hours a week do you work? How does this affect family life?
o Does anyone in the
family work shifts? How does that influence your family functioning?
o What level of
education have you completed?
o Does your family
have economic challenges at this time?
Developmental
Assessment
•
Stages that families go through
that requires adjustment or change
•
Interaction between
individual’s development and the phase of the family developmental life cycle
that are important to family functioning
•
Cycles: Leave home, become
young adults, families join together through marriage, families have young
children, then families have adolescents, move on to mid life, families in late
middle age, and families at end of life
Functional
Assessment
•
Divided into instrumental and
expressive
•
It's how family members
interact with each other
•
Instrumental Functioning
·
Normal ADL's
·
ie. meals, sleep schedules,
attending health needs
o
How these roles change when coping
with relative’s illness or disability
o Who is usually
responsible for housekeeping and child care?
o Do other family
members help with these tasks?
o Does anyone in the
family require help with activities of daily living?
o Who will be
primarily responsible for flushing Mary's broviac line (an intravenous access
device for the administration of medications and blood tests) when she is
discharged home?
•
Expressive Functioning
·
How people communicate
·
Emotional: feelings expressed by the family
·
Verbal: focusing on using words
·
Nonverbal: body language,
gestures, crying
·
Circular: how each family
member influences the behaviour of others
o How can you tell
when each member of your family is happy, sad, or under stress?
o How do you express
happiness, sadness, or stress?
o Johnny, when you
are sad or worried, who in the family do you most like to spend time with or
talk to about that?
I've embeded the youtube video at the bottom of this document.
5. Mennonite Culture
· In Ontario often difficult to
distinguish Mennonites from others
· Old Order – easier to recognize
- Typically live without
electricity, card and dress in simple, plain clothing
- Men wear plain trousers and
jackets with a plain straw hat
- Women wear their hair long,
covered by a prayer cap and have plain dresses
- Sometimes use horse drawn buggies
to get around
- Often choose to educate the
children in schools run by themselves ensuring their beliefs continue to get
passed down each generation
· Many don’t accept heath care and
education by the government
· Founding beliefs – Anabaptists
· New order – live like
non-Mennonites but religion is a major aspect
- Also called Third Way
- Try to connect faith to daily
actions
- Some believe that baptism and
church involvement are voluntary
- Use some forms of technology –
depends on the community
· Woolwich Community Health Centre
- Non-profit organization
- Provides health care, illness
prevention and health promotion services
- Funded by Ontario Ministry of
Health but not through OHIP
- Works with groups of people who
face barriers to health and accessing health care
http://www.thecanadianencyclopedia.ca/en/article/mennonites/
http://www.wchc.on.ca/about_chc.php
https://www.youtube.com/watch?v=ZHw7CvKonMw (Embed)
Readings for scenario
“No more tears for Henry”
King, C.K., Glass,
R., Bresee, J.S., & Duggan, C. (2003). Managing acute gastroenteritis among
children: Oral rehydration, maintenance, and nutritional therapy. MMWR: Morbidity & Mortality Weekly Report, 52(RR-16), 1-16. Retrieved from
http://www.cdc.gov/mmwr/index.html
Summary
Acute Gastroenteritis:
-
Common illness among infants and children in the
world
-
accounting for >1.5 million outpatient
visits, 200,000 hospitalizations, and approximately 300 deaths/year
-
Diarrhea is one of the common causes of
mortality for children < 5 y o
-
Oral Rehydration Therapy (ORT)
o
Improved health outcomes among children in
developing countries – decreased mortality
o
Use has lagged in US
-
Physicians recognize:
o
Supplementation of zinc can reduce incidence and
severity of diarrheal disease
o
ORS of reduced osmolality (proportional reduced
sodium nad glucose): recommended for global use
-
This article updates recommendations of managing
gastroenteritis
Introduction &
Background
-
ORT
encompasses two phases of treatment: 1) a rehydration phase, in which water and
electrolytes are administered as oral rehydration solution (ORS) to replace
existing losses, and 2) a maintenance phase, which includes both replacement of
ongoing fluid and electrolyte losses and adequate dietary intake
-
The
lag of ORT use in US is thought to be due to the ingrained use of IV therapy
and reduced appeal of a technologically simple solution
o
Many
children with mild dehydration and vomiting have ORT withheld
-
ORT
use began in developing countries where IV availability is reduced
-
NOW,
ORT accepted as standard of care for the clinically efficacious and
cost-effective management of acute gastroenteritis
Physiologic Basis for
using ORS
-
The
adult intestinal epithelium must handle 6,500 mL of fluids/day, consisting of a
combination of oral intake, salivary, gastric, pancreatic, biliary, and upper
intestinal secretions. This volume is typically reduced to 1,500 mL by the
distal ileum and is further reduced in the colon to a stool output of <250
mL/day in adults --- during diarrhea the volume of intestinal fluid output is
substantially increased overwhelming the reabsorptive capacity of the GI tract
-
Solutions
with a high concentration of co-transporters increase the risk from hypertonic
solutions that decrease rather than improve sodium and water transport into the
bloodstream. However, solutions of lower osmolarity, but that maintain the 1:1
glucose to sodium ratio, perform optimally as oral solutions for diarrhea
management (see Choice of ORS).
Home Management of
Acute Diarrhea
Initiation of Therapy:
-
All
families should be encouraged to have a supply of ORS in the home at all times
and to start therapy with a commercially available ORS product as soon as
diarrhea begin
Need to recognize severity:
-
Infants are more at risk for becoming dehydrated
because of higher body-surface-to-volume ratio, higher metabolic rate, smaller
fluid reserves and depend on others for fluid
-
When fever is present: infants and children
should be evaluated to rule out other serious illnesses (sepsis and meningitis)
-
Box 1 provides a guide for when to seek medical
evaluation:
Referral for Evaluation:
-
This is the responsibility of the physician
-
Focus on factors putting a child at risk of
dehydration
o
Number of days the child has been ill
o
# of episodes of diarrhea or vomiting
o
Volume of fluid output
o
Mental status
o
Past medical history
Clinical Assessment
-
Diarrhea is 3 or more loose/ watery stools/day
o
Volume of fluid lost through stools can vary
from 5mL/kg body weight/day (normal) à
>200 mL/ kg body weight/ day
-
Dehydration
and electrolyte losses associated with untreated diarrhea cause the primary
morbidity of acute gastroenteritis.
-
Diarrhea can be among the initial signs of
non-gastrointestinal tract illnesses, including meningitis, bacterial sepsis,
pneumonia, otitis media, and urinary tract infection.
-
Vomiting
alone can be the first symptom of metabolic disorders, congestive heart
failure, toxic agent ingestion, or trauma.
-
To
rule out other serious illnesses, a detailed history and physical examination
should be performed as part of the evaluation of all children with acute
gastroenteritis.
History:
-
onset,
frequency, quantity, and character (i.e., the presence of bile, blood, or
mucus) of vomiting and diarrhea
-
Recent
oral intake, including breast milk and other fluids and food; urine output;
weight before illness; and associated symptoms, including fever or changes in
mental status, should be noted.
-
The
past medical history should identify underlying medical problems, history of
other recent infections, medications, and human immunodeficiency virus (HIV)
status. A relevant social history can include the number and nature of
caregivers, which can affect instructions regarding follow-up care.
Physical Examination
Things to gather:
-
Body weight
-
Vitals: T, HR, RR, BP
-
special
concern given to infants and children who appear listless, apathetic, or less
reactive
-
sunken
eyes? Tearing?
-
lips, mouth, and tongue will yield
critical clues regarding the degree of dehydration
-
Deep
respiration can be indicative of metabolic acidosis
-
Faint
or absent bowel sounds can indicate hypokalemia
-
general
perfusion and capillary refill
-
check
skin turgor
Dehydration
Assessment
This table provides a guideline for a starting point for
treatment and who can be sent home for therapy
Lab Evaluation
-
stool
cultures should be gathered in there is dysentery but not for acute, watery
diarrhes for immunocompetent pt
-
CBC
and urine and blood cultures might be indicated when sepsis or UTIs are a
concern
Acute
Gastroenteritis Therapy based on degree of dehydration
-
7
principles guide optimal treatment in Box 2
-
Treatment
should include two phases: rehydration and maintenance.
-
Rehydration phase: the fluid deficit is replaced quickly
(i.e., during 3--4 hours) and clinical hydration is attained.
-
Maintenance phase: maintenance calories and fluids are
administered. Rapid realimentation should follow rapid rehydration, with a goal
of quickly returning the patient to an age-appropriate unrestricted diet,
including solids
-
Breastfeeding should be continued at all
times
-
Diet:
increased as soon as tolerated to compensate for lost caloric intake during the
acute illness.
o
Lactose
restriction is usually not necessary (although it might be helpful in cases of
diarrhea among malnourished children or among children with a severe
enteropathy), and changes in formula usually are unnecessary
-
During
both phases, fluid losses from vomiting and diarrhea are replaced in an ongoing
manner
-
Antidiarrheal
medications are not recommended for infants and children
Minimal
Dehydration
-
treatment
is aimed at providing adequate fluids and continuing an age-appropriate diet
-
use of ORS should be encouraged: 1 mL of
fluid should be administered for each gram of output
-
In
hospital: weigh soiled diapers (without urine)
-
If
unable to measure: children
weighing <10 kg should be administered 60--120 mL (2--4 ounces) ORS for each
episode of vomiting or diarrheal stool, and those weighing >10 kg should be
administered 120--240 mL (4--8 ounces)
Mild – Moderate
Dehydration
-
should have their estimated fluid deficit
rapidly replaced - administering
50--100 mL of ORS/kg body weight during 2--4 hours using additional ORS to
replace continued losses
-
Using
a teaspoon, syringe, or medicine dropper, limited volumes of fluid (e.g., 5 mL
or 1 teaspoon) should be offered at first, with the amount gradually increased
as tolerated
-
Nasogastric (NG) feeding allows continuous
administration of ORS at a slow, steady rate for patients with persistent
vomiting or oral ulcers
o
More
cost-effective and well-tolerated than IV rehydration
-
If
ORT doesn’t improve child’s dehydration keep them until signs of dehydration
subside
-
After
dehydration is corrected, further management can be implemented at home,
provided that the child's caregivers demonstrate comprehension of home
rehydration techniques (including continued feeding)
Severe Dehydration
-
constitutes
a medical emergency requiring immediate IV rehydration
-
LR,
NS/ similar solution administered until pulse, perfusion and mental status
return to normal
-
Serum
electrolytes, bicarbonate, blood urea nitrogen, creatinine, and serum glucose
levels should be obtained
-
Hypotonic
solutions should not be used for acute parenteral rehydration
-
Watch
for overhydration
-
Hydration
status should be reassessed frequently to determine the adequacy of replacement
therapy
-
As
soon as the severely dehydrated patient's level of consciousness returns to
normal, therapy usually can be changed to the oral route, with the patient
taking by mouth the remaining estimated deficit. An NG tube can be helpful for
patients with normal mental status but who are too weak to drink adequately.
Clinical
management in the hospital
Inpatient
care is indicated for children if
caregivers
cannot provide adequate care at home;
substantial
difficulties exist in administrating ORT, including intractable vomiting,
ORS refusal, or inadequate ORS intake;
concern
exists for other possible illnesses complicating the clinical course;
ORS
treatment fails, including worsening diarrhea or dehydration despite
adequate volumes;
severe
dehydration (>9% of body weight) exists;
social
or logistical concerns exist that might prevent return evaluation, if
necessary, or
such
factors as young age, unusual irritability or drowsiness, progressive
course of symptoms, or uncertainty of diagnosis exist that might indicate
a need for close observation.
Limitations of
ORT:
-
children in hemodynamic shock – their
airway protective reflexes might be impaired
-
Ab
ileus: don’t give fluids until BS are audible
-
Bowel
obstruction
-
A
limited percentage of infants (<1%) with acute diarrhea experience
carbohydrate malabsorption. This is characterized by a dramatic increase in
stool output after intake of fluids containing simple sugars (e.g., glucose),
including ORS
Hypernatremic
Dehydration
-
serum sodium concentration >145 mEq/L
-
Respond
well to ORT
Dietary Therapy
-
Breastfed
infants: feed on demand
-
Formula-fed
infants should continue their usual formula immediately upon rehydration in
amounts sufficient to satisfy energy and nutrient requirements
-
Not
necessary to use lactose free formulas (unless lactose intolerant)
-
Children
receiving semisolid or solid foods should continue to receive their usual diet
during episodes of diarrhea. Foods high in simple sugars should be avoided
because the osmotic load might worsen diarrhea; therefore, substantial amounts
of carbonated soft drinks, juice, gelatin desserts, and other highly sugared
liquids should be avoided.
-
Early feeding decreases changes in
intestinal permeability caused by infection, reduces illness duration, and
improves nutritional outcomes
-
Recommended foods include age-appropriate
unrestricted diets, including complex carbohydrates, meats, yogurt, fruits, and
vegetables.
Pharmacological
Therapy
Antimicrobial
-
antimicrobial
therapy is not usually indicated among children because the majority of cases
of acute diarrhea are self-limited and not shortened by antimicrobial agents.
Exceptions to these rules involve special needs of individual children
Nonantimicrobial Drug Therapies
-
Nonspecific
antidiarrheal agents (e.g., adsorbents such as kaolin-pectin), antimotility
agents (e.g., loperamide), antisecretory drugs, and toxin binders (e.g.,
cholestyramine), are commonly used among older children and adults, but data
are limited regarding their efficacy.
Supplemental Zinc
Therapy
-
severe
zinc deficiency (e.g., acrodermatitis enteropathica) is associated with
diarrhea, milder deficiencies of zinc might play a role in childhood diarrhea,
and zinc supplementation might be of benefit either for improved outcomes in
acute or chronic diarrhea or as prophylaxis against diarrheal disease
-
# of
trials have been shown that zinc supplements help in treating diarrheal disease
but this needs further evaluation
Probiotics
-
Further
human trials are needed before making specific recommendations
Acute Bloody Diarrhea (Dysentery)
-
Oral
rehydration therapy is critical in managing specific types of diarrheal
diseases.
-
Dysentery: acute bloody diarrhea caused by
invasive microbial infection.
o Doesn’t include occult blood (detected by guaiac card only) or streaks of
blood on the surface of formed stool
-
Tx
of dehydration in dysentery follows the same principles as treatment of acute watery
diarrhea.
-
Child
with bloody diarrhea is at higher risk for complications, including sepsis and
other systemic diseases - threshold for admission of such children to the
hospital for close observation is lower.
-
Stool
cultures are needed for guiding therapy. Food should not be withheld for
children with dysentery any more than in other cases of diarrhea. More
frequent, smaller meals might be better tolerated, and higher protein intakes
-
In
the majority of cases, empiric antimicrobial agents should not be administered
while awaiting culture results, because antimicrobial therapy might not be
indicated even when culture results are positive. Amoebiasis is an unusual
cause of bloody diarrhea in young children, even in less-developed countries.
Treatment for amoebiasis should be reserved for those cases in which
trophozoites are detected on microscopic examination of the stools
Choice of ORS:
-
In
1975, WHO and the United Nations Children's Fund (UNICEF) agreed to promote a
single ORS (WHO-ORS) containing (in mmol/L) sodium 90, potassium 20, chloride
80, base 30, and glucose 111 (2%) for use among diverse populations – single
solution to be used for diarrhea treatment with a variety of electrolytes
losses
-
Further
studies have shown ORS of lower osmolality is better than ORT
Barriers
-
Cultural
practices
-
Lack
of parental knowledge
-
Lack
of training for HCP
-
Cost
-
Among
physicians, preference for IV hydration, even where evidence indicates improved
results from oral rehydration = major barrier
Conclusion:
Treatment
of acute diarrhea has relied upon simple and effective therapy of oral
rehydration. The critical co-principle in case management of early resumption
of feeding of children immediately upon rehydration has also gained wide
acceptance. More recent advances in the science of diarrhea treatment include
recognition for the role of zinc supplementation in reducing disease severity
and occurrence, and development of an oral rehydration solution of lower
osmolarity for global use. The combination of oral rehydration and early
nutritional support promises to safely and effectively assist a patient through
an episode of diarrhea. If the principles of therapy outlined in this report
are accepted by all levels of the medical community and if education of parents
includes teaching them to begin ORT at home, numerous deaths and unnecessary
clinic visits and hospitalizations can be avoided. ORT is suitable for use
among children throughout the world
Toddlers
(18months – 3 yrs old)
Important stages of growth, development and maturation:
Physical
-
Growth is slower
-
Growth in spurts
-
Wide gait and walk hesitantly
-
Fine and gross motor skills progress
quickly
-
Fine Motor skills: reaching, grasping,
manipulating small objects
-
Gross Motor skills: balance and
coordination continuously improve, most are walking alone by 18months, tend to
experiment with skills
Cognitive
-
Relationships between objects and
actions
-
Imitate adults
-
Develop a number sense, match colours
and shapes
-
Engage in symbolic play (object-use and
make-believe)
Social/ Emotional
-
Egocentric
-
Autonomous and independent
-
No conscience
-
Demonstrate negativism
-
Enjoy ritualism
-
Experience separation anxieties
-
Tantrums as coping mechanism
-
Early toddlers: solitary play
-
Early preschoolers: associative play
Common Concerns/Hazards
-
Illnesses: chickenpox, viruses
-
Hazards: most deaths are a result of
accidents (from their curiosity): falls, chemicals, burns, drowning, choking,
and MVA
Communication Techniques:
-
Demonstrate and use play to teach a
procedure
-
Provide visuals
-
Simplify vocabulary: clear and firm
instructions
-
Offer limited options: don’t offer a
choice when there is none
-
Praise a child for a job well done
Information
- Description
- 2 2NN3 Note on No More Tears for Henry, created by D R on 18/01/2016.
- Created by
- D R · Jan 2016
- Updated
- Apr 6, 2018
- Views
- 122
- Tags
- Rating