
Flashcards
453 Test 1: Mech Vent, Trach, VAP, ARDS
Cards in this deck (54)
- 1Bi-PAP1. Done before mechanical ventilation
2. Noninvasive
3. Delivered through a tight fitting face mask, nasal mask or nasal pillows
4. Must breathe spontaneously & cooperate - 2Bi-PAP Indications1. Acute respiratory failure with COPD and heart failure
2. Sleep apnea - 3Endotracheal (ET) Intubation ProcedureRapid sequence intubation (RSI)
-Rapid, concurrent administration of a paralytic agent & a sedative agent during emergency airway management
-increased risks of aspiration, combativeness, & injury to patient
-not indicated for comatose or cardiac arrest patients - 4Following intubation - what to expect1. Confirmation - should hear bilateral lung sounds
2. Hemodynamic stability or instability
3. Settings
4. Comfort & control
5. Tube placement → Nosocomial breakdown
6. Monitoring (Labs) - 5The most potent vasodilator we make naturallyCO2
- 6Why is it important to have fluids nearby following intubation?Before intubation, a patient can be air hungry and the fight or flight response kicks in (↑ BP, ↑HR, ↑RR). After intubation, there is increased vasodilation and BP can decrease rapid causing a shift in hemodynamics. Fluids can help support that stability
- 7AACN Recommendations for ET suctioning1. Sawtooth pattern on vent tracing
2. Coarse crackles & rhonchi over trachea
3. ↓ Vt (tidal volume)
4. ↓ O2 Sat and/or ABG values
5. Visible secretions
6. Pts inability to generate an effective cough
7. Acute Resp Distress
8. Suspected or actual aspiration - 8Nursing Management - Artificial Airway1. Aspiration - tube feedings, HOB
2. Prevent unplanned extubation - The Joint Commission, Restraints (chemical & behavioral) - 9When to feed an intubated patient-Determined by why the Pt is there, their metabolic state & co-morbidities
-Some MDs will start a trickle tube feeding around day 3 just to keep the gut active
-May go on TPN
-Dietary consult should be obtained around day 3 - 10Mechanical Ventilation-Process by which fraction inspired oxygen (FIO2) at ≥21% (room air) is moved into and out of lungs by a mechanical ventilator
-Supportive NOT Curative
-Temporary to Permanent - 11Indications for mechanical ventilation-Apnea or impending inability to breathe
-Acute respiratory failure
-Severe hypoxia
-Respiratory muscle fatigue - 12Settings of mechanical ventilators-Regulate rate, depth, and other characteristics of ventilation
-Based on patient’s status (e.g., ABGs, body weight, level of consciousness, muscle strength)
-Ventilator is tuned to match patient’s ventilatory pattern - 13Positive pressure ventilation (PPV)-Used primarily in acutely ill patients
-Pushes air into lungs under positive pressure during inspiration
-Expiration occurs passively - 14Positive end-expiratory pressure (PEEP)-Mode of PPV
-A little bit of positive pressure that stays in the alveoli to keep it open at the end of expiration - 15Cardiovascular complications of PPV-PPV affects circulation → pressure to thoracic cavity
-↑ Intrathoracic pressure compresses thoracic vessels:
↓ Venous return to heart, ↓ left ventricular end- diastolic volume (preload), ↓ cardiac output, Hypotension - 16Pulmonary complications of PPVBarotrauma:
-Air can escape into pleural space from alveoli or interstitium, accumulate, and become trapped →pneumothorax
-COPD (rupt. Blebs)
-Chest tubes may be placed prophylactically - 17Other complications of PPVPneumomediastinum
-Begins with rupture of alveoli into lung interstitium
-Progressive air movement into mediastinum and subcutaneous neck tissue
-Commonly followed by pneumothorax - 18Other complications of PPV (cont)Ventilator Associated Pneumonia (VAP)
-Pneumonia that occurs 48 hours or more after ET intubation
-Clinical evidence:
Fever and/or elevated WBC count
Purulent or odorous sputum
Crackles or rhonchi on auscultation
Pulmonary infiltrates on chest x-ray - 19Guidelines to prevent VAP-ORAL CARE!!!!!!!
-HOB elevation at least 30 to 45 degrees unless medically contraindicated
-No routine changes of ventilator circuit tubing
-Drain condensation that collects in ventilator tubing
-Use of an ET that allows continuous suctioning of secretions in subglottic area - 20More complications of PPV-Fluid retention
-Neurologic system
-Gastrointestinal system
-Musculoskeletal system - 21Mechanical ventilation - Psychosocial needs-Physical and emotional stress due to inability to speak, eat, move, or breathe normally
-Pain, fear, and anxiety related to tubes/ machines
-Ordinary ADLs are complicated or impossible
-Involve patients in decision making
-Encourage hope and build trusting relationships with patient and family
-Provide sedation and/or analgesia to facilitate optimal ventilation - 22Psychosocial needs (cont)-If necessary, provide paralysis to achieve more effective synchrony with ventilator and increase oxygenation
-Paralyzed patient can hear, see, think, feel
-Sedation and analgesia must always be administered concurrently
-Assessment:
Train-of-four peripheral nerve stimulation
Physiologic signs of pain or anxiety
Ventilator synchrony - 23Machine disconnection-Most frequent site for disconnection is between tracheal tube and adapter
-Pause alarms during suctioning or removal from ventilator
(Reactivate alarms before leaving)
-Malfunction may be due to power failure, failure of oxygen supply, etc. - 24What to do if machine malfunctions-Disconnect patient from ventilator
-Manually ventilate with 100% O2 - 25Nutritional therapy (TPN vs. Enteral)-PPV and hypermetabolism can contribute to inadequate nutrition
-If patient is likely to be without food for 3 to 5 days, a nutritional program should be initiated
-Poor nutrition and disuse of respiratory muscles contributes to decreased muscle strength - 26Weaning from PPV & extubationProcess of:
-Decreasing ventilator support
-Resuming spontaneous ventilation
-JUST PULL the TUBE
-Patient Self-Extubations (85% Fly) - 27When weaning failsFocus on tracheostomy
- 28Definition of tracheostomy-Surgical incision into the trachea to establish an airway
-Stoma that results from tracheotomy - 29Tracheostomy indicationsProlonged intubations with unsuccessful weaning, management of bronchial hygiene, obstruction of the upper airway (head & neck trauma), and airway protection
- 30Advantages of a tracheostomy-Less of long-term damage to airway
-Increased comfort
-Patient can eat (potential)
-Speaking (potential)
-Increased mobility because tube is more secure - 31Tracheostomy care-Suctioning the airway to remove secretions
-Cleaning around stoma
-Changing ties
-Inner cannula care - 32Accidental dislodging of tracheostomy-Immediately replace tube
-Spread opening with retention sutures grasped or hemostat
-Obturator inserted in replacement tube:
Lubricated with saline poured over tip
Inserted at 45 degrees to neck - 33Nursing Diagnoses-Ineffective airway clearance
-Impaired verbal communication
-Risk for infection
-Impaired swallowing
-Ineffective therapeutic regimen management - 34Techniques to promote speech-Spontaneously breathing patient may deflate cuff, allowing exhaled air to flow over vocal cords
-Patient on mechanical ventilation can allow constant air leak around cuff - 35Decannulation-When patient can adequately exchange air and expectorate
-Stoma closed with tape and covered with occlusive dressing
-Instruct patient to splint stoma with fingers when coughing, swallowing, or speaking
-Tissue forms in 24 to 48 hours
-Opening will close in several days without surgical intervention - 36Acute Respiratory Distress Syndrome (ARDS)-Sudden failure of the respiratory system
-Extensive lung inflammation and small blood vessel injury.
-Alveolar capillary membrane becomes damaged and more permeable to intravascular fluid
-Alveoli fill with fluid
-Stiff, wet or shock lung - 37ARDS is characterized by-Severe dyspnea/Tachypnea
-Hypoxia/Hypoxemia
-Decreased lung compliance
-Alveolar Collapse
-Diffuse pulmonary infiltrates - 38ARDS etiology & pathophysiologyDevelops from a variety of direct or indirect lung injuries (some fall under both)
- 39Direct mechanisms of ARDSDirect mechanisms:
-Pneumonia
-Sepsis
-Chest Trauma
-Aspiration of gastric contents
-Toxic inhalation/Smoking
-Pulmonary contusion or PE
-O2 toxicity
-Near-drowning
-Radiation
-Reperfusion injury post-lung transplant - 40Indirect mechanisms of ARDSTriggered from outside the lung through the release of tissue damaging inflammatory cytokines that travel to the lungs.
- 41Indirect mechanism of ARDS (cont)-Most common is SEPSIS
-General Trauma
-Massive transfusion-Fluid Resuscitation
-Pancreatitis
-Drug OD
-Burns
-DIC
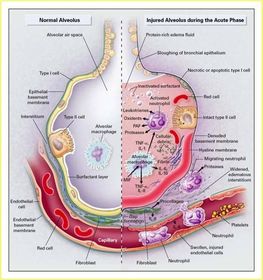
-Shock - 42Injury or Acute Exudative phase of ARDS-1 to7 days (usually 24-48 hours) after direct lung injury or host insult. Release of Inflammatory Mediators
-Permeability: Damage to the alveolar capillary endothelial cells and alveolar epithelial cells. Begin collapsing.
-Proteinaceous fld. Floods alveoli and inactivates surfactant.
-Normal gas exchange is compromised triggering diffuse alveolar collapse. V/Q mismatch & Shunting
-Worsening hypoxemia that doesn’t respond to supplemental O2. - 43Reparative of proliferative phase of ARDS-Last up to 1-2 weeks
-Influx neuts, monos, & lymphs, & fibroblasts.
-Marked by resolution of acute phase & initial repair of the lung OR pt worsens.
-Severe Hypoxemia
-A patient who reaches this phase may recover fully, or move on to the fibrotic phase.
-Of Note: Within 7-10 days, ½ ARDS pts are either deceased or weaned off Rx. - 44Fibrotic or chronic/late phase-2 to 3 weeks post initial insult
-Fibrotic tissue replaces normal lung structure, scarring.
-Causes progressive vascular occlusion & pulmonary hypertension
-Require long-term support, mechanical ventilation & supplemental O2 - 45Lasting effects of ARDS-Acute lung injury (ALI) and acute respiratory distress syndrome (ARDS) are potentially lethal complications of critical illness that are unfortunately common in some ICUs.
-Impaired physical, mental, & lung fxn @ 1 yr.
-The longer the length of stay, the worse physical fxn. - 46Recognizing ARDS-Who’s @ Risk? Everybody
-Assessment findings similar to those with -Respiratory failure.
-If on vent—increasing PIP
-Difficulty oxygenating & CXR - 47How do you know its ARDS-ABGs:
Initial - Hypoxemia & respiratory alkalosis 2° to hyperventilation, then respiratory acidosis
-Pulse Ox ↓ ↓↓ ↓↓↓↓↓ (Despite how much O2 the Pt is receiving
-Labs - FULL PANEL OF EVERYTHING!!! - 48ARDS Tx options-No definitive treatment currently exists, so………Supportive
-Mechanical Ventilation /PEEP/?Nitric Oxide
-Medications: Sedation, Chemical Paralysis
-Nutrition
-On Guard Against Complications – MODS
-Positioning: Prone - 49Prone positioning in ARDS-Repositioning of patient from a supine or lateral prone position to prone position
-Goal is improved lung recruitment
-Used as supportive therapy in critically ill patients with acute lung injury or ARDS - 50Proning-Must happen early.
-Device/Bed
-Inclusion: inadequat oxygenation at ≥ 50% FIO2, PEEP > 10cm, presence of bilateral infiltrates on CXR.
-Minimize pressure → Nosocomial -Breakdown
-Other Risks - 51True or False? I should reactive alarms before leaving the room?TRUE
- 52When should trach care be performed?24 hours after the trach has been inserted, then once a shift
- 53What might you expect when progressive vascular occlusion & pulmonary hypertension occurs in the fibrotic or chronic/late phase of ARDS?Patients will have major limitations with their ADL's, so cor pulmonale and DVTs/PE
- 54What do you need to monitor to make sure your patient is hemodynamically stable?BP & urine output
Information
- Description
- Flashcards on 453 Test 1: Mech Vent, Trach, VAP, ARDS, created by Kristi Breese on 05/02/2017.
- Created by
- Kristi Breese
- Views
- 22
- Rating