Fichas
Dermatology Final
Fichas del conjunto (117)
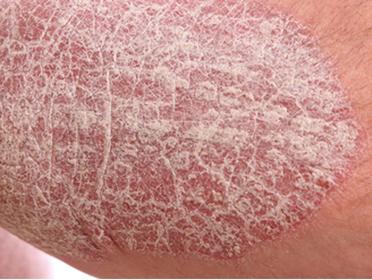
- 1—Psoriasis
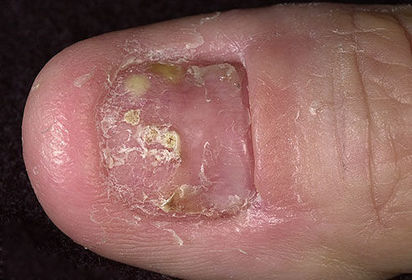
- 2—Psoriasis (nail pitting)
- 3—Koebner's Phenomenon
(psoriasis post-trauma)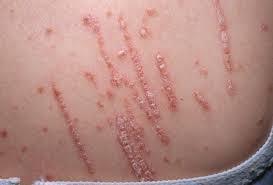
- 4—Psoriasis Vulgaris (trunk)
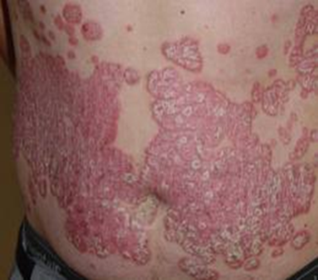
- 5—Psoriasis Vulgaris (extensor surfaces)
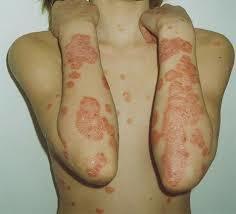
- 6—Psoriasis Vulgaris
(knees & extensor surfaces)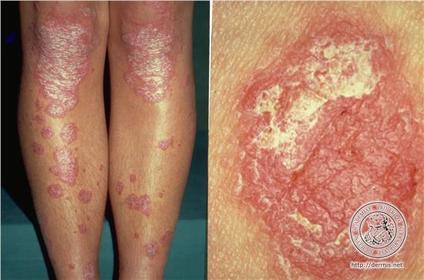
- 7—Guttate Psoriasis
- discrete
- all over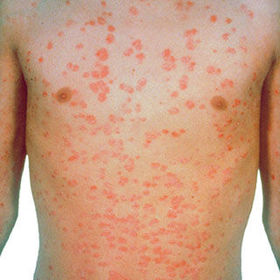
- 8—Guttate Psoriasis (dark skin)
- discrete
- all over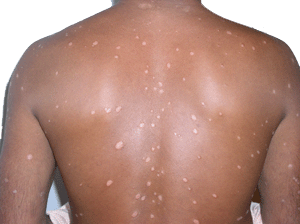
- 9—Psoriasis
- pitting
- onycholysis (nail lifting)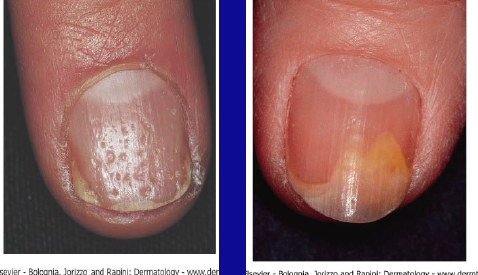
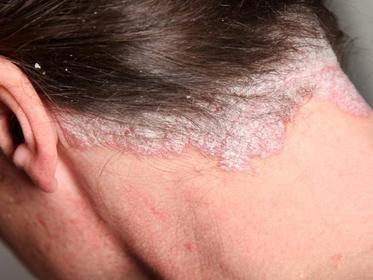
- 10—Psoriasis (scalp)
- 11—Pityriasis Rosea
- multiple red mac/pap progress to to oval, pink/red with fine scale in center
- parallel skin tension lines (xmas tree distribution)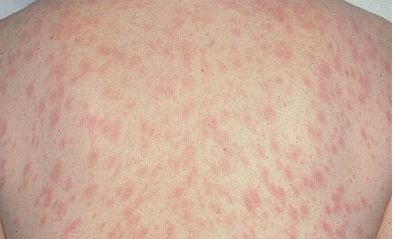
- 12—Pityriasis Rosea
- black skin --> hyper pigmented & @ folds (neck), proximal extremities, axillae, & groin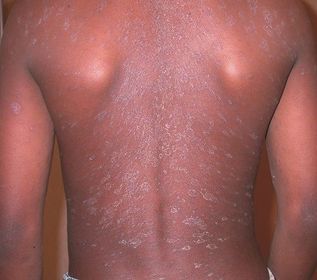
- 13—Pityriasis Rosea
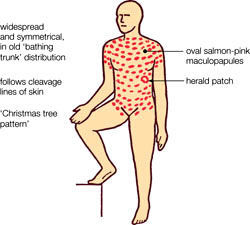
- 14—Herald Patch - Pityriasis Rosea
- preceded by prodrome (URI)
- HHV-7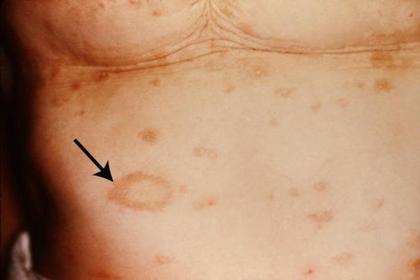
- 15—Herald Patch - Pityriasis Rosea
DDX:
- Secondary syphilis (palm/sole [≠ PR], LAD)
- Tinea corporis
- Guttate psoriasis
- Parapsoriasis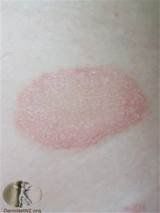
- 16—Acute Parapsoriasis (PLEVA)
- recurrent crops 2-4 mm red papules
- progress --> central crusts
- can leave depressed scars
"Chicken Pox that won't heal"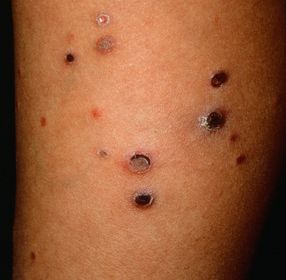
- 17—PLEVA
- can be very itchy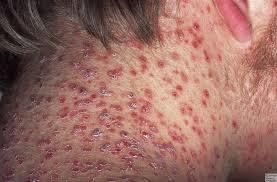
- 18Chicken Pox vs. PLEVA Mucosal involvement = ?Chicken Pox (Varicella)
- 19Chicken Pox vs. PLEVA NO mucosal involvement = ?PLEVA
- 20Chicken Pox vs. PLEVA Lasts 2 weeks = ?Varicella
- 21Chicken Pox vs. PLEVA Lasts 9-12 months = ?PLEVA
- 22—Chronic Parapsoriasis
(PLC: pityriasis lichenoides chronica)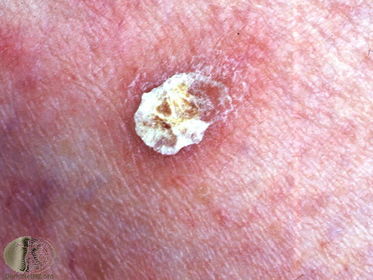
- 23—Chronic Parapsoriasis
(PLC: pityriasis lichenoides chronica
- salmon colored
- oval plaques
- central thin scale (≠ crust)
- boxer shorts distribution
- mimics PR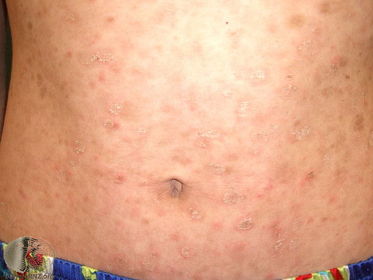
- 24—PLEVA
~ Chicken pox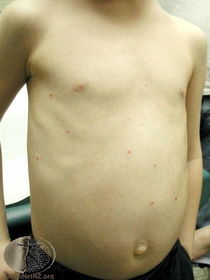
- 25—Lichen Planus
- polygonal
- purple-red
- papules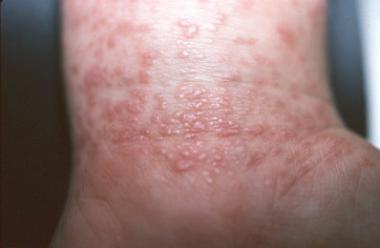
- 26—Lichen Planus
- polygonal
- purple-red
- papules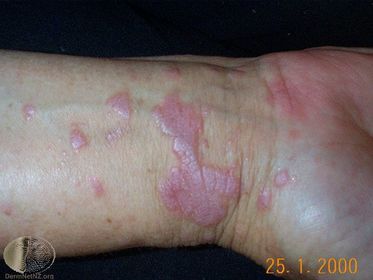
- 27—Lichen Planus
Nail dystrophy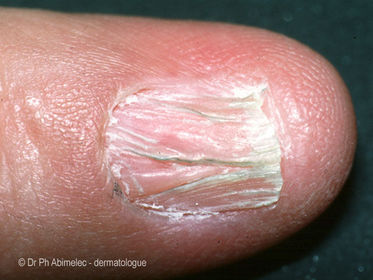
- 28—Lichen Planus
Hypertrophic version: thick & scaly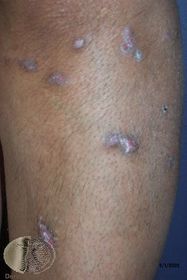
- 29—Lichen Planus
Lower legs = scaly plaques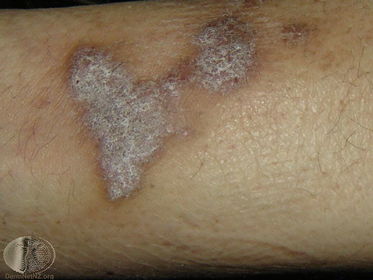
- 30—Wickham's Striae
(Lichen Planus)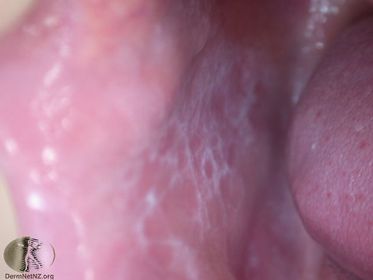
- 31—Lichen Striatus
- along lines of blascho (migration route)
- extremity
- resolve on own over 3-6 months
- skin colored / pink / brown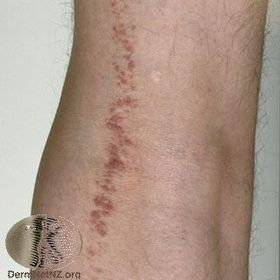
- 32—Lichen Striatus
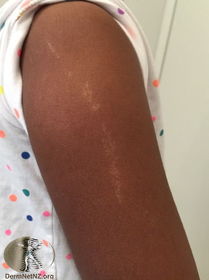
- 33—SLE - Malar Rash
Red scaly mac-pap eruption over nose & cheeks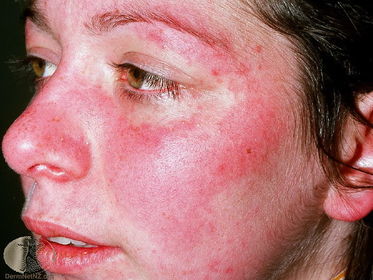
- 34—SLE - Discoid lesion
Persistent focal plaques @ face, are & scalp. Nummular w/ atrophy & follicular accentuation. Disfiguring (Seal).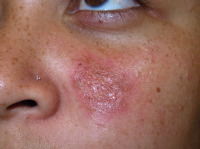
- 35—SLE
Erythematous scaly plaques on dorsal hand BETWEEN knuckles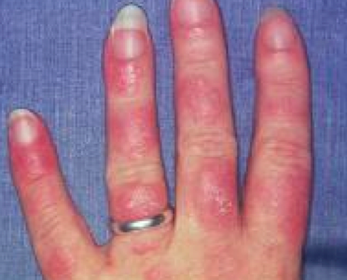
- 36—SLE
Periungal erythema (dilated blood vessels)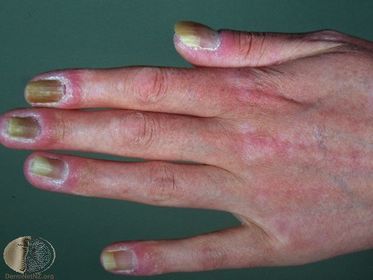
- 37—SLE
Subacute cutaneous lupus erythematous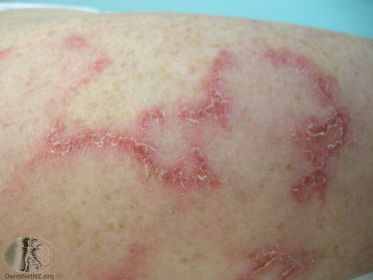
- 38—Neonatal Lupus
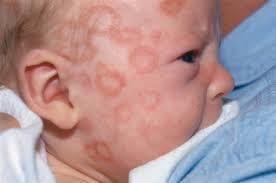
- 39—Dermatomyositis
Gottron's papules: flat-topped, red/purple, scaly nodules OVER knuckles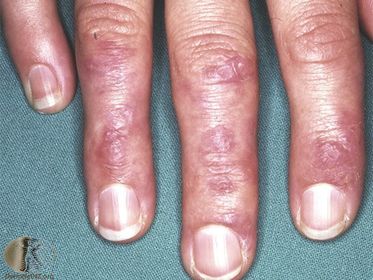
- 40—Dermatomyositis
Heliotrope Rash (periorbital edema)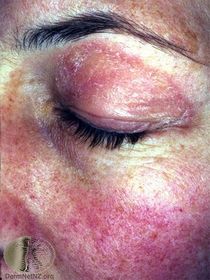
- 41—Dermatomyositis
(rash may precede muscle weakness by months WITHOUT pain)
Heliotrope Rash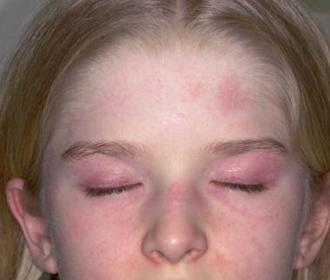
- 42—Epithelial Cyst
(Epidermoid / Sebaceous)
Dilated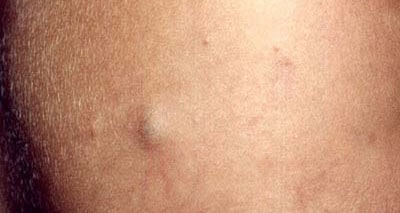
- 43—Dermoid Cyst
Newborn: lateral border of eyebrow OR in scalp
More fixed to bone than epidermoid.
- 44—Branchial Cyst
Lateral aspect of neck (defect of embryological closure)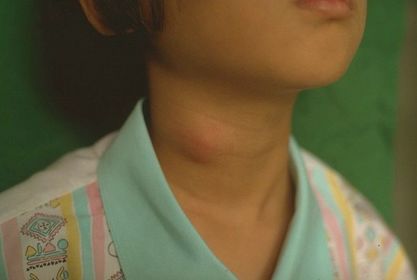
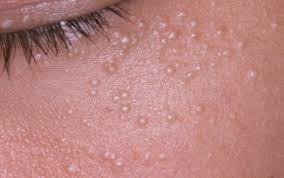
- 45—Milia
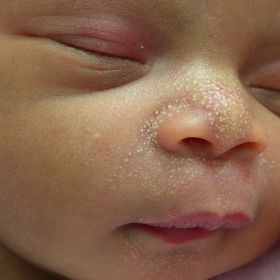
- 46—Milia
- 47—Pilomatricoma - Adnexal tumor
- cells of HAIR MATRIX
- NOT fixed
- blue (?)
- stretched skin
- Teeter totter sign (seesaw)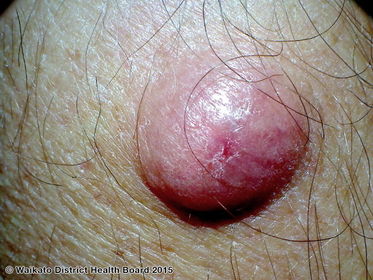
- 48—Pilomatricoma
Multi lobar papules
NOT fixed
Hard (calcify)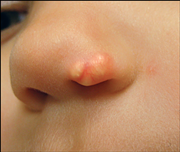
- 49—Syringoma - Adnexal Tumor
Cells of eccrine sweat glands. Eyelids, cheeks, etc.
Most common in DOWN Syndrome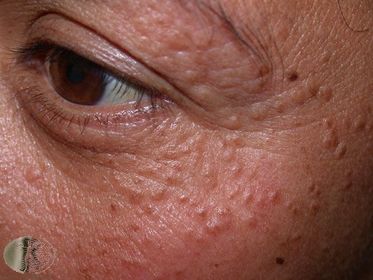
- 50—Trichoepithelioma
Cells of HAIR FOLLICLE
Firm, Benign. Cheeks, nose.
Confused with acne.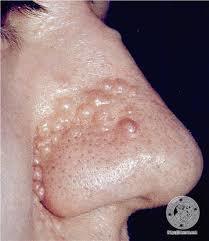
- 51—Trichoepithelioma
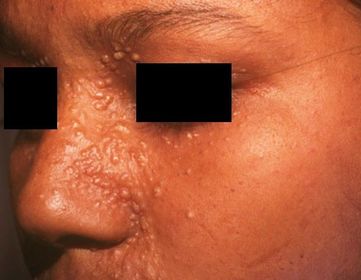
- 52—Dermatofibroma
well-defined. round. often pigmented.
@ leg/trunk.
SCAR BALL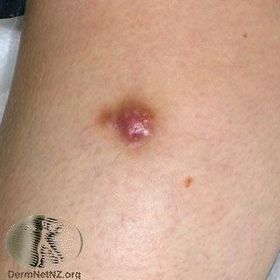
- 53—Dermatofibroma
PINCH SIGN: lateral pressure produces DIMPLING on its surface
Area of PREVIOUS TRAUMA (e.g. shaving) -- reactive proliferation of FIBROBLASTS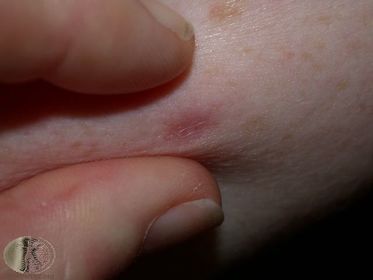
- 54—Hypertrophic Scar
Overgrowth of scar tissue. Remains at site of injury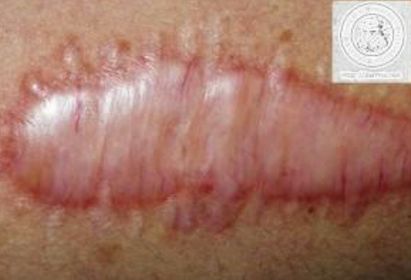
- 55—Keloid
esp. @ earlobe, presternal area, neck, face
No definition of border (noncompliant of previous scar)
- shiny & hairless
- progressively enlarging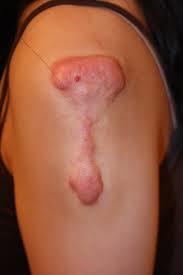
- 56—Neurofibroma
BUTTON-HOLE sign (dx): involutes into skin
Benign tumor of nerve sheath cells
Elephantiasis = whole limb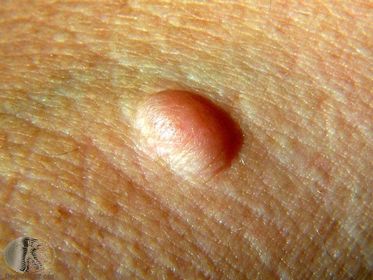
- 57—Plexiform Neurofibroma
Large clustering of neurofibromas (often gathering of hair in that area). Often associated with neurofibromatosis.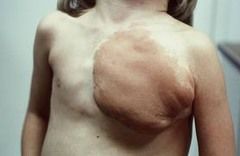
- 58—Lipoma
- soft & squishy
- SubQ nodules
- Mobile (UNattached to overlying skin)
- Solitary
- Begin in adolescence (≠ children)
- @ neck, chest, arms (forehead: elderly)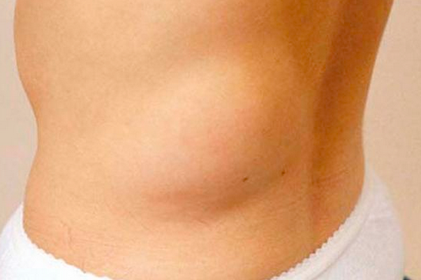
- 59—Granuloma Annulare
small, firm pap/nod
Circle / semicircle
Misdx: ringworm
Usually solitary (can have multiple)
@ ankles, WRISTS (aural areas, digits)
Dusky violaceous or skin-colored hue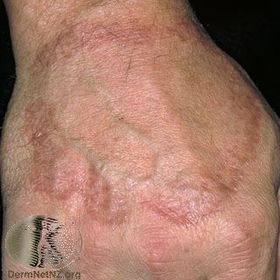
- 60—Granuloma Annulare
small, firm pap/nod
Circle / semicircle
Misdx: ringworm
Usually solitary (can have multiple)
@ ankles, wrists (aural areas, digits)
Dusky violaceous or skin-colored hue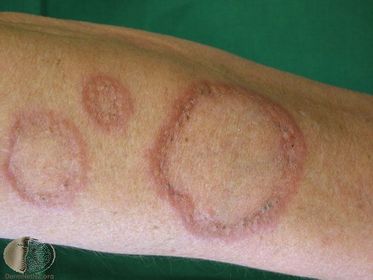
- 61—Juvenile Xanthogranuloma (JXG)
Orange/pink to yellow-brown.
Soft nodules.
Often MULTIPLE.
Large accum. of MACROPHAGES @ dermis
Also found on trunk, etc.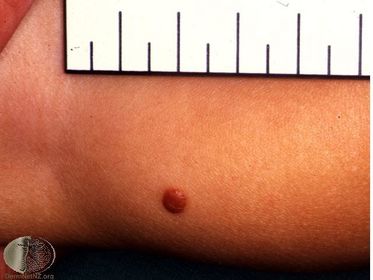
- 62—Juvenile Xanthogranuloma (JXG)
@ IRIS --> glaucoma (hyphema)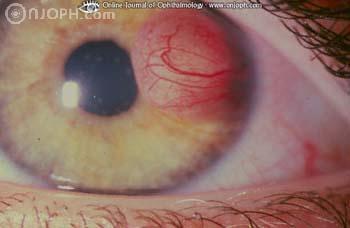
- 63—Juvenile Xanthogranuloma (JXG)
Orange/pink to yellow-brown.
Soft nodules.
Type of Non-Langerhan's Cell Histiocytosis.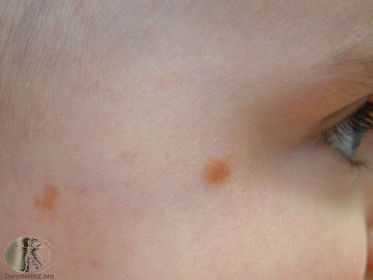
- 64—Pyogenic Granuloma (PG)
@ Acral areas: hands, fingers, face
Solitary
Dull red.
Firm (perhaps pedunculated)
BLEEDS easily: increased expression of vascular endothelial growth factor.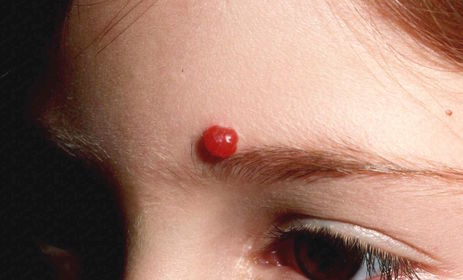
- 65—Pyogenic Granuloma (PG)
@ Acral areas
Solitary. Dull red. Firm nodules.
May be smooth/glistening...but often ulcerated & crusted if open.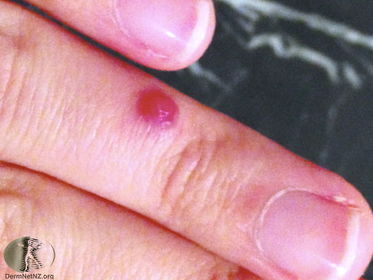
- 66—Langerhan Cell Histiocytosis (LCH)
Discrete. Papules or nodules.
Hemorrhage/petechia do NOT blanch
Red, orange, and/or yellow-brown.
Seborrheic Distribution.
Crusted scaling of SCALP, post auricular, perianal, & axillary areas.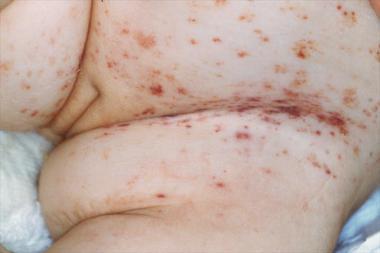
- 67—Langerhan Cell Histiocytosis (LCH)
Organs & lymph nodes may be affected.
Diagnosis via Biopsy.
Tx = chemotherapy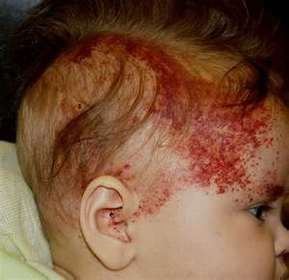
- 68—Congenital Self-Healing Reticulohistiocytosis
looks like LCH or PG (type of LCH)
Solitary
CRATERIFORM central erosion.
No tx, but monitor over time.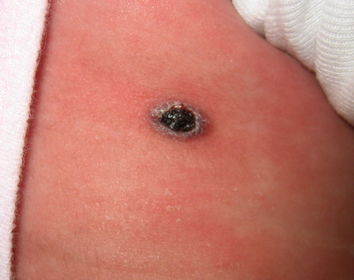
- 69—Benign Cephalic Histiocytosis
JXG on the head (non-LCH).
@ Face & neck.
Resolve during childhood (≠ tx)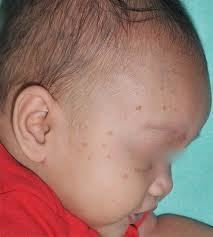
- 70—Benign Cephalic Histiocytosis
JXG on head (non-LCH)
2-5mm (small)
Yellow-red to tan papules.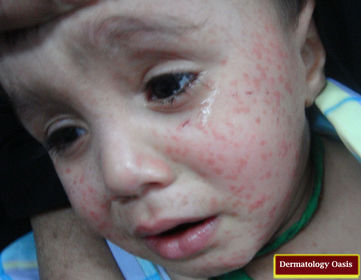
- 71—Kawasaki Disease
Mucocutaneous & lymph node
1. Abrupt high fever ≥ 5 days
2. Eyes: bilateral injection of conjunctiva (NO purulence or crusting)
3. Mouth: strawberry tongue; erythema
4. Cervical LAD. 5. Rash: nonspecific
6. Extremities: red palms/soles, Beau's lines (transverse lines on nail plates)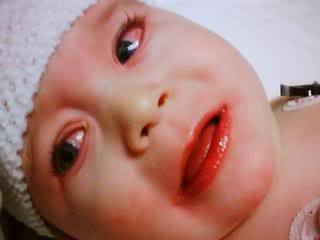
- 72—Kawasaki Disease
Beau's lines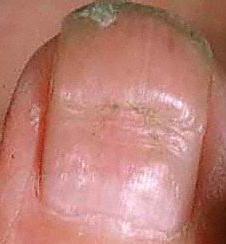
- 73—Kawasaki Disease
Nonspecific exanthem (no vesicles/crusts)
Treatment (acute: w/in 10 days of onset)
1. IVIG
2. ASA 80-100mg/kg/day (after fever controlled for 4-5 days)
3. Low dose aspirin 3-5mg/kg/day (continue forever if coronary artery abnormalities)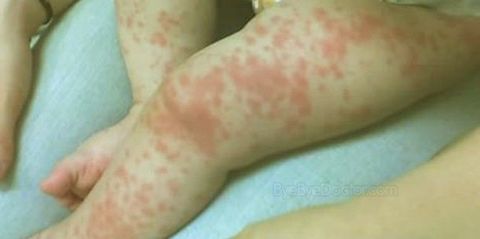
- 74—Erythema Multiforme
TARGET or IRIS lesion (concentric zone of color ∆)
- preceded by herpes labialis (?): HSV-specific host response
- NO prodrome.
- ABRUPT & symmetric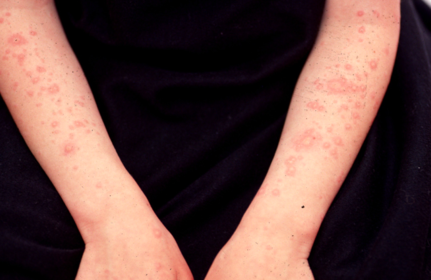
- 75—Erythema Multiforme
TARGET or IRIS lesion (concentric zone of color ∆: central duskiness, crust, or blister)
DDX: Urticaria
Sx relief: oral antihistamines
Recurrent dz: oral acyclovir -NOT steroids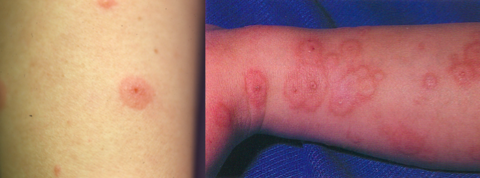
- 76Left = ? Right = ?Left = Erythema Multiform
- fixed (7 days)
- NO relief with Epi
Right = Urticaria
- transient (< 24 hrs)
- relief w/ Epi SQ
- clear center w/ red border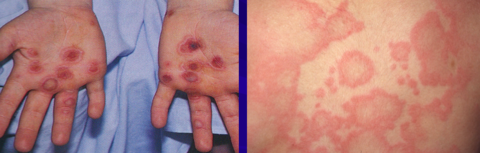
- 77—Stevens Johnson Syndrome
Prodrome 1-4 days
≥ 2 mucosal sites (oral / eyes)
HEMORRHAGIC crusts
Rapid progression to BULLAE & EROSIONS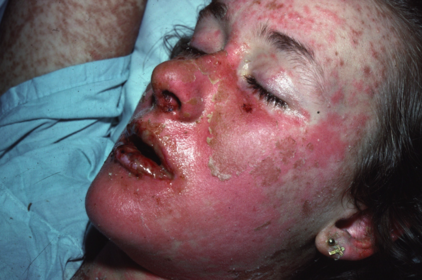
- 78—Stevens Johnson Syndrome
Etiology
- Drugs: NSAIDs, Sulfonamids, Anti-convul.
- Infection: Mycoplasma pneumonia, HSV
Tx: supportive care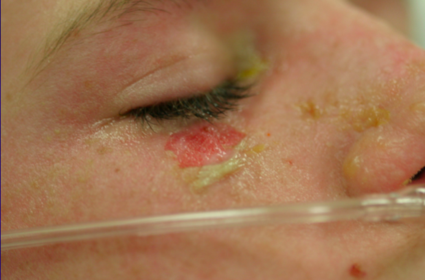
- 79—Stevens Johnson Syndrome
Tender red skin w/ dusky discoloration (lesions are targetoid)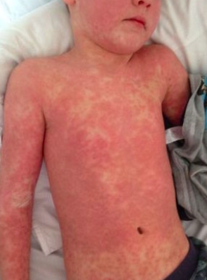
- 80—Urticaria
Acute. Itchy/burning. Clear in center. Transient.
Tx: Oral Antihistamine, Epi, Anti-Leukotriene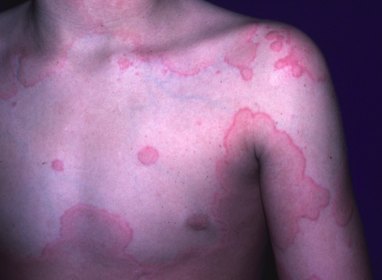
- 81—Urticaria
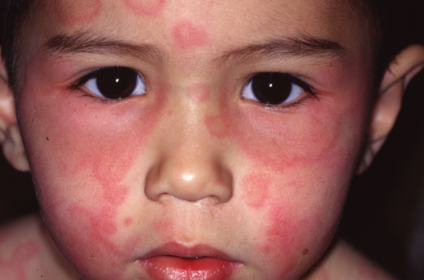
- 82—Urticaria
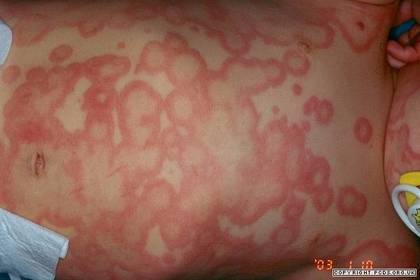
- 83—Angioedema
SubQ edema; Deep hives.
Large deep swelling with indistinct borders.
Eyelids, Lips, Hands.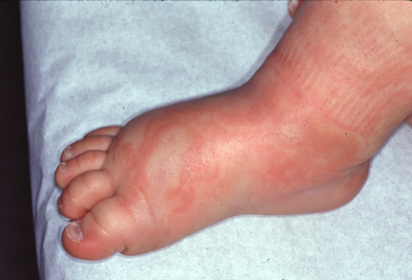
- 84—Dermatographism
Physical Urticaria
- 85—Heat- and Exercise-Induced Urticaria
(Physical Urticaria)
Sombrero Lesion: large flare with small central tiny wheal
Persistent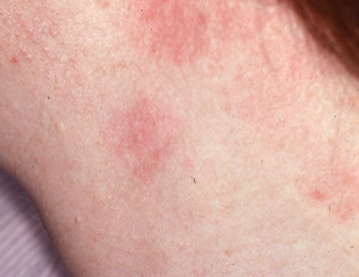
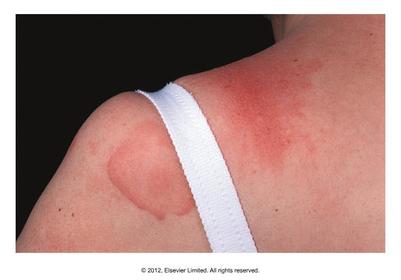
- 86—Delayed Pressure Urticaria
- 87—Salmon Patch (Nevus simplex)
"Stork Bite" / "Angel Kisses"
CAPILLARY Malformation
Most common
Face: fade over time...EXCEPT @ NECK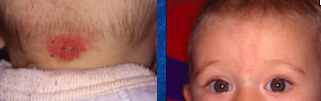
- 88—Port Wine Stain
CAPILLARY Malformation
Lacy. Reticulated. Purple.
BLANCH. Darker over time.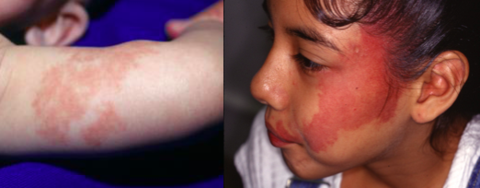
- 89—Port Wine Stain
Capillary Malformation
Face: hypertrophy, verrucous (warty) after puberty
Tx: pulsed-dye laser (PDL)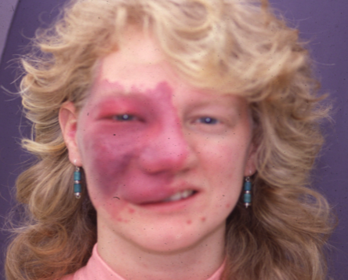
- 90—Sturge-Weber Syndrome
Facial Port Wine Stain in V1 Distribution (unilateral OR bilateral PWS)
Assoc. with CNS & EYES abnormalities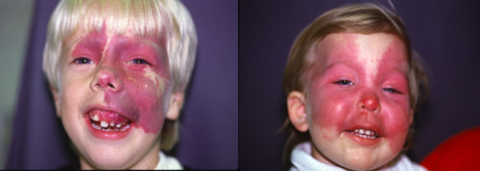
- 91—Sturge-Weber Syndrome
Capillary Malformation
V1 distribution (PWS)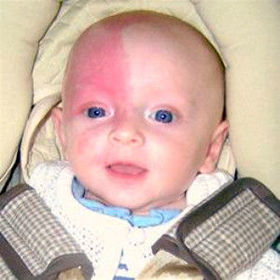
- 92—Klippel-Trenaunay Syndrome
Overgrowth of extremity associated with PWS, venous malformation, or mixed malformation.
Soft Tissue Hypertrophy. Swelling.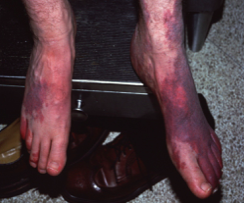
- 93—Klippel-Trenaunay Syndrome
PWS/Venous/Mixed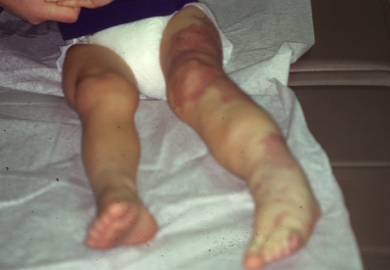
- 94—Klippel-Trenaunay Syndrome
Sometimes assoc. with varicose veins.
PWS/Venous/Mixed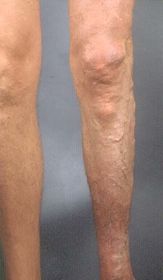
- 95—Parkes-Weber Syndrome
Overgrowth of extremity assoc. with arteriovenous malformation (AVM)
Similar to Kippel-Trenaunay, but
- higher flow (seen on imaging)
- pulsatile (AVM)
- 96—Venous Malformation
STATIC (grows only with child, since birth)
Never regresses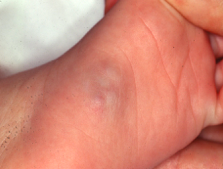
- 97—Venous Malformation
Can sometimes look like hemangiomas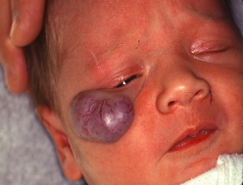
- 98—Arteriovenous Malformations
PALPABLE THRILL.
Rare.
Frequently over-diagnosed.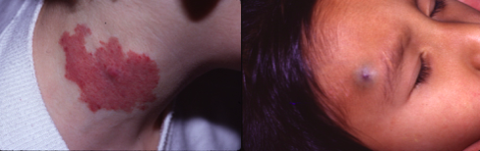
- 99—Microcystic Lymphatic Malformation
(lymphangioma circumscriptum)
If localized, they look like FROG EGGS.
More infiltrative.
Difficult to completely excise.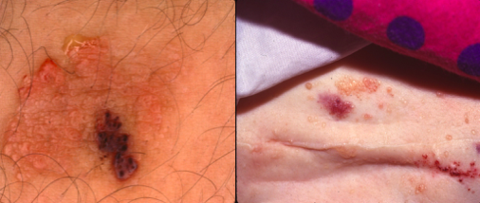
- 100—Macrocystic Lymphatic Malformation
(cavernous lymphangioma - cystic hygroma)
Less infiltrative. More easily excised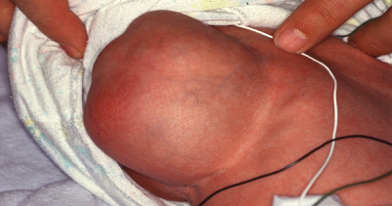
- 101—Cutis Marmorata Telangiectasia Congenita
More common in DOWN Syndrome.
Present at birth.
Stays fixed (fades over time). UNILATERAL. Atrophy of skin/limb. Mottled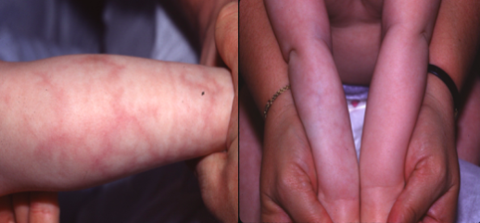
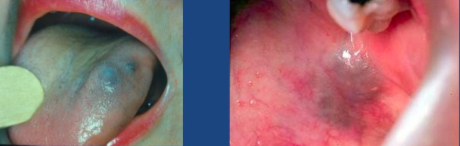
- 102—Hemangioma
(pictured: white/blue macule)
Tumor of CAPILLARY endothelium.
MOST COMMON tumor of infancy
Rapid growth phase out of proportion to growth of child. Long period of regression.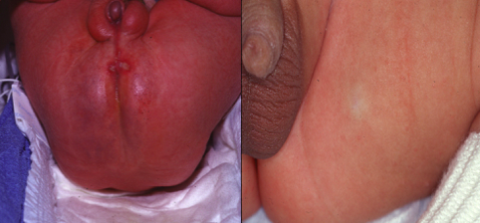
- 103—Hemangioma
- 104—Hemangioma
(pictured: telangiectasia)
More common if: FEMALE, PREMATURE, CVS, AMNIO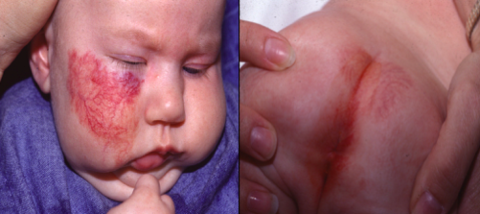
- 105—Hemangioma
(pictured: red papules)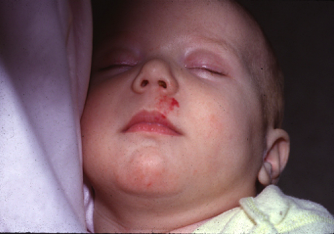
- 106—Hemangioma
Pictured: superficial
"strawberry"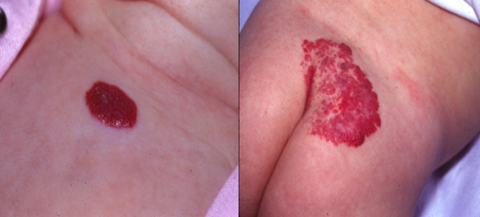
- 107—Hemangioma
Pictured: deep
Soft compressible RUBBERY bluish nodule under skin.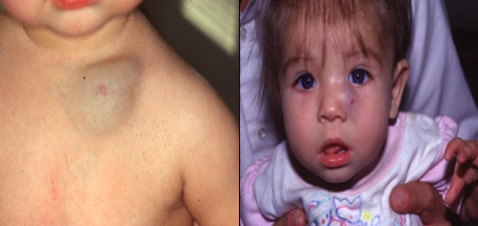
- 108—Hemangioma
Pictured: mixed
RAPID growth phase: 4-8 wks thru 6-9 m.o.
Proliferation (6-12 mo): grows slowly & APPROXIMATES GROWTH of infant
Slow INVOLUTION begins: > 12 mo
(softer, less warm, flattens out)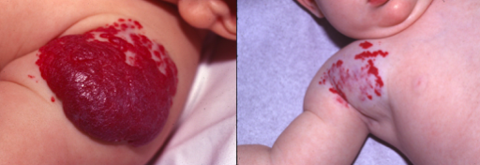
- 109—Hemangioma
BEARD distribution = AIRWAY involvement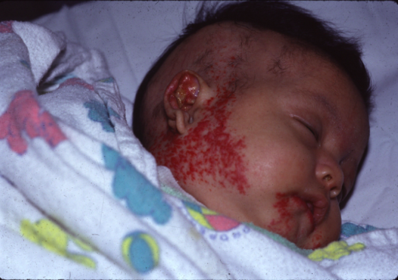
- 110—Hemangiomas
(top left = deep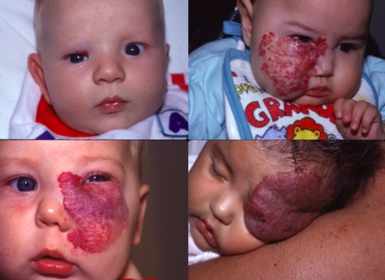
- 111—Hemangiomas
Worry about cartilage destruction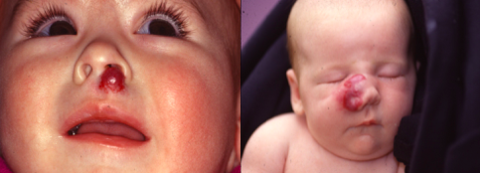
- 112—Ulceration of Hemangioma
(complication - others include, bleeding, infection [STAPH AUREUS], obstruction of vital fxn, HIGH OUTPUT CARDIAC FAILURE)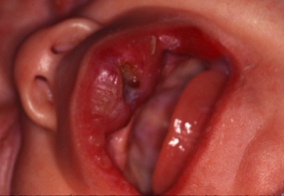
- 113—Involution of Hemangioma
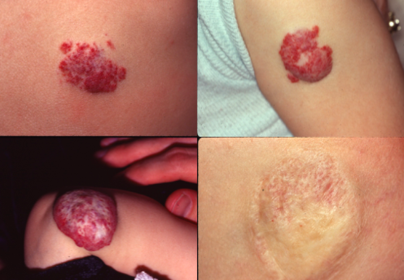
- 114—Residua of Hemangiomas
- Hypopigmentation
- Telangiectasia
- Fibrofatty deposits
- Excess skin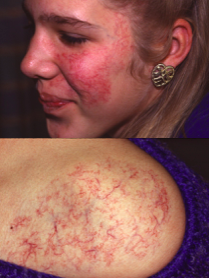
- 115—Diffuse Neonatal Hemangiomatosis
May have HUNDREDS of lesions
< 2 cm
May have INTERNAL INVOLVEMENT (e.g. central hypothyroidism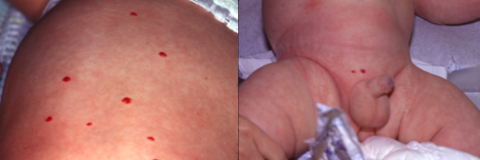
- 116—Spider Telangiectasia
Red/pink ill-defined macule
@ cheeks, nose, posterior hands
BLANCH completely w/ pressure (put glass slide over it to make sure)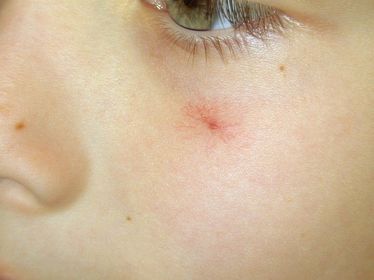
- 117—Spider Telangiectasia
Sun-exposed area
2-6 yo kids
Fair-skinned individuals
Dilation of CENTRAL feeding ARTERIOLE w/ multiple radiating capillaries.