
Mapa mental
Meningitis
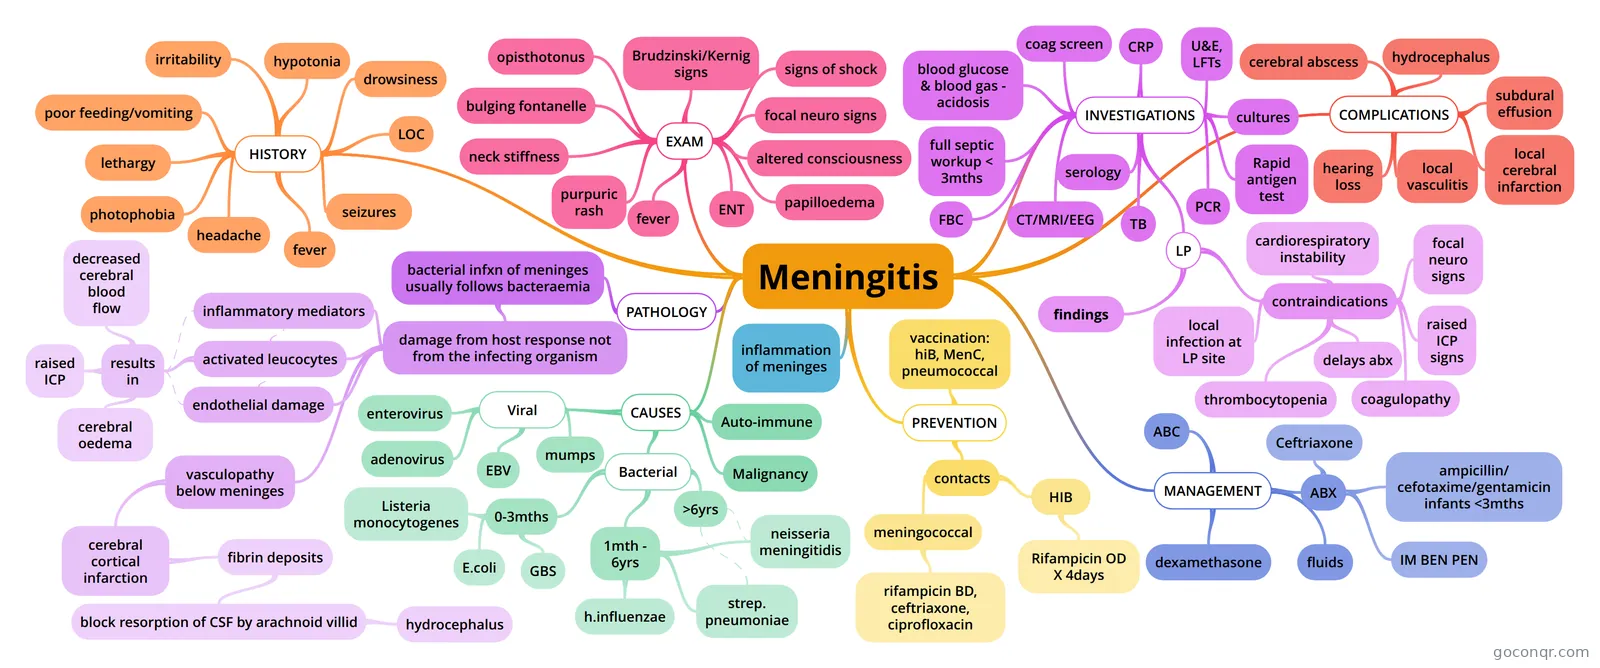
Mind map: meningitis
Contenido del mapa
Meningitis
- all of this is in relation to bacterial meningitis
INVESTIGATIONS
- FBC
- white cell count reflects infection can't do lumbar puncture if thrombocytopaenic
- blood glucose & blood gas - acidosis
- coag screen
- cant do lumbar puncture if coagulopathy
- CRP
- U&E, LFTs
- cultures
- blood, throat swab, urine, stool for bacteria & viruses
- Rapid antigen test
- for meningitis organisms, can be done on blood, CSF, or urine. without LP, bacteriological diagnosis can be achieved in at least 50% of cases from the blood by culture or PCR or RAT
- LP
- for CSF unless contraindicated. presence of inflammatory cells in CSF confirms diagnosis
- contraindications
- procedure carries a risk of coning of the cerebellum through the foramen magnum - in these circumstances, can be postponed until child's condition has stabilised
- cardiorespiratory instability
- focal neuro signs
- raised ICP signs
- coma, high BP, low HR, papilloedema
- coagulopathy
- thrombocytopenia
- local infection at LP site
- delays abx
- findings
- Normal: clear appearance, 0-5/mm3 WBC. 0.15 -0.4g/L protein. >50% of blood is glucose. Bacterial: turbid appearance, greatly increased polymorphs, greatly increased protein, greatly decreased glucose Viral: Clear appearance, increased lymphocytes, normal or slightly increased protein, normal or slightly decreased glucose TB: turbid/clear/viscous appearance, increased lymphocytes, hugely increased protein, hugely decreased glucose. encephalitis: clear appearance, normal or slightly increased lymphocytes, normal or slightly increased protein, normal or slightly decreased glucose
- PCR
- blood & CSF for possible organisms
- serology
- serum for comparison of convalescent titres. serological diagnosis can be made on convalescent serum 4-6 weeks after the presenting illness if necessary.
- TB
- CXR, Mantoux test. gastric washings or sputum, early morning urines
- CT/MRI/EEG
- consider if immunocompromised, CNS disease, new onset seizure, papilloedema, impaired consciousness & focal neurological signs
- full septic workup < 3mths
- FBC, urinalysis/culture, throat swab, blood culture, CXR, lumbar puncture
- FBC
inflammation of meninges
CAUSES
- Bacterial
- 0-3mths
- GBS
- E.coli
- & other coliform bacteria
- Listeria monocytogenes
- 1mth - 6yrs
- neisseria meningitidis
- strep. pneumoniae
- h.influenzae
- >6yrs
- 0-3mths
- Viral
- EBV
- Epstein-Barr Virus
- adenovirus
- enterovirus
- mumps
- mumps meningitis now rare due to MMR vaccine
- EBV
- Malignancy
- Auto-immune
- Bacterial
PATHOLOGY
- bacterial infxn of meninges usually follows bacteraemia
- damage from host response not from the infecting organism
- inflammatory mediators
- activated leucocytes
- results in
- cerebral oedema
- decreased cerebral blood flow
- raised ICP
- results in
- endothelial damage
- vasculopathy below meninges
- cerebral cortical infarction
- fibrin deposits
- block resorption of CSF by arachnoid villid
- hydrocephalus
- block resorption of CSF by arachnoid villid
- fibrin deposits
- cerebral cortical infarction
- damage from host response not from the infecting organism
- bacterial infxn of meninges usually follows bacteraemia
HISTORY
- fever
- headache
- photophobia
- lethargy
- poor feeding/vomiting
- irritability
- hypotonia
- drowsiness
- LOC
- seizures
EXAM
- fever
- purpuric rash
- neck stiffness
- not always present in infants
- bulging fontanelle
- infants
- opisthotonus
- arching of back
- Brudzinski/Kernig signs
- Brudzinski - flexion of the neck with the child supine causes flexion of the knees and hips Kernig - with the child lying supine and with the hips and knees flexed, there is back pain on extension of the knee
- signs of shock
- tachycardia, tachypnoea, prolonged cap refill, hypotension.
- focal neuro signs
- altered consciousness
- papilloedema
- rare
- ENT
COMPLICATIONS
- hearing loss
- inflammatory damage to cochlear hair cells may lead to deafness. all children who have had meningitis should have an audiological assessment promptly - may benefit from hearing amplification or cochlear implant.
- local vasculitis
- may lead to cranial nerve palsies or other focal lesions
- local cerebral infarction
- may result in focal or multifocal seizures, which may subsequently lead to epilepsy
- subdural effusion
- particularly assoc. w h.influenzae & pneumococcal meningitis. confirmed by CT scan. most resolve spontaneously - may require prolonged antibiotic treatment.
- hydrocephalus
- may result from impaired resorption of CSF (communicating hydrocephalus) or blockage of the ventricular outlets by fibrin (non-communicating hydrocephalus). ventricular shunt may be required.
- cerebral abscess
- clinical condition deteriorates, emergence of signs of a space-occupying lesion. temperature continues to fluctuate. confirmed on CT scan. drainage of abscess required
- hearing loss
MANAGEMENT
- ABC
- ABX
- length of course of abx depends on causative organism and clinical response
- Ceftriaxone
- immediately if spreading petechiae, purpuric rash, signs of meningitis/septicaemia, appears ill and abnormal CRP/WBC or if in doubt.
- ampicillin/ cefotaxime/gentamicin infants <3mths
- IM BEN PEN
- any febrile child with a purpuric rash should be given intramuscular benzylpenicillin immediately and transferred urgently to hospital
- fluids
- dexamethasone
- beyond neonatal period, dexamethasone administered with abx reduced risk of long-term complications such as deafness
PREVENTION
- vaccination: hiB, MenC, pneumococcal
- contacts
- meningococcal
- rifampicin BD, ceftriaxone, ciprofloxacin
- HIB
- rifampicin OD x 4 days
- Rifampicin OD X 4days
- meningococcal
Información
- Descripción
- (Paediatric Neurology) Paediatrics Mapa Mental sobre Meningitis, creado por Siobhan O'Regan el 11/05/2017.
- Creado por
- Siobhan O'Regan
- Visitas
- 37
- Valoración