
Test
Dental OSCE quiz 1
Este test tiene tipos de pregunta que se abren en el reproductor de siempre.
Preguntas del test (25)
1Is this impacted canine palatal or buccal to the centrals?
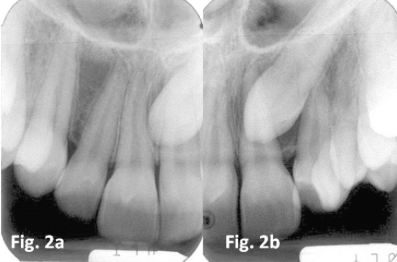
- Apalatal
- Bbuccal
2Is this impacted canine palatal or buccal to the arch?
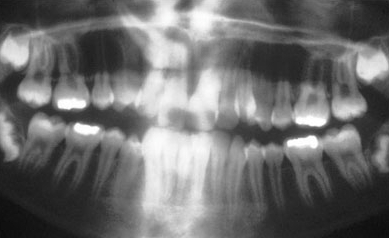
- APalatal
- BBuccal
3Are these impacted canines palatal or buccal to the arch?
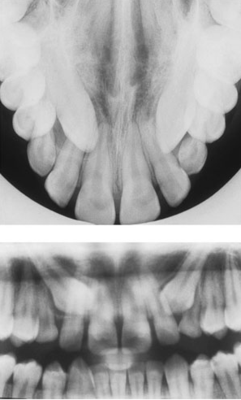
- APalatal
- BBuccal
41. Gain [blank_start]consent[blank_end]. Check for [blank_start]latex[blank_end] allergies, explain to patient the procedure and why we need the rubber raincoat.
2. Select clamp - [blank_start]DW[blank_end] for primary molars and premolars, [blank_start]FW[blank_end] for partially erupted molars, [blank_start]BW[blank_end] for permanent molars.
3. Tie [blank_start]floss[blank_end] around clamp before application
4. Rubber dam must be pre-[blank_start]punched[blank_end]. 3 overlapping holes for [blank_start]single[blank_end] tooth, 5-6 overlapping holes for [blank_start]trough[blank_end]
5. Clamp applied [blank_start]first[blank_end] without rubber dam
6. Apply rubber dam when clamp is [blank_start]secure[blank_end] - rock [blank_start]lingually[blank_end], then [blank_start]buccally[blank_end].
7. [blank_start]Frame[blank_end] attached to support dam
8. [blank_start]Trough[blank_end] isolation required dam to be stretched to include all required teeth
9. Apply wedget or wedge to [blank_start]mesial[blank_end] aspect of most mesial isolated tooth.- Aconsent
- Blatex
- CDW
- DFW
- EBW
- Ffloss
- Gpunched
- Hsingle
- Itrough
- Jfirst
- Ksecure
- Llingually
- Mbuccally
- NFrame
- OTrough
- Pmesial
5Label the image with different aspects required for an extra oral examination.
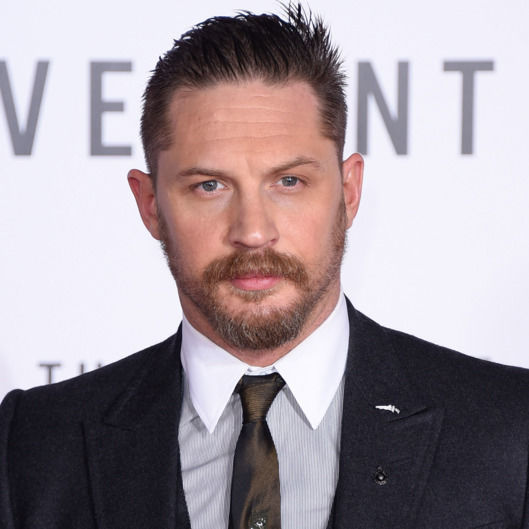
- AFacial appearance
- BSkin
- CEyes
- DEars
- ENeck
- FTMJ
- GMoM
- HFacial appearance
- ISkin
- JEyes
- KEars
- LNeck
- MTMJ
- NMoM
- OFacial appearance
- PSkin
- QEyes
- REars
- SNeck
- TTMJ
- UMoM
- VFacial appearance
- WSkin
- XEyes
- YEars
- ZNeck
- AATMJ
- ABMoM
- ACFacial appearance
- ADSkin
- AEEyes
- AFEars
- AGNeck
- AHTMJ
- AIMoM
- AJFacial appearance
- AKSkin
- ALEyes
- AMEars
- ANNeck
- AOTMJ
- APMoM
- AQFacial appearance
- ARSkin
- ASEyes
- ATEars
- AUNeck
- AVTMJ
- AWMoM
- AXFacial appearance
- AYSkin
- AZEyes
- BAEars
- BBNeck
- BCTMJ
- BDMoM
- BEThyroid
- BFThyroid
- BGThyroid
- BHThyroid
- BIThyroid
- BJThyroid
- BKThyroid
- BLThyroid
6Label the correct lymph nodes for an EO exam from the dropdown menus

- APreauricular
- BMastoid (posterior auricular)
- COccipital
- DParotid
- ESubmandibular
- FSubmental
- GPreauricular
- HMastoid (posterior auricular)
- IOccipital
- JParotid
- KSubmandibular
- LSubmental
- MPreauricular
- NMastoid (posterior auricular)
- OOccipital
- PParotid
- QSubmandibular
- RSubmental
- SPreauricular
- TMastoid (posterior auricular)
- UOccipital
- VParotid
- WSubmandibular
- XSubmental
- YPreauricular
- ZMastoid (posterior auricular)
- AAOccipital
- ABParotid
- ACSubmandibular
- ADSubmental
- AEPreauricular
- AFMastoid (posterior auricular)
- AGOccipital
- AHParotid
- AISubmandibular
- AJSubmental
- AKDeep cervical chain
- ALSupraclavicular
- AMDeep cervical chain
- ANSupraclavicular
- AODeep cervical chain
- APSupraclavicular
- AQDeep cervical chain
- ARSupraclavicular
- ASDeep cervical chain
- ATSupraclavicular
- AUDeep cervical chain
- AVSupraclavicular
- AWPreauricular
- AXMastoid (posterior auricular)
- AYOccipital
- AZParotid
- BASubmandibular
- BBSubmental
- BCDeep cervical chain
- BDSupraclavicular
- BEPreauricular
- BFMastoid (posterior auricular)
- BGOccipital
- BHParotid
- BISubmandibular
- BJSubmental
- BKDeep cervical chain
- BLSupraclavicular
7Label the image with muscles of mastication you should palpate during EO exam.

- ATemporalis
- BTrapezius
- CMasseter
- DSternocleidomastoid
- ETemporalis
- FMasseter
- GTrapezius
- HSternocleidomastoid
- ITemporalis
- JMasseter
- KTrapezius
- LSternocleidomastoid
- MTemporalis
- NMasseter
- OTrapezius
- PSternocleidomastoid
8During a TMJ examination, you should stand behind the patient and palpate both joints [blank_start]simultaneously[blank_end]. The patient should be asked to [blank_start]open[blank_end] and close their mouth, and move their jaw [blank_start]laterally[blank_end]. You should note any clicking, [blank_start]locking[blank_end] (trismus), grinding or grating ([blank_start]crepitus[blank_end]), limited [blank_start]opening[blank_end], deviation, and pain.
- Asimultaneously
- Bopen
- Claterally
- Dlocking
- Ecrepitus
- Fopening
9For an ID block you should do the following:
1. Explain what you are going to do; gain [blank_start]consent[blank_end]. Numbness will last for around [blank_start]2[blank_end] or [blank_start]3[blank_end] hours and patient should avoid hot drinks and [blank_start]biting[blank_end] their lip
2. Check for any [blank_start]allergies[blank_end] or contraindications. LA contains [blank_start]vasoconstrictors[blank_end] and an additive called [blank_start]sodium[blank_end] metabisulphate that could cause a reaction.
3. Check the [blank_start]expiry date[blank_end] on the cartridge, check your choice of [blank_start]vasoconstrictor[blank_end], check it has no [blank_start]air bubbles[blank_end].
4. Dry mucosa and apply [blank_start]topical[blank_end] anaesthetic - xylonor gel contains [blank_start]xylocaine[blank_end].
5. Put the needle together - long needles are coloured [blank_start]yellow[blank_end] and short needles [blank_start]blue[blank_end].
6. Check the [blank_start]bung[blank_end] is orientated correctly!
7. Patient should open their mouth [blank_start]wide[blank_end] so you can visualise anatomical landmarks. Ensure you have the operating [blank_start]light[blank_end] on to visualise tissues for the block.
8. Palpate the [blank_start]coronoid process[blank_end] with your thumb at the greatest depression - known as the coronoid [blank_start]notch[blank_end]
9. Slide your thumb [blank_start]posteriorly[blank_end] until you can palpate the [blank_start]internal oblique ridge[blank_end].
10. The syringe is positioned between the [blank_start]premolars[blank_end] on the opposite side and needle inserted at the level of the thumb.
11. The injection site is 1cm above the [blank_start]occlusal[blank_end] plane of the molars and medial to the thumb, lateral to the [blank_start]pterygomandibular[blank_end] raphe.
12. The needle is advanced around 2.5cm. [blank_start]Bone[blank_end] should be contacted to ensure correct position.
13. When the needle meets the middle section of the rams, withdraw slightly by 1 or 2 mm so that the needle is not [blank_start]subperiosteal[blank_end]
14. Make sure you [blank_start]aspirate[blank_end] at this point.
15. Inject [blank_start]slowly[blank_end] - 1.5ml or 2/3rds of a cartridge. This improves patient comfort and you can assess any patient [blank_start]reactions[blank_end] to the solution before you inject too much.
16. The rest of the cartridge is injected as you [blank_start]withdraw[blank_end] the needle to block the [blank_start]lingual[blank_end] nerve.
17. Double click the syringe and dispose in the [blank_start]sharps bin[blank_end]
18. Remove gloves and apply alcohol gel.- Aconsent
- B2
- C3
- Dbiting
- Eallergies
- Fvasoconstrictors
- Gsodium
- Hexpiry date
- Ivasoconstrictor
- Jair bubbles
- Ktopical
- Lxylocaine
- Myellow
- Nblue
- Obung
- Pwide
- Qlight
- Rcoronoid process
- Snotch
- Tposteriorly
- Uinternal oblique ridge
- Vpremolars
- Wocclusal
- Xpterygomandibular
- YBone
- Zsubperiosteal
- AAaspirate
- ABslowly
- ACreactions
- ADwithdraw
- AElingual
- AFsharps bin
10What must you ensure you do after extracting a tooth? (check all that apply)
- AAllow socket to bleed freely
- BGive post operative instructions
- CWrite notes on the computer
- DCompress socket with fingers
- EGet patient to bite down on rolled gauze
- FAllow patient to rinse socket with water
- GAllow patient to leave immediately
- HCheck for haemostasis
- IDispose of tooth immediately
- JCheck for apices of tooth
11How long should a patient NORMALLY take to achieve haemostasis post-extraction?
- A<5 minutes
- B<10 minutes
- C<20 minutes
- D>1 hour
12How long should a patient wait before coming back to the LDI with a non healing socket or continued symptoms?
- A5 days
- B3 days
- C7 days
- D10 days
- E2 weeks
13How many times daily should a patient carry out salty mouth rinses on the day after an extraction?
- AOnce
- BTwice
- CThree times a lady
- DTen
14What is the correct secondary movement for extraction of an UL5?
- APalatal
- BBuccal and palatal
- CRotational
- DDown
15What is the primary movement for all dental extractions?
- AApical
- BBuccal
- CRotational
- DCoronal
16What is the secondary movement for a LR2 extraction?
- ARotational
- BPalatal
- CLingual
- DBuccal
17What movement is more likely to result in root fracture during extraction of upper molars?
- ARotational
- BPalatal
- CBuccal
- DApical
18Luxators are used to: (tick all that apply)
- ASever the periodontal ligament attachment
- BExpand the socket
- CLever the tooth from the socket
19This is an example of a
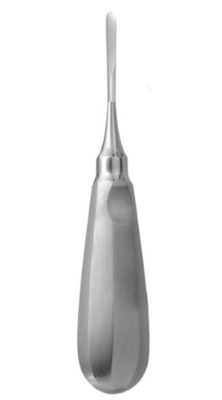
- ALuxator
- BElevator
- CForceps
20This is an example of a:

- ALuxator
- BElevator
- CForceps
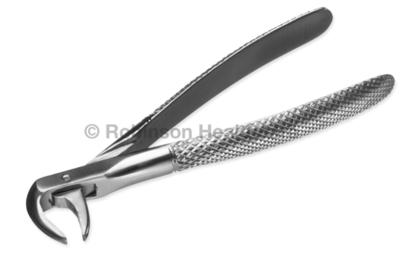
21Which forceps would you most likely use for a lower premolar extraction?
- A
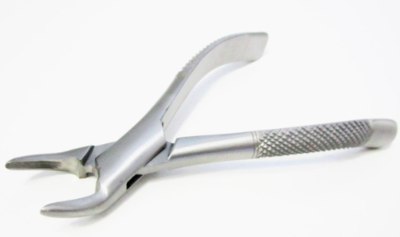
- B
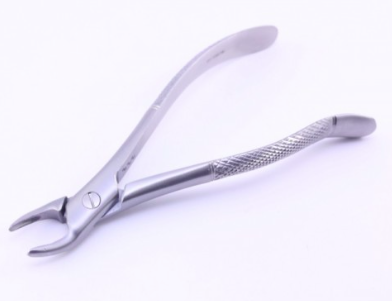
- C
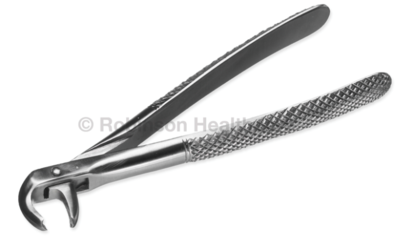
- D
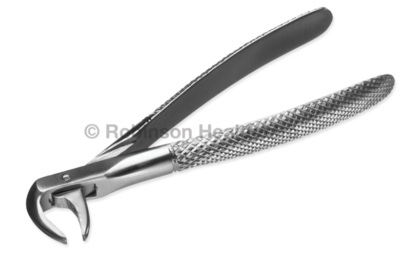
- A
22Which forceps would you use for an upper left lateral incisor extraction?
- A
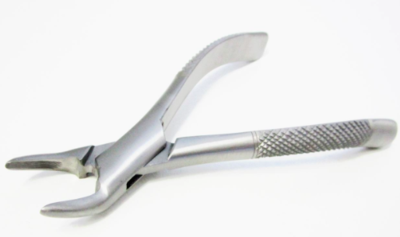
- B
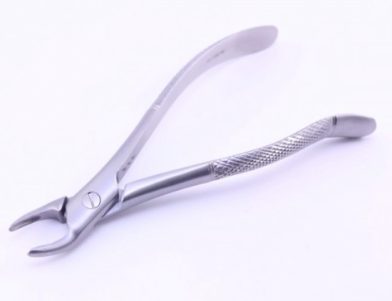
- C
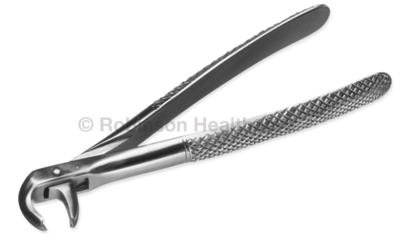
- D
- A
23You've just given a patient a new set of dentures and are giving them some advice. You advise them:
- Leave dentures in for at least [blank_start]24[blank_end] hours initially
- Feeling of compaction and excess [blank_start]saliva[blank_end] will [blank_start]decrease[blank_end] with time
- There may be [blank_start]sore[blank_end] spots to begin with
- Their lips will [blank_start]relax[blank_end] with time
- Eat [blank_start]small[blank_end] sized pieces of food and eat [blank_start]evenly[blank_end] on [blank_start]both[blank_end] sides of mouth
- Avoid [blank_start]sticky[blank_end] foods
- [blank_start]Muscles[blank_end] need to be re educated to accommodate dentures
- [blank_start]Clean[blank_end] denture using a soft nylon brush with [blank_start]soap[blank_end] over the sink. They can use [blank_start]disclosing[blank_end] solutions to help them clean.
- Soak dentures overnight in denture cleanser ([blank_start]hypochlorite[blank_end] solution)
- Clean mouth with warm [blank_start]salt[blank_end] water [blank_start]twice[blank_end] daily- A24
- Bsaliva
- Cdecrease
- Dsore
- Erelax
- Fsmall
- Gevenly
- Hsticky
- Iboth
- JMuscles
- KClean
- Lsoap
- Mdisclosing
- Nhypochlorite
- Osalt
- Ptwice
24Unerupted incisors have several possible causes, these tend to be either [blank_start]hereditary[blank_end] or environmental in origin.
Environmental causes include:
1. Trauma - [blank_start]avulsion[blank_end] or intrusion of the primary teeth that causes damage to the permanent tooth. This may include the root/crown axis to deviate, known as [blank_start]dilaceration[blank_end]. The permanent tooth may also become [blank_start]ankylosed[blank_end] to the bone. In these cases [blank_start]extraction[blank_end] may be required and tooth replacement options considered.
2. [blank_start]Retained[blank_end] primary teeth causing [blank_start]delayed[blank_end] eruption - this may cause a physical [blank_start]obstruction[blank_end] to the path of eruption of the permanent tooth. The most straightforward option here would be [blank_start]extraction[blank_end] of the primary tooth if there is no other obstruction and the teeth are close to [blank_start]eruption[blank_end].
Hereditary causes may include the presence of [blank_start]supernumerary[blank_end] teeth in the arch, [blank_start]cleft[blank_end] lip or palate, abnormal tooth/tissue ratio or other rarer conditions such as [blank_start]cleidocranial[blank_end] dysostosis.
The other option is that the permanent teeth may be congenitally [blank_start]absent[blank_end]!
According to the RCS guidelines, we should start monitoring unerupted incisors when:
1. [blank_start]Contralateral[blank_end] teeth erupted more than 6 months ago
2. Both centrals are unerupted and the lowers erupted more than [blank_start]12[blank_end] months ago
3. Deviation in the normal sequence of eruption
During an intra oral examination, you may find that:
- The primary teeth have been retained beyond normal [blank_start]exfoliation[blank_end] dates (which is [blank_start]6[blank_end] or [blank_start]7[blank_end] years for upper centrals, [blank_start]7[blank_end] or [blank_start]8[blank_end] years for upper laterals)
- There may be buccal or palatal [blank_start]swellings[blank_end] on palpation
- Note the space available for incisors - [blank_start]9[blank_end]mm for centrals and [blank_start]7[blank_end]mm for laterals
You may wish to take some [blank_start]radiographs[blank_end] to determine the cause of the unerupted teeth. The [blank_start]parallax[blank_end] technique can locate the position of impacted teeth.- Ahereditary
- Bavulsion
- Cdilaceration
- Dankylosed
- Eextraction
- FRetained
- Gdelayed
- Hobstruction
- Iextraction
- Jeruption
- Ksupernumerary
- Lcleft
- Mcleidocranial
- Nabsent
- OContralateral
- P12
- Q6
- R7
- S7
- T8
- Uexfoliation
- Vswellings
- W9
- X7
- Yradiographs
- Zparallax
25The upper canines usually erupt around [blank_start]11[blank_end] or [blank_start]12[blank_end] years of age. [blank_start]Congenitally[blank_end] absent canines is rare 0.3%. [blank_start]Impaction[blank_end] of canines is more common, and is usually bilateral. You should be able to [blank_start]palpate[blank_end] maxillary canines around 9 years of age in the buccal [blank_start]sulcus[blank_end].
Causes of impacted maxillary canines may be due to the:
- [blank_start]Long[blank_end] path of eruption
- [blank_start]Short[blank_end] rooted or [blank_start]absent[blank_end] upper lateral incisors ([blank_start]peg[blank_end] laterals)
- Crowding
- [blank_start]Retention[blank_end] of primary canine (an indicator rather than a cause!)
- [blank_start]Genetic[blank_end] factors. It may run in the [blank_start]family[blank_end].
- It should also be noted that impacted canines is associated with other dental anomolies
You should first assess the child [blank_start]clinically[blank_end] to see if you can tell where the tooth is displaced. If you suspect displacement you may wish to take some [blank_start]radiographs[blank_end].
The radiographs most commonly used for assessing ectopic canines are [blank_start]panoramic[blank_end] radiographs, upper [blank_start]occlusal[blank_end] radiographs, lateral [blank_start]cephalometric[blank_end] (for more accurate localisation), [blank_start]cone beam[blank_end] computerised tomography, and periodicals (useful for prognosis of retained deciduous canines).
Management depends on wether the teeth are [blank_start]buccally[blank_end] or [blank_start]palatally[blank_end] displaced.
Buccal displacements are usually due to [blank_start]crowding[blank_end], so relief of [blank_start]crowding[blank_end] is usually the option
Palatal displacements may require surgical [blank_start]exposure[blank_end] with orthodontic [blank_start]alignment[blank_end], or surgical [blank_start]removal[blank_end] of the impacted canine.
Occasionally unerupted canines can cause [blank_start]resorption[blank_end] of adjacent lateral incisor roots and possibly the centrals. In this case intervention should be done swiftly.- A11
- B12
- CCongenitally
- DImpaction
- Epalpate
- Fsulcus
- GLong
- HShort
- Iabsent
- Jpeg
- KRetention
- LGenetic
- Mfamily
- Nclinically
- Oradiographs
- Ppanoramic
- Qocclusal
- Rcephalometric
- Scone beam
- Tbuccally
- Upalatally
- Vcrowding
- Wcrowding
- Xexposure
- Yalignment
- Zremoval
- AAresorption
Información
- Descripción
- Dental osce Leeds 4th yr 2016. Credit to Introduction to Orthodontics by Laura Mitchell for orthodontic information.
- Idioma
- English
- Visitas
- 1.065
- Etiquetas
- Valoración
- Aún sin valoraciones Valora este test