Mind map
COPD

Map content
COPD
PATHOPHYSIOLOGY
- Emphysema "Pink Puffer"
- Decrease aveoli elasticity in connective tissue of lungs
- Airway instability
- Increase lung compliance
- Chronic Bronchitis "Blue Bloaters"
- Bronchial inflammation + edema
- Mucus hypersecretion
- Bronchospasms
- Airway obstruction, Air trapping
- Hypoxia
- Polycythemia
- Increased thickness of blood
- Increased thickness of blood
- Pulmonary vasoconstriction
- increase pulmonary vasculature resistance
- Pulmonary hypertension
- Hypertrophy of right ventricle
- Cor pulmonale
- Right sided heart failure
- Cor pulmonale
- Hypertrophy of right ventricle
- Pulmonary hypertension
- increase pulmonary vasculature resistance
- Hypercapnia
- Respiratory acidosis
- Hypoxemia
- Cyanosis
- Polycythemia
- Hypoxia
- Emphysema "Pink Puffer"
CLINICAL OBSERVATIONS
- Etiology
- Heredity
- Smoking
- Chemical + Air pollutants
- Infection
- Age
- Symptoms
- Anorexia
- Difficulty eating
- Decrease levels of ADLs
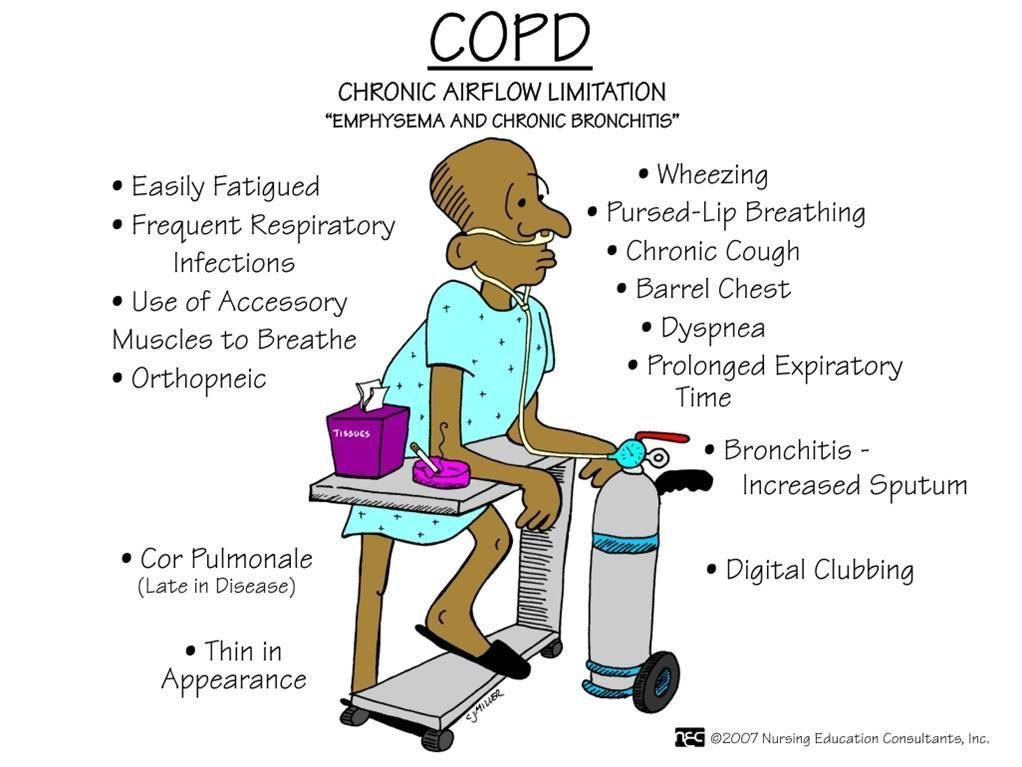
- Dyspnea
- Orthopnea
- Productive cough
- Fatigue
- Headaches
- Wheezing
- Bloating
- Swelling of feet
- Etiology
DIAGNOSIS
- ABG findings
- Low PaO2; ↑ PaCO2 (> 45 mmHg) ;↓ pH (< 7.35); ↑Bicarbonate level found in late stages of COPD (> 26 mmHg)
- Pulmonary tests
- Chest X-ray
- Spirometry
- Oximetry
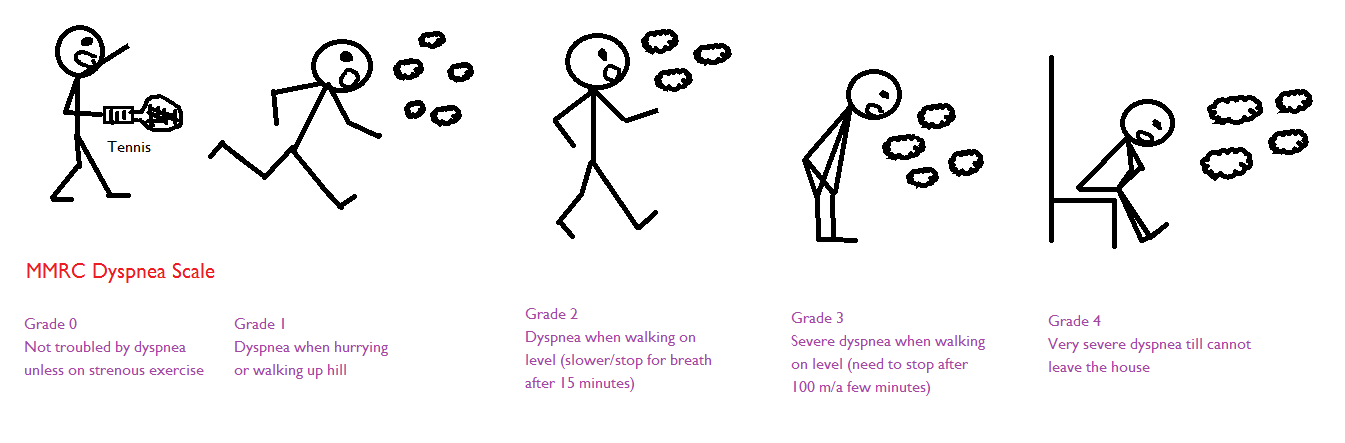
- Dyspnea Scale
- Walk test determines oxygen desaturation in blood
- Patient health hx.
- Family history of COPD
- AAT deficiency
- Body is unable to make enough proteins to protect the lungs and liver from damage; may lead to emphysema and/or liver disease
- Hx./frequency of respiratory infections; hx. of resp. and cardiac problems
- ECG findings
- ST depression + T inversion; RHF
- ABG findings
TREATMENTS
- Drug therapy
- Corticosteroid
- Prescribed for moderate to severe forms of COPD
- Inhaler
- Pills
- Combination medicines
- Inhalers that combine a bronchodilator and a corticosteroid help to treat and prevent COPD exacerbations
- fluticasone + salmeterol
- fluticasone furoate + vilanterol trifenatate
- budesonide + formoterol fumarate
- Inhalers that combine a bronchodilator and a corticosteroid help to treat and prevent COPD exacerbations
- Prescribed for moderate to severe forms of COPD
- Bronchodilators
- Aids by opening the airways in the lungs, thus making it easier to breath
- Rapid-onset bronchodilators: relieves SOB in few minutes
- Slow-onset bronchodilators: take longer to act (i.e., 4-6 hrs, and some lasting 24 hrs)
- Beta-2 agonists
- Anticholinergics
- Aids by opening the airways in the lungs, thus making it easier to breath
- Corticosteroid
- Oxygen therapy
- Effective for those with low blood-oxygen levels (hypoxemia) and/or those with lung damage due to infections (i.e., pneumonia)
- Reduces workload on the heart and work of breathing
- Surgical therapy
- Lung transplantation
- Usually a single lung transplantation; aids in improving quality of life
- Lung volume reduction surgery
- Removal of the damaged lung to improve respiratory function
- Bullectomy
- Surgical removal of a bulla to improve symptoms and respiratory function for those with emphysema
- Lung transplantation
- Nutritional therapy
- Breathing requires a lot of energy for those with COPD as muscles use 10x more calories than those without COPD
- Having a high calorie & high protein diet
- Eat small meals (~ 5-6 meals) to avoid bloating
- Calorie increasing desserts such as ice cream can aid supplementary intake
- Avoid foods that require a lot of chewing
- Exercise & treatment 1 hr before and after eating
- Gas-forming foods
- Exercise & treatment 1 hr before and after eating
- AVOID!
- Breathing requires a lot of energy for those with COPD as muscles use 10x more calories than those without COPD
- Nursing Management
- Assessment
- Obtain patients complete health history + physical assessment; collecting subjective + objective data
- Planning
- Formulate patient goals: improve QoL, prevent disease progression, assess patient knowledge and ability to perform long-term goals, relieve symptoms
- Evaluation
- Expected Outcomes: improved sleep cycle, maintaining body weight, effective coughing, normal breath sounds
- Implementation
- Health Promotion: smoking cessation, family hx. of COPD & AAT deficiency
- Acute intervention: due to secondary causes (i.e., pneumonia, acute resp. failure, cor pulmonale)
- Ambulatory care & Home Care: perform exercises (i..e, walk 15-20 mins/day for at least 3x a week), instruct pt. to wait 5 mins after finishing the exercise before using bronchodilators and instead allocate for slow pursed-lip breathing
- Acute intervention: due to secondary causes (i.e., pneumonia, acute resp. failure, cor pulmonale)
- Health Promotion: smoking cessation, family hx. of COPD & AAT deficiency
- Assessment
- Drug therapy
COMPLICATIONS
- Infection + air pollution
- Changes in dyspnea/cough/sputum
- Exacerbations of COPD
- Exacerbations of COPD
- Changes in dyspnea/cough/sputum
- Discontinuation of corticosteroid and/or bronchodilators
- overuse of sedatives /benzodiazapenes/opiods
- Depression/anxiety
- Surgery or severe painful illness involving chest or abdomen
- Peptic ulcer disease
- Acute respiratory failure
- Infection + air pollution
an irreversible, slow, progressive obstruction of airflow into and/or out of the lungs mainly due to an abnormal inflammatory response from the lungs