
Mind map
Brain Tumors
Map content
Brain Tumors
Differential Diagnosis of Double Vision
- Lens Problems
- Cataract
- Cornea Problems
- Astigmatism\Dry eyes syndrome\Infections
- Eye Muscle Problems
- Strabismus\ Graves disease
- Nerve problem
- Diabetes\Myasthenia gravis \MS\ Guillain Barre syndrome
- Brain problems
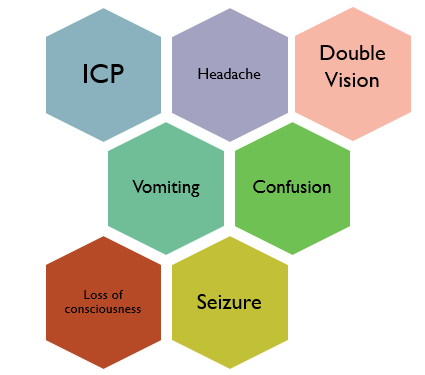
- Brain tumors\Migraine\Increased ICP
- Lens Problems
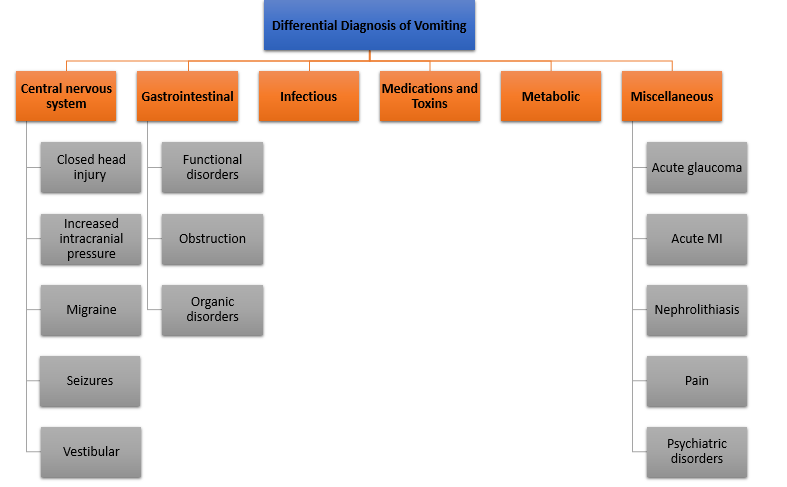
Differential Diagnosis of Vomiting
Differential Diagnosis of Limb Weakness
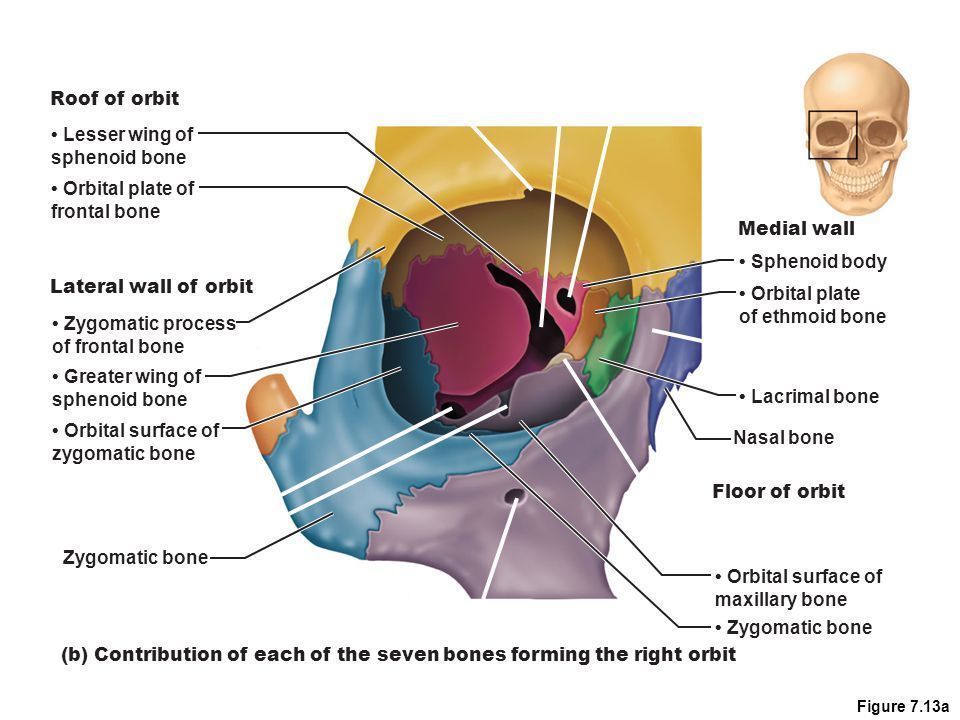
Anatomy of orbit
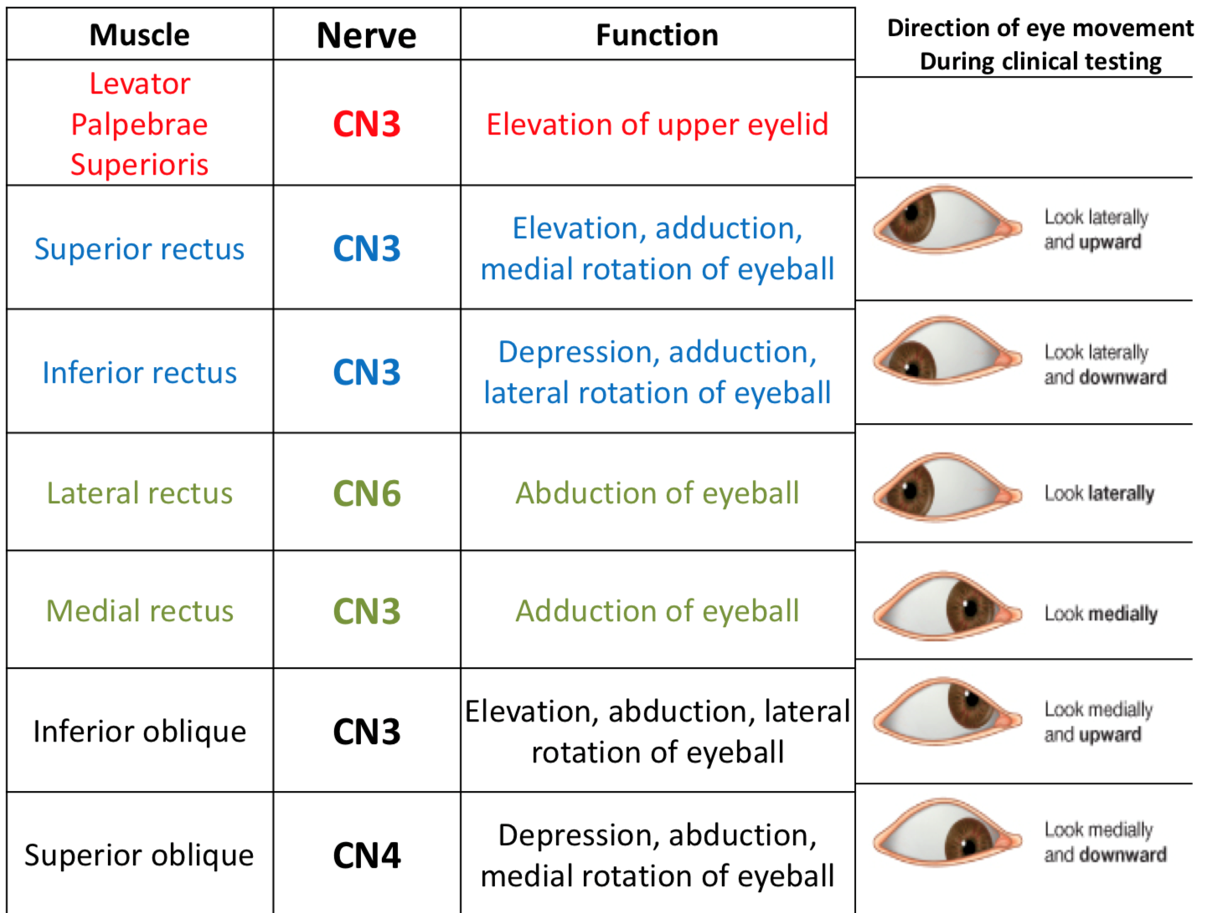
- Anatomy of extraocular muscles
- Anatomy of extraocular muscles
The Visual Pathway
- 1st order neuron
- its cell bodies lie in the retina (ganglion cells)
- their axons form the optic nerve, optic chiasma & optic tract.
- their axons form the optic nerve, optic chiasma & optic tract.
- their axons form the optic nerve, optic chiasma & optic tract.
- its cell bodies lie in the retina (ganglion cells)
- 2nd order neuron
- its cell bodies lie in the L.G.B
- their axons form the optic radiation that terminate in the visual cortex of the occipital lobe of the brain
- its cell bodies lie in the L.G.B
- 1st order neuron
Types of speech
- Apraxia of speech
- and involves inconsistent production of speech sounds and rearranging of sounds in a word
- Cluttering
- a rapid rate of speech, which makes speech difficult to understand.
- Dysarthria
- is a weakness or paralysis of speech muscles
- Dysprosody
- It is characterized by alterations in intensity, in the timing of utterance segments, and in rhythm, cadence, and intonation of words.
- Muteness
- is complete inability to speak
- Speech Sound Disorders
- involve difficulty in producing specific speech sounds
- Stuttering
- Voice disorders
- are impairments, often physical, that involve the function of the larynx or vocal resonance
- Apraxia of speech
Clinical presentation
Risk Factors of Brain Tumors
- Age\Gender\Home & Work Exposures\Family History\Exposure to infections, viruses and allergens\Electromagnetic fields \Race and ethnicity\Ionizing Radiation\Head Injury & Seizures
Types of brain tumors
- Adults tumors
- primary tumors are usually supratentorial.
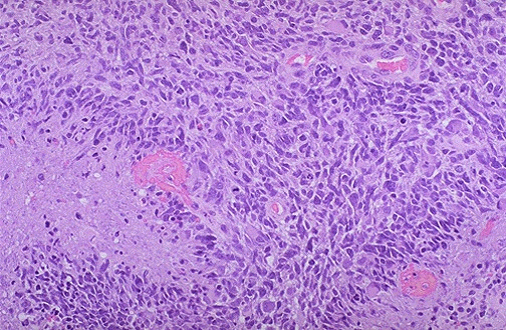
- glioblastoma multiforme
- Malignant, high-grade tumor of astrocytes
- Most common primary malignant CNS tumor in adults
- Usually arises in the cerebral hemisphere; characteristically crosses the corpus callosum
- Butterfly lesion
- Histology
- Characterized by regions of necrosis surrounded by tumor cells (pseudopalisading) and endothelial cell proliferation; tumor cells are GFAP positive.
- Characterized by regions of necrosis surrounded by tumor cells (pseudopalisading) and endothelial cell proliferation; tumor cells are GFAP positive.
- Poor prognosis
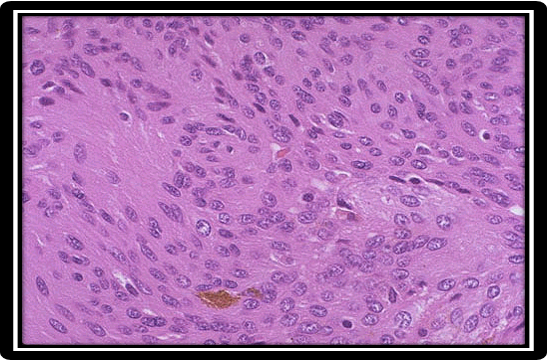
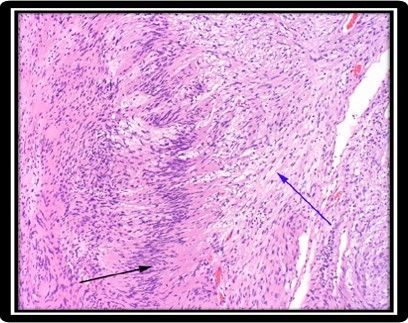
- schwannoma
- Benign tumor of Schwann cells
- involves cranial or spinal nerves; within the cranium, most frequently involves cranial nerve VIII at the cerebellopontine angle (presents as loss of hearing and tinnitus)
- Tumor cells are S-100 positive.
- Histology
- prognosis
- Good prognosis after resection
- meningioma
- Benign tumor of arachnoid cells
- Most common benign CNS tumor in adults
- More commonly seen in women; rare in children
- May present as seizures; tumor compresses, but does not invade, the cortex.
- Imaging reveals a round mass attached to the dura.
- Histology
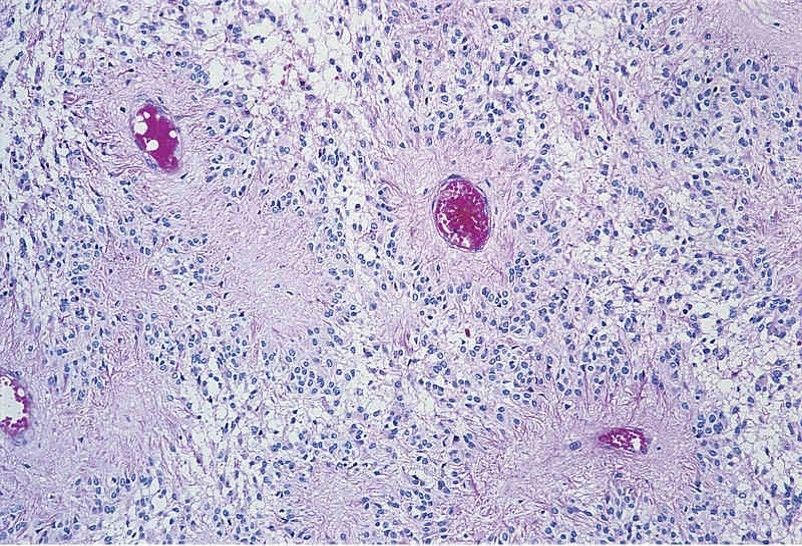
- shows a whorled pattern; psammoma bodies may be present.
- shows a whorled pattern; psammoma bodies may be present.
- Prognosis
- Good prognosis
- Grade 1
- 93%
- Grade 2
- 5%
- Grade 3
- 2%
- Grade 1
- Good prognosis
- Children tumors
- primary tumors are usually infra tentorial
- pilocytic astrocytoma
- Benign tumor of astrocytes
- Most common CNS tumor in children; usually arises in the cerebellum
- Imaging reveals a cystic lesion with a mural nodule
- Histology
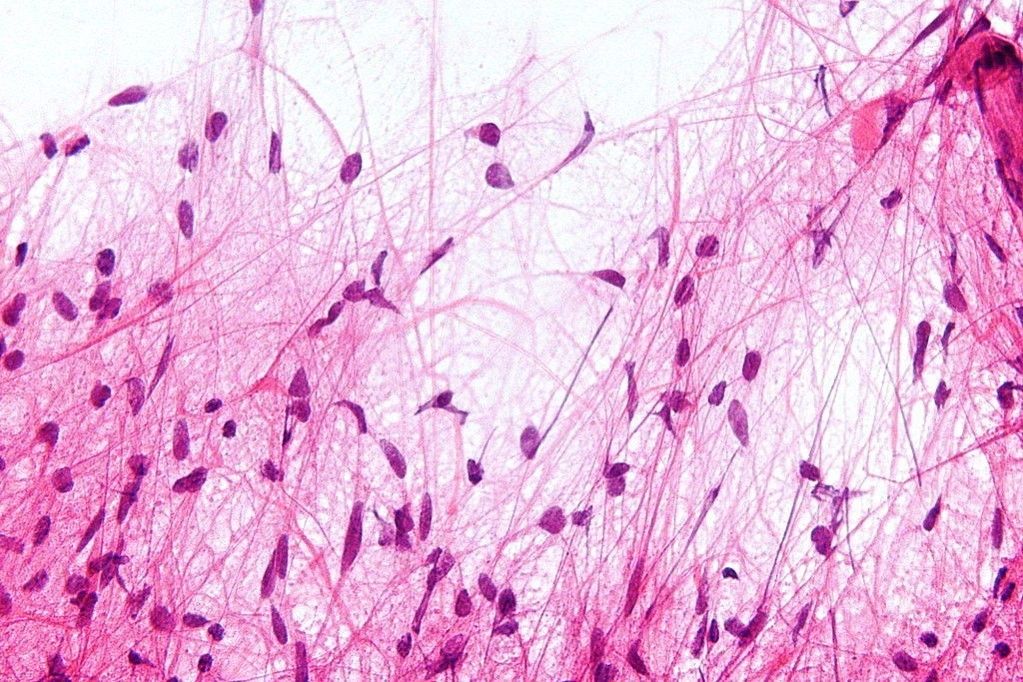
- Biopsy shows Rosenthal fibers (thick eosinophilic processes of astrocytes) and eosinophilic granular bodies; tumor cells are GFAP positive.
- Biopsy shows Rosenthal fibers (thick eosinophilic processes of astrocytes) and eosinophilic granular bodies; tumor cells are GFAP positive.
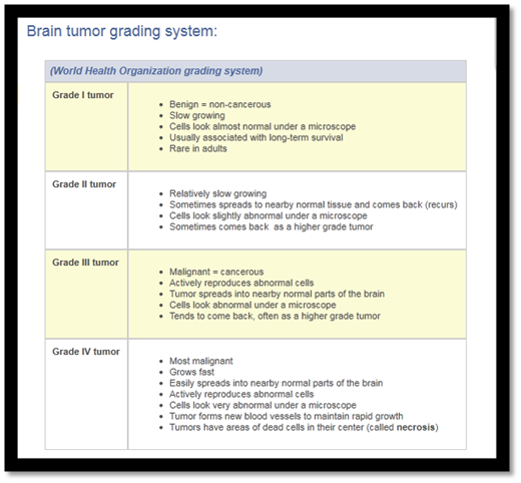
- Grading
- ependymoma
- Malignant tumor of ependymal cells
- Most commonly arises in the 4th ventricle; may present with hydrocephalus
- Histology
- Perivascular pseudorosettes are a characteristic finding on biopsy
- Perivascular pseudorosettes are a characteristic finding on biopsy
- Prognosis
- Recur after surgery, acquire more aggressiveness
- Prognosis depends on the location and its histologic grade.
- Recur after surgery, acquire more aggressiveness
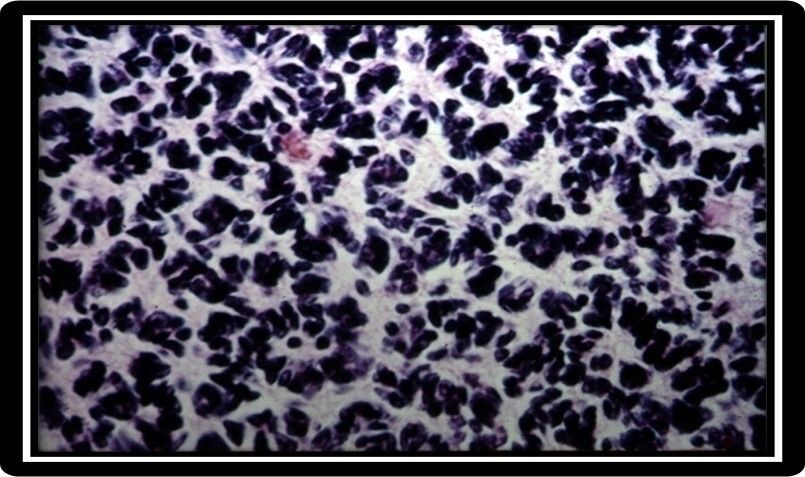
- medulloblastoma
- Malignant tumor derived from the granular cells of the cerebellum (neuroectoderm)
- Histology
- Histology reveals small, round blue cells; Homer-Wright rosettes may be present.
- Histology reveals small, round blue cells; Homer-Wright rosettes may be present.
- Poor prognosis; tumor grows rapidly and spreads via CSF.
- Metastasis to the cauda equina is termed 'drop metastasis
- Prognosis
- Resection & radiation allow 5-year survival of 75%.
- Metastatic Brain tumors
- Breast\Lung\Skin\Kidney\GIT
- Other tumors
- OLIGODENDROGLIOMA
- Malignant tumor of oligodendrocytes
- Imaging reveals a calcified tumor in the white matter, usually involving the frontal lobe; may present with seizures
- Histology
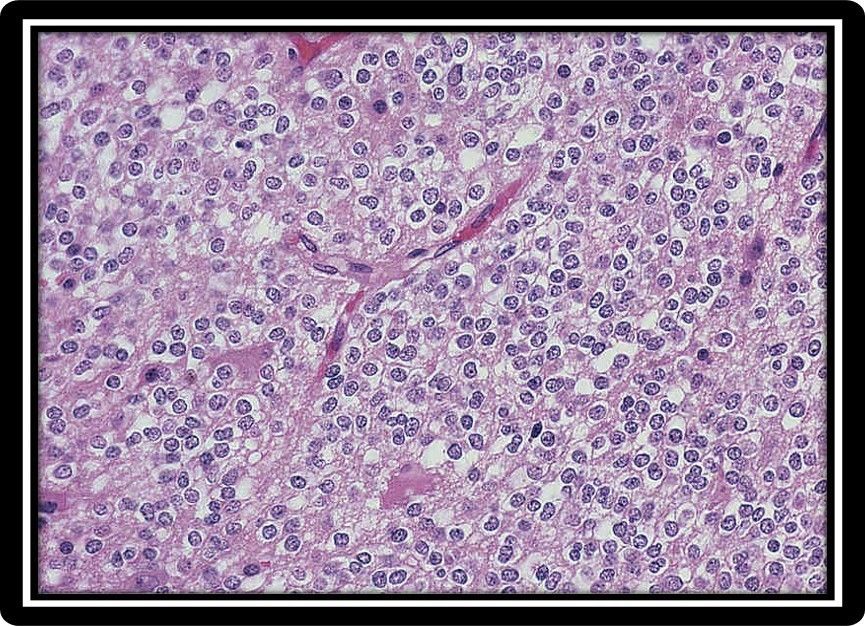
- 'Fried-egg' appearance of cells on biopsy
- 'Fried-egg' appearance of cells on biopsy
- prognosis
- Slow-growing, long survival (5-10 yrs)
- Grade 2 (with treatment): 10-20 years
- Grade 3 (with treatment): 5-10 years
- 5-year survival rate is 75%, 10-year survival rate is 50%.
- OLIGODENDROGLIOMA
- Adults tumors
Investigations of space occupying lesions of the brain
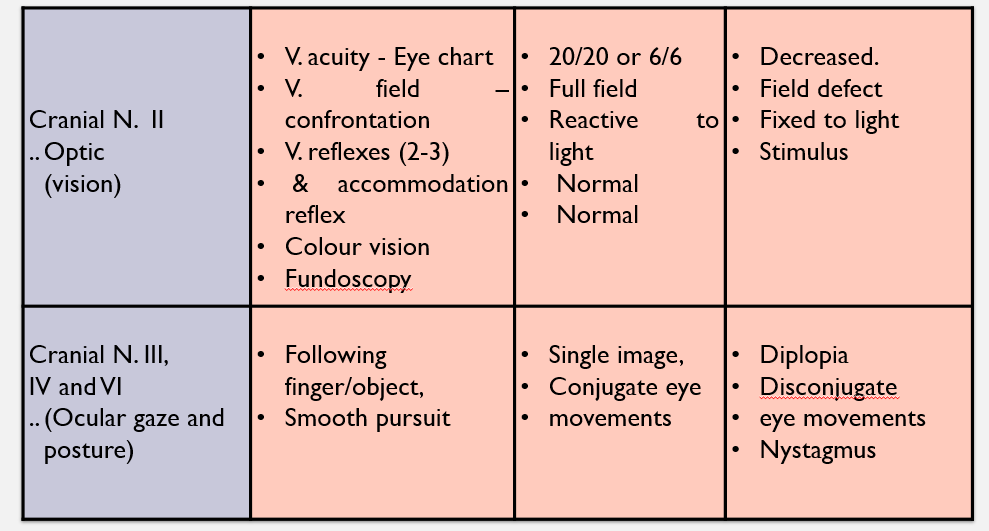
Eye Examination
Risks of Brain Surgery
- Allergic reaction to anesthesia\Bleeding in the brain\A blood clot\Brain swelling\Coma\Impaired speech, vision, coordination, or balance\Infection in the brain or at the wound site\Memory problems\Seizures\Stroke
Brain tumor grading system
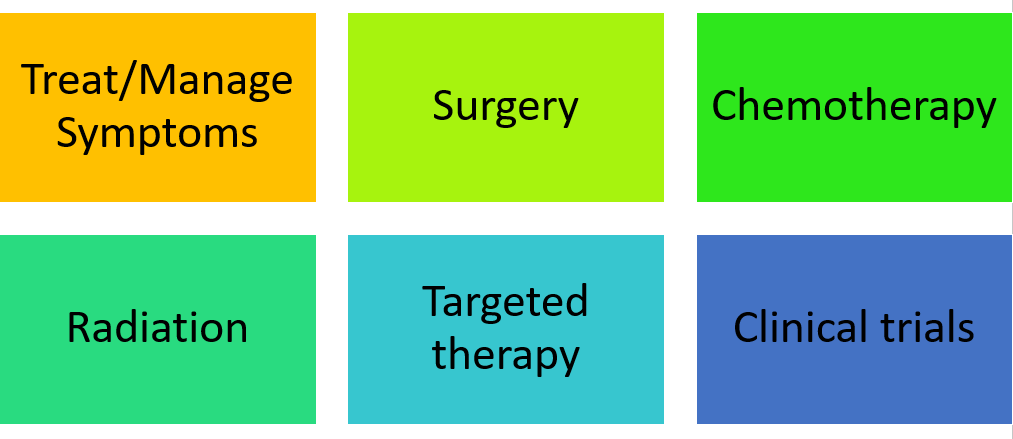
Management plan
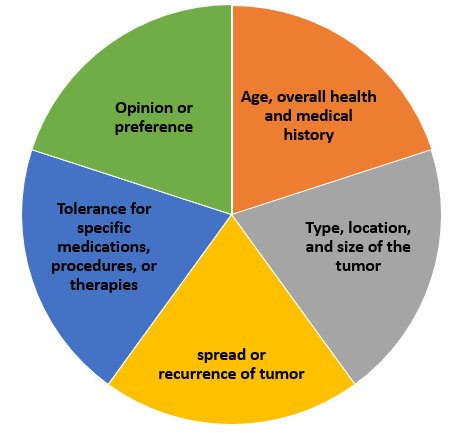
- Consider
- Consider
Images and files in the map



Information
- Description
- Mind Map on Brain Tumors, created by hamda ali on 04/11/2018.
- Created by
- hamda ali
- Views
- 224
- Rating