
Mind map
HIV/AIDS
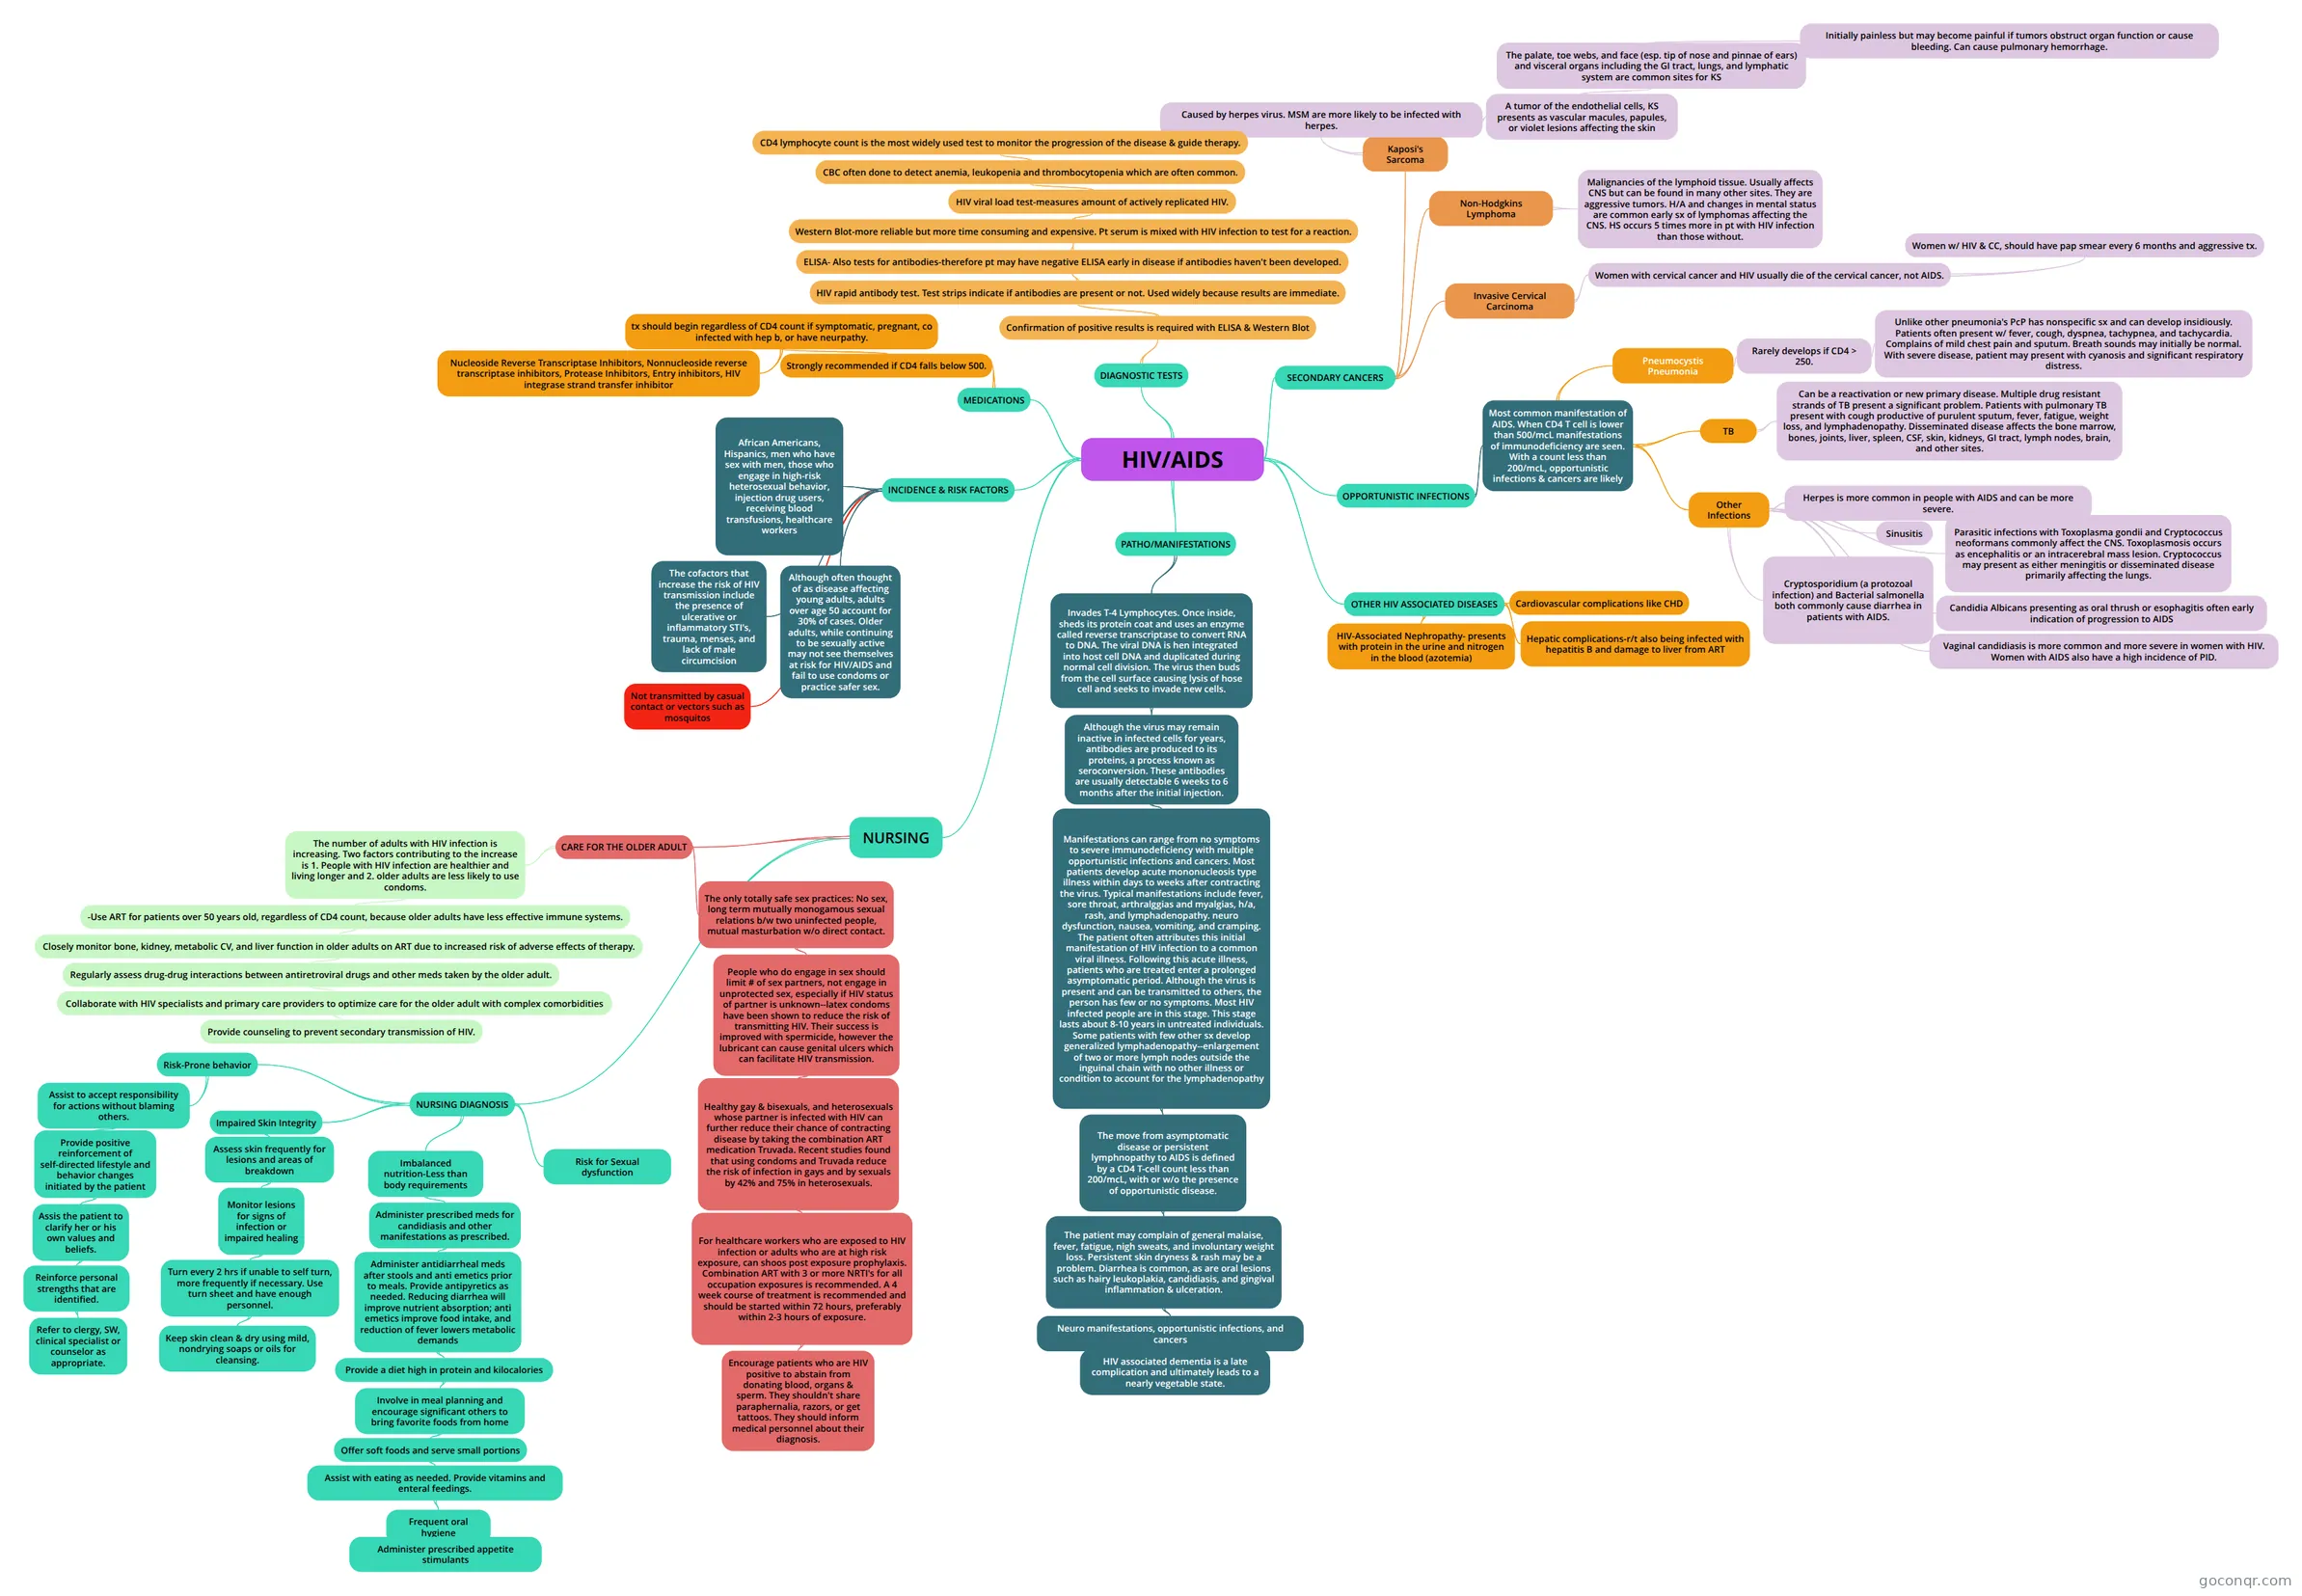
Mind map: HIV/AIDS
Map content
HIV/AIDS
INCIDENCE & RISK FACTORS
- African Americans, Hispanics, men who have sex with men, those who engage in high-risk heterosexual behavior, injection drug users, receiving blood transfusions, healthcare workers
- Although often thought of as disease affecting young adults, adults over age 50 account for 30% of cases. Older adults, while continuing to be sexually active may not see themselves at risk for HIV/AIDS and fail to use condoms or practice safer sex.
- The cofactors that increase the risk of HIV transmission include the presence of ulcerative or inflammatory STI's, trauma, menses, and lack of male circumcision
- Not transmitted by casual contact or vectors such as mosquitos
OPPORTUNISTIC INFECTIONS
- Most common manifestation of AIDS. When CD4 T cell is lower than 500/mcL manifestations of immunodeficiency are seen. With a count less than 200/mcL, opportunistic infections & cancers are likely
- Pneumocystis Pneumonia
- Rarely develops if CD4 > 250.
- Unlike other pneumonia's PcP has nonspecific sx and can develop insidiously. Patients often present w/ fever, cough, dyspnea, tachypnea, and tachycardia. Complains of mild chest pain and sputum. Breath sounds may initially be normal. With severe disease, patient may present with cyanosis and significant respiratory distress.
- Rarely develops if CD4 > 250.
- TB
- Can be a reactivation or new primary disease. Multiple drug resistant strands of TB present a significant problem. Patients with pulmonary TB present with cough productive of purulent sputum, fever, fatigue, weight loss, and lymphadenopathy. Disseminated disease affects the bone marrow, bones, joints, liver, spleen, CSF, skin, kidneys, GI tract, lymph nodes, brain, and other sites.
- Other Infections
- Herpes is more common in people with AIDS and can be more severe.
- Cryptosporidium (a protozoal infection) and Bacterial salmonella both commonly cause diarrhea in patients with AIDS.
- Sinusitis
- Parasitic infections with Toxoplasma gondii and Cryptococcus neoformans commonly affect the CNS. Toxoplasmosis occurs as encephalitis or an intracerebral mass lesion. Cryptococcus may present as either meningitis or disseminated disease primarily affecting the lungs.
- Candidia Albicans presenting as oral thrush or esophagitis often early indication of progression to AIDS
- Vaginal candidiasis is more common and more severe in women with HIV. Women with AIDS also have a high incidence of PID.
- Pneumocystis Pneumonia
- Most common manifestation of AIDS. When CD4 T cell is lower than 500/mcL manifestations of immunodeficiency are seen. With a count less than 200/mcL, opportunistic infections & cancers are likely
SECONDARY CANCERS
- Kaposi's Sarcoma
- Caused by herpes virus. MSM are more likely to be infected with herpes.
- A tumor of the endothelial cells, KS presents as vascular macules, papules, or violet lesions affecting the skin
- The palate, toe webs, and face (esp. tip of nose and pinnae of ears) and visceral organs including the GI tract, lungs, and lymphatic system are common sites for KS
- Initially painless but may become painful if tumors obstruct organ function or cause bleeding. Can cause pulmonary hemorrhage.
- The palate, toe webs, and face (esp. tip of nose and pinnae of ears) and visceral organs including the GI tract, lungs, and lymphatic system are common sites for KS
- A tumor of the endothelial cells, KS presents as vascular macules, papules, or violet lesions affecting the skin
- Caused by herpes virus. MSM are more likely to be infected with herpes.
- Non-Hodgkins Lymphoma
- Malignancies of the lymphoid tissue. Usually affects CNS but can be found in many other sites. They are aggressive tumors. H/A and changes in mental status are common early sx of lymphomas affecting the CNS. HS occurs 5 times more in pt with HIV infection than those without.
- Invasive Cervical Carcinoma
- Women with cervical cancer and HIV usually die of the cervical cancer, not AIDS.
- Women w/ HIV & CC, should have pap smear every 6 months and aggressive tx.
- Women with cervical cancer and HIV usually die of the cervical cancer, not AIDS.
- Kaposi's Sarcoma
MEDICATIONS
- Strongly recommended if CD4 falls below 500.
- tx should begin regardless of CD4 count if symptomatic, pregnant, co infected with hep b, or have neurpathy.
- Nucleoside Reverse Transcriptase Inhibitors, Nonnucleoside reverse transcriptase inhibitors, Protease Inhibitors, Entry inhibitors, HIV integrase strand transfer inhibitor
- tx should begin regardless of CD4 count if symptomatic, pregnant, co infected with hep b, or have neurpathy.
- Strongly recommended if CD4 falls below 500.
OTHER HIV ASSOCIATED DISEASES
- HIV-Associated Nephropathy- presents with protein in the urine and nitrogen in the blood (azotemia)
- Cardiovascular complications like CHD
- Hepatic complications-r/t also being infected with hepatitis B and damage to liver from ART
DIAGNOSTIC TESTS
- Confirmation of positive results is required with ELISA & Western Blot
- HIV rapid antibody test. Test strips indicate if antibodies are present or not. Used widely because results are immediate.
- ELISA- Also tests for antibodies-therefore pt may have negative ELISA early in disease if antibodies haven't been developed.
- Western Blot-more reliable but more time consuming and expensive. Pt serum is mixed with HIV infection to test for a reaction.
- HIV viral load test-measures amount of actively replicated HIV.
- CBC often done to detect anemia, leukopenia and thrombocytopenia which are often common.
- CD4 lymphocyte count is the most widely used test to monitor the progression of the disease & guide therapy.
- CBC often done to detect anemia, leukopenia and thrombocytopenia which are often common.
- HIV viral load test-measures amount of actively replicated HIV.
- Western Blot-more reliable but more time consuming and expensive. Pt serum is mixed with HIV infection to test for a reaction.
- ELISA- Also tests for antibodies-therefore pt may have negative ELISA early in disease if antibodies haven't been developed.
- HIV rapid antibody test. Test strips indicate if antibodies are present or not. Used widely because results are immediate.
- Confirmation of positive results is required with ELISA & Western Blot
NURSING
- CARE FOR THE OLDER ADULT
- The number of adults with HIV infection is increasing. Two factors contributing to the increase is 1. People with HIV infection are healthier and living longer and 2. older adults are less likely to use condoms.
- -Use ART for patients over 50 years old, regardless of CD4 count, because older adults have less effective immune systems.
- Closely monitor bone, kidney, metabolic CV, and liver function in older adults on ART due to increased risk of adverse effects of therapy.
- Regularly assess drug-drug interactions between antiretroviral drugs and other meds taken by the older adult.
- Collaborate with HIV specialists and primary care providers to optimize care for the older adult with complex comorbidities
- Provide counseling to prevent secondary transmission of HIV.
- Collaborate with HIV specialists and primary care providers to optimize care for the older adult with complex comorbidities
- Regularly assess drug-drug interactions between antiretroviral drugs and other meds taken by the older adult.
- Closely monitor bone, kidney, metabolic CV, and liver function in older adults on ART due to increased risk of adverse effects of therapy.
- -Use ART for patients over 50 years old, regardless of CD4 count, because older adults have less effective immune systems.
- The only totally safe sex practices: No sex, long term mutually monogamous sexual relations b/w two uninfected people, mutual masturbation w/o direct contact.
- People who do engage in sex should limit # of sex partners, not engage in unprotected sex, especially if HIV status of partner is unknown--latex condoms have been shown to reduce the risk of transmitting HIV. Their success is improved with spermicide, however the lubricant can cause genital ulcers which can facilitate HIV transmission.
- Healthy gay & bisexuals, and heterosexuals whose partner is infected with HIV can further reduce their chance of contracting disease by taking the combination ART medication Truvada. Recent studies found that using condoms and Truvada reduce the risk of infection in gays and by sexuals by 42% and 75% in heterosexuals.
- For healthcare workers who are exposed to HIV infection or adults who are at high risk exposure, can shoos post exposure prophylaxis. Combination ART with 3 or more NRTI's for all occupation exposures is recommended. A 4 week course of treatment is recommended and should be started within 72 hours, preferably within 2-3 hours of exposure.
- Encourage patients who are HIV positive to abstain from donating blood, organs & sperm. They shouldn't share paraphernalia, razors, or get tattoos. They should inform medical personnel about their diagnosis.
- For healthcare workers who are exposed to HIV infection or adults who are at high risk exposure, can shoos post exposure prophylaxis. Combination ART with 3 or more NRTI's for all occupation exposures is recommended. A 4 week course of treatment is recommended and should be started within 72 hours, preferably within 2-3 hours of exposure.
- Healthy gay & bisexuals, and heterosexuals whose partner is infected with HIV can further reduce their chance of contracting disease by taking the combination ART medication Truvada. Recent studies found that using condoms and Truvada reduce the risk of infection in gays and by sexuals by 42% and 75% in heterosexuals.
- People who do engage in sex should limit # of sex partners, not engage in unprotected sex, especially if HIV status of partner is unknown--latex condoms have been shown to reduce the risk of transmitting HIV. Their success is improved with spermicide, however the lubricant can cause genital ulcers which can facilitate HIV transmission.
- The number of adults with HIV infection is increasing. Two factors contributing to the increase is 1. People with HIV infection are healthier and living longer and 2. older adults are less likely to use condoms.
- NURSING DIAGNOSIS
- Risk-Prone behavior
- Assist to accept responsibility for actions without blaming others.
- Provide positive reinforcement of self-directed lifestyle and behavior changes initiated by the patient
- Assis the patient to clarify her or his own values and beliefs.
- Reinforce personal strengths that are identified.
- Refer to clergy, SW, clinical specialist or counselor as appropriate.
- Reinforce personal strengths that are identified.
- Assis the patient to clarify her or his own values and beliefs.
- Provide positive reinforcement of self-directed lifestyle and behavior changes initiated by the patient
- Assist to accept responsibility for actions without blaming others.
- Impaired Skin Integrity
- Assess skin frequently for lesions and areas of breakdown
- Monitor lesions for signs of infection or impaired healing
- Turn every 2 hrs if unable to self turn, more frequently if necessary. Use turn sheet and have enough personnel.
- Keep skin clean & dry using mild, nondrying soaps or oils for cleansing.
- Turn every 2 hrs if unable to self turn, more frequently if necessary. Use turn sheet and have enough personnel.
- Monitor lesions for signs of infection or impaired healing
- Assess skin frequently for lesions and areas of breakdown
- Imbalanced nutrition-Less than body requirements
- Administer prescribed meds for candidiasis and other manifestations as prescribed.
- Administer antidiarrheal meds after stools and anti emetics prior to meals. Provide antipyretics as needed. Reducing diarrhea will improve nutrient absorption; anti emetics improve food intake, and reduction of fever lowers metabolic demands
- Provide a diet high in protein and kilocalories
- Involve in meal planning and encourage significant others to bring favorite foods from home
- Offer soft foods and serve small portions
- Assist with eating as needed. Provide vitamins and enteral feedings.
- Frequent oral hygiene
- Administer prescribed appetite stimulants
- Frequent oral hygiene
- Assist with eating as needed. Provide vitamins and enteral feedings.
- Offer soft foods and serve small portions
- Involve in meal planning and encourage significant others to bring favorite foods from home
- Provide a diet high in protein and kilocalories
- Administer antidiarrheal meds after stools and anti emetics prior to meals. Provide antipyretics as needed. Reducing diarrhea will improve nutrient absorption; anti emetics improve food intake, and reduction of fever lowers metabolic demands
- Administer prescribed meds for candidiasis and other manifestations as prescribed.
- Risk for Sexual dysfunction
- Risk-Prone behavior
- CARE FOR THE OLDER ADULT
PATHO/MANIFESTATIONS
- Invades T-4 Lymphocytes. Once inside, sheds its protein coat and uses an enzyme called reverse transcriptase to convert RNA to DNA. The viral DNA is hen integrated into host cell DNA and duplicated during normal cell division. The virus then buds from the cell surface causing lysis of hose cell and seeks to invade new cells.
- Although the virus may remain inactive in infected cells for years, antibodies are produced to its proteins, a process known as seroconversion. These antibodies are usually detectable 6 weeks to 6 months after the initial injection.
- Manifestations can range from no symptoms to severe immunodeficiency with multiple opportunistic infections and cancers. Most patients develop acute mononucleosis type illness within days to weeks after contracting the virus. Typical manifestations include fever, sore throat, arthralggias and myalgias, h/a, rash, and lymphadenopathy. neuro dysfunction, nausea, vomiting, and cramping. The patient often attributes this initial manifestation of HIV infection to a common viral illness. Following this acute illness, patients who are treated enter a prolonged asymptomatic period. Although the virus is present and can be transmitted to others, the person has few or no symptoms. Most HIV infected people are in this stage. This stage lasts about 8-10 years in untreated individuals. Some patients with few other sx develop generalized lymphadenopathy--enlargement of two or more lymph nodes outside the inguinal chain with no other illness or condition to account for the lymphadenopathy
- The move from asymptomatic disease or persistent lymphnopathy to AIDS is defined by a CD4 T-cell count less than 200/mcL, with or w/o the presence of opportunistic disease.
- The patient may complain of general malaise, fever, fatigue, nigh sweats, and involuntary weight loss. Persistent skin dryness & rash may be a problem. Diarrhea is common, as are oral lesions such as hairy leukoplakia, candidiasis, and gingival inflammation & ulceration.
- Neuro manifestations, opportunistic infections, and cancers
- HIV associated dementia is a late complication and ultimately leads to a nearly vegetable state.
- Neuro manifestations, opportunistic infections, and cancers
- The patient may complain of general malaise, fever, fatigue, nigh sweats, and involuntary weight loss. Persistent skin dryness & rash may be a problem. Diarrhea is common, as are oral lesions such as hairy leukoplakia, candidiasis, and gingival inflammation & ulceration.
- The move from asymptomatic disease or persistent lymphnopathy to AIDS is defined by a CD4 T-cell count less than 200/mcL, with or w/o the presence of opportunistic disease.
- Manifestations can range from no symptoms to severe immunodeficiency with multiple opportunistic infections and cancers. Most patients develop acute mononucleosis type illness within days to weeks after contracting the virus. Typical manifestations include fever, sore throat, arthralggias and myalgias, h/a, rash, and lymphadenopathy. neuro dysfunction, nausea, vomiting, and cramping. The patient often attributes this initial manifestation of HIV infection to a common viral illness. Following this acute illness, patients who are treated enter a prolonged asymptomatic period. Although the virus is present and can be transmitted to others, the person has few or no symptoms. Most HIV infected people are in this stage. This stage lasts about 8-10 years in untreated individuals. Some patients with few other sx develop generalized lymphadenopathy--enlargement of two or more lymph nodes outside the inguinal chain with no other illness or condition to account for the lymphadenopathy
- Although the virus may remain inactive in infected cells for years, antibodies are produced to its proteins, a process known as seroconversion. These antibodies are usually detectable 6 weeks to 6 months after the initial injection.
- Invades T-4 Lymphocytes. Once inside, sheds its protein coat and uses an enzyme called reverse transcriptase to convert RNA to DNA. The viral DNA is hen integrated into host cell DNA and duplicated during normal cell division. The virus then buds from the cell surface causing lysis of hose cell and seeks to invade new cells.
Information
- Description
- Mind Map on HIV/AIDS, created by Misty Ballard on 18/03/2016.
- Created by
- Misty Ballard
- Views
- 3
- Rating