
Mapa mental
Liver Function & Fed/Fasted Metabolism
Conteúdo do mapa
Liver Function & Fed/Fasted Metabolism
METABOLISM FED/FASTED
- GLUCONEOGENESIS (GNG)
- GNG is almost the reverse of GLYCOLYSIS but uses enzymes (in blue) needed due to large free energy change
- NB. Enzymes are differentially regulated to prevent futile cycling
- GNG consumes ATP and GTP - is energetically expensive but NEEDED
- WHY? Brain has no reserves so we ALWAYS need a glucose supply. Glycogen reserves in liver aren't enough. SO we synthesise glucose from pyruvate, glycerol & AAs = GNG IN LIVER. Needed in STARVATION or VIGOROUS EXERCISE.
- Animals can't produce glucose from fatty acids but plants can (why seeds are full of fat)
- Any compound that can form PYRUVATE/OXALOACETATE can initiate GNG
- The path from PYRUVATE to PHOSPHOENOLPYRUVATE (PEP) is via OXALOACETATE, an intermediate of the citric acid cycle
- TRAVERSES MITOCHONDRIA. Inner mitochon membrane permeable to malate, PEP & pyruvate.
- OVERALL: 2xPyruvate + 4xATP + 2xGTP + 2xNADH + 2xH+ + 4xH2O = 1xGlucose + 4xADP + 2xGDP + 2xNAD+ + 6xPi
- OVERALL GNG COSTS (per glucose): 4xATP, 2xNADH 2xGTP
- OVERALL: 2xPyruvate + 4xATP + 2xGTP + 2xNADH + 2xH+ + 4xH2O = 1xGlucose + 4xADP + 2xGDP + 2xNAD+ + 6xPi
- GNG is almost the reverse of GLYCOLYSIS but uses enzymes (in blue) needed due to large free energy change
- REGULATION OF FED <> FASTED STATES
- Proteins
- How alter rates of biochemical reactions? See diagram below right
- Half-life of proteins varies between tissues eg. muscle is 10days!
- How alter rates of biochemical reactions? See diagram below right
- Substrate Conc
- Feedback Inhibition
- Often, products of a metabolic pathway, directly/indirectly reduce rate
- eg. glycolysis: HEXOKINASE inhibited by GLUCOSE-6-PHOSPHATE. PHOSPHOFRUCTOKINASE inhibited by ATP.
- Often, products of a metabolic pathway, directly/indirectly reduce rate
- Many enzymes have a Km that is near/greater than the conc of their substrate.
- Feedback Inhibition
- ATP and AMP
- AMP = Adenosine MONOphosphate
- ATP > Pi + ADP
- 2xADP >(adenylate kinase)> AMP + ATP
- Presence of AMP indicates usage of ATP
- 2xADP >(adenylate kinase)> AMP + ATP
- ATP > Pi + ADP
- Both act on individual enzymes and whole organism via AMP-activated Protein Kinase (AMPK)
- eg. GNG and Glycolysis - ADP & ATP ALLOSTERICALLY regulate PFK & FBPase (feedback control). PFK also activated by insulin, inhibited by glucagon.
- 1) AMP activates AMPK (via leptin & adiponectin in adipose tissue, and SNS)
- 2) AMPK regulates metabolic proteins by phosphorylating them (Opt. 9)
- AMPK shifts metabolism away from energy-consuming synthetic pathways > ACTS TO RAISE [ATP]
- Extrahepatic tissues: stimulates use of fatty acids for fuel
- Liver: stimulates GNG, slows synthetic pathways
- Brain: stimulates feeding for fuel
- AMPK shifts metabolism away from energy-consuming synthetic pathways > ACTS TO RAISE [ATP]
- 2) AMPK regulates metabolic proteins by phosphorylating them (Opt. 9)
- AMP = Adenosine MONOphosphate
- Acetyl CoA > Fate of Pyruvate
- Proteins
- FATTY ACIDS
- 1/3 of our energy needs comes from dietary triacylglycerols (TAGs)
- Fats most energy efficient for storage: highly reduced & bind little H2O
- eg. hibernating bears
- Oxidation provides energy for HEART, LIVER, KIDNEYS & RESTING MUSCLE
- 1) Absorbed in S. INTESTINE. 2) Bile > mixed micelles. 3) Lipase breaks fatty acids > TAGs. 4) TAGs + cholesterol + apolipoproteins > chylomicrons. 5) Travel via lymphatic system/blood > tissues (myocyte or adipocyte)
- 6) Lipoprotein lipase converts TAGs back to fatty acids and glycerol
- 7) fatty acids OXIDISED as fuel
- OXIDATION...
- Transported into mitochondria via carnitine shuttle
- Stage 1) β oxidation: fatty acids are oxidised 2 carbons at a time and combine with CoA to form ACETYL-CoA, and high energy e's in the form of NADH and FADH2.
- Stage 2) ACETYL-CoA enters citric acid cycle (ie. Step 3 of resp) > NADH and FADH2.
- Stage 3) the high energy e's in NADH and FADH2 synthesise ATP in oxidative phosphorylation (electron transport chain! ie. Step 4 of resp)
- Fatty acids > acetyl-CoA - explains KETOGENESIS...
- When ACETYL-CoA from fatty acids (and some AAs) are in excess > converted into ketone bodies in LIVER MITOCHONDRIA > EXPORTED to tissues
- (reserves oxaloacetate for GNG)
- NB. GNG requires oxaloacetate. This TAKES PREFERENCE over acetyl-CoA's entry into citric acid cycle (by ketones)
- 3 types of ketone bodies:
- Acetone - exhaled
- Acetoacetate & β-hydroxybutyrate - FUEL for extrahepatic tissues by conversion back to ACETYL-CoA (>entry into citric acid cycle)
- (Heart prefers acetoacetate to glucose)
- Acetoacetate detected on urine dipstick
- REMEMBER THIS: "Ketone bodies are a form of mobile acetyl-CoA (which can enter Citric Acid Cycle)"
- (reserves oxaloacetate for GNG)
- When ACETYL-CoA from fatty acids (and some AAs) are in excess > converted into ketone bodies in LIVER MITOCHONDRIA > EXPORTED to tissues
- This Acetyl Co-A can EITHER: enter CITRIC ACID CYCLE (Resp continues as normal) OR (when in excess) is converted into KETONE BODIES in liver (reserves oxaloacetate for GNG)
- Stage 2) ACETYL-CoA enters citric acid cycle (ie. Step 3 of resp) > NADH and FADH2.
- Stage 1) β oxidation: fatty acids are oxidised 2 carbons at a time and combine with CoA to form ACETYL-CoA, and high energy e's in the form of NADH and FADH2.
- Transported into mitochondria via carnitine shuttle
- OXIDATION...
- 7) or reesterified for storage
- 7) fatty acids OXIDISED as fuel
- 6) Lipoprotein lipase converts TAGs back to fatty acids and glycerol
- FED/FASTED OVERVIEW
- When FASTING: Liver is PRINCIPAL SOURCE of GLUCOSE for BRAIN
- When FED:
- ARROWS:
- GLUCOSE
- AMINO ACIDS
- LIPIDS
- UREA
- KETONE BODIES
- UREA
- LIPIDS
- AMINO ACIDS
- GLUCOSE
- ARROWS:
- When PROLONGED FASTING / DM Type II:
- OXALOACETATE preferentially used for GNG to maintain BLOOD GLUCOSE. This slows the citric acid cycle in liver, so enhances formation of KETONE BODIES, releasing CoA for β oxidation to continue. Ketone bodies used as fuel for extrahepatic tissues.
- VITAMINS & MINERALS
- Vitamins = organic molecules that cannot be synthesised > dietary. Categorised according to solubility in fat (or H2O if Vit B/C). Act as COENZYMES or ANTIOXIDANTS.
- Vitamins A, B (complexes), C, D, E, K
- *See lecture slides for function of each
- Vitamins A, B (complexes), C, D, E, K
- Minerals = Excreted in urine/sweat so have to be replaced.
- Ca, Na, K, Mg
- Trace Elements eg. Fe, Zn, Cu
- Vitamins = organic molecules that cannot be synthesised > dietary. Categorised according to solubility in fat (or H2O if Vit B/C). Act as COENZYMES or ANTIOXIDANTS.
- TISSUE PROFILES
- BRAIN = no fuel reserve. GLUCOSE is the only fuel, apart from KETONES in prolonged starvation. Consumes 120g glucose/day (60% of entire body at rest). Glucose below ~2mM > hypoglycaemic coma > death.
- MUSCLE = uses GLUCOSE, FATTY ACIDS, KETONE BODIES. When contracting, glycolysis exceeds citric acid cycle so pyruvate > lactate (back to glucose by liver). When resting, FATTY ACIDS are used (meets 85% of energy needs)
- HEART = almost all AEROBICALLY. No glycogen reserves. Uses mainly FATTY ACIDS, or KETONE BODIES or LACTATE [or ACETOACETATE (ketone body produced by liver) over glucose].
- LIVER = FATTY ACIDS. Fatty acid synthesis. Removes 2/3s of glucose from blood and monosaccharides. FED state: glucose 6-phosphate > acetyl CoA > fatty acids, cholesterol, bile salts. FASTING state: fatty acids > acetyl CoA > ketone bodies.
- GLYCOGEN SYNTHESIS / GLYCOGENOLYSIS
- Glucose<>Glycogen. Glycogen rapidly synthesised/degraded according to need.
- GLYCOGEN SYNTHASE (LIVER) activated by GLUCOSE & GLUCOSE 6-PHOSPHATE
- GLYCOGEN PHOSPHORYLASE (MUSCLE) activated by AMP and Ca2+. (Converts glycogen into glucose 1-phosphate)
- Both enzymes controlled by INSULIN, GLUCAGON, ADRENALIN.
- GLYCOGEN SYNTHASE (LIVER) activated by GLUCOSE & GLUCOSE 6-PHOSPHATE
- Glucose<>Glycogen. Glycogen rapidly synthesised/degraded according to need.
- GLUCONEOGENESIS (GNG)
BILIARY CIRCULATION
- Bilirubin metabolism PROBLEMS
- If too much bilirubin before liver = ^unconjugated bilirubin = PREHEPATIC JAUNDICE eg. haemolytic anaemia, spherocytosis of RBCs, haemolysis
- High bilirubin = JAUNDICE. Bilirubin is UV mobile (broken up/dispersed when exposed to UV). SEVERE jaundice = yellow sclera. MILD jaundice/ANAEMIA = white where UV shines on eye (bilirubin broken up) BUT yellow under eyelids
- GILBERT'S SYNDROME = ^isolated bilirubin (stressful triggers eg. dehydration) Can be normal and go down.
- High bilirubin = JAUNDICE. Bilirubin is UV mobile (broken up/dispersed when exposed to UV). SEVERE jaundice = yellow sclera. MILD jaundice/ANAEMIA = white where UV shines on eye (bilirubin broken up) BUT yellow under eyelids
- Also POST-HEPATIC conjugated bilirubin stopped from getting from liver to gut eg. by GALL STONES.
- Excess conjugated bilirubin in liver No urobilinogen in faeces = fats not emulsified > PALE/FLOATING STOOL Bilirubin goes into kidneys instead > DARK URINE
- Blood tests
- LIVER PROFILE: bilirubin ALT ALP albumin
- Bilirubin conjugated or not? Work out location of problem
- Liver isoenzyme of alkaline phosphatase found in biliary ducts. RAISED ALP in lover suggests cholestasis (blockage of biliary system)
- NB. RAISED ALP also in BONE DISEASE and PREGNANCY (produced by placenta)
- LIVER PROFILE: bilirubin ALT ALP albumin
- If too much bilirubin before liver = ^unconjugated bilirubin = PREHEPATIC JAUNDICE eg. haemolytic anaemia, spherocytosis of RBCs, haemolysis
- BILE SALTS are synthesised from cholesterol. Emulsify lipids before intestinal absorption. Made in liver and stored in gall bladder.
- Cholesterol > Bile acids > Cholic acid
- ENTEROHEPATIC CIRCULATION
- Bile salts recirculated several times per day - EITHER reabsorbed as UROBILINOGEN or lost as STERCOBILIN
- Also elimination of drugs
- DETOXIFICATION
- Bilirubin metabolism PROBLEMS
SYNTHETIC FUNCTION (albumin, clotting factors, α and β globulins)
- ALBUMEN
- Makes up 50% of plasma proteins (ref range 35-45g/L). Main factor in ONCOTIC PRESSURE.
- Carrier protein for CALCIUM and BILIRUBIN (ie. can calculate corrected Ca2+ level)
- Causes of HYPOalbuminaemia: liver disease, nephrotic syndrome, malnutrition, burns
- Low albumin increases osmotic pressure of ECF > PERIPHERAL OEDEMA
- CLOTTING FACTORS (ABC case Yr 2)
- synthesised in liver (look at ALT or AST for clotting ability when giving transplant)
- Cholestasis: malabsorption of Vit K
- Low platelets - Impaired thrombopoietin synthesis (makes platelets)
- ALBUMEN
METABOLISM (Carbohydrates, proteins, lipids)
- Lipids
- (see Chest Pain case Yr2) - affects cholesterol & triglyceride lipid levels
- Proteins
- Transamination (break down proteins into AA's to produce energy) *SEE N2 lecture in Urinary
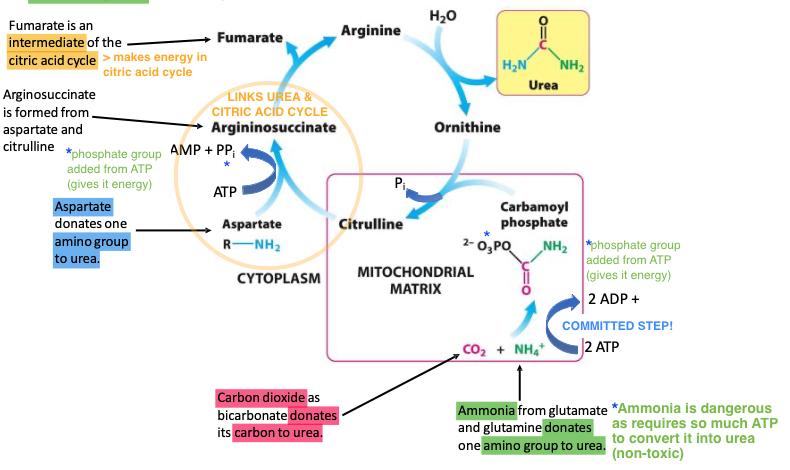
- Urea cycle
- Liver damage = problems with urea cycle > HYPERAMMONAEMIA > brain problems (ENCEPHALOPATHIC)
- from GENETIC DISEASES that affect enzymes (baby will have ^NH3 - need low protein diet and no fasting as will start digesting own muscles for protein)
- from ALCOHOLIC liver damage
- Liver damage = problems with urea cycle > HYPERAMMONAEMIA > brain problems (ENCEPHALOPATHIC)
- AMINOTRANSFERASES should be IN HEPATOCYTES so sign of liver damage if in bloodstream
- Clinically, we use ALT (Alanine transferase) which is SENSITIVE and SPECIFIC to liver (>50 = hepatocellular damage)
- Perviously used AST (Aspartate transaminase) but also produced with heart damage. Troponin now marker for heart damage.
- Clinically, we use ALT (Alanine transferase) which is SENSITIVE and SPECIFIC to liver (>50 = hepatocellular damage)
- Urea cycle
- Transamination (break down proteins into AA's to produce energy) *SEE N2 lecture in Urinary
- Carbohydrates
- altruistic organ - RELEASES GLUCOSE into blood for rest of body (unlike skeletal muscle which makes own glucose)
- Relationship between LIVER & PANCREAS
- Glucose level when fasting = 4mmol. If continue to fast - glucose level kept constant by breaking down glycogen or muscles
- See RHS of mind map
- GLUCONEOGENESIS
- GLYCOGEN STORAGE
- altruistic organ - RELEASES GLUCOSE into blood for rest of body (unlike skeletal muscle which makes own glucose)
- Lipids
STRUCTURE
- Hepatic portal system
- build up of blood > block > chronic liver disease
- Microanatomy
- Hepatic portal system
LIVER DISEASE SUMMARY
Imagens e arquivos do mapa


Informações
- Descrição
- Year 1 - CBL Weeks 11-20 (GI) Mapa Mental sobre Liver Function & Fed/Fasted Metabolism, criado por Ella Breese em 06-03-2020.
- Criado por
- Ella Breese
- Visualizações
- 5
- Avaliação