
Karteikarten
Pulmonology - Diseases
Karten in diesem Stapel (173)
- 1Classic Community Acquired Pneumonia CharacteristicsAcquired in the home or non-hospital environment
Most cases, causative agent not identified, but usually bacterial
Causative agents include: Streptococcus pneumoniae, Haemophilus influenzae, Moraxella catarrhalis, Staphylococcus aureus, Kelbsiella pneumoniae, other gram negative bacilli.
Viral causes: influenza, RSV, adenovirus, parainfluenza - 2Community Acquired Pneumonia (CAP) Clinical FeaturesTypical presentation is 1-10 day history of Increaseing cough, prurulent sputum, SOB, tachycardia, pleuritic chest pain, fever or hypothermia.
Physical exam may reveal altered breath sounds and crackles,dullness to percussion if an effusion present, and bronchial breath sounds over an area of consolidation.
The chest exam alone is not enough to confirm or exclude the diagnosis. - 3Community Acquired Pneumonia (CAP) Laboratory FindingsOrganisms may be detected with conventional stain or sputum culture, although typically not done before starting treatment. The most common bacterial pathogen found ins Streptococcus pneumoniae.
CXR shows lobar or segmental infiltrates, air bronchograms and pleural effusions. THere is no pathognomonic radiograph presentation. - 4Community Acquired Pneumonia (CAP) Treatment for otherwise healthy patientPatient is otherwise healthy and free of respiratory distress or complications.
May be treated as an outpatient with oral antibiotics and appropriate supportive care.
Doxycycline, erythromycin, Macrolides (clarithromycin, azithromycin), or fluoroquinalines. - 5Community Acquired Pneumonia (CAP) Treatment for more severe or complicationsNeutropenia, involvement of more than one lobe, or poor host resistance indicates need for hospitalization.
Consider hospitalization for patients older than 50 with Comorbidities, altered mental status, or hemodynamic instability.
If inpatient treatment necessary consider coverage for Streptococcus pneumoniae and Legionella sp. with ceftriaxone or ceftaxime plus azithromycin or a fluoroquinalone. - 6Community Acquired Pneumonia (CAP) VaccinesThe polyvalent pneumococcal vaccine (Peumovax) contains antigens of 23 common strains. Efficacy ranges from 51-86%.
Pneumococcal conjugate vaccine (PCV) s recommended in children 6 weeks to 15 months.
The pneumococcal polysaccharide vaccine (PPV is recommended for children 2-5 not previously immunized and adults 65 or older or any person with chronic illness that increases risk of CAP. Booster shots needed every 6 years. - 7Mycoplasma pneumonia SymptomsLow-grade fever
Cough
Bullous my ringgits
Cold agglutinins - 8Pneumocystis jerovici SymptomsSlower onset, immunosuppression
Increased lactate dehydrogenase
More hypoxemic than appears on chest radiography
Interstitial infiltrates - 9Legionella pneumoniae SymptomsChronic cardiac or respiratory disease
Hyponatremia
Diarrhea, other systemic symptoms - 10Chlamydia pneumoniae SymptomsLonger pro drone
Sore throat, hoarseness - 11Streptococcus pneumoniae SymptomsSingle rigor
Rust-colored sputum - 12Klebsiella pneumoniae SymptomsCurrant jelly sputum
Chronic illness, including alcohol abuse - 13Kelbsiella pneumoniae Patient GroupAlcohol abuse
- 14Haemophilus pneumoniae Patient groupCOPD
- 15Pseudomonas Patient CroupCystic Fibrosis
- 16Mycoplasma pneumoniae Chlamydia pneumoniae Patient groupYoung adults
College settings - 17Legionella pneumoniae Patient groupAir conditioning/aerosolized water
- 18Encapsulated organisms Streptococcus pneumoniae Haemophilus pneumoniae Patient groupPostsplenectomy
- 19Fungus Patient groupLeukemia, lymphoma
- 20RSV Patient groupChildren, <1 year
- 21Parainfluenza Patient groupChildren, <2 years
- 22Atypical CAP General characteristicsMycoplasma pneumonia is the most common atypical. Other causes include viruses (influenza A and B and adenovirus), Chlamydia pneumoniae, Legionella sp. and Moraxella sp.
- 23Atypical CAP Clinical FeaturesPresents as a low-grade fever with relatively mild pulmonary symptoms which are self limited, occuring in young, otherwise healthy adults. A non productive cough, myalgia, and fatigue are common.
Legionella infection associated with exposure to contaminated water droplets from cooling and ventilation symptoms. Acute development of high fever, dry cough, Dyspnea, and systemic symptoms is common.
Viral pneumonias are variable in presentation but are often associated with epidemics and upper resp. symptoms. - 24Atypical CAP Laboratory findingsOrganisms are usually not detected with conventional stain or culture of sputum.
The WBC count is normal or only slightly elevated.
Radiography shows segmental unilateral lower lung zone infiltrates or diffuse infiltrates. - 25Atypical CAP TreatmentAntibiotic treatment is started empirically based on the clinical features. Regimens include erythromycin (for suspected mycoplasma and legionella) and tetracycline (for suspected chlamydia)
Viral pneumonias are treated with supportive measures unless influenza is suspected. Neuraminidase inhibitors (inhaled zanamivir or oral oselamivir) may be used. - 26Nosocomial pneumonia General characteristicsHospital acquired pneumonia is caused by organisms that colonize ill patients, staff, equipment, producing clinical infection more than 48 hours after admission to the hospital. THose at highest risk are in ICU or mechanical ventilation.
Pneumonia is second most cause of hospital acquired infection.
The causative organisms are unique and mortality is 20-50%. The usual organisms are Stphylococcus aureus and gram negative bacilli, which are easy to recover from respiratory secretions. Pseudomonas aeruginosa is the most likely pathogen in the ICU an carries worst prognosis. Others are Staphylococcus aureus, Klebsiella, Escherichia coli, and Enterobacter. - 27Nosocomial pneumonia Clinical featuresSimilar to CAP
Typical presentation is 1-10 day history of Increaseing cough, prurulent sputum, SOB, tachycardia, pleuritic chest pain, fever or hypothermia.
Physical exam may reveal altered breath sounds and crackles,dullness to percussion if an effusion present, and bronchial breath sounds over an area of consolidation. - 28Nosocomial pneumonia Laboratory findingsDiagnosis is clinical and supported with gram stain and culture of sputum and blood.
CXR may help support the diagnosis. - 29Nosocomial pneumonia TreatmentIncludes use of appropriate empiric antibiotics such as cefepime, ticarcillin/calculatio acid, piper amcillin/tazobactam, meropnem. If an organism is isolated, therapy can be based on the culture results. Patients need aggressive supportive measures including ventilation as appropriate.
- 30TB General characteristicsMycobacterium tuberculosis infection is acquired by inhaling organisms within aerosol droplets expelled during coughing by people with active disease.
Most exposed people mount an immune response sufficient to prevent progression from primary infection to clinical illness. Overall, 10% if persons infected with TB will develop the disease. This is called primary TB.
Approximately 5% of exposed people fault to contain the primary infection and progress to active TB within 2 years, this is known as progressive primary RB.
Approximately 95% of infected persons will contain the bacterium without becoming symptomatic. This is known as latent TB infection. These patients are not considered to be infectious, nor can they spread the disease. Reactivation TB develops from latent TB in the setting of immune compromise.
Outbreaks since the 90's have seen an emergence of resistant organisms. - 31TB Clinical featuresCough is the most common symptom. It begins as a dry cough and progresses to a productive cough with or without hemoptysis, typically over 3 weeks or longer.
The classic symptom complex includes fever, drenching night sweats, anorexia, and weight loss. Other common classic pulmonary symptoms are cough, pleuritic chest pain, duspnea, and hemoptysis. Posttusive rales are classic.
On exam, the patient may appear chronically ill and malnourished. - 32TB Laboratory findings Primary TBHomogenous infiltrates, hilar/parathracheal lymph node enlargement, segmental Atelectasis, cavitation S with progressive disease
- 33TB Laboratory findings Reactivation TBFibroma votary apical disease, nodules, infiltrates, posterior and apical segments of the right upper lobe, apical-posterior segments of the left upper lobe, superior segments of the lower lobes.
- 34TB Laboratory findings When healedGhon complexes (Calcified primary focus) and Ranke complexes (calcified primary focus and calcified hilar lymph node) represent healed primary infection.
- 35TB Skin Test (TST)Identifies individuals who have been infected, but it does not differentiate between active and latent infection.
Tuberculin skin testing (such as the PPD) is report according to the diameter of induration, not erythema. - 36TB DiagnosisRequires the identification of Mycobacterium tuberculosis from cultures by DNA or RNA amplification techniques. Demonstration of acid fast bacilli on sputum supports, but does not confirm a diagnosis.
- 37TB Diagnosis BiopsyBiopsy revealing caseating granuloma (also known as necrotizing granulomas) is the histologic hallmark.
- 38TB TreatmentAntituburculosous drugs including isoniazid (INH), rifampin (RIF), pyrazinamide (PZA), and ethambutol (EMB), are the cornerstone of therapy.
- 39TB Treatment Side EffectsINH: hepatitis, peripheral neuropathy, coda minister with B6 to reduce risk.
RIF: hepatitis, flu syndrome, orange body fluid.
EMB: optic neuritis (red-green vision loss) - 40TB Skin Test Interpretation>=5mm: Considered + in HIV+, recent contacts of those with active TB, persons with evidence of TB on chest radiography, immunosuppressed patients on steroids.
>=10mm: Considered + in recent immigrants from countries with high rate of TBm HIV- injection drug users, myco bacteriology lab personnel, residents/employees of high risk congregate settings, persons with certain medical conditions (diabetes, silicosis, chronic renal failure, etc.), children younger than 4, infants, and children/adolescents exposed to adults at high risk.
>=15mm: Considered + in those with no risk factors for TB - 41Acute bronchitis General characteristicsMore than 90% of cases are caused by viruses including rhinovirus, corona virus, and RSV.
Bronchitis is defined as inflammation of the airways (trachea, bronchi, bronchioles) characterized by cough)
In patients with chronic lung disease, causes also include Haemophilus influenza, Streptoccocus pneuma, and Moraxella catarrhalis. - 42Acute bronchitis Clinical featuresSigns and symptoms include cough (with or without sputum), Dyspnea, fever, sore throat, headache, myalgia S, subset renal discomfort, and expiratory rhonchi or wheezes.
Bronchitis can be difficult to distinguish from pneumonia so the examination should be conducted to identify Comorbidities conditions that may influence the treatment. - 43Acute bronchitis Laboratory findingsGenerally, no laboratory evaluation is required unless there is a strong need to differentiate bronchitis from pneumonia.
The CXR will be negative in acute bronchitis. - 44Acute bronchitis TreatmentSupportive measures include hydration, expectorants, analgesics, β2-agonists, and cough suppressants.
For acute exacerbations of chronic bronchitis, in which bacterial causes are more likely, empiric first line treatement is a second generation cephalosporin; second line treatment is a second generation Macrolides or trimethoprim/sulfamethoxazole.
Antibiotics are indicated fro elderly patients, those with underlying cardiopulmonary disease and a cough for more than 7-10 days, and any patient who is immunocompromised.
For acute exacerbations in otherwise healthy adults, no empiric treatment is needed. - 45Acute bronchiolitis General characteristicsBronchiolitis refers to inflamation of the bronchioles (airways smaller than 2mm in diameter(. It is primarily an illness of young children and infants.
RSV is the most common cause, other agents include parainfluenza, adenovirus, and rhinovirus. - 46Acute bronchiolitis Clinical featuresSigns and symptoms include rhinos rhea, sneezing, wheezing, and low-grade fever
Nasal flaring, tachyons, and retractions indicate respiratory distress. - 47Acute bronchiolitis Laboratory findingsThe CBC is usually normal.
Nasal Washington for RSV culture and antigen assay often are done in infants.
CXR normal but can show air trapping and peribronchial thickening. - 48Acute bronchiolitis TreatmentIf RSV is present, consider hospitalization and administration of ribavirin. This is especially important for infant born premature or who are severely ill.
Supportive measures, such as nebulized albuterol, IV fluids, antipyretic S, chest physiotherapy, and humidified O2. - 49Bronchogenic carcinoma GeneralBronchogenic carcinoma is the leading cause of cancer deaths in men and women. There are more deaths from lung cancer than from colon, breast, and prostate combined.
The overall 5 year survival rate is 15%.
Smoking is the #1 risk factor. - 50Bronchogenic carcinoma SCLC GeneralAccounts for 25-35% of cases; it is more likely to spread early and rarely is amenable to surgery.
Mean survival is 6-18 weeks.
Tends to originate in the central bronchi and to metastasize to regional lymph nodes.
It is prone to early metastasis and an aggressive clinical course. Assume micrometasteses at presentation. - 51Bronchogenic carcinoma NSCLC GeneralGrows more slowly and is more amenable to surgery. Includes squamous cell carcinoma, adenocarcinoma, and large cell carcinoma.
- 52Bronchogenic carcinoma NSCLC - Squamous Cell Carcinoma GeneralRepresents 25-35% of cases.
Bronchiole in origin and a centrally located mass.
More likely to present with hemoptysis and there fore more likely to be diagnosed via sputum cytology. - 53Bronchogenic carcinoma NSCLC - Adenocarcinoma GeneralThe most common type of bronchogenic carcinoma, accounting for 35-40% of cases.
Typically metastatic to distant organs
This tumors arises from mucous glands, usually appears in the periphery of the lung, and is not amenable to early detection through sputum examination.
Bronchoaveolar cell carcinoma, a subtype, is a low-grade carcinoma. - 54Bronchogenic carcinoma NSCLC - Large Cell Carcinoma GeneralA heretogenous group of undifferentiated types that do not fit elsewhere.
Cytology typically shows large cells.
Doubling time is rapid.
Metastasis is early.
There may be central or peripheral masses. - 55Bronchogenic carcinoma Clinical featuresSymptoms include cough, hemoptysis pain, anorexia, weight loss, or asthenia.
Patients may also exhibit lymphadenopathy, hepatomegaly, and clubbing.
Paraneoplastic syndromes occur in 10-20% of patients with lung cancer. - 56Bronchogenic carcinoma Laboratory findingsCXR and CT scans usually demonstrate abnormalities.
Cytologic examination of sputum, if adequate cells re obtained, permits definitive diagnosis of specific cell type in many cases.
Bronchoscopy, examination of pleural fluid, and biopsy are also used to establish a diagnosis by looking at specific cell types through direct visualization.
PET scans may also aid in diagnosis and prevent unnecessary surgery. - 57Bronchogenic carcinoma Treatment NSCLCSurgery remains the treatment of choice.
The 5 year survival rate after resection is 35-40% - 58Bronchogenic carcinoma SCLCCombination chemotherapy is the treatment of choice and results in improved median survival, although patients rarely live for more than 5 years after diagnosis.
- 59Bronchogenic carcinoma Complications SVC SyndromeCompression of SVC: plethora, headache, mental status change
- 60Bronchogenic carcinoma Complications Pancoast's tumorTumor of the lung apex
Causes Horner's syndrome and shoulder pain
Affects brachial plexus and cervical sympathetic nerve - 61Bronchogenic carcinoma Complications Horner's syndromeUnilateral facial anhidrosis, ptosis, miosis
- 62Bronchogenic carcinoma Complications EndocrineCarcinoid syndrome: flushing, diarrhea, telangiectasis
- 63Bronchogenic carcinoma Paraneoplastic Syndromes Endocrine/metabolicSmall Cell: Cushing's syndrome, SIADH
Squamous cell: Hypercalcemia
Large cell: Gynecomastia - 64Bronchogenic carcinoma Paraneoplastic Syndromes NeuromuscularSmall cell: Peripheral neuropathy, myasthenia (Eaton-lambert), cerebellum degeneration
- 65Bronchogenic carcinoma Paraneoplastic Syndromes HematologicAll: Anemia, DIC, eosinophilia, thrombocytosis
- 66Bronchogenic carcinoma Paraneoplastic Syndromes CardiovascularAdenocarcinoma: thrombophlebitis
- 67Bronchogenic carcinoma Paraneoplastic Syndromes CutaneousAll: Acanosis nigricans
- 68Solitary pulmonary nodule General characteristicsPulmonary nodules are also known as coin lesions. If the lesion measures greater than 3 cm, it is referred to as a mass.
Most solitary nodules are infectious granulomas from old or active TB, fungal infection, or foreign body reaction.
Approximately 40% are malignant and represent carcinoma, hamartoma, or metastasis (bit these are usually multiple) as well as bronchial adonoma (95% are carcinoid tumors).
Malignancy is rare in patients younger than 30 years.
Smears have an increased risk of malignancy; risk increases with number of pack-years smoked. - 69Solitary pulmonary nodule Clinical featuresMost pulmonary nodules are found unexpectedly at radiography and are asymptomatic.
- 70Solitary pulmonary nodule Laboratory findingsA solitary pulmonary nodule is a round or oval, sharply circumscribed mass up to 5cm in diameter surrounded by normal lung tissue.
Central cavitation, calcification, or surrounding (satellite) lesions may occur.
A lesion that has not enlarged in more than 2 years suggests a benign cause. Most are infectious granulomas.
Malignant lesions occasionally are symptomatic, tend to occur in patients older than 45 years, usually are greater than 2cm in diameter, often have in distinct margins, exhibit rapid progression in size and rarely are calcified. - 71Solitary pulmonary nodule TreatmentLesions with a low probability of malignancy can be watched. Patients should undergo CT every 3 months for a year, if stable, frequency of CT can be reduced to every 6 months for the next 2 years.
Lesions with high probability of malignancy should be resected as soon as possible. An interim biopsy is not recommended.
Lesions with intermediate probability of malignancy should be biopsied. Use transthoracic needle biopsy or bronchoscopy if the lesion is peripheral. False-positive rates can be as high as 25%. high res CT or PET may aid in diagnosis. High res CT is best to delineate the mass and detect adenopathy Ro the presence of multiple nodules. - 72Obstructive Pulmonary Disease Asthma General CharacteristicsAsthma is characterized by three components:
Obstruction of airflow
Bronchial hyperreactivity
Inflammation of the airway
-It is a disease of chronic inflammation leading to airway narrowing and increased mucus production. - 73Obstructive Pulmonary Disease Asthma EpidemiologyAsthma effects 7% of the population.
Most common among pediatric patients
3rd leading cause of preventable hospitalization
Significant mortality (4000/yr) (on the rise)
5-15% of asthmatics are severe.
Half of $56 billion costs are spent on severe asthma. - 74Obstructive Pulmonary Disease Asthma Strongest Predisposing FactorAtopy
The atopic triad consists of wheeze, eczema and seasonal rhinitis - 75Obstructive Pulmonary Disease Asthma Common Precipitants/Triggers*Environmental triggers are the most important Precipitants of severe asthma exacerbations.
Allergens (especially dust and dust mites, dander, cockroaches, pollen)
Exercise
Upper respiratory tract infections
Post nasal drip
Gastroesophageal reflux disease
Drugs (β-blockers, ACEi, aspirin, NSAIDs,)
Stress
Cold air or weather change
Environmental irritants - 76Obstructive Pulmonary Disease Asthma Morphological ChangesBasement membrane thickening/fibrosis
Mucus gland hypertrophy and hypersecretion
Smooth muscle hypertrophy
Epithelial damage
Inflammatory cell infiltration
Edema
Vascular dilation - 77Obstructive Pulmonary Disease Asthma Clinical featuresPatients have intermittent occurrence of cough, chest tightness, shortness of breath, and wheezing (associated with coughing).
Asthma is classified according to the frequency of symptoms and PFTs. - 78Obstructive Pulmonary Disease Asthma Laboratory Findings SpirometryAirflow obstruction is indicated by DECREASED ratio of FEV1/FVC.
A greater than 10% in FEV1 after bronchodilator therapy is supportive of the diagnosis. - 79Obstructive Pulmonary Disease Asthma Laboratory Findings ABGABG (arterial blood gas) measurements may be normal in mild asthma ut in severe cases may show hypoxemia and hypercapnia with a PaO2 < 60mmHg and PaCO2 > 40mmHg. ABGs rarely used unless patient non responsive to treatment.
- 80Obstructive Pulmonary Disease Asthma Laboratory Findings CXRMay show hyperinflation.
Want to have one on file. Should be <= 5 years.
If already on file, then indicated only if pneumonia is suspected, asthma is complicated, or other disorder suspected. - 81Obstructive Pulmonary Disease Asthma Laboratory Findings FeNO (Inflammometer)Exhaled Nitric Oxide measurement.
Correlated with eosinophilia inflammation.
Levels decrease with ICS
Can predict asthma exacerbations/compliance
May correlate with decline in FEV1
FeNO 5-20 NL/controlled
FeNO 20-35 NL/elevated
FeNO > 35 Elevated - 82Obstructive Pulmonary Disease Asthma Laboratory Findings IgE, Immunocap testingSpecific allergen testing
+/- CBC with differential (looks for eosinophils in the blood)
70% of patients are allergic - 83Obstructive Pulmonary Disease Asthma Laboratory Findings Methacholine challengeBronchial provocation test
An FEV1 decrease of more than 20% is diagnostic.
Useful when spirometry is nondiagnostic - 84Obstructive Pulmonary Disease Asthma Treatment GoalsThe goals of treatment are to minimize chronic symptoms, prevent recurrent exacerbations and minimize need for urgent care visits, and maintain near-normal pulmonary function.
- 85Obstructive Pulmonary Disease Asthma Treatment Medications (Generally)Long-term Control: Corticosteroids, chromodynamics, LABA, leukotrine modifiers, theophylline.
Quick Relief: SABA, ipratropium bromide, systemic corticosteroids) - 86Obstructive Pulmonary Disease Asthma Classification of Severity IntermittentSymptoms: <= 2 days/week
Nighttime: <= 2/month
Use of Rescue Meds: < 2 days/week
FEV1 > 80% predicted
FEV1/FVC normal
No interference with daily activities - 87Obstructive Pulmonary Disease Asthma Classification of Severity Mild PersistantSymptoms: >2 days/week but not daily
Nighttime: 3-4/month
Use of Rescue Meds: > 2 days/week, but not daily and not more than once per day
FEV1 > 80% predicted
FEV1/FVC normal
Minor limitation on daily activities - 88Obstructive Pulmonary Disease Asthma Classification of Severity Moderate PersistantSymptoms: Daily symptoms
Nighttime: > 1/week, but not daily
Use of Rescue Meds: Daily
FEV1 > 60% but < 80% predicted
FEV1/FVC reduced 5%
Some limitation in daily activity - 89Obstructive Pulmonary Disease Asthma Classification of Severity Severe PersistentSymptoms: Continual symptoms
Nighttime: Often 7/week
Use of Rescue Meds: Serveral/day
FEV1 < 60% predicted
FEV1/FVC reduced > 5% - 90Obstructive Pulmonary Disease Bronchiectasis General CharacteristicsDefined as abnormal, permanent dilation of the bronchi and destruction of bronchial walls. It can be congential (system fibrosis) or acquired from recurrent infections (TB, fungal, lung abscess) or obstruction (tumor).
results from bronchial injury subsequent to severe infection and/or inflamation.
Cystic Fibrosis causes half of all cases. - 91Obstructive Pulmonary Disease Bronchiectasis Clinical FeaturesSymptoms include chronic prurulent sputum (often foul smelling), hemoptysis, chronic cough, recurrent pneumonia.
Physical exam may reveal localized chest crackles and clubbing. - 92Obstructive Pulmonary Disease Bronchiectasis Laboratory Findings CTHigh resolution Chest Ct is imaging modality of choice.
It reveals dilated, tortuous airways. - 93Obstructive Pulmonary Disease Bronchiectasis Laboratory Findings CXRWill be abnorma. The degree of abnormality depends on the extent and severity of the disease.
Crowded bronchial markings and basal cystic spaces are characteristic.
May reveal train-track lung markings, honey combing, atelectasis. - 94Obstructive Pulmonary Disease Bronchiectasis Laboratory FIndings BronchoscopyWarranted to evaluate hemoptysis, remove secretions, and rule out obstructing lesions.
- 95Obstructive Pulmonary Disease COPD General CharacteristicsClinical and pathophysiologic syndrome that includes emphysema and chronic bronchitis.
*Smoking is the most important cause of COPD.
Other causes include environmental pollutants, recurrent upper respiratory tract infections, eosinophilia, bronchial hyperresponsiveness, and α1-antitrypsin deficiency. - 96Obstructive Pulmonary Disease COPD Epidemiology~15 million Americans diagnosed with COPD
63% remain undiagnosed
Common, treatable, preventable (except α1-antitrypsin deficiency) - 97Obstructive Pulmonary Disease COPD Clinical FeaturesPatients present with history of progressive SOB, excessive cough, and sputum production.
Advanced COPD may reveal asthenia, dyspnea, pursed lip breathing, grunting expirations. - 98Obstructive Pulmonary Disease COPD Chest ExaminationSigns of hyperinflation with increase in the anteroposterior dimension are noted.
Percussion yields increased resonance.
Auscultation reveals decreased breath sounds and early inspiratory crackles.
Wheezing may not be present at rest but can be evoked with forced expiration or exertion.
Duration of experiation is prolonged. - 99Obstructive Pulmonary Disease COPD Clinical FIndings Emphysema Predominant"Pink Puffers"
Exertional dyspnea, cough is rare (may be dry), quiet lungs, no peripheral edema, thin (recent weight loss), barrel chest, hyperventilation
Radiography: Decreased lung markings at apicies, flattened diaphragm, hyperinflation, small thin appearing heart.
Loss of both vessels and surface area for gas exchange, so minimal V/Q mismatch. Oxygenation maintained by increased breathing effort - 100Obstructive Pulmonary Disease COPD Clinical Findings Bronchitis Predominant"Blue Bloaters"
Rhonchi reflect secretions in the airways and breathing typically is raspy and loud.
Mild dyspnea, chronic productive cough, noisy lungs (rhonchi and wheeze), peripheral edema, overweight and cyanotic, pursed lip breathing.
Radiography: Increased interstitial markings at bases, diaphragm NOT flattened, parenchymal bullae and blebs.
Obstruction with preservation of distal
parenchyma leads to V/Q mismatch and
hypoxemia - 101Obstructive Pulmonary Disease COPD Laboratory Findings CXRNot sensitive or specific enough to serve as diagnostic or screening tool.
May show hyperinflation, flat diaphragm. - 102Obstructive Pulmonary Disease COPD Laboratory Findings PFTAirflow obstruction demonstrated on forced expiratory spirometry is suggestive.
The FEV1/FVC ratio is DECREASED. - 103Obstructive Pulmonary Disease COPD Laboratory FIndings CBCMay show polycythemia caused by chronic hypoxemia.
- 104Obstructive Pulmonary Disease COPD Treatment - Generally*Smoking cessation is the single most important intervention.
Anticholiergic inhalers are superior to B-adernergic agonists in achieving bronchodialtion.
SABA for acute exacerbations.
Antibiotics often necessary.
Supplemental O2 therapy in patients with resting hypoxemia (PaO2 <55 or SaO2 <88)
Graded aerobic physical exercise encouraged.
Use steroids with caution.
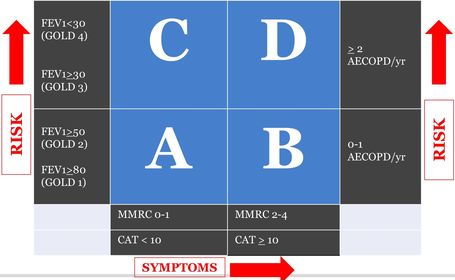
Pneumococcal and flu vaccines. - 105Obstructive Pulmonary Disease COPD GOLD 2014 CharacterizationMMRC = medical research council dyspnea scale
AECOPD = acute exacerbation of COPD - 106Obstructive Pulmonary Disease COPD MMRC ScaleModified Medical Research Council Dyspnea Scale
0 = Not troubled by breathlessness except on strenuous exercise
1= Shortness of breath when hurrying on the level or walking up a slight hill
2 = Walks slower than people of the same age on level because of breathlessness or has to stop for breath when walking at own pace on the level.
3 = Stops for breath after walking about 100m or after a few minutes on the level.
4 = Too breathless to leave the house or breathless when dressing or undressing. - 107Obstructive Pulmonary Disease COPD Hospital Readmissions Reduction ProgramCOPD affects 24 mil in USA, 65 mil worldwide
> 700,000 hospitalizations/year
$35 bill in inpatient costs
1 in 5 readmitted within 30 days
3rd highest rate of readmission
3rd highest source of cost
Half admitted without interim office visit
Critical inhaler technique errors prevalent
Treatments fall short of guidelines - 108Obstructive Pulmonary Disease COPD ComorbiditiesEnvironmental Factors: Smoking, sedentary lifestyle, diet, obesity
Biologic Factors: Systemic inflammation, oxidative stress, endothelial dysfunction, genetics, age, hypoxemia. - 109Obstructive Pulmonary Disease COPD Impact of ComorbiditiesChronic State: Higher symptom burden, lower quality of life, higher costs of care.
Exacerbations: prolonged recovery times, more frequent complications, higher admission/readmission rate
Survival: Higher all-cause mortality, higher disease specific mortality - 110Obstructive Pulmonary Disease COPD COPD + Cardiovascular Disease (CVD)Patients with CVD have higher burden of chronic respiratory symptoms.
CVD increases risk of hospitalization and death at any stage of COPD. - 111Obstructive Pulmonary Disease COPD Palliative CareOnly 13 of patients with O2 dependent COPD discuss palliative care with Dr.
Patients with COPD are less likely to receive palliative care than other advanced illnesses.
Palliative care improves patient satisfaction, decreases hospitalization admissions (36% v 59%), reduces overall costs of care > 50%. - 112Pleural Diseases Pleural Effusion General CharacteristicsThe accumulation of significant volumes of pleural fluid.
May result from inflammation of structures adjacent to the pleural space or lesions within the chest.
Small effusions may not cause symptoms and are discovered on routine radiography.
About 25% of effusions are associated with malignancy. - 113Pleural Diseases Pleural Effusion 4 Types1. Exudates are associated with leaky capillaries. Examples include infection, malignancy, trauma.
2. Transudates (intact capillaries) are associated with increased hydrostatic or decreased oncotic pressure. Examples include CHF, Atelectasis, renal or liver disease (cirrhosis)
3. Empyema is an infection within the pleural space.
4. Hemothorax indicates bleeding into the pleural space, commonly as a result of trauma or malignancy. - 114Pleural Diseases Pleural Effusion Clinical FeaturesWith a small inflammatory effusion, patients are usually asymptomatic.
Large or bilateral effusions may lead to dyspnea.
A dull to flat percussion note over the area of fluid may be heard with reduced or absent breath sounds.
The mediastinum is usually shifted away from the side of the large effusion. - 115Pleural Diseases Pleural Effusion Laboratory FIndingsRadiographic findings include blunting of the costophrenic angle, loss of sharp demarcation of the diaphragm and hear, and mediastinal shift to the uninvolved side.
Lateral deficits radiographs can help to identify small effusions and differentiate free-flowing versus loculated fluid.
CT may be useful if plain film cannot differentiate between parenchymal and pleural densities. - 116Pleural Diseases Pleural Effusion Laboratory Findings ThoracentesisGold standard.
Fluid sent for protein, LDH, pH, total WBC and differential cell counts, glucose, cytology and gram stain with culture and sensitivity. - 117Pleural Diseases Pleural Effusion Laboratory Findings Transudates v ExudatesLight's Criteria.
Fluid is considered an exudate if it meets any ONE of the following.
1. Pleural fluid protein to serum protein ratio > 0.5
2. Pleural fluid LDH to serum LDH ratio > 0.6
3. Pleural fluid LDH greater than 2/3 the upper limit of normal for serum LDH. - 118Pleural Diseases Pleural Effusion TreatmentUnless the cause has been clearly established, the presence of fluid is an indication for thoracentesis.
Transudates pleural effusions resolve when underlying causes are treated.
Emphysema requires drainage and antibiotic therapy. - 119Pleural Diseases Pneumothorax General CharacteristicsThe accumulation of air in the pleural space.
The cause may be spontaneous (primary pneumothorax), traumatic, or iatrogenic.
Tall, thin males between 10-30 are are greatest risk for primary pneumothorax.
Tension pneumothorax is secondary to a sucking chest wound or a pulmonary laceration that allows air to enter the chest with inspiration but does not allow it to leave on expiration. - 120Pleural Diseases Pneumothorax Clinical FeaturesCharacterized by the acute onset of ipsilateral chest pain and dyspnea.
Physical findings depend on the size of the pneumothorax and may include unilateral chest expansion, decreased tactile fremitus, hyperresonance, diminished breath sounds.
Tension pneumothorax is associated with a mediastinal shift to the contra lateral side and impaired ventilation leading to cardiovascular compromise. - 121Pleural Diseases Pneumothorax Laboratory FindingsCXR reveals the presence of pleural air.
A visceral pleural line may be the only evidence of a small pneumothorax.
ABG analysis (if done) reveals hypoxemia. - 122Pleural Diseases Pneumothorax TreatmentDepends on Severity
Small resolve spontaneously
Severely symptomatic or large, chest tube.
Tension pneumothorax is medical emergency. Large bore needle should be inserted to allow air to move out of the chest then chest tube.
Patients should be followed with CXR every 24 hours until resolved. - 123Pulmonary Circulation Pulmonary Embolism General CharacteristicsPE arises from thrombi in the systemic venous circulation or the right side of the heart.
More than 90% of pulmonary embolism originate as clots in the deep veins of the lower extremities. Others include air emboli from central lines, amniotic fluid from active labor, and fat from long bone femur fracture. - 124Pulmonary Circulation Pulmonary Embolism Risk FactorsVirchow's triad
1. Hypercoagulable state
2. Venous stasis
3. Vascular inflammation or injury
Specific risks include surgical procedures, cancer, oral contraceptives, pregnancy. - 125Pulmonary Circulation Pulmonary Embolism EpidemiologyApprox 50-60% of patients with deep vein thrombosis will experience a PE. Half of those will be asymptomatic.
Often, PE is found only on autopsy.
Symptomatic PE is a serious and potentially fatal condition.
PE is the third leading cause of death in hospitalized patients. - 126Pulmonary Circulation Pulmonary Embolism Clinical FeaturesSymptoms include pleuritic chest pain, dyspnea, apprehension, cough, hemoptysis, diaphoresis.
Signs include tachycardia, tachypnea, crackles, accentuation of the pulmonary compartment of the second heart sound, and a low-grade fever. - 127Pulmonary Circulation Pulmonary Embolism Laboratory Findings ABGMeasurements show acute respiratory alkalosis secondary to hyperventilation
- 128Pulmonary Circulation Pulmonary Embolism Laboratory Findings ElectrocardiographyShows tachycardia and nonspecific ST-T wave changes. The classic S1Q3T3 pattern, indicating corpulmonale, is seen in fewer than 20% of patients with symptomatic PE.
- 129Pulmonary Circulation Pulmonary Embolism Laboratory FIndings CXRMay show nonspecific abnormalities such as basilar Atelectasis.
The main purpose of getting a CXR is to rule out other abnormalities and aid in interpreting a ventilation/perfusion scan. - 130Pulmonary Circulation Pulmonary Embolism Laboratory Findings Ventilation - Perfusion ScanShows perfusion defects with normal ventilation.
A normal scan rules out clinically significant thromboembolism.
Nondiagnostic scans warrant further testing. - 131Pulmonary Circulation Pulmonary Embolism Laboratory Findings Pulmonary AngiographyRemains the definitive test for diagnosis but is reserved for cases in which the diagnosis is uncertain after noninvasive testing.
- 132Pulmonary Circulation Pulmonary Embolism Laboratory Findings D-dimerMay be useful to rule out PE if clinical suspicion is low and D-dimer is negative.
- 133Pulmonary Circulation Pulmonary Embolism Laboratory FIndings Spiral CTInitial method of identifying pulmonary embolus
- 134Pulmonary Circulation Pulmonary Embolism TreatmentAnti coagulation therapy is initiated.
Heparin is the anticoagulant of choice.
Low molecular weight heparin or warfarin is continued after the acute phase.
Duration of therpay depends on clinical situation.
Filter is helpful in patients at high risk for recurrence who are unable to tolerate anticoagulants.
High Risk Patients: Early ambulation, Intermittant pneumatic compression stockings - 135Pulmonary Circulation Pulmonary Hypertension General CharacteristicsPresent when the pulmonary arterial pressure rises to a level inappropriate for a given cardiac output. Once present, it is self-perpetuating.
Primary HTN is rare and has a fatal outcome.
Secondary HTN has many causes that develop as a result of obliteration and obstruction of the pulmonary arterial tree.
Hypoxia is the most important and potent stimulus of pulmonary arterial vasoconstriction. Other causes include acidosis and veno-occlusive conditions. - 136Pulmonary Circulation Pulmonary Hypertension Clinical FeaturesDyspnea, retrosternal chest pain, weakness, fatigue, edema, sacites, cyanosis, syncope.
Signs may include marrow splitting and accentuation of the second heart sound and systolic ejection click. - 137Pulmonary Circulation Pulmonary Hypertension Laboratory Findings CXRMay show enlarged pulmonary arteries.
- 138Pulmonary Circulation Pulmonary Hypertension laboratory Findings ElectrocardiographyMay show right ventricular hypertrophy, atrial hypertrophy, and right ventricular strain.
May be useful in estimating pulmonary arterial pressure, but right heart catheterization offers more precise hemodynamic monitoring. - 139Pulmonary Circulation Pulmonary Hypertension TreatmentTreatment of primary pulmonary HTN may include chronic oral anticoagulants, calclum channel blockers to lower systemic arterial pressure and prostacyclin (a potent pulmonary vasodilator).
Heart-lung transplant is usally needed.
Treatment of secondary pulmonary HTN consists of treating the underlying disorder in addition to anticoagulants. - 140Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia General CharacteristicsThis is the most common diagnosis among patients with interstitial lung disease.
There are three histologic patterns with different natural histories and treatments.
1. Usual interstitial pneumonia
2. Respiratory bronchiolitis associated interstitial lung disease
3. Acute interstitial pneumonitis - 141Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia Clinical FIndingsSymptoms include insidious dry cough, exertion all dyspnea, fatigue, malaise.
Examination may reveal clubbing and inspiratory crackles. - 142Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia Laboratory FIndings CXRDemonstrates evidence of progressive fibrosis over several years
- 143Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia Laboratory Findings CTShows diffuse, patchy fibrosis with pleural based honeycombing.
- 144Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia PFTsMay show restrictive pattern (decreased lung volume with a normal to increased FEV1/FVC ratio)
- 145Restrictive Pulmonary Disease Idiopathic fibrosis interstitial pneumonia TreatmentControversial.
None has been shown to improve survival or quality of life compared to no treatment. - 146Restrictive Pulmonary Disease Pneumoconioses General CharacteristicsChronic fibrotic lung diseases caused by the inhalation of coal dust or various inert, inorganic, or silicate dusts.
Clinically important because include coal workers pneumoconiosis, silicosis, and asbestosis. - 147Restrictive Pulmonary Disease Pneumoconioses AsbestosisOccupation: Insulation, demolition, construction
Diagnosis: Bx asbestos bodies
Complications: Increased risk of lung cancer and mesothelioma, especially if a smoker. - 148Restrictive Pulmonary Disease Pneumoconioses Coal workers' pneumoconiosisOccupation: Coal mining
Diagnosis: CXR nodular opacities at upper lung fields
Complications: Progressive massive fibrosis - 149Restrictive Pulmonary Disease Pneumoconioses SilicosisOccupation: Mining, sand blasting, quarry work, stone work
Diagnosis: CXR nodular opacities at upper lung fields
Complications: Increased risk of TB; progressive massive fibrosis. - 150Restrictive Pulmonary Disease Pneumoconioses BerryliosisOccupation: High tech fields, aerospace, nuclear power, ceramics, foundries, tool and die manufacturing.
Diagnosis: CXR diffuse infiltrates and hilar adenopathy
Complications: Requires chronic steroids - 151Restrictive Pulmonary Disease Pneumoconioses Clinical FeaturesIn simple cases, usually asymptomatic.
In complicated cases patients have dyspnea, inspiratory crackles, clubbing, and cyanosis. - 152Restrictive Pulmonary Disease Pneumoconioses Laboratory Findings PFTsShow restrictive dysfunction and reduced diffusing capacity.
- 153Restrictive Pulmonary Disease Pneumoconioses Laboratory Findings Chest radiographyCoal Workers' pneumoconiosis: small opacities are prominent in the upper lung fields
Silicosis: Small rounded opacities are seen throughout the lung and hilar lymph nodes may be calcified.
Asbestosis: Interstitial fibrosis, thickened pleura, calcified plaques appear on the diaphragm or later chest wall. - 154Restrictive Pulmonary Disease Pneumoconioses TreatmentTreatment is primarily supportive as no effective treatment is available.
Supportive therapy includes O2, vaccinations (pneumovax, influenza), and rehabilitation.
Corticosteroids may relieve the chronic alveoli tis of silicosis.
Smoking cessation is equally important for patients with asbestosis because soling intereferes with short asbestos fiber clearance from the lung.
Smoking and asbestos are linked synergistically to lung cancer. - 155Restrictive Pulmonary Disease Sarcoidosis General CharacteristicsSarcoidosis is a multi organ disease of idiopathic cause.
Characterized by noncaseating Granulamatous inflammation in affected organs.
Approximately 90% have lung involvement.
Incidence is highest in North American blacks (esp. Women) and Northern European whites. - 156Restrictive Pulmonary Disease Sarcoidosis Clinical FeaturesCommon respiratory symptoms include cough, dyspnea of insidious onset, chest discomfort.
Patients may present with malaise, fever and symptoms consistent with the he involvement of various organs.
Extra pulmonary findings are common and include erythema nodosum or enlargement of parotid glands., lymph nodes, liver or spleen. - 157Restrictive Pulmonary Disease Sarcoidosis Laboratory Findings Serum Blood TestsMay show leukopenia, eosinophilia, elevated erythrocyte sedimentation rate, hypercalcemia, hypercalciuria.
ACE levels are legates in 40-80% of patients. - 158Restrictive Pulmonary Disease Sarcoidosis Laboratory Findings RadiographicDemonstrate bilateral hilar and right parathracheal adenopathy and bilateral diffuse reticular infiltrates.
- 159Restrictive Pulmonary Disease Sarcoidosis Laboratory Findings Transbronchial biopsy or Fine needle biopsyConfirms diagnosis.
Biopsy shows noncaseating granulomas. - 160Restrictive Pulmonary Disease Sarcoidosis TreatmentApproximately 90 of cases are responsive to corticosteroids and can be controlled with modest maintenance doses.
- 161Acute (adult) Respiratory Distress Syndrome (ARDS) General CharacteristicsThree clinical setting account for 75% of ARDS.
1. Sepsis (most important)
2. Severe multiple trauma
3. Aspiration of gastric contents
Other causes include shock, toxic inhalation, near-drowning, multiple transfusions.
The underlying abnormality is increased permeability of the alveolar capillary membranes which leads to development of protein-rich pulmonary edema. - 162Acute (adult) Respiratory Distress Syndrome (ARDS) Clinical featuresRapid onset of dyspnea occurring 12-24 hours after the precipitating event.
Physical exam shows tachypnea, frothy pink or red sputum, and diffuse crackles.
Many patients are cyanotic with increasingly severe hypoxemia that is refractory to administered oxygen. - 163Acute (adult) Respiratory Distress Syndrome (ARDS) Laboratory Findings CXRMaybe normal at first.
Infiltrates tend to be peripheral (spares the costophrenic angles) with are bronchograms in 80% of patients.
The heart is normal in size.
Upper lung venous engorgement is uncommon.
Pleural effusions are small to absent. - 164Acute (adult) Respiratory Distress Syndrome (ARDS) Laboratory FIndingsPulmonary capillary wedge pressure is normal.
Multiple organ failure is common. - 165Acute (adult) Respiratory Distress Syndrome (ARDS) TreatmentIncludes identification and specific treatment of underlying precipitating and secondary conditions.
Supportive care required to compensate for the severe respiratory dysfunction. O2 should be delivered via endo tracheal intubation with positive pressure ventilation and low levels of positive and end-expiratory pressure (PEEP).
Hypoxia is often refractory to treatment.
Mortality rate is high.
1/3 of deaths occur withing 3 days of onset of symptoms. Remaining deaths within 2 weeks of diagnosis and are caused by infection and multiple organ failure. - 166Aspiration of Foreign Bodies General CharacteristicsMay be of gastric contents, inert material, poorly chewed food.
Degree of injury depends on the substance aspirated. - 167Aspiration of Foreign Bodies Clinical FeaturesAn episode of choking and coughing or unexplained wheezing or hemoptysis should raise the suspicion of foreign body aspiration.
Asphyxia may result from the aspiration of osbstructing material.
Pneumonia may develop secondary to aspiration of toxic materials.
Acute gastric aspiration is one of the most common causes of ARDS. - 168Aspiration of Foreign Bodies Laboratory FIndingsExpiratory radiography may reveal regional hyperinflation caused by a check valve effect
- 169Aspiration of Foreign Bodies TreatmentBronchoscopy may help establish the diagnosis but also can be the treatment of choice for removal of the object.
Cultures should be obtained if post obstructive pneumonia is suspected. - 170Hyaline membrane disease General CharacteristicsThe most common cause of respiratory disease in the preterm infant.
It is caused by a deficiency of surfactant. - 171Hyaline Membrane Disease Clinical FeaturesThe infant will demonstrate typical signs of respiratory distress
- 172Hyaline Membrane Disease Laboratory FindingsCXR demonstrates air bronchograms, diffuse bilateral atelectasis causing a ground glass appearance and coming of the diaphragm.
- 173Hyaline Membrane Disease TreatmentSynchronized intermittent mandatory ventilation should be used.
Administration of exogenous surfactants can be used in the delivery room as prophylaxis or as rescue in established hyaline membrane disease.
Informationen
- Beschreibung
- 1 PA School Karteikarten am Pulmonology - Diseases, erstellt von Elle Ashe am 08/01/2016.
- Erstellt von
- Elle Ashe
- Aufrufe
- 86
- Tags
- Bewertung