
Karteikarten
Test 4: Part 1
Karten in diesem Stapel (200)
- 1What are the 3 themes seen in the evolution of gas exchange?1. Expansion of surface area for gas exchange
2. Development of efficient ventilatory or pumping mechanisms
3. Evolution of respiratory pigments - 2What would happen if gas exchange systems did not evolve?There would be severe constraints on size and metabolism so they could not be >0.5-1 mm
- 3How many alveoli are there in each lung?300 million
- 4How wide are alveoli?0.2 mm in diameter
- 5What is the respiratory surface area?50-100 m^2
(vs. <2 m^2 in the rest of the body) - 6What separates air from the blood?2 thin cells
1 alveolar, 1 endothelial - 7How much blood is in the pulmonary capillaries?60-140 mL spread over the surface area of 50-100 m^2
- 8What causes the alveoli and the lungs to tend to collapse?Elasticity and surface tension
- 9What is the distribution of recoil force?Elasticity = 1/3
Surface tension = 2/3 - 10How are the lungs kept inflated?The pressure in the intrapleural spaces is ~5 mmHg less than that in the lungs
- 11What generates the lower amount of pressure in the intrapleural spaces?Generated partly by lymphatic drainage of pleural fluid and partly by structure of the chest
- 12How much of a pressure change is required to move air in and out of lungs?~1 mmHg
- 13What is the max expiratory effort?~100 mmHg
- 14What is the max inspiratory effort?~ -80 mmHg
- 15How does quiet breathing work?Occurs via movements of the diaphragm
- Inhalation: diaphragm moves down
- Exhalation: resting occurs via passive recoil - 16What happens during heavy breathing?Intercostal muscles raise and lower the rib cage
During forced exhalation, there is an additional contraction of the abdominal muscles - 17What are phospholipid surfactants?They are found in the fluid lining the alveoli
Reduce surface tension and aid in breathing
Secreted by Type 2 alveolar cells
Lowers surface tension by >10x - 18How much pressure does it take to inflate lungs without surfactant?~ - 25 mmHg
- 19What is Respiratory Distress Syndrome? (RDS)Often found in premies as a result of undeveloped surfactant secretion which normally begins at ~32 weeks
First breaths are strong: ~ -60 mmHg
Treatment includes surfactants and cortisol to speed maturation - 20What is Boyle's Law?Pressure of a given quantity of gas is inversely proportional to its volume
- 21What determines respiration rates under normal circumstances?CO2 or H+ concentrations
- 22Where are gas concentration receptors located?Arterial system and medulla of the brain
- 23Respiration is adjusted to maintain PCO2 levels at what pressure?40 mmHg
- 24What is hypocapnia?State of reduced carbon dioxide in the blood
Caused by hyperventilation
Leads to cerebral vasoconstriction, reduced perfusion, dizziness, ischemia (inadequate blood supply to a part of the body), and acidotic condition in the brain
Reduced by breathing into a paper bag - 25What is tidal volume?The amount of air breathed in and out during normal respiration
- 26Inspiratory reserve volumeAmount of air that can be forcefully taken in above normal inspiration
- 27Expiratory reserve volumeAmount of air that can be forcefully expelled from the lungs following a normal expiration
- 28Residual volumeAir that remains in the lungs that can't be forced out
- 29Total lung capacitySum of tidal volume, inspiratory reserve volume, expiratory reserve volume, and residual volume
- 30Vital capacityAmount of air that can be expelled following a maximal inspiration
- 31Functional residual capacityAmount of air remaining in lungs after normal expiration
- 32Inspiratory capacityAmount of air that can be inspired following normal expiration
- 33How much O2 do we use and CO2 do we produce per minute?~200 mL
- 34Where do local decreases in O2 or pH cause local vasoconstriction? Wha? What is the significance of this?In the alveoli ONLY
This means that blood only passes through well-ventilated alveoli - 35How much more soluble is CO2 that O2 in water?20x
- 36How is O2 transported?It diffuses from the alveoli into the capillaries, then dissolves in plasma and then into RBCs where it combines with hemoglobin.
- 37What is our respiratory pigment?Hemoglobin
- 38How much does hemoglobin increase the O2 carrying capacity of our blood?60-70x
- 39Which is a brighter red: oxy- or deoxy-hemoglobin?Oxyhemoglobin
- 40What effect does packaging hemoglobin inside RBCs have on osmotic pressure?It keeps the OP low
- 41How is the Antarctic Icefish able to survive without respiratory pigment?O2 is more soluble in cold, so they live in cold water and have a low metabolic rate
- 42Describe vertebrate hemoglobinHas 4 polypeptide globin subunits (beta 1&2 and alpha 1&2), each with a heme group
Each heme group has Fe++ which binds 1 O2 loosely. Four molecules of O2 can be transported for every 1 heme group. - 43Difference between HbA, HbF, and HbSHbA (adult hemoglobin) has mostly 2 alpha and 2 beta subunits
HbF (fetal) has mostly 2 alpha and 2 gamma subunits. The gammas switch to betas at birth
HbS (sickle cell anemia) has 2 alpha and 2 sickles - 44What is sickle cell anemia?A disease that causes individuals to have 2 sickle hemoglobin chains instead of 2 betas (the sickle chain has 1 AA different than beta)
Causes hemoglobin to polymerize and crystallize, which causes RBC rigidity and capillary obstruction
ESPECIALLY in low O2 environments - 45How much higher is hemoglobin's affinity for CO than for O2?200x
- 46What are the three means of CO2 transport in the blood?7% in solution as: CO2 + H20<->H2C03 <->H+ + HCO3-
70% is transported inside RBCs as: CO2 + H20 <->H2C03 <-> H+ + HCO3- <-> H+:Hb
15-25% as: CO2 + Hb -> Carbaminohemoglobin - 47What is carbonic anhydrase?Speeds up the CO2 transportation reaction inside RBCs by 5000x
- 48Where does CO2 attach to hemoglobin?An amino acid
NOT the site where O2 binds - 49What is the O2 pressure at sea level?160 mmHg
- 50What is the pressure of O2 in the alveoli? Why?105 mmHg
Because air in the alveoli is subjected to removal of O2 as soon as it enters - 51Is the O2 partial pressure higher in tissures during rest or during exercise?Rest (40 vs. <20)
- 52What is the Bohr effect?In acidic conditions, hemoglobin has a lower affinity for O2
This lets Hb load more O2 in the lungs where pH is higher and unload more in the tissues where pH is lower - 53What is normal arterial pH?7.40
- 54What is the pH of blood during rest after it passes through the capillaries?7.36
- 55What is the pH in muscle with exercise?Down to 6.9
Increases O2 unloading - 56How much does the temperature of active muscles change?Can increase by 3-4 degrees
Causes unloading of O2 - 57What is subunit cooperativity?As each hemoglobin subunit binds O2, it increases the affinity of other subunits for O2
- 58What is the T (taut) state?It is the state in which a hemoglobin subunit is not bound to O2
In "low-affinity" state - 59What is the R (relaxed) state?It is the state after the 1st subunit of hemoglobin binds O2 in which the other three subunits have a higher affinity for O2
SUBUNIT COOPERATIVITY - 60How does O2 binding/unloading in hemoglobin affect CO2 affinity?As Hb binds O2, its affinity for CO2 decreases and as it unloads O2 its affinity increases
- 61What is the Haldane Effect?Causes hemoglobin to load 2X more CO2 than oxygen in the tissues and unload the same amount more in the lungs
- 62What is 2, 3 BPG?Biphosphoglycerate
Byproduct of glycolysis that has a high affinity for the T form of hemoglobin and decreases its affinity for O2
It is higher in tissues where it enhances O2 unloading - 63What can cause a lowered affinity for O2 in hemoglobin?2, 3 BPG binds to T form and decreases its affinity for O2
Binding of H+ and CO2 to hemoglobin in tissues shifts hemoglobin to T form, lowering its affinity for O2 - 64Why do smokers not load as much O2?They have more 2,3 BPG in their blood
- 65What happens to 2,3 BPG levels during pregnancy? What does this cause?30% increase
Lowers the mom's affinity for O2 so more can be offloaded to the fetus. HbF (fetal) doesn't bind much BPG, so it has a higher affinity for O2 to extract it from the mom. - 66What happens to the hemoglobin/O2 saturation graph in sickle-cell anemia?The curve is shifted right
- 67What is the inspiratory region?Region in the brainstem that generates basic rhythm for breathing by sending signals to the diaphragm
- 68What is the expiratory region?Region of the brainstem that stimulates expiratory muscles during heavy breathing
Not activated during quiet breathing - 69What is the pneumotaxic center?A region of the brainstem whose activity increases ventilation rate
- 70What is the apneustic center?Region of the brainstem that creates long breaths when activated
- 71What is the Hering-Breuer Reflex?When inhalation >1.5 L, stretch receptors begin firing to protect against overinflation
- 72What is the goal of respiration?Maintain proper concentrations of O2, CO2, and H+
- 73How does the body maintain proper concentrations of O2, CO2, and H+?Blood is monitored by central and peripheral chemoreceptors to detect changes in gases. The receptors automatically adjust ventilation to keep blood gases within set limits.
- 74Which chemoreceptors respond most to CO2 and H+?Central chemoreceptors in the brainstem
Increased levels lead to increased ventilation by action of CCs in other respiratory regions
Decrease O2 levels have no effect in the brain on respiration - 75What chemoreceptors respond the most to low levels of O2?Peripheral chemoreceptors in the carotid and aorta
Only way low O2 affects respiration
The act by causing the respiratory centers to increase breathing rate - 76What is the normal ventilation rate?12-14 breaths/min
- 77When PO2 decreases by 1/2, how much does ventilation increase?1.5x
- 78How does the ventilation rate change with a drop in pH from 7.4 to 7.0?Leads to a 4x increase in ventilation
- 79What is the effect on ventilation of increasing the pressure of CO2 by 50%It leads to a 10x increase in ventilation
- 80What is the "Braking Effect"?The reason low O2 pressure has small effects
Occurs because increased ventilation "blows off" too much CO2, causing decreased H+
Low CO2 and H+ causes dramatic inhibition of ventilation via effects on control centers, therefore the O2 pressure usually has little control over ventilation - 81Why does low CO2 and H+ cause dramatic inhibition of ventilation?Because their regulation is important for acid-base balance
- 82At most O2 pressures, is hemoglobin saturated or unsaturated with O2Saturated
- 83What provides the strongest stimulus to breathe?CO2 levels
- 84What is the functional unit of the kidney?Nephron
- 85How many nephrons are there per kidney?1 million
- 86What are the two types of nephrons?Cortical: not so important for water reabsorption (5x more)
Juxtamedullary: important for water reabsorption - 87How thick are the walls of the nephron?1 cell thick
- 88What is the glomerulus?Capillary bed inside of Bowman's Capsule
Supplied by the afferent arteriole and drained by the efferent arteriole which allows control of blood pressure on either side of the glomerulus (because of arteriole sphincters) - 89What is the vasa recta?Comes from the efferent arteriole
Capillary system that surrounds each juxtamedullary nephron
Important for reabsorption and secretion - 90What is the osmotic gradient from the cortex to the medulla?300 mOsm (cortex) to 1200 mOsm (medulla)
- 91What determines how concentrated urine can be?Length of the Loop of Henle and the size of the osmotic gradient
- 92What can urine osmolarity be in some desert animals?3000+ mOsm
- 93What are the three steps of urine formation?Filtration, reabsorption, and secretion
- 94What detects dehydration?Hypothalamus
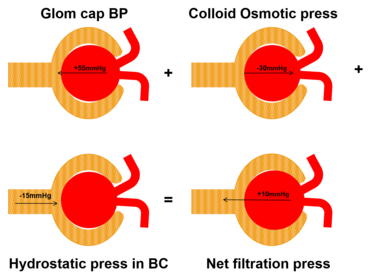
Secretes ADH which causes the kidney to conserve - 95What drives glomerular filtration?10 mmHg net pressure in the glomerulus
- 96What gets filtered into Bowman's Capsule?Anything less than 5,000 MW is freely filtered into the BC
Based ONLY on molecule size - 97What are the pressures like around Bowman's Capsule? (picture)
- 98What does fenestrated mean?To have holes
Glomerular capillaries are fenestrated
Causes glomerular capillaries to be 100x more permeable than most other capillaries - 99What are podocytes?"foot cells"
What make up the inner layer of Bowman's Capsule and cover the glomeruli - 100What are filtration slits?Slit between pedicels of the podocytes which dictate what size molecules can be filtered (prevent anything too big from getting through)
- 101What percentage of water and solutes passing through the glomerulus is filtered?15-25%
- 102How many milliliters of water/solutes pass through the glomerulus per minute?125 mL/min
(=45 gals/day of water) - 103What things are too large to be filtered through the glomerulus?RBCs and most proteins
- 104How much of water/salts is reabsorbed before the kidney produces final urine?99%
Reabsorption is selective so that some wastes (like urea) become concentrated - 105How does reabsorption occur?By transport and diffusion
Ions are transported and water follows - 106What compounds are 100% reabsorbed in the kidney?Glucose, vitamins, and amino acids
- 107How are 2/3 of filtered Na+ reabsorbed?Through active transport
- 108What is the driving force for most that happens in the proximal convoluted tubule?R
- 109How are filtered proteins reabsorbed?By endocytosis
- 110How much of total filtrate is reabsorbed on the PCT?2/3s
If he says "most reabsorbed".....assume PCT! - 111Drugs, toxins, and H+ can be secreted in the PCT. How?The liver tags drugs/toxins with glucuronate or sulfate groups. The kidney recognizes and secretes these.
- 112What are the functions of the Descending Loop of Henle?Passive H2O reabsorption
NO active transport of salts - 113What are the permeabilities in the Descending Loop of Henle?Salt is moderately permeable
Urea has low permeability
High H2O permeability (H2O is pulled out by high osmolarity in the medulla via Aq1 aquaporins) - 114What controls Aq2?ADH
- 115What are the functions of the Ascending Loop of Henle?Passive salt reabsorption in the thin part and active reabsorption in the thick
- 116What are the permeabilities in the Ascending Loop of Henle?High salt permeability (pulled out by decreasing osmolarity of the ECF as pre-urine moves toward the cortex)
Low urea
Low water - 117What is the Diluting Segment?The thick part of the Ascending Loop of Henle
Called that because the filtrate become hyposomotic as salt is actively transported out - 118What is the osmolarity of pre-urine at the end of the Diluting Segment?100 mOsm (1/3 of blood)
- 119What do the actions of the Distal Convoluted Tubule and the Cortical Collecting Duct depend on?Hormones and acid-base balance
- 120Where does aldosterone stimulate Na+ reabsorption and K+ secretion?Distal Convoluted Tubule and the Cortical Collecting Duct
Way that the potassium concentration in the urine is controlled - 121When are the DCT and CCT permeable?Only when ADH is present
- 122What can be secreted into urine and reabsorbed from pre-urine?Secreted into: K+, H+, and NH3
Reabsorbed from: Na+, Cl-, and HCO3- - 123What happens if pre-urine is too acidic?Too basic?Acidic: H+ can be secreted (against up to a 1000x gradient)
Basic: HCO3- can be secreted - 124What is the function of the medullary CD?Mainly in variable H2O reabsorption (depends on state of hydration and concentration of ADH)
- 125What happens when ADH is present?The Medullary CD becomes permeable to H2O and the pre-urine equilibrates with the high osmolarity of medulla
ADH stimulates the insertion of aquaporins (Aq2) into the membrane
Also stimulates facilitated transport of urea out of pre-urine into the medullary ECF - 126How does ETOH dehydrate?Reduces the release of ADH
- 127When does the gradient reach 1200 mOsm?Only when ADH is high
Urine will be between 100 and 1200 mOsm depending on the concentration of ADH - 128What are the two mechanisms that produce the up to 900 mOsm gradient/Active transport of salts in the diluting segment creates 600 mOsm of gradient
Facilitated transport of urea out of the medullary CD creates 300 mOsm - 129How does facilitated transport of urea out of the medullary CD create part of the gradient?Urea becomes concentrated by ~65x as pre-urine flows through the nephron
In the Medullary CD it is transported down its concentration gradient into extracellular fluid when ADH is high - 130How is the glomerular filtration rate controlled?Through both ANS and local control
ANS: strong sympathetic activity via fight/flight, exercise, or bleeding causes vasoconstriction of the afferent arteriole. This shunts blood away from the kidney, leading to decreased filtration to maintain blood volume
Local: also called autoregulation; maintains filtration fairly constant over BPs from 75 mmHg to 160 mmHg because if filtrate flows through nephron fast then too little is reabsorbed (and vice versa) - 131What is myogenic autoregulation?When high blood pressure stretches the afferent arteriole, causing a reflex smooth muscle contraction that leads to a decreased glomerular filtration rate
Decreased blood pressure causes dilation of the afferent arteriole and constriction of the efferent, increasing GFR - 132What is the Juxtaglomerular Apparatus?When activated the JGA causes increased glomerular filtration rate
Area located in the angle between the afferent and efferent arterioles in the region of the DCT just after the diluting segment
Formed from aff/eff arterioles + the adjoining DCT - 133What is the macula densa?DCT cells that touch arterioles and sense [Na+]
When [Na+] is low, it causes the macula densa to release NO which dilates the afferent arteriole and PGs which cause granular cells to secrete renin. - 134Why does low [Na+] cause the macula densa to release NO to dilate the afferent arteriole?low Na+ can be caused by over-absorption in the diluting segment due to low flow, so dilating the aff. arteriole increases that flow
- 135What are the granular cells?Cells between the macula densa and the afferent arteriole which secrete renin both in response to PGs from the macula densa and in response to BP or sympathetic NS stimulation
- 136What is RAAS?renin angiotensin aldosterone system
- 137What is renin?It is an enzyme produced by granular cells that converts angiotensinogen from the liver to angiotensin I
- 138How do you make Angiotensin II?A converting enzyme in the lungs converts Angio I to Angio II
- 139What does angiotensin II do?Causes systemic vasoconstriction (greater effect on efferent arteriole than aff. to maintain SOME kidney filtration)
Stimulates sympathetic NS activity
Stimulates ADH secretion
Stimulates thirst
Causes the adrenal cortex to release aldosterone, which increases Na+, H2O, and Cl- reabsorption and K+ secretion. - 140How do ACE inhibitors work?The block the angiotensin converting enzyme in the lungs
- 141What are the three natriuretic peptides? Where are they produced?Atrial natriuretic peptide (ANP): hormone produced by the atria
B-type natriuretic peptide (BNP): hormone produced by the ventricles
C-type natriuretic peptide (CNP): paracrine compound produced in the endothelium and the heart - 142What do natriuretic peptides do? When are they released?Released when high blood volume stretches the tissues that produce them
Act opposite to RAAS: inhibit sympathetic system and secretion of renin, aldosterone, and ADH
Cause vasodilation and loss of Na+ and water
Causes lipolysis which reduces the fat load on the heart - 143Why are BNP levels used to assess heart failure?The heart output during heart failure can't match the venous return, so the ventricles get stretched. When they are stretched, they release BNP.
- 144What are diuretics?Most inhibit reabsorption of Na+ and Cl- so you lose both NaCl and H2O
Used to treat heart failure, high blood pressure, and kidney disease - 145What are the #1 and #2 causers of nephropathy? (kidney disease)1. Diabetes
2. High blood pressure - 146What does nephropathy cause?Albuminuria (loss of albumin) and hyperfiltration
- 147What causes nephropathy?High glucose and high blood pressure lead to the loss of podocytes
- 148How long is the tube of the digestive tract?17-20 feet
- 149What is the primary method of chemical digestion?Hydrolysis
Molecules are split by adding water - 150What does saliva contain?Amylase: breaks down starch
Lipase: breaks down fat
Lysozyme: enzyme that lyses gram+ bacteria - 151How does the autonomic nervous system affect saliva release?Parasympathetic stimulates
Sympathetic inhibits - 152What is chyme?Mix of food and gastric secretions from the stomach
- 153What produces gastric secretions?Cells of the gastric pits in the stomach
- 154What does the stomach do?Produces chyme
Denatures proteins
Disinfects
Produces gastric secretions (including acid and mucus) - 155What are mucous neck cells?Cells in the gastric glands of the stomach that produce a thick mucus/bicarbonate (basic) layer for protection
- 156What are chief cells?Cells in the gastric glands of the stomach that produce pepsinogen
Pepsinogen is converted by HCl from the stomach to pepsin, which cuts proteins into small peptides - 157What does pepsinogen do?Pepsinogen is converted by HCl from the stomach to pepsin, which cuts proteins into small peptides
- 158What are parietal cells?Cells in the gastric glands in the stomach that secrete [HCl] at a pH of about 1
Inhibited by Prilosec, Prevacid, and others - 159How strong is the proton pump of parietal cells?Can pump against a million times gradient
- 160What is the function of [HCl] in the stomach?Disinfects, is a good solvent, and denatures 3rd degree structures of proteins
- 161What are G cells?Cells of the gastric glands of the stomach which secrete gastrin
- 162What is gastrin?Peptide hormone released by the G cells in the gastric glands which indirectly stimulate parietal cells to release HCl
Excessive amounts are related to ulcers - 163How does gastrin stimulate the release of HCl?Stimulates the secretion of histamine by the ECLs (enterochromaffin-like cells) of the gastric pits
The histamine acts as a paracrine to stimulate the parietals which then release HCl - 164How do Zantac and Pepcid work?They block histamine receptors to prevent the stimulation of parietal cells which secrete acid in the stomach
- 165What effect does the parasympathetic have on parietal cells and ECLs?Stimulates both!
"Rest/DIGEST" - 166What can the stomach absorb?Some small molecules
ETOH, H2O, glucose, especially non-polars - 167How often is the lining of the stomach replaced?Every 3 days
- 168What is the intrinsic factor?A polypeptide that is produced by parietals that is necessary for absorption of vitamin B12 in the small intestine
- 169What is pernicious anemia?Anemia that results from a lack of vitamin B12
B12 is necessary for RBC production, so too little results in low hematocrit (anemia)
Occurs mostly from autoimmune attack against parietals or intrinsic factor - 170Where does most digestion occur?Small intestine
- 171How long is the small intestine? How big is the absorptive area?10 feet long
Size of a tennis court - 172Describe the surface of the inside of the small intestineHighly folded, covered with finger-like villi (looks like carpet), has tight junctions so nutrients have to move across membranes
- 173What are microvilli?Cover the villi of the small intestine
Secrete enzymes for complete breakdown of food molecules to monosaccharides and amino acids prior to absorption - 174What part of the small intestine functions in reabsorption of nutrients? Fats?Capillaries in the villi (nutrients)
Lacteals, which are blind-ending lymph capillaries (fats) - 175How long does it take for chyme to move through the small intestine?Several hours
- 176Where is the pancreas?Below the stomach and connected to the small intestine via the pancreatic duct
- 177What enzymes are secreted by the pancreas?Amylases: convert starches to smaller saccharides
Lipase: converts triglycerides into free fatty acids and monoglycerides
Proteases: convert proteins into dipeptides
Bicarbonate: neutralizes stomach acid
ALL PRODUCED AND SECRETED IN INACTIVE FORM - 178Why are pancreatic enzymes produced and secreted in the inactive form?Because they are so powerful that they can digest the pancreas itself if in active form
Normally activated in the small intestine - 179What is acute pancreatitis?Pancreatic enzymes become active in the pancreas instead of in the small intestine
Can cause death in a few days if not stopped - 180What is the pH in the small intestine?6.5-7.5
- 181Digested carbohydrates and proteins are absorbed by capillaries in the small intestine villi. Where do they go next?Directly to the liver via the hepatic portal vein
- 182What does the liver do?Detoxifies blood
Processes nutrients - 183What is the first pass effect? How do you avoid it?Many drugs absorbed by the GI tract are broken down in the liver
To avoid this, they have to be injected, absorbed transdermally, or in suppository - 184What are prodrugs?Drugs that are designed to be absorbed in the GI tract and activated in the liver
Example: dextromethorphan (cough suppressant) is activated in the liver to dextrorphan - 185What are bile acids?Emulsifying, detergent-like molecules produced by the liver that are the first step in fat digestion
Secreted by the liver constantly and stored in the gall bladder - 186What happens to the gall bladder after meals?It contracts, sending bile to the small intestine
- 187What does emulsification do?Increases surface area for lipase to covert fat to fatty acids and monoglycerides
Forms micelles - 188What are micelles?Aggregates of fatty acids and monoglycerides that are coated with bile acids
- 189What happens to the fatty acids and monoglycerides produced by lipase?Absorbed by the small intestine villi and most then used to resynthesize triglycerides in smooth ER of the villi
Some of the small fatty acids are absorbed by capillaries in the villi and go to the liver - 190What are chylomicrons?Made in the small intestine villi
Triglycerides and cholesterol are packaged with a phospholipid and lipoprotein coat
Chylomicrons are then secreted into the lacteals (lymphatic system) - 191Why is plasma taken after meals often cloudy?Because of the chylomicrons being released into the lymphatic system
- 192How long is the large intestine (colon)?4 feet
- 193How much water does the large intestine absorb?0.5-2L per day
- 194What does the large intestine absorb?Water, vitamins, drugs, suppositories
- 195Why is the large intestine slow-moving?Lets bacteria digest unabsorbed material (mostly cellulose)
- 196How many species of bacteria are there in the large intestine?400+
- 197How much of the mass of feces is of bacterial origin?1/3
- 198What is flatus?Gas produced by bacteria in the large intestine
- 199Why do beans give you gas?They contain undigestable carbohydrates which bacteria convert to gas
- 200What do bacteria in the large intestine produce from fiber?Vitamin K, vitamin B, and fatty acids
Informationen
- Beschreibung
- Test 4
- Erstellt von
- Brianne Schmiegelow · Apr 2016
- Aktualisiert
- 13 Aug 2016
- Aufrufe
- 45
- Tags
- Bewertung