
Notes
Spastic Dysarthria
Content of the notes (1)
Page 1
Speech: the motor act of verbal expression
The Five Subsystems of Speech:
1. Respiration
2. Phonation
3. Resonance
4. Articulation
5. Prosody
Dysarthria - Defining Characteristics
It is a group of speech disorders caused by disturbances of neuromuscular control of the speech production systems
A disruption to the execution of speech movements
It can result from underlying neuromuscular disturbances to muscle tone, reflexes and kinematic aspects of movement, such as speed, range, accuracy and steadiness
Generally more consistent in its errors and amount of intelligibility compared to apraxic speech
Seven Types of Dysarthria
Spastic Dysarthria
Flaccid Dysarthria
Hypokinetic Dysarthria
Hyperkinetic Dysarthria
Ataxic Dysarthria
Unilateral UMN Dysarthria
Mixed Dysarthrias
Assessment Methods
Perceptual: listening; audio visual and tactile
Acoustic: measurement of speech
Physiologic: measurement of physiological processes (electrical measurement)
SPASTIC DYSARTHRIA
Quick Overview:
associated with bilateral damage that affects the UMN - direct and indirect activation pathways of the CNS
this means the PYRAMIDAL and EXTRAPYRAMIDAL motor pathways
Px has increased muscle tone (spasticity)
Weakness
Reduced speed and range and force of movements
Hyperreflexes
Can be a result of bilateral lesions in the motor cortex and its pathway to the LMN that are responsible for muscle contraction
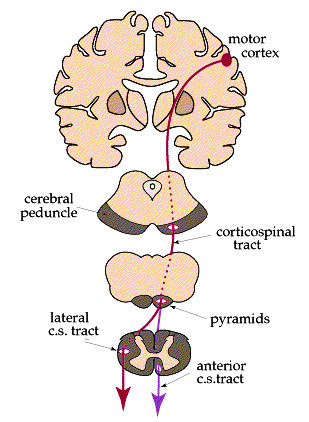
Pyramidal Descending Motor Pathway
Motor impulses at the cortical level
Corticospinal and corticobulbar tract
Controls speech movements, which are discrete and skilled movements
Works at a conscious level - voluntary movements
Direct Pathway - this is because its axons descend without synapsing from the pyramidal neurones to the spinal cord
Large neurons with long axons that project into the spinal cord
Control the precise or skilled voluntary movements of our skeletal muscles
If damaged:
Leads to weakness and slowness of movements
Further info:
the pyramidal cells that control foot movements are in one place and those that control hand movements are in another
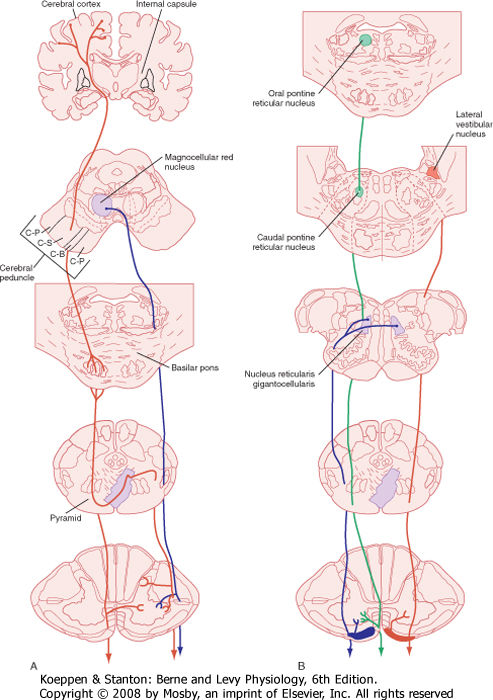
Extrapyramidal Descending Motor Pathway
Motor impulses in the cerebral cortex
Rubrospinal, reticulospinal, vestibulospinal and tectospinal tract
These pathways are involved in:
Maintaining posture
Regulation of reflexes
Monitoring muscle tone
More unconscious and therefore involuntary motor control
Indirect Pathway - this is because they project to influence the activity of most extrapyramidal nuclei
Involved in:
maintaining balance and posture
controlling coarse limb movement
head, neck and eye movements that follow objects in the visual field
If damaged:
Weakness of movements
Spasticity
Abnormal reflex movements
Presentation
May affect one or a combination of:
Respiration
Phonation
Resonance
Articulation
Prosody
Diagnosis of spastic dysarthria = bilateral damage to UMN
Unilateral UMN damage = Upper Motor Neuron Dysarthria - generally less severe due to bilateral CN innervation
THEREFORE:
Result of combined effects of:
Bilateral damage to pyramidal motor tracts
Bilateral damage to extrapyramidal motor tracts
THIS THEN LEADS TO:
Weakness
Slowness
Spasticity
Abnormal reflexes
AETIOLOGIES
Those conditions that can impede the function of UMN of DESCENDING pathways BILATERALLY
These include:
Degenerative conditions (MND, MSA etc)
Degenerative causes make up the largest group
Spastic dysarthria may be evident if degeneration begins in the UMN
Vascular (CVA, anoxia)
CVA need to be at brainstem to cause bilateral damage, multiple CVA in both hemispheres or one CVA in one hemisphere plus pre-existing condition in other hemisphere
Vascular dementia can also cause spastic dysarthria
Idiopathic causes
Congential
Traumatic (TBI)
Demyelinating Conditions (MS)
CLINICAL CHARACTERISTICS
The weakness and spasticity we can see in the Px speech may also present elsewhere in the body
Keep in mind their gag reflex might be hypersensitive, but this is generally a redundant procedure
Babinski Reflex - this may reappear even though previously diminished. Px toes may curl up if bilateral damage
Jaw Jerk Reflex - this is only carried out on Px suspected of having neurological damage and is an indicator of spastic dysarthria
DYSPHAGIA
may be present
Px may be able to swallow food, but chewing may take a long time
Due to reduced swallowing frequency and control over saliva secretion, there may be drooling
LABILITY
Px may be emotionally labile
Excessive and uncontrollable laughter or crying
CLONUS
Shivering or rapid tremor-like appearance
ORO-MOTOR
Slow movements
Symmetrical appearance of structures
IMPACT ON SPEECH
According to Duffy, spastic dysarthria will most likely impact all speech systems, as it is associated with impaired patterns of movement that use muscle groups and not just individual muscles
DAB - MOST COMMON CHARACTERISTICS
Imprecise consonants
Monopitch
Reduced stress
Harsh voice quality
Monoloudness
Low pitch
Slow rate
Hypernasality
Strained-strangled voice quality
Short phrases
Distorted vowels
Pitch breaks
Breathy voice
Excess and equal stress
REMEMBER: You can't rely on the presence of one of these features to make a differential diagnosis; look for clusters or patterns of features
CLUSTERS
CLUSTER ONE: PROSODIC EXCESS
Result of slowness of repetitive movements that are associated with speech
Evident when there is:
Excess and equal stress
Slow rate of speech
CLUSTER TWO: ARTICULATORY-RESONATORY INCOMPETENCE
Result of the decreased range and force of movement by the articulators
Evident when there is:
Imprecise consonants
Distorted vowels
Hypernasality
CLUSTER THREE: PROSODIC INSUFFICIENCY
It is the reduced ability to vary the patterns of movement (in speech)
This is apparent through:
Monopitch
Monoloudness
Reduced stress
Short phrases
CLUSTER FOUR: PHONATORY STENOSIS
When there is over-adduction of the vocal chords as as result of spasticity
This is apparent due to:
low pitch
harshness
strained-strangled voice
pitch breaks
short phrases
slow rate
IMPACT ON THE SPEAKER
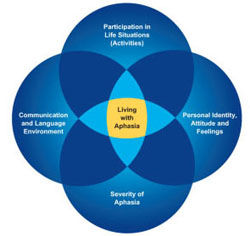
PERSONAL IDENTITY
Somebody who has had a bilateral stroke may also have cognitive deficits, therefore they may be unaware of their limitations
WHAT THE PATIENT MIGHT TELL YOU ABOUT THEIR SPEECH
Speech might be slow or effortful
Speaking against resistance
Speech will deteriorate when patient becomes fatigued
May need to speak slower
Speech may be nasalised
Swallowing difficulties and drooling
Emotional lability
INTRO
SPASTIC DYSARTHRIA
SPASTIC DYSARTHRIA - CHARACTERISTICS
Information
- Description
- Includes introduction to acquired speech disorders
- Created by
- jessica.wilson1
- Views
- 160
- Rating