
Fichas
Treatment of diabetes
Fichas del conjunto (49)
- 1Insulin - produced where - released with and how - stimulant of secretion - basal secretionInsulin is produced in beta cells which constitute 75% of the islets of Langerhans of the pancreas
Insulin, as well as C peptide, are released by exocytosis into the portal venous system which leads it directly to the liver (50%)
The principal stimulant of insulin secretion is glucose
With a basal secretion of approximately 40 microgram/h under fasting conditions
released in 2 phases! - 2mechanism of insulin secretion- glucose enters the beta cell via GLUT2
- glucose phosphorylated by glucokinase (traps it inside cell)
- glucose --> ATP
- ATP closes K+ channel
- membrane depolarisation opens Ca2+ channels
Ca2+ influx stimulates exocytosis of insulin - 3T1DM treatmentInsulin!
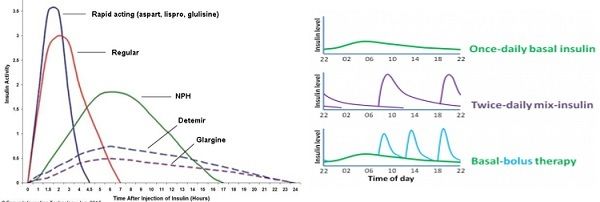
peptide so cannot be given orally, subcutaneous injections - 4types of insulin therapy
- 5insulin overview (short, long, mixed

- 6Why can Lantus not be mixed with other insulins prior to injection?acidic pH
- 7benefits of intensive diabetes therapyIntensive therapy effectively delays the onset and slows the progression of diabetic retinopathy, nephropathy, and neuropathy in patients with IDDM.
- 8insulin pen benefitsMore convenient and easier to transport than traditional vial and syringe
Repeatedly more accurate dosages
Easier to use for those with impairments in visual and fine motor skills
Less injection pain (as polished and coated needles are not dulled by insertion into a vial of insulin before a second insertion into the skin)
Can be used without being noticed - 9Continuous subcutaneous infulin infusion (CSII) - benefits - drawbacks- CSII (pump therapy) can improve diabetic control and QOL for T1DM
- less danger of severe and incapacitating hypoglycaemia
- complications include: reactions and occasionally infections at the cannula site, tube blockage and pump malfunction.
- CSII therapy is expensive, incurring costs for batteries, reservoirs, infusion sets, insulin, lancets, test strips and glucometers - 10How does insulin pump work?infuses insulin at basal rate, with patient-activated boosts at meals
- 11'Curative' treatment in T1DMislet cell transplant
pancreatic transplant - 12Whipple's Triadfor Hypoglycaemia!
1. Symptom of low blood glucose: autonomic or neuroglycopaenic
2. Measured plasma glucose
< 2.8mmol - normal
< 4.0mmol – insulin-treated DM
3. Better after glucose - 13hypoglycaemia effects by glucose level4.6 mmol/l - inhibition of insulin release - general malaise: headache, nausea
3.8 mmol/l - release of counterrgulatory hormones glucagon and adrenaline – onset of autonomic symptoms (most occur ~3 mmol/l)
- sweating, palpitations, shaking, nausea, anxiety, hunger
BUT 70-80% of readings at this level no symptoms
2.5 -2.8 mmol/l - impairment of cognitive function and concentration, inability to perform complex tasks - confusion, drowsiness, odd behaviour, speech difficulty, incoordination, weakness, visual change, dizziness, tiredness
<2mmol/l – EEG changes, seizures
<1.5 mmol/l - coma, convulsions - 14severity scale of hypoglycaemia and treatmentmild: autonomic
- give 15-20g quick acting carbohydrate eg. Dextrosol, Lucozade, fruit juice
- repeat up to 3 cycles until >4mmol/L
moderate: autonomic and neuroglycopaenic
- if capable, treat as per mild
- if not but can swallow give glucose gel, or Glucagon IM
- repeat up to 3 cycles
Severe: autonomic and neuroglycopaenic
- check ABC and stop IV insulin
- give IV glucose or Glucagon IM - 15Hypos and driving group 1CBG> 5mmol/l before driving, carry CHO, identifiers
If between 4-5 mmol/l– eat before driving
2 hours at a time
Do not drive if feeling hypo or BM <4 mmol/l
If hypo: 1hour before driving (from onset) and CBG>5
Group 1 entitlement: on insulin
Adequate hypo awareness
Not >1 severe hypo whilst awake in 12 months or most recent <3months f
CBG monitoring evidence
Not a danger to the public
Acuity and visual fields OK
Group 1 entitlement: tablets risk of hypos
No more than one severe hypo in 12 months
BM diary for driving - 16hypos and driving group 2CBG > 5mmol/l before driving, carry CHO, identifiers
If between 4-5 mmol/l– eat before driving
2 hours at a time
Do not drive if feeling hypo or BM <4 mmol/l
If hypo: 1hour before driving (from onset) and CBG>5
Group 2 entitlement: IRDM
Full hypo awareness and understanding of risks
No severe hypos in 12 months
CBG monitoring evidence: 3 months of recordings
Not a danger to the public
Acuity and visual fields OK
Group 2 entitlement: tablets risk of hypos
No severe hypos in 12 months
Full hypo awareness and understanding of risks
CBG checks at least twice daily and more often for driving - 17Diabetic ketoacidosis - what - investigation findingsClinical diagnosis with diagnostic criteria
Mainly T1DM but now recognise ketosis prone T2DM
1) Metabolic acidosis:
VENOUS bicarbonate < 18mmol
H+ > 45 mEq/L
pH < 7.3
2) Plasma glucose: > 13.9mmol/l
3) Urinary / plasma ketones: ≥2+ urinary / >3mmol/L - 18mortality in diabetic ketoacidosis - young - adultsMortality in young: cerebral oedema 70-80% deaths
Mortality in adults: severe hypokalaemia, ARDS, illness causing decompensation - 19pathogenesis of ketoacidosisAbsolute or relative insulin deficiency
+
Increase in stress hormones
-->
1. Lipolysis: FFAs: ketogenesis
2. Gluconeogenesis: severe hyperglycaemia
3. Osmotic diuresis + acidosis: dehydration - 20clinical features of ketoacidosis- Osmotic Symptoms
- Weight Loss
- Breathlessness – Kussmaul respiration
- Abdominal pains, especially in children
- Leg cramps
- Nausea and vomiting
- Confusion - 21DKA precipitating factors- insulin omission
- infections
- new onset DM
- acute illness (MI, trauma, pancreatitis)
Steroids
CSII Pump failure
Substance abuse
Deliberate omission of Insulin dose
Eating disorder - 22Typical key losses in DKA6-8 litres of water – 100ml/kg
Sodium 500-1000
Chloride 350
Potassium 300-1000 (3-5 mmol/Kg) - 23Treatment of ketoacidosisAlways consider and treat the precipitant
Fluid: restoration of circulatory volume: crystalloid clearance of ketones: 10% dextrose
Potassium
Insulin - 24Hyperglycaemic Hyperosmolar State (HHS) - features - may proceed todecreased insulin action
- Hypovolaemia
- Very high blood glucose > 30mmol/L
- Serum osmolality >320mOsmol/l
- Bicarbonate usually > 15mmol/l
- Absence of significant ketones
May proceed to coma: watch GCS - 25Measuring osmolalityOsmolality = 2 x (Na + K) + Urea + Glu
- 26Who gets HHS? Precipitating factors?Less than 1% diabetes related admissions annually
Mortality rates 15-35%
Elderly (55-70yrs), first presentation T2DM in 30%
Insidious onset
Precipitating factors:
Infection – 60%
Poor compliance 30%
Drugs - 27Treatment of HHSTreat the precipitant
Fluid
0.9% sodium chloride
Aim for a positive fluid balance of 3-6L by 12 hours
Only switch to 0.45% sodium chloride if osmolality not falling despite
positive fluid balance
Rate of fall in sodium should not exceed 10mmol in 24 hours
Insulin
Rate of fall no more than 5mmol/L/hr
Only start when glucose not falling with fluid alone
Low dose insulin 0.05units/kg/hr
Other
LMWH
Foot protection - 28which electrolytes must be monitored in fluid replacement in DKA and HHS?DKA: potassium
HHS: sodium - 29Microvascular, foot and macrovascular complications of diabetesRetinopathy (eyes):
A leading cause of blindness in the working population in the developed world
First microvascular complication for patients with diabetes
Nephropathy (kidneys):
Will affect 30-40% of patients with diabetes;
23% of patients starting dialysis have diabetes as the primary case, but poorer survival on it
Neuropathy/foot disease:
Life-time risk for a foot ulcer is 25%
80% of non-traumatic amputations occur in patients with diabetes
Cardiovascular disease (CVD):
Increased risk of CVD
Duration of diabetes and female gender increase risk - 30cardiovascular problems in T2DM- stroke
- myocardial infarction
- hypertension
- intermittent claudication - 31Management of diabetic retinopathyAnnual photographic retinal screening with triggers for ophthalmology referral
- 32management of diabetic nephropathyAnnual monitoring of renal function and urinary albumin excretion, referral to renal team if nephropathy progesses e.g. CKD4; macroalbuminuria
- 33management of diabetic neuropathy/foot diseaseAnnual foot-screening (minimum) with risk stratification and referral to podiatry/vascular as appropriate e.g. progressive neuropathy, structural change, ischaemia
- 34management of diabetic CVDKeep BP <130/80, lower if nephropathy
Statin therapy if T2DM and age >40 regardless of DM duration and baseline cholesterol. Consider in T1DM especially if complications - 35investigations and examinations in diabetesEXAMINATION
BMI?
BP?
INVESTIGATIONS
HbA1c
Lipids
Renal function - 36pathophysiological failures contributing to hyperglycaemia (8)- impaired insulin secretion
- increased hepatic glucose production
- increased lipolysis
- decreased glucose uptake
- neurotransmitter dysfunction
- decreased incretin effect
- increased glucagon secretion
- increased glucose reabsorption - 37targeted treatment in T2DM
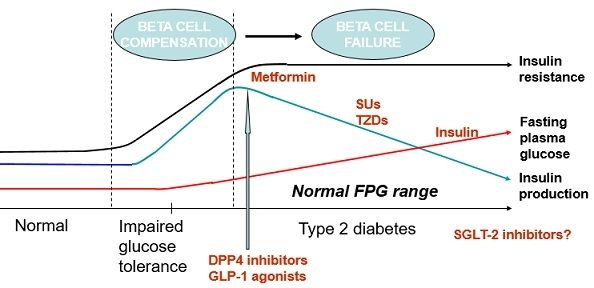
- 38limitations of older therapies- Weight gain (SU, TZD, insulin)
- Hypogylcaemia (SU, insulin)
- Concerns over CV safety (TZD)
- Concerns over cancer risks (TZD, some insulins)
- Limited options in patients with renal disease
- Natural history of disease not altered - 39Effect of incretins on insulin secretionIncretins are released after eating and augment the secretion of insulin
insulin concentration was greater following oral glucose ingestion than following IV glucose infusion, demonstrating the contribution of incretins on insulin secretion.
The incretin effect is the difference in insulin response between orally delivered and intravenously delivered glucose. - 40Which anti-diabetic drugs work throught the incretin system?GLP1(parenteral)
DPP4 (make incretin work longer)
GLP1 receptor agonists
- SE: nausea - 41SGLT 2 inhibitorsprevent kidney from reabsorbing glucose
--> glycosuria
weight loss
less efficacious in CKD - 42Who should get GLP1 receptor agonist therapy?BMI >30
in combination with oral glucose-lowering drugs or basal insulin
established CV disease - 43Metformin - drug class - mechanism - indications - SEs - contraindicationsBiguanide
Increases activity of AMP-dependent protein kinase (AMPK) --> this inhibits gluconeogenesis --> reduces insulin resistance
Indications: T2DM, PCOS
SEs: D&V, taste disturbance, lack of appetitie, risk of lactic acidosis in RF
not recommended in pregnancy or renal failure, reduced absoprtion with food - 44Gliclazide/Glimepride - drug class - mechanism - indications - SEssulphonylureas
stimulates Beta cells of the pancreas to PRODUCE MORE INSULIN --> increased cellular glucose uptake and glycogenesis, reduces gluconeogenesis
gliclazide is short-acting
for T2DM , with diet and exercise
SEs: hypoglycaemia, N&V, weight gain, indigestion, rashes
renally excreted so accumulate in renal failure - 45Exanatide/Liraglutide - drug class - mechanism - indications - SEsGLP-1 agonist - INJECTED
GLP1 is a hormone that is released after meals to increase insulin secretion. --> GLP1 agonist increases insulin secretion, decreases glucagon secretion and reduces hunger
for T2DM with excess weight
SEs: D&V, hypoglycaemia
When given in combination it can improve glucose control.
Renally excreted so dose adjustment needed in renal failure. - 46Insulin - examples - mechanism - indications - SEsNovorapid (15mins to circulation, lasts 5 hrs), Glargine (long-acting, reaches circulation in 6-12 hours, lasts 24hrs), Humalog mix (fast and intermediate)
insulin increases cellular uptake of glucose, stimulates glucogenesis, encourages DNA synthesis and promotes release of grwoth hormone
for T1DM, T2DM, hyperkalaemia (with dextrose)
SEs: hypoglycaemia (+ symptoms), oedema, injection site reactions
actarapid can be given IV - 47action of DPP4blocking the action of DPP-4, an enzyme which destroys the hormone incretin.
Incretins help the body produce more insulin only when it is needed and reduce the amount of glucose being produced by the liver when it is not needed - 48action of pioglitazonebinds to PPARy and PPARa, modulating transcription of genes involved in the control of glucose and lipid metabolism
--> reduces insulin resistance, decreases gluconeogenesis, and reduces quantity of glucose and glycated hemoglobin in the bloodstream. - 49risk fo pioglitazoneCV events and bladder cancer
Información
- Descripción
- Endocrinology Fichas sobre Treatment of diabetes, creado por Ellie Britt el 22/01/2018.
- Creado por
- Ellie Britt
- Visitas
- 18
- Valoración