
Fichas
Unit 5 - Upper Extremity
Fichas del conjunto (109)
- 1Upper extremity usually uses _____ -scale contrast.SHORT SCALE CONTRAST
high contrast
low kVp - 2What will happen when the part is not parallel to the IR?SHAPE DISTORTION
foreshortening
elongation
joint spaces closed - 3Oblique Digitfinger not parallel to IR
*should be more concave to one side*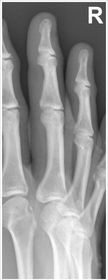
- 4Oblique Digitfinger not obliqued to 45 degrees - can't see the concavity of one side of the digit
joint spaces closed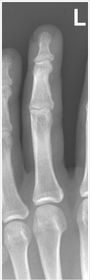
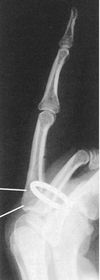
- 5Lateral Digitfinger bent back - not truly lateral
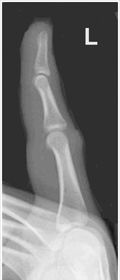
- 6Lateral Digitartifact
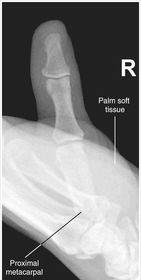
- 7AP Thumbmetacarpals overlapping thumb
- 8Oblique Thumbslightly overrotated
foreshortened distal phalanx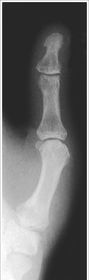
- 9Lateral Thumbsshould be concave to one side only and straight on the other
images are not truly lateral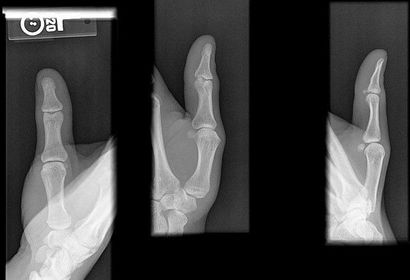
- 10PA Handdistal phalynxes are bent
flatten hand to true PA
*should be equal concavity on all digits*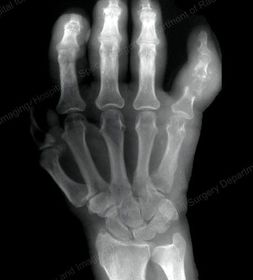
- 11PA Handobliqued - fingers are not equally concave on both sides
distal metacarpals are overlapped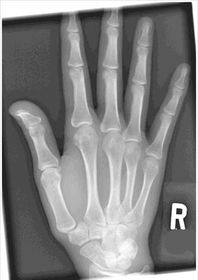
- 12Oblique HandOverly obliqued - metacarpals superimposed
joint spaces closed - fingers bent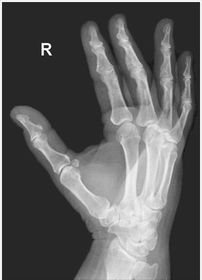
- 13Oblique HandMCP joints superimposed - fingers too close together
*underexposed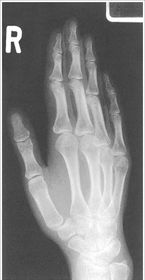
- 14Oblique Handjoint spaces closed
hand overly obliqued
MCP joints superimposed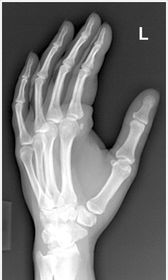
- 15Fan Lateral Handphalanges are superimposed and not well visualized
patient's hand is externally rotated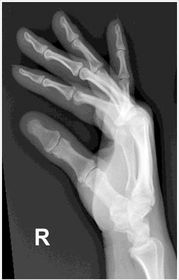
- 16Fan Lateralpatient's 2nd digit is bent - closed joint space
hand is internally rotated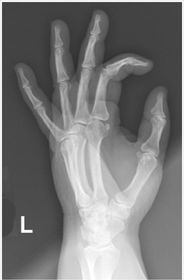
- 17Fan Lateralpatient's metacarpals are not superimposed - hand is externally rotated
distal phalanx's are bent - joint spaces closed
not truly lateral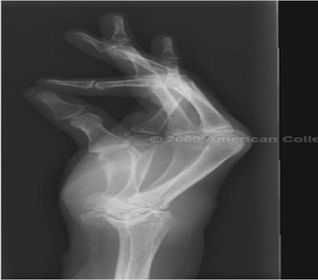
- 18PA Wristwrist externally rotated - joint spaces closed, proximal metacarpals superimposed, carpals superimposed
radiocarpal joint is closed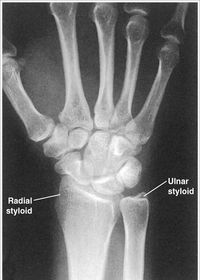
- 19Oblique Wristover rotation
radial styloid is not seen in profile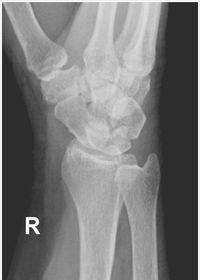
- 20Lateral Wristunder rotation - radius and ulna are not superimposed, hand is internally rotated
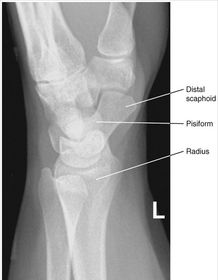
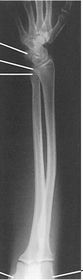
- 21AP Forearmnot AP - wrist is internally rotated, proximal radius and ulna are superimposed
- 22Lateral ForearmElbow is not 90 degrees
proximal radius and ulna are superimposed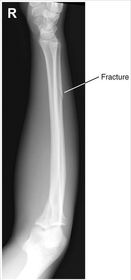
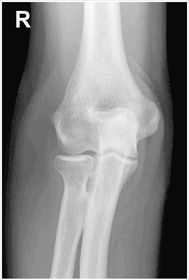
- 23AP Elbowhumerus is externally rotated because the epicondyles are not in profile
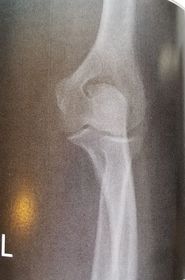
- 24AP Oblique Elbow Internal RotationInsufficient obliquity
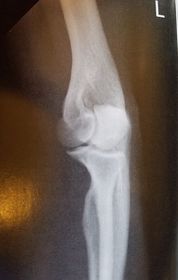
- 25AP Oblique Elbow Internal RotationExcessive obliquity
- 26AP Oblique Elbow External Rotationforearm is not parallel to IR
capitulum-radial joint is closed
olecranon is not in the fossa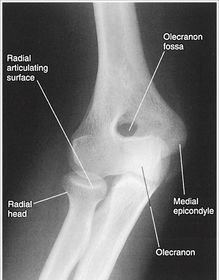
- 27AP Oblique Elbow External RotationUnderrotation
distal forearm slightly elevated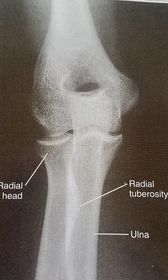
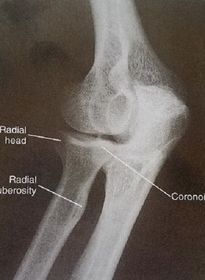
- 28AP Oblique Elbow External RotationOverrotation
- 29Lateral ElbowThe elbow is elevated above the level of the shoulder
radial head anterior to coronoid - should be superimposed
capitulum too proximal to trochlea
radial tuberosity seen - hand is pronated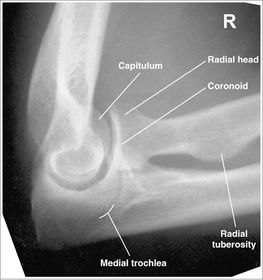
- 30Lateral ElbowElbow is depressed below the level of the shoulder
radial head superimposed by coronoid
capitulum too distal to medial trochlea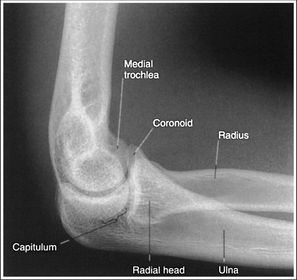
- 31Lateral Elbowthe distal wrist is elevated
hand is pronated because you can see the radial tuberosity - should not see that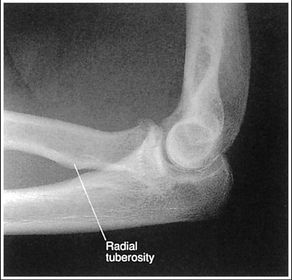
- 32AP Humerushumeral epicodyles not in profile
radial head, neck and tuberosity to not superimpose ulna
arm is externally rotated (greater tubercle in profile)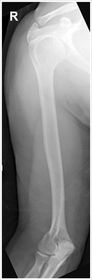
- 33Lateral Humerusover rotation places the humeral head within the field of the chest
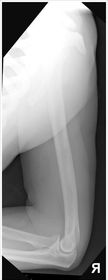
- 34Lateral Humerusepicondyles are not perpendicular
humerus is internally rotated (lesser tubercle is in profile medially)
overrotation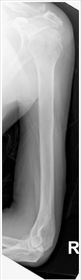
- 35AP Shoulder internal rotationthe MCP is tilted posteriorly as marked by the superior scapular angle is inferior to the clavicle
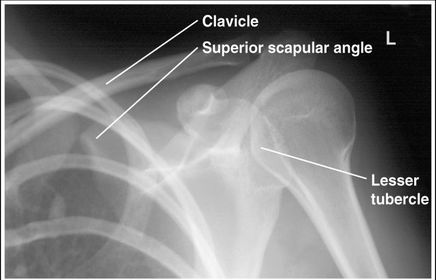
- 36AP Shoulderpatient is rotated towards the unaffected shoulder:
decreased thoracic superimposition over the scapular body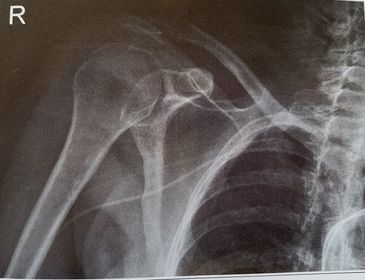
- 37AP Shoulderpatient is rotated towards affected side:increased thoracic superimposition over the scapular body
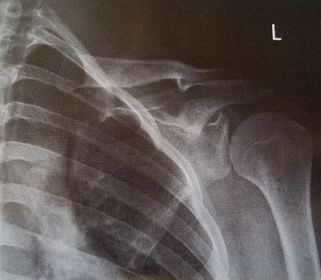
- 38Inferosuperior Axiolateral Shoulderhumerus is foreshortened - humeral head is distorted
arm is not abducted 90 degrees from body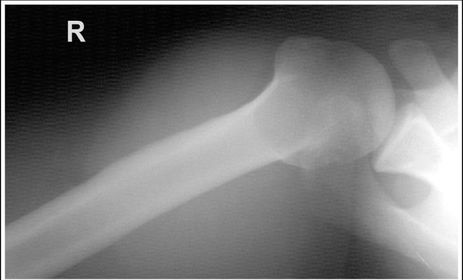
- 39GrasheyInsufficient obliquity
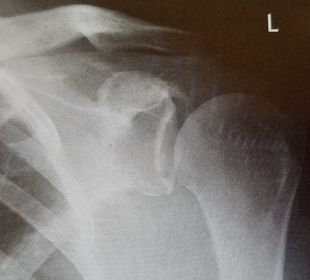
- 40GrasheyExcessive obliquity
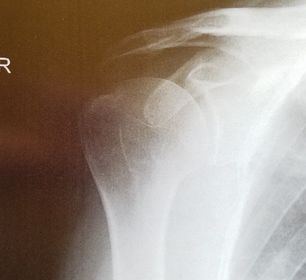
- 41GrasheyMCP is tilted posteriorly
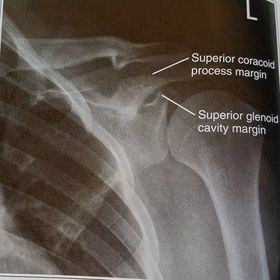
- 42PA Oblique Scapular Y-LateralExcessive Obliquity
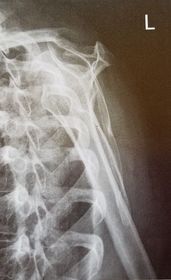
- 43PA Oblique Scapular Y-LateralInsufficient Obliquity
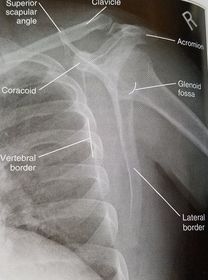
- 44PA Oblique Scapular Y-LateralMCP is tilted anteriorly
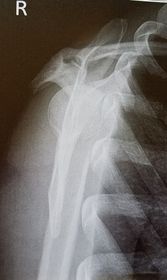
- 45PA Oblique Scapular Y-LateralMCP is tilted posteriorly
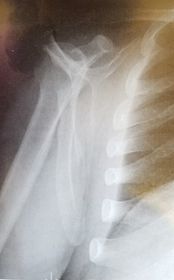
- 46AP ClavicleMCP is tilted anteriorly
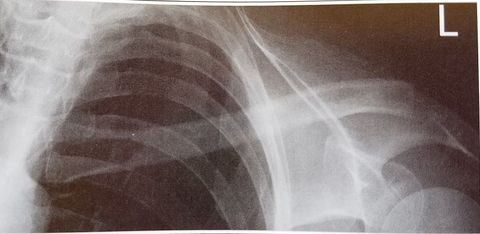
- 47AP ClavicleMCP is tilted posteriorly
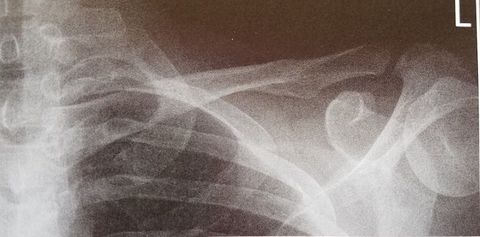
- 48AP ClaviclePatient is rotated towards affected shoulder
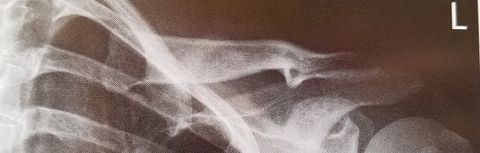
- 49AP ClaviclePatient is rotated towards unaffected shoulder
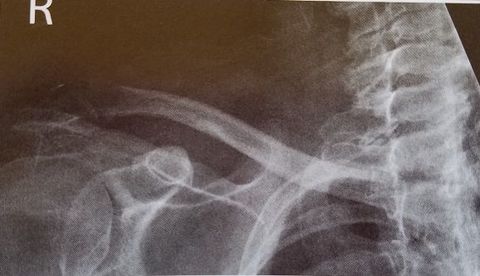
- 50AP AC Joints UnilateralMCP tilted anteriorly
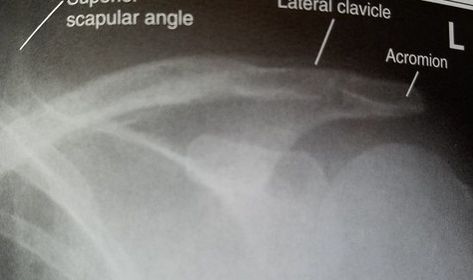
- 51AP Scapulaarm is not abducted so scapula is hidden behind the thorax
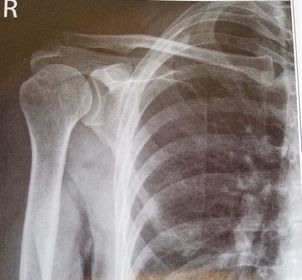
- 52Lateral ScapulaInsufficient obliquity
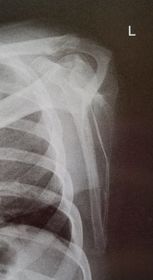
- 53Lateral ScapulaExcessive Obliquity
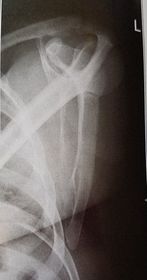
- 54Oblique Sternumprojection taken as LAO instead of RAO
sternum is projected within the heart and scapula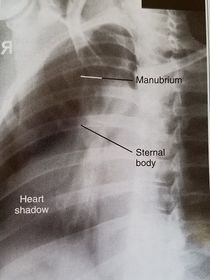
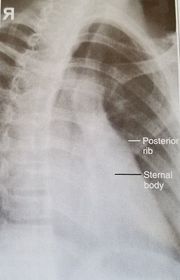
- 55RAO Sternuminadequate breathing technique
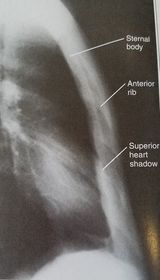
- 56Lateral Sternumpatient's left thorax is rotated anteriorly
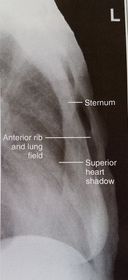
- 57Lateral Sternumpatient's right thorax is rotated anteriorly
- 58PA Ribs Above Diaphragm Unilateralpatient rotated towards the right
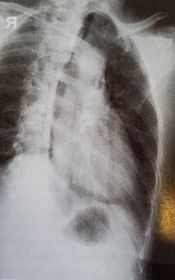
- 59PA Ribs Below Diaphragm UnilateralExcessive obliquity
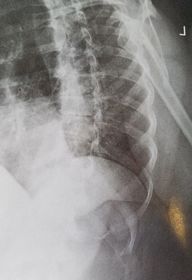
- 60AP - LPO Ribs Above Diaphragm UnilateralInsufficient obliquity
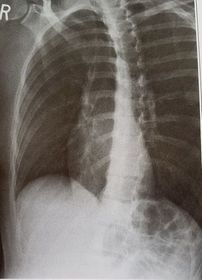
- 61—Left thorax is more anterior
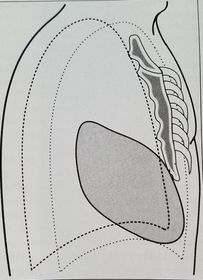
- 62—Right thorax is more anterior
- 63What's the evaluation criteria for the PA Finger X-Ray?ANATOMY:
distal phalynx -> distal 1/2 of metacarpal demonstrated
CRITERIA:
- equal concavity on both sides of phalanges
- IP and MCP open
- no overlapping of adjacent fingers
POSITIONING:
CR perpendicular @ PIP joint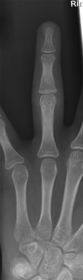
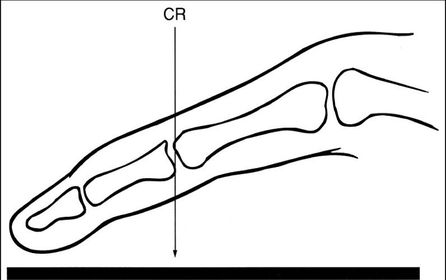
- 64What's the evaluation criteria for the Lateral finger x-ray?ANATOMY:
entire digit demonstrated
CRITERIA:
open joint spaces
concave to one side, while the dorsal side is straight
no overlapping of adjacent fingers/soft tissues
POSITIONING:
CR perpendicular @ PIP joint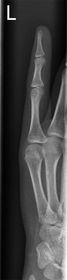
- 65Oblique finger x-ray image criteria?ANATOMY:
entire digit demonstrated
CRITERIA:
more concavity to one side
open joint spaces
no superimposition of adjacent fingers
POSITIONING:
CR perpendicular @ PIP joint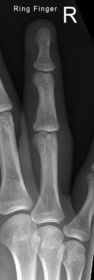
- 66AP Thumb CriteriaANATOMY:
entire digit including trapezium
CRITERIA:
equal concavity on both sides of digit
open joint spaces
no superimposition from adjacent bones
POSITIONING:
CR perpendicular @ 1st MCP joint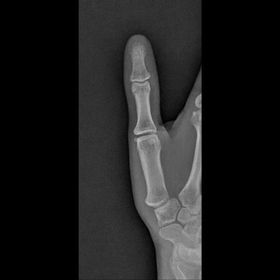
- 67Oblique ThumbANATOMY:
entire digit including trapezium
CRITERIA:
more concave to the side farthest from IR
open joint spaces
no superimposition from adjacent bones
POSITIONING:
CR perpendicular @ 1st MCP joint
- 68Lateral ThumbANATOMY:
entire digit including trapezium
CRITERIA:
most concave to one side, while the other is straight
open joint spaces
no superimposition from adjacent bones
POSITIONING:
CR perpendicular @ 1st MCP joint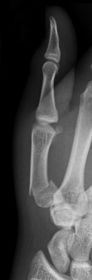
- 69PA HandANATOMY:
entire hand including 1'' of distal radius and ulna
CRITERIA:
equal concavity on either side of digits
digits separated with no superimposition
open joint spaces
POSITIONING:
CR perpendicular @ 3rd MCP joint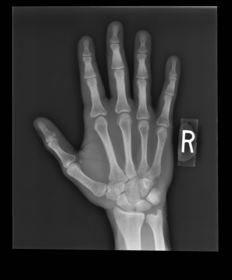
- 70Oblique HandANATOMY:
entire hand including 1'' of distal radius and ulna
CRITERIA:
digits more concave to one side
minimal overlap of 3rd-5th metacarpal shafts
separation of the 2nd and 3rd metacarpals
POSITIONING:
CR perpendicular @ 3rd MCP joint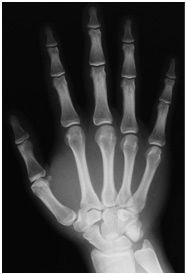
- 71Lateral HandANATOMY:
entire hand including distal 1'' of radius and ulna superimposed
CRITERIA:
metacarpals and distal radius/ulna are superimposed
thumb is free of superimposition
*thumb in lateral position*
open joint spaces
POSITIONING:
CR perpendicular @ 3rd MCP joint
LAT Extension: foreign body localization
LAT Flexion: phalanges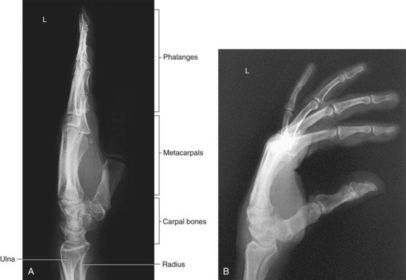
- 72PA WristANATOMY:
all carpals including midmetacarpals and distal radius/ulna
CRITERIA:
true PA is marked by symmetry of proximal metacarpals
carpals should be free of superimposition of the metacarpals and radius/ulna
POSITIONING:
CR perpendicular @ midcarpals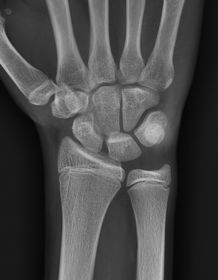
- 73Oblique WristANATOMY:
carpals on lateral side of wrist, scaphoid
CRITERIA:
scaphoid well demonstrated
45 degree obliquity
POSITIONING:
CR perpendicular @ midcarpals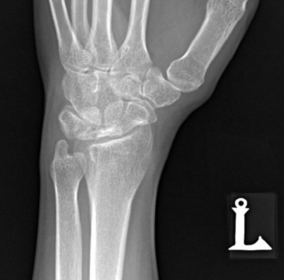
- 74LCRITERIA:
radius/ulna should be superimposed
thumb should be forward
metacarpals superimposed
POSITIONING:
CR perpendicular @ midcarpals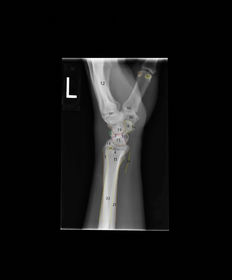
- 75AP ForearmANATOMY:
entire forearm: wrist joint -> elbow joint
CRITERIA:
slight superimposition of proximal radius/ulna
POSITIONING:
CR perpendicular @ midforearm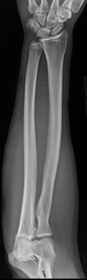
- 76Lateral ForearmANATOMY:
entire forearm including wrist joint and elbow joint
CRITERIA:
humeral epicondyles must be superimposed
distal radius/ulna superimposed
half of radial head superimposed by coronoid process
olecranon process in profile
POSITIONING:
CR perpendicular @ midforearm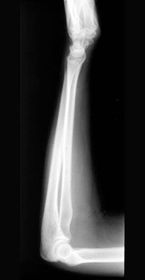
- 77AP ElbowANATOMY:
distal humerus - proximal forearm
CRITERIA:
slight superimposition of proximal radius/ulna
humeral epicondyles in profile
open joint space
POSITIONING:
CR perpendicular @ midelbow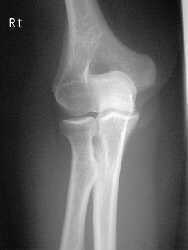
- 78Medial Oblique ElbowANATOMY:
proximal radius/ulna, distal humerus, medial epicondyle and trochlea
CRITERIA:
coronoid process in profile
radial head and neck should superimpose the ulna
olecranon process seen within olecranon fossa
POSITIONING:
CR perpendicular @ midelbow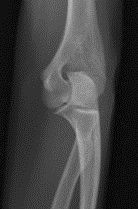
- 79Lateral Oblique ElbowANATOMY:
open joint space, radial head, neck, tuberosity, and capitulum
CRITERIA:
radial head, neck, and tuberosity are free of superimposition
humeral epicondyles and capitulum in profile
POSITIONING:
CR perpendicular @ midelbow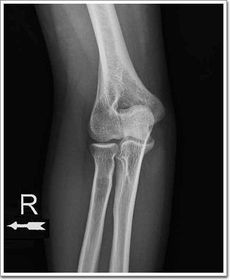
- 80Lateral Elbow Evaluation CriteriaANATOMY:
distal humerus, proximal forearm, entire elbow joint
CRITERIA:
humeral epicondyles are superimposed
radial tuberosity is invisible (if visible the hand is pronated)
half of the radial head superimposed by coronoid process
Elbow is flexed 90 degrees to see/not see fad pads
3 concentric arcs visible
POSITIONING:
CR perpendicular @ lateral epicondyle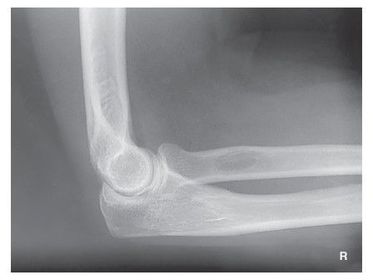
- 81AP HumerusANATOMY:
entire humerus: shoulder -> elbow
CRITERIA:
greater tubercle in profile - hand externally rotated
humeral epicondyles are parallel to IR
POSITIONING:
CR perpendicular @ midhumerus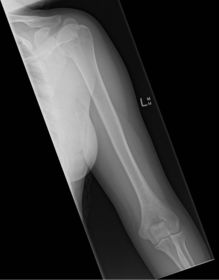
- 82Lateral HumerusANATOMY:
entire humerus: shoulder -> elbow
CRITERIA:
lesser tubercle in profile - arm internally rotated
epicondyles superimposed
POSITIONING:
pt rotated 15-20 degrees from PA to get arm lateral and away from chest - flex elbow 90 degrees
CR perpendicular @ midhumerus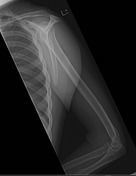
- 83AP Shoulder NeutralANATOMY:
proximal humerus, lateral 2/3 of clavicle, open shoulder joint
CRITERIA:
humeral epicondyles are 45 degrees to the IR
neither tubercle should be seen on the humeral head
POSITIONING:
CR perpendicular @ 1'' inferior to coracoid process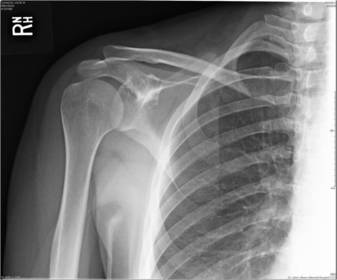
- 84AP Shoulder Internal RotationCRITERIA:
lesser tubercle in profile medially
POSITIONING:
CR perpendicular @ 1'' inferior to coracoid process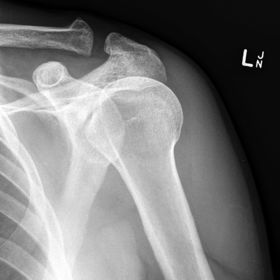
- 85AP Shoulder External RotationCRITERIA:
greater tubercle in profile laterally
POSITIONING:
CR perpendicular @ 1'' inferior to coracoid process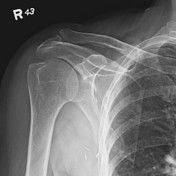
- 86Scapular Y-LateralANATOMY:
humeral head resting in the 'Y' of the acromion and coracoid process
CRITERIA:
vertebral border and lateral border of scapula are directly superimposed
humeral head is aligned with body of scapula
POSITIONING:
pt's unaffected arm is abducted 90 degrees, pt in 45-60 degree anterior oblique
CR perpendicular @ scapulohumeral joint
(neer) CR angled 10-15 degrees caudal @ scapulohumeral joint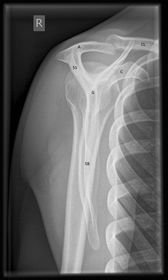
- 87Inferosuperior Axial ShoulderANATOMY:
lateral view of the proximal humerus in relation to the glenoid fossa
CRITERIA:
lesser tubercle in profile medially
humeral head is in the center of VOI
POSITIONING:
affected arm abducted 90 degrees, hand rotated externally with hand supinated
CR horizontal 25-30 degrees medial to the scapulohumeral joint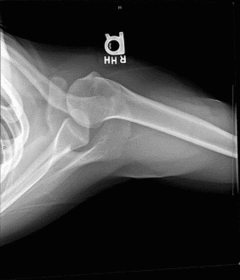
- 88Posterior Oblique GrasheyANATOMY:
glenoid cavity in profile
glenohumeral joint center of VOI
CRITERIA:
open glenoid cavity
anterior/posterior rims of glenoid cavity are superimposed
POSITIONING:
pt in 35-40 degree posterior oblique
CR perpendicular @ glenoid cavity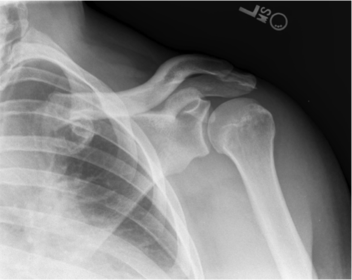
- 89AP ClavicleANATOMY:
entire clavicle with both AC and SC joints included
CRITERIA:
entire clavicle and acromion are included
lateral clavicle bows up, while the medial clavicle is superimposed by ribs 2-3
POSITIONING:
CR perpendicular @ midclavicle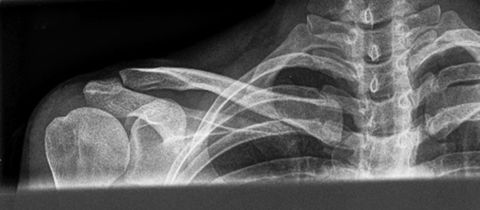
- 90AP Axial ClavicleANATOMY:
entire clavicle and both joints included
CRITERIA:
clavicle is more horizontal, and projected above the scapula and ribs
medial end may be superimposed by ribs
POSITIONING:
CR angled 15-30 degrees cephalic @ midclavicle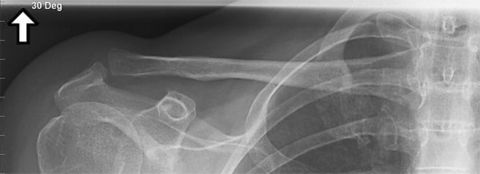
- 91AC JointsANATOMY:
Bilateral AC joints included and open
CRITERIA:
non weight bearing and weight bearing projections marked correctly
both joints included
lateral clavicle almost horizontal
POSITIONING:
CR perpendicular @ jugular notch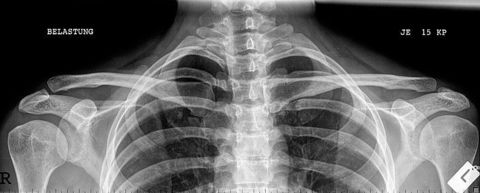
- 92AP ScapulaANATOMY:
entire scapula
midscapula center of VOI
CRITERIA:
lateral border seen without superimposition of thorax
humerus abducted 90 degrees
POSITIONING:
CR perpendicular @ midscapula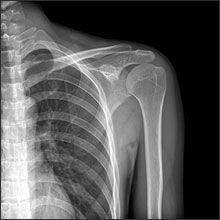
- 93Lateral ScapulaANATOMY:
entire scapula
CRITERIA:
vertebral border and lateral border directly superimposed
humerus abducted to view scapular body
POSITIONING:
45-60 degree oblique (to get scapula perpendicular to IR)
CR perpendicular to midscapular body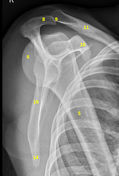
- 94RAO SternumANATOMY:
jugular notch, SC joints, sternal body, and xiphoid process
CRITERIA:
sternum projected within heart shadow next to vertebral column
POSITIONING:
pt. rotated 15-20 degrees
breathing technique
CR perpendicular @ midsternum (2 fingers off downside spine)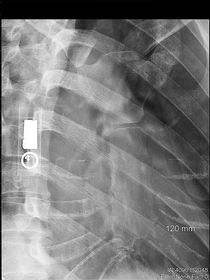
- 95Lateral SternumANATOMY:
manubrium, sternal body, and xiphoid in profile
CRITERIA:
72'' SID reduces OID
arms must be behind pt's back
POSITIONING:
CR perpendicular @ midsternum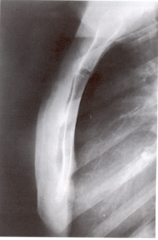
- 96AP/PA RibsANATOMY:
all ribs demonstrated
1-9 for upper
8-12 for lower
CRITERIA:
no motion/breathing
POSITIONING:
AP ribs when pt c/o posterior pain
PA ribs when pt c/o anterior pain
CR perpendicular @ T7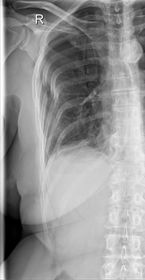
- 97Oblique RibsCRITERIA:
45 degree oblique will shift spine away from anatomy of interest
LPO/RAO = left axillary ribs
RPO/LAO = right axillary ribs
ribs 1-9 are seen on above diaphragm projections
ribs 8-12 see on below diaphragm projections
CR perpendicular @ T7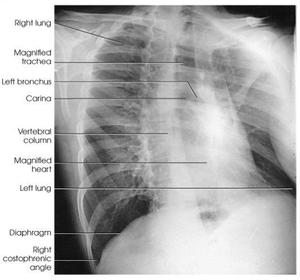
- 98with digital, if the mAs is too high your image will appearbrightness appropriate
- 99with digital, if the IR is not exposed to enough radiationimage brightness will be appropriate
quantum noise will be visible - 100increasing tube filtration will ___increase beam energy and decrease radiographic contrast
- 101casts made of fiberglass require ______ in exposure factorsno change
- 102to see soft tissues with DR, the standard exposure factors should be ______left the same because you can change window level to see tissues
- 103Increasing SID will have what effect on your image?will be sharper
- 104what will happen to the contrast if the atomic number of the structure is increased?contrast will increase due to increased absorption
- 105When using the AEC, the RT must set the ____kVp
- 106a higher kVp on an AEC exam results in ____shorter exposure time
- 107When using AEC, what is the most critical aspect of performing the exam?centering the anatomy of interest over the detector
- 108what is a grid ratio?the height of the lead strips inside the grid vs. the space between them
- 109When you apply a grid during an exam what will happen to your contrast?employing a grid will result in higher contrast in your image because less scatter is reaching the IR
Información
- Descripción
- ARRT Image Evaluation Fichas sobre Unit 5 - Upper Extremity, creado por RadTech Fairy el 27/02/2017.
- Creado por
- RadTech Fairy
- Visitas
- 428
- Valoración