
Apuntes
SURGERY CBL 3 UPPER LIMB FRACTURES
Contenido del apunte (2)
Página 1
UPPER LIMB FRACTURES CBL
Osteoporotic fractures: occur with minimal trauma
Pathological fractures: no trauma
Stress fractures: due to prolonged unaccustomed activity but no trauma
ANATOMY: outer envelope is cortical bone while inner core is cancellous bone
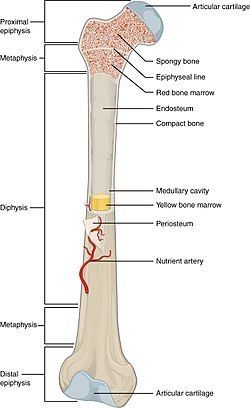
:::::::::::::::::::::::::::: humerus ::::::::::::::::::::::::
ANATOMY
muscle insertion for pec major, deltoid and corachobrachialis
muscle origin for brachialis, biceps and brachioradialis
median + ulnar nerve run along shaft while radial nerve is in spiral groove in between proximal and medial epicondyle
MODE OF INJURY
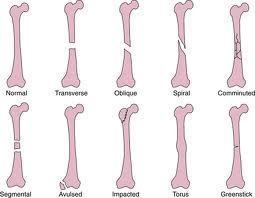
direct trauma usually a transverse fracture
indirect trauma usually spiral fracture
fall on outstretched hand: high velocity comminuted fractures
minimal trauma: pathological fractures in elderly
fractures mostly in middle third (60%)
Investigations: XR, MR/bone scan (pathological fractures), calcium levels
Initial mgt: pain relief, splint, x-ray exam, temporary splintage
definitve mgt: sugar tong humeral brace and regular XRs
conservative mgt: fn-al brace for shaft fractures
indications for surgery: open fracture, neurovascular injury, segmental fractures, polytrauma, floating elbow, floating shoulder, adequate alignment
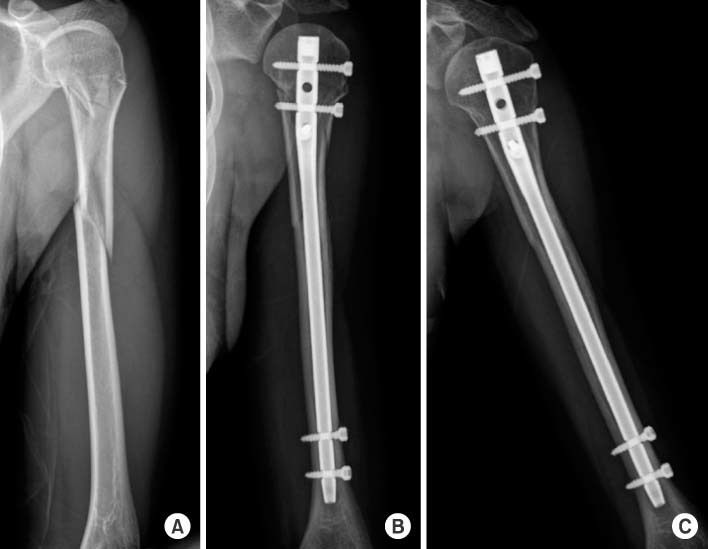
INTRAMEDULLARY NAILING
anterograde/retrograde**
indicated in patho, segmental and osteoporotic fractures
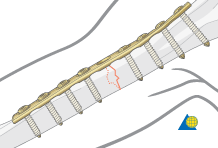
COMPRESSION PLATING
method of choice for fixing fractures
better union rate and lower complication rate compared with nailing
COMPLICATIONS OF SURGERY (definite): infection, delayed/non union, nerve damage (radial nerve palsy)
most humeral fractures treated conservatively
radial nerve involvement should be checked
90% heal well
Página 2
hand and wrist fractures
COLLES FRACTURE
#1 distal radius fracture
FOOSH
#1 in older women due to osteoprosis
on XR consider: angulation, impaction, displacement, joint involvement, other fractures (ulnar styloid, carpal bones)
MGT
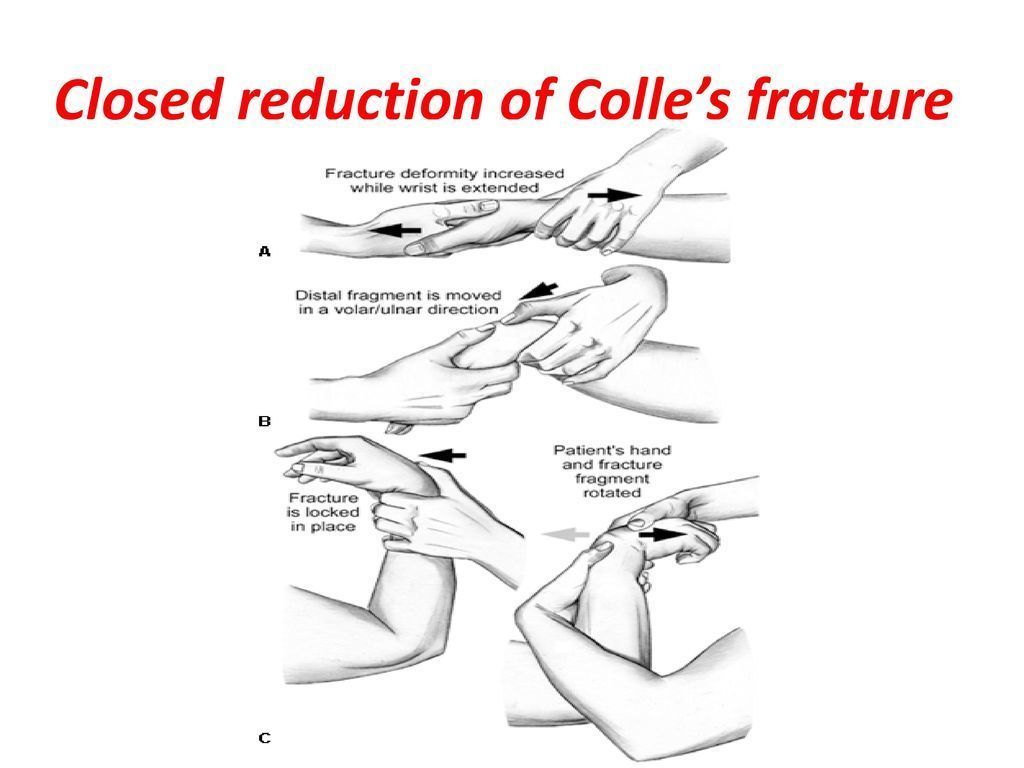
conservative: with closed reduction (immediate in neurovascular damage) and plaster cast immobilisation,
surgical: open plating, external fixation, closed manipulation
COMPLICATIONS: malunion w/ dinner fork deformity, median nerve palsy, carpal tunnel
SCAPHOID FRACTURES
#1 carpal fracture
15-30y males
caused by FOOSH or forced dorsiflexion (steering wheel)
CFs: tenderness in anatomical snuffbox, scaphoid tubercle and longitudinal compression of scaphoid
Investigations: scaphoid series (3/4 plain X-Rays), 2nd line is MRI
Dx is difficult with XR
MGT:
Immobilise in plaster cast
Follow-up
internal fixation (screw/wire) to reduce risk of complication
bone grafting potentially for non union
Comps: non/mal union, OA, scapho-lunate dissociation, avascular necrosis
BOXER'S FRACTURE
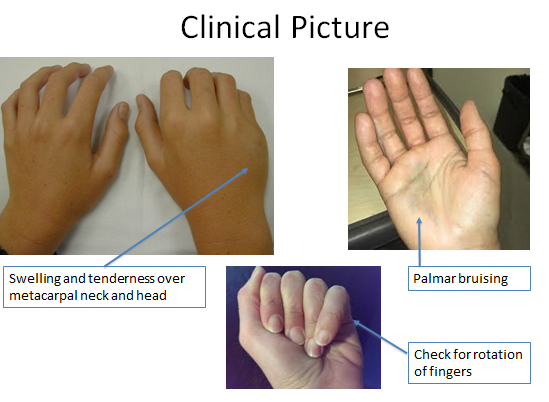
- #1 metacarpal fracture: 5th metacarpal neck with volar (palmar) displacement
- usually after a punch
- MGT: check for other injuries, abx for open wounds, most will heal with minimal immobilisation/splintage, may require operative fixation with percutaneous wires.
Información
- Descripción
- Surgery Apunte sobre SURGERY CBL 3 UPPER LIMB FRACTURES, creado por Omolade Abidoye el 06/11/2018.
- Creado por
- Omolade Abidoye · nov 2018
- Actualizado
- 7 nov 2018
- Visitas
- 301
- Etiquetas
- Valoración