
Mind map
DIABETES MELLITUS
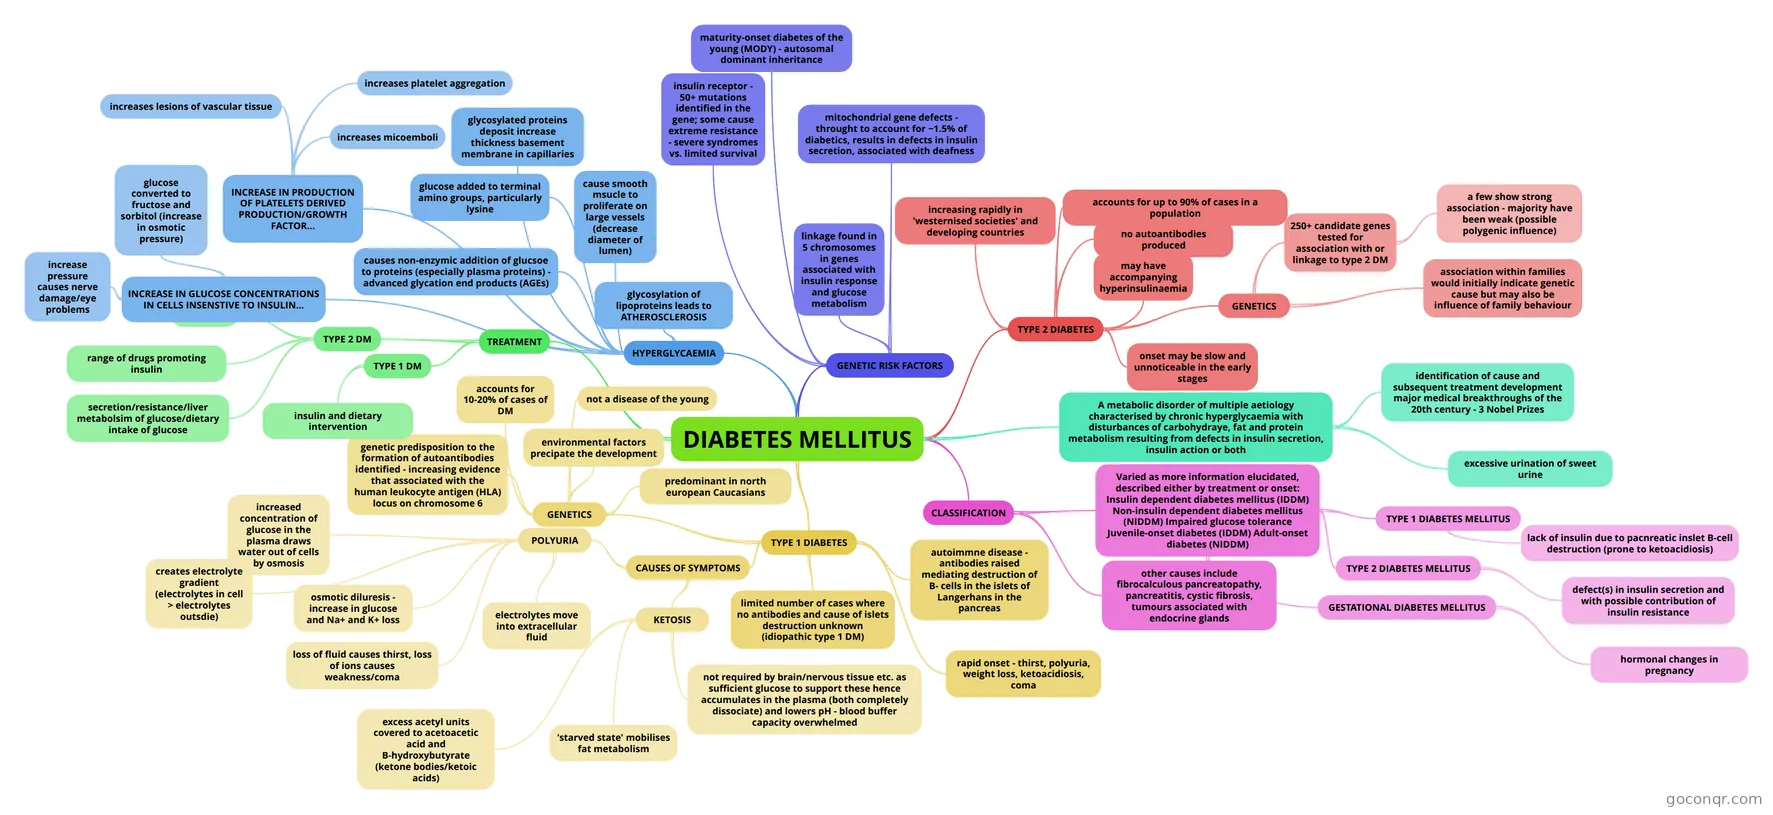
Mind map: Diabetes mellitus
Map content
DIABETES MELLITUS
A metabolic disorder of multiple aetiology characterised by chronic hyperglycaemia with disturbances of carbohydraye, fat and protein metabolism resulting from defects in insulin secretion, insulin action or both
- excessive urination of sweet urine
- identification of cause and subsequent treatment development major medical breakthroughs of the 20th century - 3 Nobel Prizes
CLASSIFICATION
- Varied as more information elucidated, described either by treatment or onset: Insulin dependent diabetes mellitus (IDDM) Non-insulin dependent diabetes mellitus (NIDDM) Impaired glucose tolerance Juvenile-onset diabetes (IDDM) Adult-onset diabetes (NIDDM)
- TYPE 1 DIABETES MELLITUS
- lack of insulin due to pacnreatic inslet B-cell destruction (prone to ketoacidiosis)
- TYPE 2 DIABETES MELLITUS
- defect(s) in insulin secretion and with possible contribution of insulin resistance
- GESTATIONAL DIABETES MELLITUS
- hormonal changes in pregnancy
- TYPE 1 DIABETES MELLITUS
- other causes include fibrocalculous pancreatopathy, pancreatitis, cystic fibrosis, tumours associated with endocrine glands
- Varied as more information elucidated, described either by treatment or onset: Insulin dependent diabetes mellitus (IDDM) Non-insulin dependent diabetes mellitus (NIDDM) Impaired glucose tolerance Juvenile-onset diabetes (IDDM) Adult-onset diabetes (NIDDM)
TYPE 1 DIABETES
- autoimmne disease - antibodies raised mediating destruction of B- cells in the islets of Langerhans in the pancreas
- limited number of cases where no antibodies and cause of islets destruction unknown (idiopathic type 1 DM)
- rapid onset - thirst, polyuria, weight loss, ketoacidiosis, coma
- CAUSES OF SYMPTOMS
- POLYURIA
- increased concentration of glucose in the plasma draws water out of cells by osmosis
- creates electrolyte gradient (electrolytes in cell > electrolytes outsdie)
- electrolytes move into extracellular fluid
- osmotic diluresis - increase in glucose and Na+ and K+ loss
- loss of fluid causes thirst, loss of ions causes weakness/coma
- KETOSIS
- 'starved state' mobilises fat metabolism
- excess acetyl units covered to acetoacetic acid and B-hydroxybutyrate (ketone bodies/ketoic acids)
- not required by brain/nervous tissue etc. as sufficient glucose to support these hence accumulates in the plasma (both completely dissociate) and lowers pH - blood buffer capacity overwhelmed
- POLYURIA
- GENETICS
- predominant in north european Caucasians
- genetic predisposition to the formation of autoantibodies identified - increasing evidence that associated with the human leukocyte antigen (HLA) locus on chromosome 6
- environmental factors precipate the development
- not a disease of the young
- accounts for 10-20% of cases of DM
TYPE 2 DIABETES
- accounts for up to 90% of cases in a population
- increasing rapidly in 'westernised societies' and developing countries
- no autoantibodies produced
- may have accompanying hyperinsulinaemia
- onset may be slow and unnoticeable in the early stages
- GENETICS
- 250+ candidate genes tested for association with or linkage to type 2 DM
- a few show strong association - majority have been weak (possible polygenic influence)
- association within families would initially indicate genetic cause but may also be influence of family behaviour
- 250+ candidate genes tested for association with or linkage to type 2 DM
GENETIC RISK FACTORS
- maturity-onset diabetes of the young (MODY) - autosomal dominant inheritance
- linkage found in 5 chromosomes in genes associated with insulin response and glucose metabolism
- insulin receptor - 50+ mutations identified in the gene; some cause extreme resistance - severe syndromes vs. limited survival
- mitochondrial gene defects - throught to account for ~1.5% of diabetics, results in defects in insulin secretion, associated with deafness
HYPERGLYCAEMIA
- causes non-enzymic addition of glucsoe to proteins (especially plasma proteins) - advanced glycation end products (AGEs)
- glucose added to terminal amino groups, particularly lysine
- glycosylated proteins deposit increase thickness basement membrane in capillaries
- cause smooth msucle to proliferate on large vessels (decrease diameter of lumen)
- glycosylation of lipoproteins leads to ATHEROSCLEROSIS
- INCREASE IN GLUCOSE CONCENTRATIONS IN CELLS INSENSTIVE TO INSULIN...
- glucose converted to fructose and sorbitol (increase in osmotic pressure)
- increase pressure causes nerve damage/eye problems
- INCREASE IN PRODUCTION OF PLATELETS DERIVED PRODUCTION/GROWTH FACTOR...
- increases platelet aggregation
- increases micoemboli
- increases lesions of vascular tissue
TREATMENT
- TYPE 1 DM
- insulin and dietary intervention
- TYPE 2 DM
- lifestyle
- range of drugs promoting insulin
- secretion/resistance/liver metabolsim of glucose/dietary intake of glucose
- TYPE 1 DM
Information
- Description
- Mind Map on DIABETES MELLITUS, created by misbah.baig1993 on 18/04/2014.
- Created by
- misbah.baig1993
- Views
- 27
- Rating