
Mapa mental
proteinuria
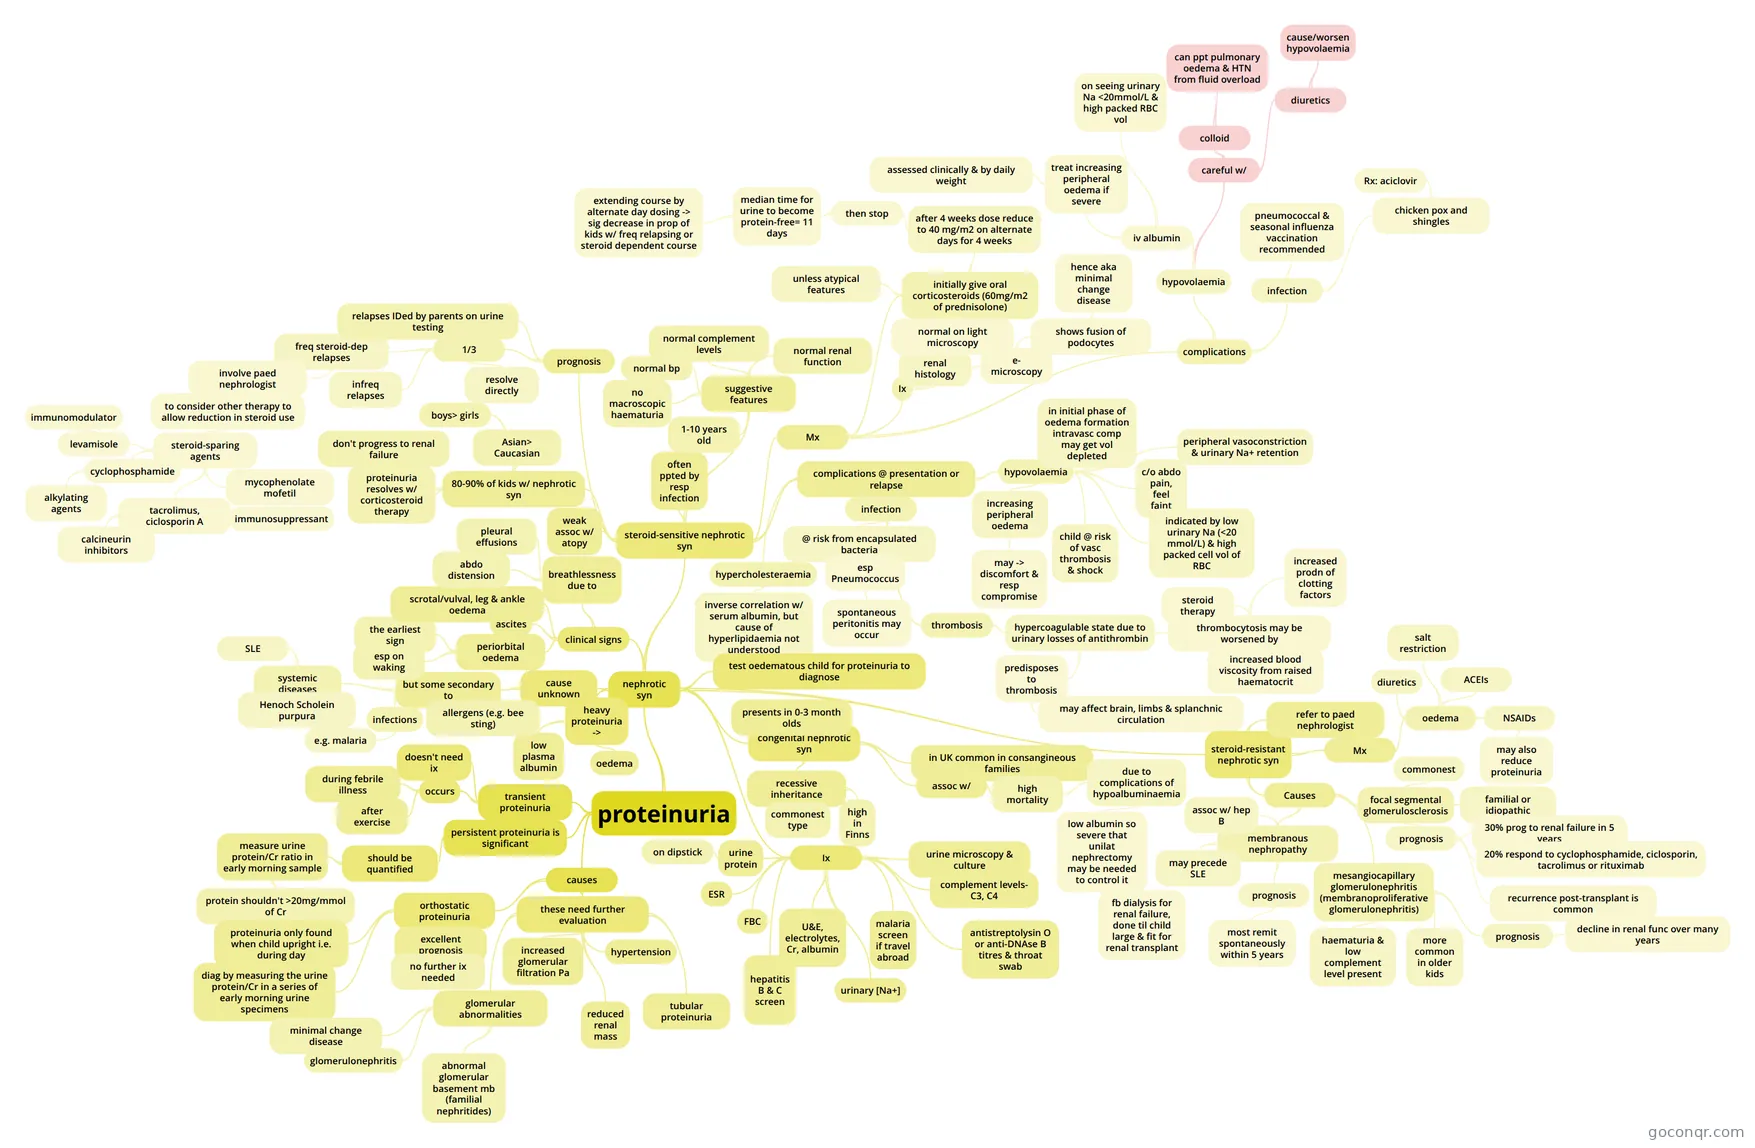
Mind map: proteinuria
Conteúdo do mapa
proteinuria
transient proteinuria
- occurs
- during febrile illness
- after exercise
- doesn't need ix
- occurs
persistent proteinuria is significant
- should be quantified
- measure urine protein/Cr ratio in early morning sample
- protein shouldn't >20mg/mmol of Cr
- measure urine protein/Cr ratio in early morning sample
- should be quantified
causes
- orthostatic proteinuria
- proteinuria only found when child upright i.e. during day
- diag by measuring the urine protein/Cr in a series of early morning urine specimens
- excellent prognosis
- no further ix needed
- these need further evaluation
- glomerular abnormalities
- minimal change disease
- glomerulonephritis
- abnormal glomerular basement mb (familial nephritides)
- increased glomerular filtration Pa
- reduced renal mass
- hypertension
- tubular proteinuria
- glomerular abnormalities
- orthostatic proteinuria
nephrotic syn
- heavy proteinuria ->
- low plasma albumin
- oedema
- cause unknown
- but some secondary to
- systemic diseases
- Henoch Scholein purpura
- SLE
- infections
- e.g. malaria
- allergens (e.g. bee sting)
- systemic diseases
- but some secondary to
- clinical signs
- periorbital oedema
- esp on waking
- the earliest sign
- scrotal/vulval, leg & ankle oedema
- ascites
- breathlessness due to
- pleural effusions
- abdo distension
- periorbital oedema
- steroid-sensitive nephrotic syn
- 80-90% of kids w/ nephrotic syn
- proteinuria resolves w/ corticosteroid therapy
- don't progress to renal failure
- boys> girls
- Asian> Caucasian
- weak assoc w/ atopy
- often ppted by resp infection
- suggestive features
- 1-10 years old
- no macroscopic haematuria
- normal bp
- normal complement levels
- normal renal function
- Mx
- initially give oral corticosteroids (60mg/m2 of prednisolone)
- unless atypical features
- after 4 weeks dose reduce to 40 mg/m2 on alternate days for 4 weeks
- then stop
- median time for urine to become protein-free= 11 days
- extending course by alternate day dosing -> sig decrease in prop of kids w/ freq relapsing or steroid dependent course
- median time for urine to become protein-free= 11 days
- then stop
- Ix
- renal histology
- normal on light microscopy
- e- microscopy
- shows fusion of podocytes
- hence aka minimal change disease
- shows fusion of podocytes
- renal histology
- complications
- hypovolaemia
- iv albumin
- treat increasing peripheral oedema if severe
- assessed clinically & by daily weight
- on seeing urinary Na <20mmol/L & high packed RBC vol
- treat increasing peripheral oedema if severe
- careful w/
- colloid
- can ppt pulmonary oedema & HTN from fluid overload
- diuretics
- cause/worsen hypovolaemia
- colloid
- iv albumin
- infection
- pneumococcal & seasonal influenza vaccination recommended
- chicken pox and shingles
- Rx: aciclovir
- hypovolaemia
- initially give oral corticosteroids (60mg/m2 of prednisolone)
- complications @ presentation or relapse
- hypovolaemia
- in initial phase of oedema formation intravasc comp may get vol depleted
- c/o abdo pain, feel faint
- peripheral vasoconstriction & urinary Na+ retention
- indicated by low urinary Na (<20 mmol/L) & high packed cell vol of RBC
- child @ risk of vasc thrombosis & shock
- increasing peripheral oedema
- may -> discomfort & resp compromise
- thrombosis
- hypercoagulable state due to urinary losses of antithrombin
- thrombocytosis may be worsened by
- steroid therapy
- increased prodn of clotting factors
- increased blood viscosity from raised haematocrit
- predisposes to thrombosis
- may affect brain, limbs & splanchnic circulation
- thrombocytosis may be worsened by
- hypercoagulable state due to urinary losses of antithrombin
- infection
- @ risk from encapsulated bacteria
- esp Pneumococcus
- spontaneous peritonitis may occur
- esp Pneumococcus
- @ risk from encapsulated bacteria
- hypercholesteraemia
- inverse correlation w/ serum albumin, but cause of hyperlipidaemia not understood
- hypovolaemia
- prognosis
- 1/3
- resolve directly
- infreq relapses
- freq steroid-dep relapses
- involve paed nephrologist
- to consider other therapy to allow reduction in steroid use
- steroid-sparing agents
- levamisole
- immunomodulator
- cyclophosphamide
- alkylating agents
- tacrolimus, ciclosporin A
- calcineurin inhibitors
- mycophenolate mofetil
- immunosuppressant
- levamisole
- steroid-sparing agents
- to consider other therapy to allow reduction in steroid use
- involve paed nephrologist
- relapses IDed by parents on urine testing
- 1/3
- 80-90% of kids w/ nephrotic syn
- Ix
- urine protein
- on dipstick
- FBC
- ESR
- U&E, electrolytes, Cr, albumin
- complement levels- C3, C4
- antistreptolysin O or anti-DNAse B titres & throat swab
- urine microscopy & culture
- urinary [Na+]
- hepatitis B & C screen
- malaria screen if travel abroad
- urine protein
- steroid-resistant nephrotic syn
- refer to paed nephrologist
- Mx
- oedema
- diuretics
- salt restriction
- ACEIs
- NSAIDs
- may also reduce proteinuria
- oedema
- Causes
- focal segmental glomerulosclerosis
- commonest
- familial or idiopathic
- prognosis
- 30% prog to renal failure in 5 years
- 20% respond to cyclophosphamide, ciclosporin, tacrolimus or rituximab
- recurrence post-transplant is common
- mesangiocapillary glomerulonephritis (membranoproliferative glomerulonephritis)
- more common in older kids
- prognosis
- decline in renal func over many years
- haematuria & low complement level present
- membranous nephropathy
- assoc w/ hep B
- may precede SLE
- prognosis
- most remit spontaneously within 5 years
- focal segmental glomerulosclerosis
- congenital nephrotic syn
- presents in 0-3 month olds
- recessive inheritance
- commonest type
- high in Finns
- in UK common in consangineous families
- assoc w/
- high mortality
- due to complications of hypoalbuminaemia
- low albumin so severe that unilat nephrectomy may be needed to control it
- fb dialysis for renal failure, done til child large & fit for renal transplant
- low albumin so severe that unilat nephrectomy may be needed to control it
- due to complications of hypoalbuminaemia
- high mortality
- test oedematous child for proteinuria to diagnose
- heavy proteinuria ->
Informações
- Descrição
- Paediatrics (kidneys ) Mapa Mental sobre proteinuria, criado por v.djabatey em 30-01-2014.
- Criado por
- v.djabatey
- Visualizações
- 48
- Tags
- Avaliação