
Apuntes
Chest Pain/Dyspnea Case 1
Contenido del apunte (5)
Página 1
Obese 39yof, presenting with chest pain and shortness of breath for 6 hours.
HR/Rhythm: sinus tach 122
BP: 100/62
RR: 32
SpO2: 85% --> 94% on NRB 15Lpm
T: 37
Glucose: 100
Weight: 100kg
Critical actions:
Obtain full set of VS including temp, glucose and WEIGHT (patient may need weight based medications e.g. heparin drip)
place patient on monitor
set BP cuff to cycle q3 mins
establish 2 large bore IVs
move to resus bay if available
Página 2
HPI: pain is constant, severe, sharp, R sided, nonradiating, worsens with inspiration. Feels very short of breath. Recently returned from flight to Japan. No recent surgeries, no h/o clots, no h/o cancer. No family hx of clots. No hemoptysis
PMH: HTN, DM, smoker 1ppd, takes OCPs
Physical Exam:
Gen: appears tachypneic and in pain
Lungs: clear
CV: tachy but otherwise unremarkable
Abd: unremarkable
Ext: pulses equal. BLE 1+ edema, RLE tenderness in the popliteal fossa.
(WYD)
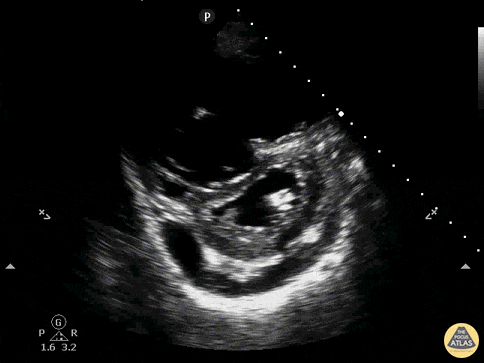
[Ultrasound images]
Critical Actions:
obtain pertinent history, perform physical exam with attention paid to lungs
for MS4s/Interns: discuss Wells criteria and when to use wells and PERC
Perform BSUS of heart, lungs and RLE (DVT)
obtain EKG
order CXR but verbalize to not wait for CXR before proceeding to CT
order CT PE study
start heparin drip based on U/S, if not already started empirically
order labs: CBC, BMP, Troponin, BNP, VBG
notify pharmacy of potential need for tPA
Discuss reasoning for ordering the BNP (assess for R heart strain) and troponin (assess for heart strain and severity of PE)
Discuss PESI score and the anticoagulation regimens - heparin drip vs enoxaparin vs tPA
Discuss accuracy of POC US for PE
Página 3
CT says there's two traumas that are already in line for the scanner
While awaiting CT, patient goes into AF RVR rate 170s, BP drops to 86/40
[sedate and cardiovert, ineffective until cardioverting at 200J ]
BP improves to 98/60
[echo ultrasound images]
[LE compression ultrasound images]
Critical actions:
recognize need for electrical cardioversion
recognize the potential need to infuse tPA if BP does not improve after cardioversion
should have pharmacist prepare the tPA and have it ready to go if need be
discuss sedation regimens for cardioversion (see below, reference: mostly uptodate)
methohexital IV:
dose: 0.75-1.5mg/kg (according to retrospective review of sedation in ED, avg dose 1.4mg/kg)
onset: immediate
duration: 5-15 mins
etomidate IV:
dose: 0.15-0.3 mg/kg
onset: 30-60s
duration: 2-15 mins
metabolism: 76% protein bound, primarily hepatic metabolism
ketamine IV:
dose: 1-2 mg/kg
onset: 30-60s
duration: anesthetic effect 5-10mins, full recovery 1-2 hours
midazolam IV:
dose: 0.5mg-2mg initial dose then additional doses q2-3min. Usual required dose 2.5-5mg
onset: 3-5 min
duration: 1-2 hours (dose dependent)
Discuss PESI score and the anticoagulation regimens - heparin drip vs enoxaparin vs tPA
Discuss accuracy of POC US for PE
Página 4
If intern: patient codes in the ED prior to going to CT scanner
If senior resident: You go with the patient to CT scan, as the patient is on the table in the scanner, you see the monitor go into VT.
Critical actions in the following order:
start CPR and direct someone to place CPR board on stretcher
connect pads to defibrillator and charge defibrillator
place pads on patient
pulse and rhythm check [pulseless VT]
deliver shock
pull patient onto stretcher with CPR board
??turn heparin drip off so tPA can be given??
resume compressions
return to ED with patient and compressions ongoing
delegate someone to charge the defibrillator at 1:50
Once returned to ED it has been approx 2 minutes.
Critical actions in the following order:
charge defibrillator at 1:50
pulse and rhythm check [pulseless 3rd degree heart block]
resume CPR and disarm defibrillator
push 1mg epinephrine
hang tPA [discuss tPA dosing and continuing compressions for several minutes even if ROSC achieved]
_____ does tPA need to be delivered through CVC?
intubate patient
place femoral arterial line [link to art line video]
approaching the next 2 minute mark.
charge defibrillator at 1:50
pulse and rhythm check [sinus tach 128 with a pulse]
evaluate BP [60/38]
start norepinephrine drip @10mcg/min (can titrate up or down as needed)
evaluate mental status [localizes to pain but does not follow commands]
put on ventilator and start fentanyl drip for analgesia
start post-arrest care (does not have to be in order):
elevate head of bed to prevent vent associated pneumonia
obtain CXR to confirm tube placement
obtain repeat EKG
place NGT
initiate hospital's hypothermia protocol
admit to ICU
For bonus points:
if patient were to be refractory to the norepinephrine, what would you do?
max norepi, start vaso, start epi drip
how do you make a dirty epinephrine drip?
inject 1mg of the 0.1mg/mL (code) epinephrine into 1L bag of NS to give 1mcg/mL concentration of epinephrine
If patient remained profoundly hypotensive despite multiple pressors and there was still evidence of R heart strain on POCUS, what would you do?
start VA ECMO and have patient go for either catheter directed lysis or thrombectomy depending on the preference of the surgeon/IR team
Página 5
Pulmonary Embolism Management References/Resources:
Información
- Descripción
- Pulmonary Embolism Case
- Creado por
- Zander Prewitt · abr 2019
- Actualizado
- 30 abr 2019
- Visitas
- 94
- Etiquetas
- Valoración