
Flashcards
SU5505 Midterm Test
Flashcards do conjunto (41)
- 1List the 7 steps for Spirometry interpretation1. Six seconds long
2. Flow volume loop shape
3. FEV1/ FVC >70%
4. FVC > 80%
5. FEV1 > 80%
6. ID pattern
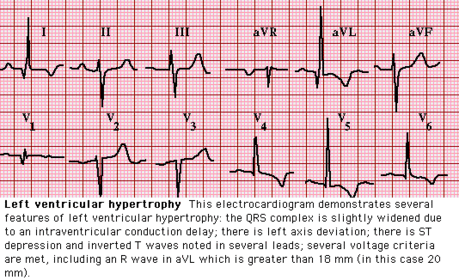
7. Classify Severity - 2—LV hypertrophy: Increased R wave peak time:Left ventricular strain pattern:
*T wave inversion in the lateral leads V5-6* - 3Proventil HFA, ProAir, Xopenex is an example of ?SABA: Short- acting beta agonist ( short-acting bronchodilator)
- 4Aerospan, Flovent, Pulmicort and Qvar are examples of ?ICS- inhaled corticosteriods
- 5Foradil and Serevent are examples of ?LABA
- 6Atrovent, Combivent, Tudorza, and Spiriva are examples of ????Anticholinergics
- 7Advair, Breo, Dulera, and Symbicort are examples of?????Combo Medications: ICS and LABA
- 8Gold Standard DX for COPDSpirometry
- 9Diagnostics for Asthma20% variation in PEF (liters/mins)
Spirometry - 10Peak Flow Measurement 1. Stand___ 2. Cursor at _____ 3. Blow _____& _____ 4. Best of _____ attempts 5. Record _______ best.1. Stand up
2. Cursor at zero
3. Blow hard & fast
4. Best of 3 attempts
5. Record personal best. - 11Deaths from Asthma is best reduced by.... 1. written _______ plan 2. Oral _______ prior to severe attack 3. Use of Peak _____ meter ( Liters/mins.)1. written Action plan
2. Oral corticosteroids prior to severe attack
3. Use of Peak Flow meter ( Liters/mins.) - 12This type of Asthma Medication benefits those who are obese, smoke, or triad of asthmaLeukotriene medications: Singulair

- 13Triad Asthma criteriaNasal polyps
ASA sensitivity
Severe asthma - 14Asthma Control Test A score of ____ is controlled asthmatic.<19 not controlled
>20 is well controlled - 15What medication increase the risk of pneumonia in COPD patients?Corticosteroid do not cause Pneumonia or osteoporosis in asthmatics, however those with COPD .
- 16Peak Flow Monitoring 1. best lung function __ pm & lowest __am 2. ___% fluctuation is healthy 3. ___% variation DX of asthma 4. NOT USED FOR _____.1. best lung function 4 pm & lowest 4am
2. 8% fluctuation is healthy
3. 20% variation DX of asthma
4. NOT USED FOR COPD.
* effort dependent* - 17Schedule of Asthma Follow up 1st F/U within ____ month. Routine visit ___ to ___ months.1st F/U within 1 month.
Routine visit 1 to 6 months.
*assess correct use of inhaler, spacer, peak flow meter (PFM)* - 18COPD is not fully ________.COPD is not fully reversible.
Preventable and treatable. - 19Productive cough for 3 consecutive months for 2 consecutive years.Chronic Bronchitis
- 20COPD SOB manifest at __ % of lung functionSOB manifest at 50 % of lung function
- 21PATHO of COPD 1. increases in ______ and neutrophils. 2. ______ hyperplasia. 3. Bronchiolar ______. 4. Peribronchiolar ________. 5. Loss of _______ attachments.1. increases in macrophages and neutrophils.
2. bronchiolar hyperplasia.
3. Bronchiolar edema.
4. Peribronchiolar fibrosis.
5. Loss of alveolar attachments. - 22COPD presentation 1. SXS present at 1 PPD for > ____ years. 2. manifestation at _____ decade: chronic cough after viral infx. 3. Dypsnea at ___ or ____ decade.1. SXS present at 1 PPD for > 20 years.
2. manifestation at fifth decade: chronic cough after viral infx.
3. Dypsnea at sixth or seventh decade. - 23COPD Physical Exam 1. ______ and _____ expiration. 2. Chest wall _______inflation. 3. Distant _____ and ____ sounds. 4. Pursed ____ breathing. 5. Cor ______: JVD, edema, heptomegaly1. Slow and prolonged expiration.
2. Chest wall hyperinflation.
3. Distant heart and breath sounds.
4. Pursed lip breathing.
5. Cor pulmonale: JVD, edema, heptomegaly - 24COPD Chest XrayCOPD Chest XRAY
1. flat diaphragm
2. tear shaped heart
3. Increase AP/ retrosternal airspace
*Emphysema: pruning of pulmonary vessels and bullae*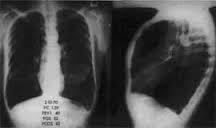
- 25COPD assessment test (CAT) < 10 > 10Group A: low risk, less SXS (CAT< 10)
Group B: low risk, more SXS (CAT>10)
Group C: high risk, less SXS (CAT< 10)
Group D: high risk, high SXS (CAT >10)
*GROUP B &D: 5x risk for cardiovascular dx and cancer* - 26COPD Treatment : 1st Choice Group A and BGroup A: SAAC (Atrovent/ combivent) or
SABA (Proair, Proventil)
Group B: LAAC (spiriva/anora ) or LABA (Foradil/ Serevent)
* add- on exercise and pulmonary rehab* - 27COPD 1st choice treatment for Group C and DGroup C: LAAC (Anora/Spriva) and (+)LABA ( Foradil/Serevent)
Group D: ICS (Flovent/ Pulmicort) and(+)LABA or LAAC
* add- on exercise, oxygen therapy pulmonary rehab* - 28Spirometry List the predicted values/ criteria.1. Gender
2. Race
3. Age
4. height - 29____ _____ _____ (FVC) maximum volume of air exhaled _____ _____ ______ (FEV1): volume exhaled during the first second.Forced Vital Capacity: maximum volume of air exhaled
Forced Expiratory Volume: volume exhaled during the first second. - 30Normal Lung Volume Values FEV / FVC1 >____% FVC > _____% FEV1 > _____%Normal Lung Volume Values
FEV / FVC1 >70%
FVC > 80 %
FEV1 > 80 % - 31Obstructive vs Restrictive Disease pattern Obstructive: FEV1 / FVC _____, FVC _____ FEV1_____Obstructive: FEV1 / FVC down , FVC normal, FEV1 down
- 32Obstructive vs Restrictive Disease pattern Restrictive : FEV1 / FVC _____, FVC _____ FEV1_____Restrictive : FEV1 / FVC normal , FVC down FEV1 down
Combined:FEV1 / FVC down, FVC down, FEV1 down - 33Obstructive Lung DiseasesAsthma
COPD
Bronchiectasis
Cystic Fibrosis - 34Obstructive Reversibility defined as a change of ____% post Albuterol (SABA) or Ipratropium (Atrovent) and increase of _______ mL.Obstructive Reversibility
defined as a change of 12 % post Albuterol (SABA) or Ipratropium (Atrovent) and increase of 200 mL. - 35CAD inflammation marker. < 1 low risk for CV events 1-3 intermediate >3 highHigh Sensitivity CRP (hs-CRP)
- 36Which is an independent risk factor for CHD? HDL, LDL, TriglyceridesElevated Triglycerides are an independent risk factor for CHD. Low HDL independent predictor
(inverse relationship)
Normal < 150
Borderline 150-199
High > 200- increased risk for pancreatitis - 37What are the criteria for Metabolic syndrome? Metabolic syndrome- 3+SXS to DX1. Abdominal obesity (M >40in. W> 35)
2. Triglyceride> 150 mg/dl
3. Low HDL ( M<40, W< 50)
4. High BP ( 130/85)
5. Fast blood glucose (> 110) - 38DXD for Dyslipidemia1. DM
2. Hypothyroidism
3. obstructive liver dx
4. Chronic renal failure
5. Protease inhibitor ( HIV meds)
6. BBB, HCTZ= low HDL
7. Prednisone ( high TG)
8. Tamoxifen- high TG ( Breast CA) - 39—Non occlusive thrombus
unstable angina and non-Q wave MI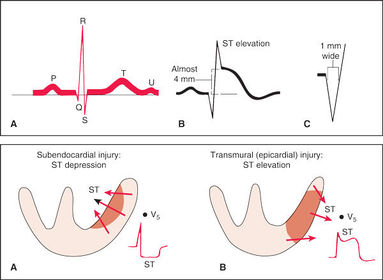
- 40—Occlusive thrombus
Q wave MI and sudden death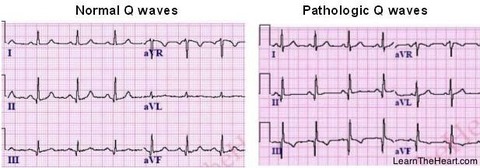
- 41—