
Mindmap
Liver Pathology
Inhalt der Mindmap
Liver Pathology
Functions
- Portal Vein
- Metabolic processing
- Dietary carbohydrates
- Lipids
- Amino Acids
- Vitamins
- Amino Acids
- Lipids
- Dietary carbohydrates
- Detoxification, Degredation &/or Biliary Excretion
- Endogenous wastes
- Toxic molecules
- Hormones
- Xenobiotic compounds
- Biotransformation of drugs
- Xenobiotic compounds
- Detoxified chemical wastes
- Hormones
- Bile salts, Bilirubin, cholesterol, HCO3-, H2O
- Toxic molecules
- Endogenous wastes
- Blood from Intestinal tract
- Processing & Activation of some xenobiotic agents
- Pro-drugs
- Ex. Cytochrome p450
- Pro-drugs
- Metabolic processing
- Synthesis of Plasma Proteins
- Albumin
- Globulins
- Clotting factors
- Complement proteins
- Other serum transport/ binding proteins
- Globulins
- Albumin
- Storage
- Glycogen
- Fats
- Fe
- Cu
- Vitamins
- Ex. Vitamin A (stored in Hepatic stellate cells)
- Vitamins
- Cu
- Fe
- Fats
- Glycogen
- Processing of Vitamin D
- With Kidneys
- Removal of Bacteria & Erythrocytes
- Kupffer cells
- Removal of Erythrocytes also occurs in the Spleen
- Portal Vein
Clinical Signs of Liver Disease
- Jaundice/ Icterus
- Accumulation of bilirubin in the body
- Mechanism
- Pre-Hepatic
- Excessive breakdown of Erythrocytes
- Liver is overwhelmed & cannot excrete the bilirubin fast enough
- Ex. IMHA (Immune mediated Haemolytic Anaemia)
- Liver is overwhelmed & cannot excrete the bilirubin fast enough
- Excessive breakdown of Erythrocytes
- Post-Hepatic
- Physical obstruction of bile outflow
- Damage, disease, compression or obstruction of the gallbladder or common bile duct
- Prevents Bile from being excreted into the small intestine (Cholestasis)
- Ex. Gallstones, compressive tumor
- Prevents Bile from being excreted into the small intestine (Cholestasis)
- Damage, disease, compression or obstruction of the gallbladder or common bile duct
- Physical obstruction of bile outflow
- Hepatic
- Liver is diseased & cannot excrete even the normal bilirubin load
- Ex. Cirrhosis
- Liver is diseased & cannot excrete even the normal bilirubin load
- Pre-Hepatic
- Oedema/Ascites/Anasarca
- If the liver is unable to synthesize the normal plasma proteins, there will be a reduction in plasma oncotic pressure
- Ex. Decrease in serum Albumin, Decrease in Oncotic pressure
- Fluid moves out of circulation => Fluid accumulates in the body cavities & subcutaneous spaces
- If the liver is unable to synthesize the normal plasma proteins, there will be a reduction in plasma oncotic pressure
- Coagulation (Clotting) Disorders
- If liver is unable to produce sufficient clotting factors, fibrinolytic proteins, complement proteins & acute phase proteins:
- => Poor or inappropriate Haemostasis & immune function
- Risk of Haemorrhage after liver biopsy
- Paradoxial balance
- Liver products
- Pro-coagulation
- Lack of Anti-clotting factors
- Anti-coagulation
- Lack of clotting factors
- Pro-coagulation
- Liver products
- => Poor or inappropriate Haemostasis & immune function
- If liver is unable to produce sufficient clotting factors, fibrinolytic proteins, complement proteins & acute phase proteins:
- Hepatic Encephalopathy
- Liver usually converts ammonia into urea (excreted by the kidneys)
- NH3 produced in intestine by bacteria
- Liver disease:
- Reduced ability to detoxify &/or remove nitrogenous compounds from the body
- Increased [NH3] & other toxic substances (Mn?) in the blood
- => Impairs brain function
- =>Status spongiosus of white matter in CNS
- Multiple fluid filled spaces of microscopic size in cerebral white matter
- =>Status spongiosus of white matter in CNS
- Toxicity
- => Impairs brain function
- Increased [NH3] & other toxic substances (Mn?) in the blood
- Reduced ability to detoxify &/or remove nitrogenous compounds from the body
- Liver usually converts ammonia into urea (excreted by the kidneys)
- Metabolic disease & dysfunction
- Liver disease (Reduced ability to):
- Process dietary components delivered from the portal blood
- Store Glycogen, fat & vitamins
- Detoxify endogenous or exogenous toxins
- Implications for drug selection, administration & dosage
- Liver disease (Reduced ability to):
- Jaundice/ Icterus
Incidental Post-Mortem Changes
- Prone to rapid PM change:
- Composition
- Vascularity
- Proximity to the intestine
- Vascularity
- Composition
- Softening & increased friability
- Production of gas bubbles (Putrefactive bacterial fermentation)
- Black discoloration (bacterial breakdown of Hb)
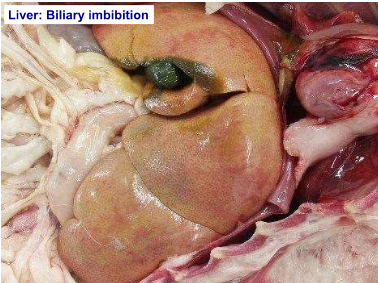
- Green discoloration (Bile leakage)
- Biliary Imbibition
- Microscopically:
- Dissociation of hepatocyte cords
- Pyknosis of nuclei
- Lysis of hepatocytes
- Pyknosis of nuclei
- Dissociation of hepatocyte cords
- Prone to rapid PM change:
Hepatic Degeneration
- Hydrophobic Degeneration (Cloudy swelling)
- Hepatocellular swelling
- Early manifestation of cell injury (Hypoxia, toxins)
- Hepatocytes unable to maintain normal homeostatsis
- NRG production decreases => membrane pumps fail => lack of ATP
- Intracellular accumulation of H2O
- Swelling of mitochondria & other organelles
- Intracellular accumulation of H2O
- NRG production decreases => membrane pumps fail => lack of ATP
- Hepatocytes unable to maintain normal homeostatsis
- Cytoplasmic vacuoles may develop if severe
- Early manifestation of cell injury (Hypoxia, toxins)
- Reversible
- Hepatocytes not damaged or destroyed
- Hepatocellular swelling
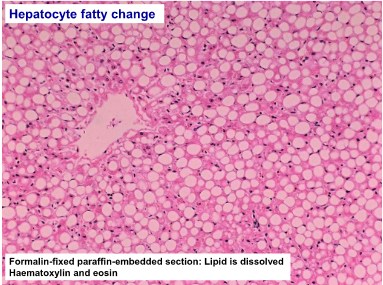
- Fatty Change
- Lipid accumulates in cytoplasm of injured hepatocytes
- Inability to metabolize/function normally (Hypoxia, toxins)
- I.e. Conversion of FFA => TAG
- Often more severe damage than in hydropic degeneration/cloudy swelling
- Reversible (If inciting cause is removed/corrected)
- Fatty change (due to hypoxia/toxins) may eventually lead to lipidosis/steatosis when severe &/or chronic
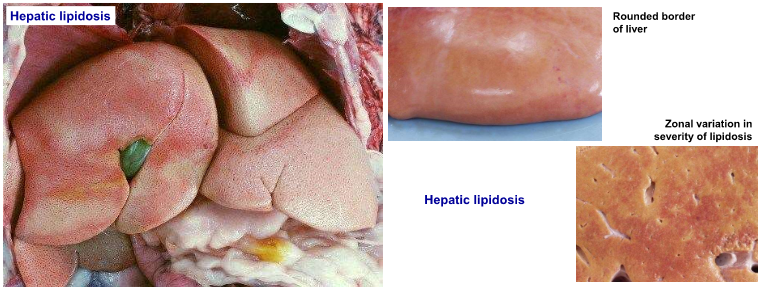
- Hepatic Lipidosis/Steatosis
- Hepatocytes distended by discrete circular lipid vacuoles (displace nucleus to periphery of cell)
- Due to massive uptake of fatty acids from the bloodstream following excessive mobilisation of adipose tissue reserves => Overloads metabolic capacity of hepatocytes & further inhibits their function
- Pale, yellow, friable, "greasy" liver
- Causes:
- Starvation
- Equine hyperlipaemia
- Negative NRG balance in cattle
- Feline hepatic lipidosis
- Feline hyperlipaema
- Diabetes mellitus (Glycogen vs. lipid)
- Hypoxia/toxins => Lipidosis
- Diabetes mellitus (Glycogen vs. lipid)
- Feline hyperlipaema
- Feline hepatic lipidosis
- Negative NRG balance in cattle
- Equine hyperlipaemia
- Starvation
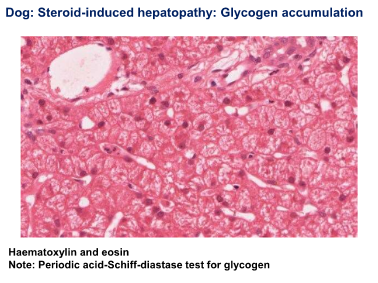
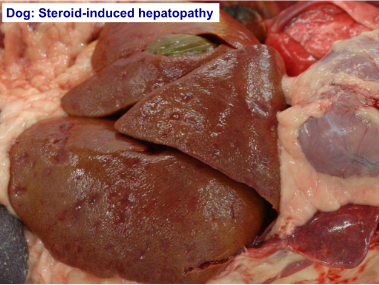
- Glycogen (Steroid Induced Hepatopathy)
- Excessive accumulation of glycogen in the presence of high levels of corticosteroids
- Exogenous corticosteroids
- E.g. Dexamethasone (iatrogenic)
- Endogenous corticosteroids
- Hyperadrenocorticism
- Diabetes mellitus
- Glycgoen &/or fat accumulations
- Diabetes mellitus
- Hyperadrenocorticism
- Exogenous corticosteroids
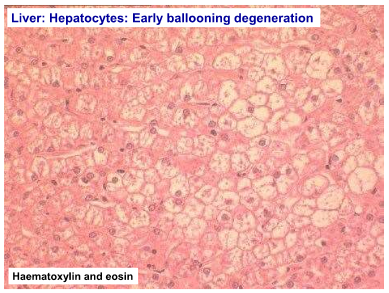
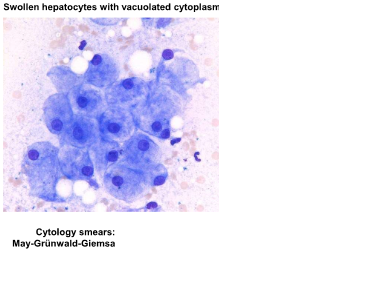
- Hepatocytes distended by floccular ("feathery") cytoplasmic vacuoles (do not displace the nucleus)
- Ballooning degeneration may occur
- Irreversible
- Excessive accumulation of glycogen in the presence of high levels of corticosteroids
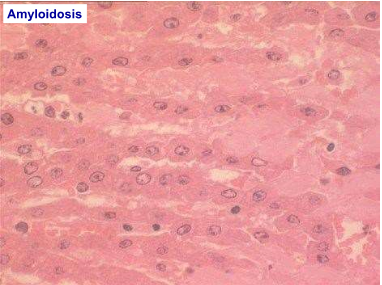
- Amyloidosis
- Primary
- Can be familial
- Shar pei dogs
- Abyssinian, Siamese & other exotic cats
- Secondary
- Chronic inflammation
- Gross pathology
- Liver is enlarged
- Pale & firm
- Rounded borders
- Pale & firm
- Liver is enlarged
- Histopathology
- Amyloid is deposited extracellularly around portal tracts & along sinusoids in the space of Disse
- Can also be deposited in kidneys, pancreas, blood vessels
- Amyloid is deposited extracellularly around portal tracts & along sinusoids in the space of Disse
- Special stains
- Congo red + Green birefringence
- Types:
- AA Type
- Derived from the inflammatory acute phase protein serum amyloid A
- AL Type
- Derived from Ig light chains
- ABeta type
- Derived from amyloid precursor protein & islet amyloid polypeptide (IAPP: Hormone produced by Beta cells in pancreatic islets of cats)
- AA Type
- Primary
- Hydrophobic Degeneration (Cloudy swelling)
Hepatic Necrosis
- Mode of action of agent
- Directly affects hepatocellular or biliary cells
- Secondary to interference with blood supply or biliary tract damage
- Severity & duration of action of agent
- Mild &/or short duration => Reversible change
- Severe, constant or repeated action => Irreversible change
- Route of Access of Agent
- Umbilical vein in foetus/neonate
- Portal Vein
- Hepatic Artery (O2)
- Transcoelemic
- Infections, neoplasms
- Biliary system
- Ascending infections
- Toxins
- Transcoelemic
- Hepatic Artery (O2)
- Portal Vein
- Umbilical vein in foetus/neonate
- Single-Cell Necrosis
- Coagulative necrosis of individual cells & their immediate neighbors
- Some forms of viral hepatitis e.g. Herpesvirus
- Focal Necrosis
- Usually a microscopic change in hepatocytes/biliary cells randomly distributed without obvious relationship to lobular pattern
- Can be of minimal clinical significance
- Viral & bacterial agents most common
- Zonal Necrosis
- Centrilobular (Periacinar) Necrosis
- Hepatocytes are vulnerable to Hypoxic damage (Chronic venous congestion; Anaemia) b/c of relatively low gradient of O2 in center of the lobule
- Also susceptible to toxic insult by toxins requiring hepatic biotransformation
- Hepatocytes are vulnerable to Hypoxic damage (Chronic venous congestion; Anaemia) b/c of relatively low gradient of O2 in center of the lobule
- Most common
- Periportal Necrosis
- Commonly seen in toxic damage where the toxin is preformed (closest to the incoming blood supply)
- Portal vein or Hepatic artery
- Commonly seen in toxic damage where the toxin is preformed (closest to the incoming blood supply)
- Centrilobular (Periacinar) Necrosis
- Massive Necrosis
- Complete necrosis of individual lobules (cells & connective tissue scaffold)
- May be isolated or multiple lobules
- More Serious insult &/or longer duration insult
- Does not neccessarily mean whole organ is affected
- Followed by "Post-necrotic lobular collapse" & fibrosis (due to loss of reticulin scaffold
- Ex. Hepatosis dietica (Vit. E deficiency - Pigs)
- Mode of action of agent
Response of Liver to Inflammation
- Hypertrophy of Hepatocytes
- Increase in size of surviving Hepatocytes: Increased amount of cytoplasm
- Regenerative Hyperplasia
- Nodular regeneration of existing mature hepatocytes in response to liver injury
- Ability to regenerate varies w/ species & age
- Hyperplasia may be diffuse, but often occurs as:
- Microscopic nodules (Micronodular Hyperplasia)
- Macroscopic nodules (Macronodular hyperplasia)
- Nodular regeneration of existing mature hepatocytes in response to liver injury
- Nodular Hyperplasia
- Common incidental finding in older dogs
- Discrete, unencapsulated nodules of hepatocytes which retain good architecture of hepatic lobules & hepatocyte cords
- Might be slightly vaculated
- No evidence of concurrent hepatic disease
- Not inflammatory
- Needs to be differentiated from macronodular regeneration & neoplasia
- Oval Cell Proliferation
- Regeneration of new hepatocytes & bile ducts by proliferation of bipotential stem cells ("Oval cells") located in the terminal bile ductules (canals of Hering)
- Oval cells = source of Hepatic Fibrosis
- Often just see proliferation of bile duct type cells
- i.e. more differentiated cells => biliary hyperplasia
- Regeneration of new hepatocytes & bile ducts by proliferation of bipotential stem cells ("Oval cells") located in the terminal bile ductules (canals of Hering)
- Hepatic Atrophy
- Atrophy of the whole liver, individual lobes or parts of lobes
- Pressure on liver parenchyma, e.g. External or internal space occupying lesions
- Anoxia/Hypoxia (Insidious O2 deprivation)
- Impairment of bile flow: Chronic biliary disease
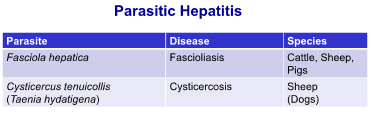
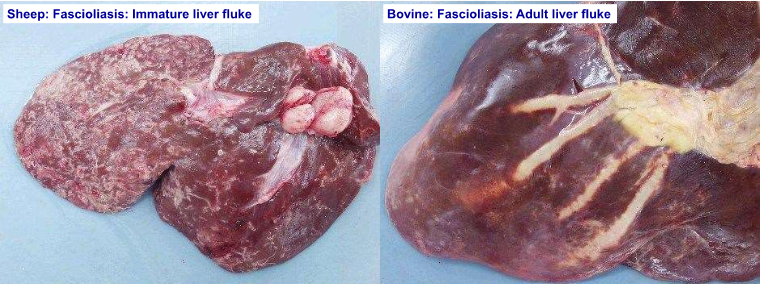
- Fasciola hepatica infestation (Cattle & Sheep)
- Cholestasis (Dogs & Cats)
- Fibrosis
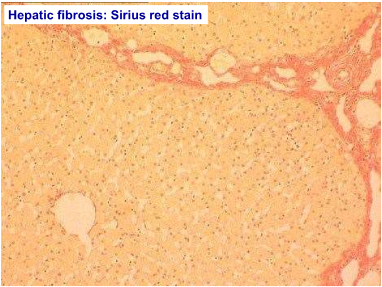
- Localized or generalized deposition of extracellular connective tissue matrix (fibrous/scar tissue) as a healing response to hepatic injury
- Centrilobular fibrosis
- Prolonged hypoxia, cell death & fibrosis of centrilobular zones
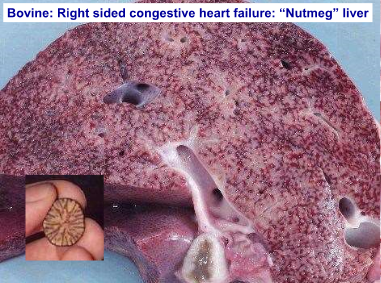
- Chronic venous congestion (Cardiac failure)
- Biliary Fibrosis
- Chronic periportal inflammation, cholangitis/cholangiohepatitis &/or biliary obstruction
- Usually fibrosis in portal areas
- Post-necrotic scarring
- Following a single episode of widespread (massive) hepatocellular necrosis
- Parenchyma & connective tissue scaffold (reticulin) are damaged
- Post-necrotic collapse
- Affected area cannot regenerate & is replaced by fibrous tissue
- Diffuse Hepatic Fibrosis
- On-going (Chronic) hepatocyte necrosis => Overwhelms the regenerative capacity
- Chronic toxic injury => Phenobarbital, copper-associated, chronic inflammation
- Widespread fibrous tissue deposition
- Deposition of connective tissue in space of Disse =>Loss of fenestrations in sinusoidal endothelium (capillarisation) => Reduced permeability => Impaired blood-hepatocyte exchange
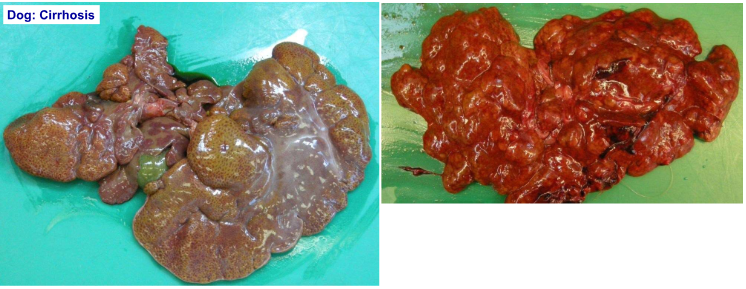
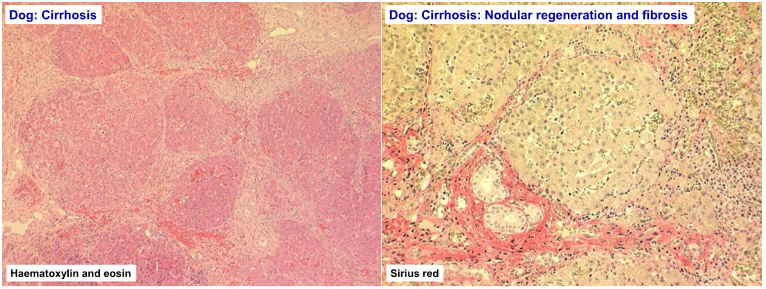
- Cirrhosis
- Diffuse, irreversible, end-stage hepatic disease
- Combination of:
- Hepatocyte destruction
- Nodular regeneration
- Biliary hyperplasia
- Bridging fibrosis (across portal areas)
- Portal-centrilobular vascular anastomoses
- Bridging fibrosis (across portal areas)
- Biliary hyperplasia
- Nodular regeneration
- Hepatocyte destruction
- Mostly seen in Dogs
- Hepatic insufficiency
- Liver failure
- Cause cannot always be established
- Liver failure
- Hepatic insufficiency
- Pathology:
- Hypoproteinaemia:Ascites
- Icterus: Hyperbilirubinaemia
- Coagulopathy
- Hepatic encephalopathy: NH3 retention
- 2ndary photosensitisation: Herbivores (Phylloerythrin not excreted due to cholestasis)
- Hypertrophy of Hepatocytes
Hepatic Mechanical Conditions (Trauma)
- Displacement
- Aquired displacement of Liver
- RTA
- Dogs, Cats
- Liver lobe torsion
- Dogs, Cats
- Rupture
- Compression trauma
- RTA (Dogs & Cats)
- Abuse (Ex. kicks: Dogs & Cats)
- Overlying (Piglets crushed by Sow)
- "High rise syndrome" (Dogs & Cats)
- Overlying (Piglets crushed by Sow)
- Abuse (Ex. kicks: Dogs & Cats)
- Displacement
Developmental Conditions
- Congenital Cysts
- Biliary cysts
- Isolated or clusters
- Formed from bile ductules
- Concurrent polycystic kidney disease
- Formed from bile ductules
- Pigs, Calves,Lambs, Kittens, Dogs
- Isolated or clusters
- Biliary cysts
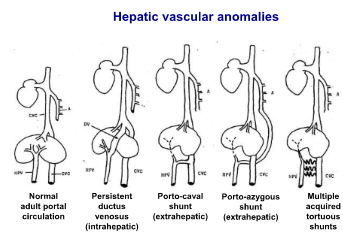
- Congenital vascular anomalies
- Portosystemic Shunts
- Anomalous development of portal vein
- Extrahepatic: Prior to liver
- Intrahepatic: Within liver
- Persistent ductus venosus
- Porto-caval; Porto-azygous
- Intrahepatic: Within liver
- Extrahepatic: Prior to liver
- Sxs (Dogs, Cats):
- Failure to gain weight, illthrift
- Hepatic encephalopathy
- Hypoplasia of liver & portal vein
- Histopath:
- Absence of portal venules (portal circulation diverted elsewhere)
- Proliferation of Hepatic arterioles
- Anomalous development of portal vein
- Primary portal vein hypoplasia
- Microvascular dysplasia
- Intrahepatic arteriovenous fistulae
- B/w Hepatic artery & portal vein
- Portosystemic Shunts
- Hepatic Displacement
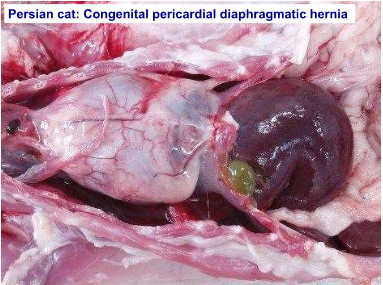
- Congenital pericardial diaphragmatic hernia
- Proplapse of one or more liver lobes into thorax (pericardial sec)
- Persian cats
- Opening in diaphragm to pericardial sac
- Proplapse of one or more liver lobes into thorax (pericardial sec)
- Congenital pericardial diaphragmatic hernia
- Biliary atresia
- Absence of bile ducts & ductules
- Absence of gallbladder
- Congenital Cysts
Acquired Disturbances of Hepatic Circulation
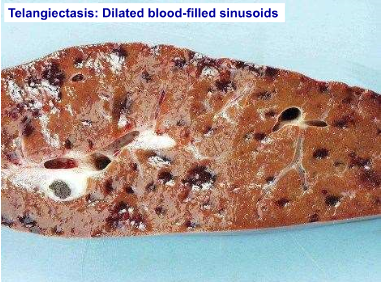
- Telangiectasis
- Dilation (ectasia) of groups of sinusoids
- Filled w/ blood
- Incidental finding
- Cattle, Cats
- Incidental finding
- Filled w/ blood
- Dilation (ectasia) of groups of sinusoids
- Vascular Obstruction
- Portal Vein
- Total rapid obstruction:
- Death as a result of hypovolemic shock (sequestration of blood in splanchnic bed)
- Medical Emergency
- Death as a result of hypovolemic shock (sequestration of blood in splanchnic bed)
- Partial or slowly progressive occlusion:
- Atrophy of lobes of liver, depending on development of accessory portal circulation
- When accessory circulation is inadequate, portal hypotension develops => Congestion & ascites
- Aquired porto-systemic vascular shunting
- Collateral blood vessels bypass the normal route of blood flow through the liver
- Secondary to Portal Hypertension
- Severe hepatic disease (fibrosis/cirrhosis)
- Occlusion of the hepatic vein or portal vein
- Arteriovenous fistulae
- Primary portal vein hypoplasia
- Arteriovenous fistulae
- Secondary to Portal Hypertension
- Dogs & Cats
- Caval obstruction/chronic venous congestion of HEART FAILURE does NOT result in acquired shunts (No pressure gradient, caudal venacava & hepatic circulation are equally affected)
- Collateral blood vessels bypass the normal route of blood flow through the liver
- Atrophy of lobes of liver, depending on development of accessory portal circulation
- Total rapid obstruction:
- Portal Vein
- Telangiectasis
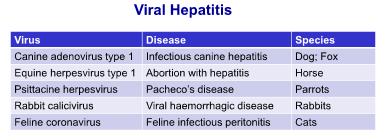
Hepatitis
- Acute Hepatitis
- Usually associated w/ hepatocellular necrosis
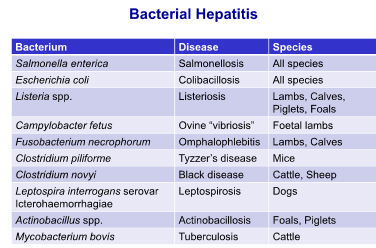
- Suppurative necrotizing hepatitis (Bacterial infections)
- Salmonellosis
- Eosinophilic hepatitis (Parasitic infections)
- Larval forms migrate through liver => Hepatitis
- Suppurative necrotizing hepatitis (Bacterial infections)
- Usually associated w/ hepatocellular necrosis
- Chronic Hepatitis
- Chronic inflammatory stimulus
- Fibrovascular hyperplasia (Granulation tissue)
- Nodular regeneration
- Fibrosis
- Cellular inflammatory infiltrates
- Lymphocytes & plasma cells (portal areas)
- Eosinophils (Portal areas)
- Granulomatous inflammation
- Cellular inflammatory infiltrates
- Fibrosis
- Nodular regeneration
- Copper-associated hepatopathy (Dogs)
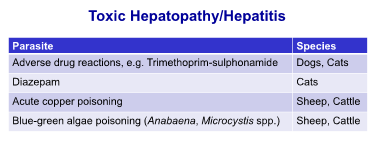
- Chronic copper toxicity (Sheep)
- Ragwort toxicity (Due to pyrrolizidine alkaloids) (Horses, Cattle, Sheep)
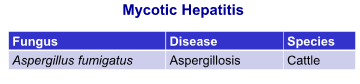
- Alfatoxins (aspergillus flavus) on stored grain (Pigs, Sheep)
- Ascaris suum (pigs)
- Milk spot liver
- Ascaris suum (pigs)
- Alfatoxins (aspergillus flavus) on stored grain (Pigs, Sheep)
- Ragwort toxicity (Due to pyrrolizidine alkaloids) (Horses, Cattle, Sheep)
- Chronic copper toxicity (Sheep)
- Chronic venous congestion w/ hepatocyte fatty degeneration & necrosis
- Cholangiohepatitis
- Inflammation of the biliary tree & hepatocellular parenchyma
- Inflammation starts in the bile ducts & extends into parenchyma
- Chronic fascioliasis in ruminants
- Bacterial cholangiohepatitis from ascending infections from the intestine to the bile ducts
- Cats: Chronic Cholangiohepatitis
- In association w/ chronic pancreatitis &/or enteritis
- => Triaditis (possibly due to common entry of bile & pancreatic ducts into the small intestine)
- In association w/ chronic pancreatitis &/or enteritis
- Cats: Chronic Cholangiohepatitis
- Bacterial cholangiohepatitis from ascending infections from the intestine to the bile ducts
- Inflammation of the biliary tree & hepatocellular parenchyma
- Acute Hepatitis
Biliary Disease
- Cholangitis
- Affects intra &/or extra Hepatic bile ducts
- Usually an ascending infection
- Chronic lymphocytic cholangitis (Cats)
- Excessive aggregation of lymphocytes in portal tracts, bile duct proliferation & portal fibrosis
- Possibly immune mediated
- Excessive aggregation of lymphocytes in portal tracts, bile duct proliferation & portal fibrosis
- Cholecystitis
- Inflammation of the gallbladder
- Acute or Chronic
- Ascending infection: Salmonella enterica
- Cystic mucinous hyperplasia
- Hyperplasia of the gallbladder & lining epithelium
- Abundant production of mucous
- Severe distension (mucocoele)
- Obstruction (RARE)
- Stenosis of the bile duct
- External compression
- Fibrosis, Inflammation, Tumors
- External compression
- Cholelithiasis
- Gall stones (Choleliths)
- Usually form in gallbladder
- Mixture: Bilirubin, Ca carbonate, glycoprotein
- Usually form in gallbladder
- Dogs, Cats
- Cattle (Incidental finding)
- Complete obstruction => Extrahepatic cholestasis => Jaundice
- Leakage of bile into portal areas => inflammation & fibrosis
- Gall stones (Choleliths)
- Cholangitis
Hepatic Neoplasia
- Hepatocellular carcinomas are more common than hepatocellular adenomas
- Cholangiocarcinomas & Cholangioadenomas - Tumors of the gallbladder (Uncommon)
- Vascular tumors - Haemangiosarcoma
- Metastatic neoplasia (To Liver)
- Ex. Pancreatic carcinoma, intestinal adenocarcinoma, splenic haemangiosarcoma
- Multicentric neoplasia
- Lymphoma or leukaemia
Bilder und Dateien der Mindmap
Informationen
- Beschreibung
- Doctorate Pathology (Systems Pathology) Mindmap am Liver Pathology, erstellt von melian.yates am 04/11/2013.
- Erstellt von
- melian.yates
- Aufrufe
- 265
- Tags
- Bewertung