
Karteikarten
BMS10-1025 - Regulation of cardiac function 2
Karten in diesem Stapel (24)
- 1Electrical signals transmit through the heart from the ....cardium to the ...cardiumEndocardium to Epicardium
- 2What is the conduction pathway through the heart, starting from the SA node?1. SA node
2. Atrial systole
3. Atria
4. AV node
5. Bundle of His
6. Left/right bundle
7. Purkinje Fibers - 3Excitation Contraction coupling refers specifically toevents at the neuromuscular junction where a motor fibre excites a muscle cell
- 4When an AP arrives at the T-tubule, which channels open? What happens after?L-Type Ca2+ channels
Ca2+ binds RyR receptors on sacroplasmic reticulum, Ca2+ release bu Sacro.retic, causing contraction - 5How is Ca2+ reuptaken?Circle pump and Na+/Ca2+ exchanger
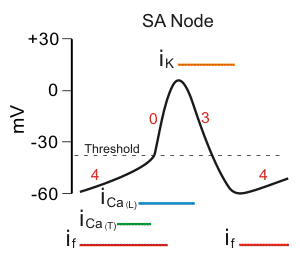
- 6In the first phase of depolarisation in the pacemaker potential (SA node), why is depolarisation so slow?1. Lack of Na+ channels, so Ca2+ depolarises instead
3. Transient Ca2+ channels open first
4. Then L-type Ca2+ channels open (slower)
5. Delayed rectifier K+ channel also slows - 7What initiates spontaneous depolarisation in the SA node?The funny currents, which are streams of Na+ that enable spontaneous depolarisation
- 8What channel is responsible for depolarisation (phase 0) of Pacemaker potential?L-type Ca2+ channels
- 9What channel is responsible for repolarisation (phase 3) of Pacemaker potential?Rectifier K+ channels
- 10What causes depolarization (phase 0) of the ventricular action potential?Opening of voltage gated Ca2+ channels
- 11After depolarisation (phase 0) in the ventricular action potential, why is there a partial repolarisation?Na+ channels close
- 12After partial repolarisation (phase 1) in the ventricular action potential, why is there a plateau (phase 2)?L type Ca2+ channels open, Ca2+ enters
- 13What eventually causes repolarisation (phase 3) in the ventricular action potential? What is phase 4?1. K+ outward current
2. Resting membrane potential - 14What is the ventricular action potential? What is the unique feature about its shape and why is it important?The spontaneous electrical activity in cardiac muscle cells
It is longer with a plateau (300ms) to PREVENT tetany in cardiac muscle - 15What is the rate of distribution of AP in the heart determined by? (2)1. Membrane capacitance
2. Number of connexons - 16How does AP distribute through myocytes?They are electrically coupled due to their intercalated discs
Ions move through the connexons - 17How do ionotropic factors (eg. noradernaline, B agonist) affect HR?They impact contractility
- 18How does noradernaline affect HR?Increases Ca2+, HR
- 19How do B-adrenergic agonists impact HR?Mimic SNS, increase HR
- 20How does ischemia hypoxia impact the heart?Lowers contractibility
- 21What do chronotropic drugs do? What is an example of a sympathetic drug? What about examples of parasympathetic drugs?Impact heart rate
1. Noradrenaline
2. Ach, B-blockers, Adenosine receptors - 22How do sympathetic chronotropic drugs increase HR?Creates a steeper pacemaker potential by incresing adenylyl cyclase, which increases activity of K+, funny, and Ca2+ channels
- 23What is the Staircase/Trepple Effect?Increase in HR means less time to remove Ca2+, which in turn increases contractile force
- 24How do parasympathetic chronotropic drugs decrease HR?Create a flatter pacemaker potential by inhibiting adenylyl cyclase, which lowers K+/funny/Ca2+ channels
Informationen
- Beschreibung
- the cardiac muscle action potential and associated ion currents+ explain how it differs between ventricular/ pacemaker tissues. origin of the heart-beat, and how its conducted through the heart. Explain how action potential couples to contraction, and how heart relaxes at end of systole. Explain how the ANS affects heart rate and force; give examples of chronotropic and inotropic agents and explain their actions. Describe the ECG
- Erstellt von
- Evian Chai
- Aufrufe
- 34
- Tags
- Bewertung